Lecture 7: Challenge to the System - Autoimmune Diseases part 2
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/11

There's no tags or description
Looks like no tags are added yet.
12 Terms
Breaking Tolerance: Environmental Factors
Infections:
Damaging barriers → release sequestered antigens
Superantigens → released by microbes→ don’t require costimulation
Significant Inflammation → increased cytokine production
Inflammatory cytokines can activate autoreactive lymphocytes
•Drugs- procainamide- can induce lupus
•Foods- gluten
•Appropriate immune response to microbial infection that mimic host antigens (antibody cross-reactivity). Guillain Barre--> human gangliosides that look like Camplobacter jejuni lipopolysaccharides→ microbial antigens evolve to resemble host antigens to evade host immune response
Molecular Mimicry

Breaking Tolerance: Susceptibility Genes
Multiple genes involved
• HLA Alleles (MHC):
Don't display self-antigens properly to maturing T-cells in thymus
Unusually high affinity for binding self-antigens
Cross-reactive antigen presentation (molecular mimicry)
Non-HLA Genes:
Rheumatoid Arthritis/Graves/Systemic Lupus Erythrematous: PTPN22 gene polymorphisms
Encodes Lyp: Lymphoid tyrosine phosphatase
Normal function: Brake on T-cell and B-cell receptor signaling to prevent overactivation
Mutation leading to autoimmunity: Gain-of-function- suppresses the immune receptor signaling too strongly; disrupts negative selection' process in thymus- autoreactive T-cells in circulation
Systemic Lupus Erythematosus (SLE)
Hallmark Characteristic:
Development of autoantibodies that bind dsDNA
Often preceded by viral illness
Range of symptoms and disease severity vary greatly among individuals
MHC genes & deficiencies in complement strongly associated (clearing apoptotic cells)
Major propensity for females (9:1 vs. males); role for hormones

Type 1 Diabetes Mellitus
Genetic Susceptibility:
HLA-DR3 & DQ8 genes
Polymorphisms in CTLA-4
* < 10% progress to clinical disease
Exogenous Triggers:
Viral infections: congenital rubella
Foods-early exposure cow milk proteins (bovine insulin)
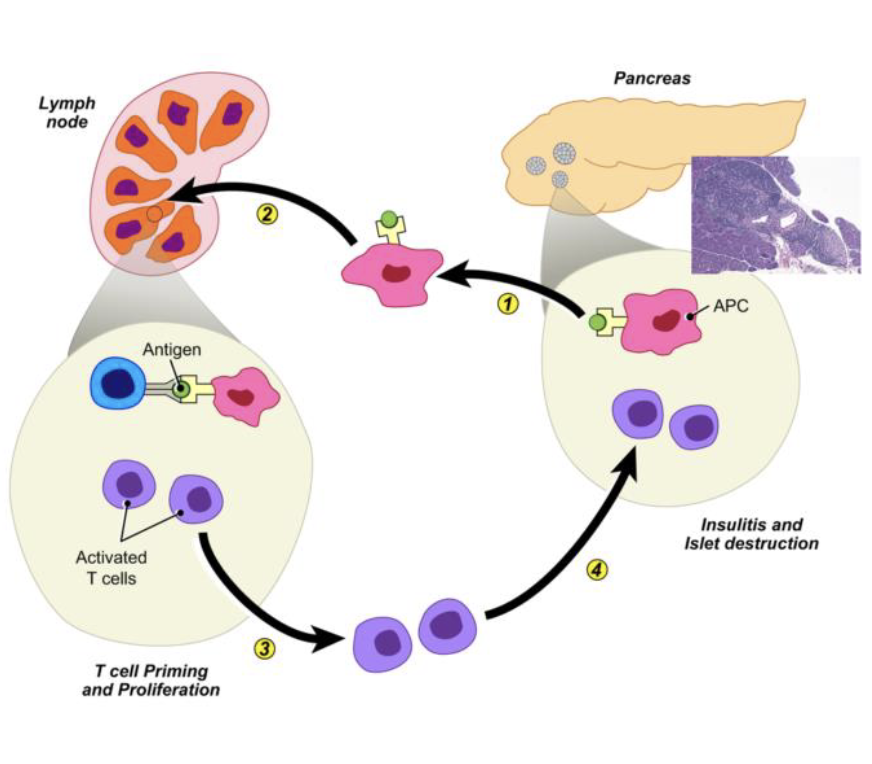
Environmental triggers in an individual with genetic predisposition leads to infiltration of the pancreatic islets with CD4+ and CD8+ T-cells, B-cells, and macrophages, and the production of autoantibodies
CD4+/CD8+ cells induce apoptosis of beta cells in pancreas
Clinical expression of disease only after 90% of B-cells in pancreas are destroyed.
Multiple Sclerosis
Demyelinating disease
Neurologic deficits: relapsing course followed by progressive phase
More common in females (2:1 vs. males)
More in temperate climates
Relapses after viral respiratory tract infections
Characterized by myelin-reactive T-Cells
Genetic predisposition. HLA-DR2 and DQ6

Celiac Disease
Genetically predisposed individuals
Environmental cause is known: Gluten
Gliadin-primary antigen leading to inflammation
HLA phenotype: HLA-DQ2 or DQ8-–necessary for development; not sufficient for developing disease

Population Based Surveillance
NHANES serum data to assess prevalence of autoimmunity in the US
Thyroid autoantibodies present in 18% of US adults, 10 % of younger adults and 25% of older adults
32% of adults >60 years old had at least one of the 4 autoantibodies studied:
Rheumatoid factor
Anti-thyroidoglobulin or anti-thryroperoxidase,
Anti-tissue transglutaminase autoantibodies
Estimated Prevalence of Antinuclear Antibodies
*Frequent screening assay for autoimmune diseases
Period 1: 1988-1991
Period 2: 1999-2004
Period 3: 2011-2012

Autoimmune Disease: Diagnostics
Considerations:
Non-specific symptoms differ from individual to individual
Medical history, Physical examinations, Laboratory tests, Diagnostic Imaging, Biopsies
Historical starting point: Detection of autoantibodies:
Not sufficient to diagnose; define presence of autoimmunity
Oftentimes are excellent predictors of disease because of their persistence
Traditionally detection of antibodies using ELISA & Western Blotting
Can be expensive, time consuming, tests require expertise and not very sensitive
Autoimmune Disease: Therapeutics
Complement Dependent Cytotoxicity (CDC): Monoclonal antibodies engineered to bind specific antigens on surface of target T and B cells—activates the complement cascade→ destroy target cell
Antibody-dependent cellular cytotoxicity (ADCC): Monoclonal antibodies engage natural killer cells recognize and target T and B cells in antigen specific manner

Further Considerations of Autoimmune Disease
Understanding risk factors:
Changes in exposures to foods, air pollution, infections, stress, climate change
Difficult task to determine doses, duration and effects of environmental factors
Improve preventative approaches:
How?
Is this feasible based on the molecular basis of these types of diseases?