Endocrine (COMPLETE)
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/334

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
335 Terms
Where is the pituitary gland located?
In the sella turcica at the base of the brain
What are the two major divisions of the pituitary gland?
Anterior pituitary (adenohypophysis)
Posterior pituitary (neurohypophysis)
What is the embryologic origin of the anterior pituitary?
Derived from developing oral cavity epithelial cells
Specifically Rathke pouch
What is the embryologic origin of the posterior pituitary?
Develops from neural tissue extending from the hypothalamus
What does the anterior pituitary primarily do?
Produces hormones that stimulate the production of hormones from:
Thyroid
Adrenal
Gonads
Breast
What are the three major staining categories of anterior pituitary cells?
Basophils
Eosinophilic/acidophilic cells
Chromophobes
What is this?

Normal pituitary
What hormone does a somatotroph produce?
Growth hormone (GH)
What hormone does a lactotroph produce?
Prolactin (PRL)
What hormone does a corticotroph produce?
Adrenocorticotropic hormone (ACTH)
Pro-opiomelanocortin (POMC)
Melanocyte-stimulating hormone (MSH)
What hormone does a thyrotroph produce?
Thyroid-stimulating hormone (TSH)
What hormones do mammosomarotrophs produce?
GH
Prolactin
What hormones are produced by gonadotrophs?
FSH
LH
What does FSH do in women?
Stimulates the formations of graafian follicles in the ovary
What does LH do in women?
Induces ovulation
Formation of corpora lutea in the ovary
What does FSH/LH do in men?
Regulate spermatogenesis
Testosterones production

What is this showing?
Normal anterior pituitary gland
Basophilic cells (blue)
Thyrotroph, gonadatroph, corticotroph
Eosinophilic cells (red)
Somatotroph, lactotroph
Chromophobes (yellow)
Non-staining → no hormones
What is the major distinction between anterior and posterior pituitary hormone production?
Anterior pituitary → Synthesizes and secretes its own hormones
Posterior pituitary → Stores and releases hormones synthesized in the hypothalamus
What is the posterior pituitary composed of?
Modified glial cells and axonal processes extending from the hypothalamus
Which two hormones are stored and released by the posterior pituitary?
ADH (vasopressin)
Oxytocin
Where are ADH and oxytocin synthesized?
In the hypothalamus
What is the major effect of ADH?
Promotes renal water reabsorption
What happens when ADH production/release is deficient?
Diabetes insipidus
Characterized by excessive urination due to inability to adequately concentrate urine
Kidneys cannot resorb water from water
What happens with excessive ADH secretion?
SIADH — Syndrome of inappropriate ADH secretion
ADH overproduction — Excessive renal reabsorption of water
What malignancy is classically associated with ectopic ADH production?
Small-cell carcinoma of the lung
What are the three major ways pituitary tumors can cause disease/tumors?
Local mass effects
Excess hormone production
Decreased hormone production
What is the difference between a functioning and nonfunctioning pituitary tumor?
Functioning → Produces excess biologically active hormone
Nonfunctioning → Does NOT produce clinically significant excess hormone and often presents because of mass effect (LARGE at discovery)
What age group is typical for pituitary tumors according to the lecture?
Approximately 35–60 years old
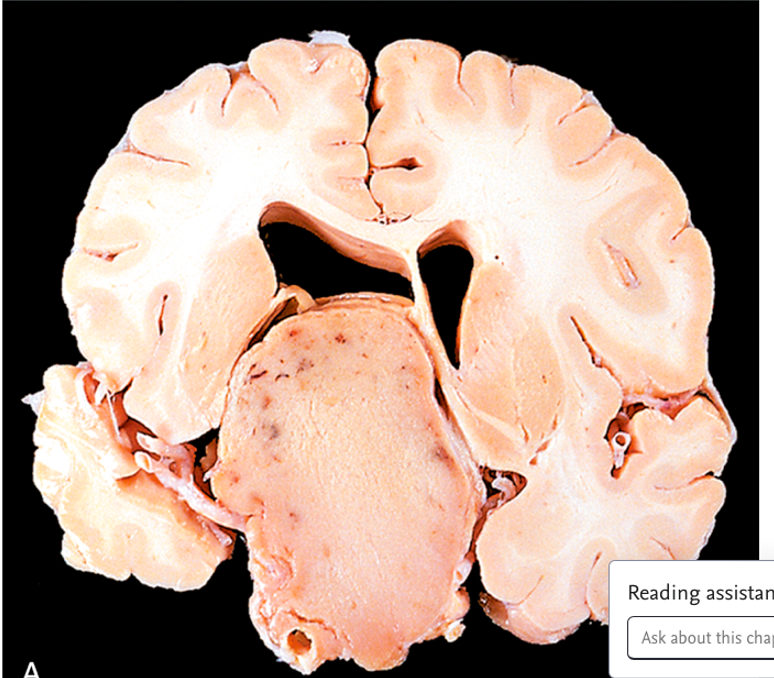
What is this showing?
A typical pituitary adenoma

What is this historically showing?
Pituitary adenoma
Large, nonfunctioning adenoma
(Notice the ONE cell type)
What is another word for an pituitary adenoma?
Pituitary neuroendocrine tumors (PitNETs)
Pituitary neuroendocrine tumors primarily arise from which part of the pituitary?
The anterior pituitary
What is the most common functional consequence of pituitary adenomas?
Hyperpituitarism
Excessive production of pituitary hormones
What other major pituitary pathologies besides adenomas are mentioned in the lecture?
Hyperplasia
Carcinoma
What is a pituitary microadenoma?
A pituitary adenoma less than 1 cm in diameter
What is a pituitary macroadenoma?
A pituitary adenoma 1 cm or larger
What is a major local mass effect of a large pituitary tumor?
Compression of surrounding structures
Particularly the optic chiasm → Cause bitemporal hemianopia
What is the most common functioning pituitary adenoma?
Prolactinoma (lactotroph adenoma)
What hormone is released by prolactinoma/lactotroph adenoma?
Prolactin
What are the classic syndromes of prolactinoma/lactotroph adenoma?
Galactorrhea
Amenorrhea (females)
Sexual dysfunction
Infertility
What does a somatotroph adenoma secrete?
Growth hormone (GH)
What are the classic syndromes of somatotroph adenoma?
Gigantism (children)
Acromegaly (adults)
What hormones are released in excess by mammosomatotroph adenoma?
GH
Prolactin
What are the classic syndromes of mammosomatotroph adenoma?
Combined features of GH and prolactin excess
What hormones are released by corticotroph adenoma?
ACTH
Other POMC-derived peptides
What are the classic syndromes of corticotroph adenoma?
Cushing syndrome
Hyperpigmentation (light-skinned individuals)
What hormone is released by thyrotroph adenoma?
TSH
What is the classic syndrome of thyrotroph adenoma?
Hyperthyroidism
What is the key distinction between Cushing disease and Cushing syndrome?
Cushing disease → Specifically refers to a pituitary ACTH-secreting tumor
Cushing syndrome → Refers to excess cortisol from any cause
What hormones are secreted by gonadotroph adenomas?
FSH
LH
What are the classic syndromes of gonadotroph adenomas?
Ovarian hyperstimulation
Menstrual irregularities in women
Testicular enlargement in males
Precocious puberty in adolescents
What is a null cell pituitary adenoma?
A pituitary tumor that lacks evidence of a specific hormone-producing cell lineage
Is generally nonfunctioning
What distinguishes a pituitary carcinoma from a pituitary adenoma/PitNET?
Metastatic spread establishes the diagnosis of carcinoma
What are the two major disorders associated with abnormal ADH secretion?
Diabetes insipidus → too little ADH
SIADH → too much ADH
What can cause ADH deficiency?
Neoplasms or inflammation
Involving the hypothalamic/posterior pituitary system
What is the basic gross anatomy of the thyroid?
Two lobes
Connected via an isthmus
Located below and anterior to the larynx
What is the basic structural unit of the thyroid?
The thyroid follicle
What type of cells line thyroid follicles?
Cuboidal OR low-columnar follicular epithelial cells
What protein is synthesized by thyroid follicular cells and stored within follicles?
Thyroglobulin
In what form is thyroglobulin stored?
As colloid within thyroid follicles
Where are thyroid hormones produced?
Produced within the follicular epithelial cells
Using thyroglobulin within the follicle
Which thyroid cells produce calcitonin?
Parafollicular C cells
What is thyrotoxicosis?
A hypermetabolic state caused by elevated circulating thyroid hormone levels
What are the three major causes of hyperthyroidism?
Graves disease
Hyperfunctioning multinodular goiter
Hyperfunctioning thyroid adenoma
What happens to TSH in primary hyperthyroidism?
TSH decreases because of negative feedback from elevated thyroid hormone
What is the single best laboratory test for evaluating thyroid function?
Serum TSH
What are common skin findings in hyperthyroidism?
Skin is soft, warm, and flushed
Due to:
Increased blood flow
Heat intolerance
Excessive sweating
Why can diarrhea occur in hyperthyroidism?
Increased thyroid hormone causes rapid gastrointestinal transit
What are some GI symptoms of hyperthyroidism?
Diarrhea
Malabsorption
Steatorrhea
(Due to rapid transit time)
What cardiovascular findings are characteristic of hyperthyroidism?
Palpitations
Tachycardia
What neuromuscular/psychiatric findings can occur in hyperthyroidism?
Anxiety
Tremor
Proximal muscle weakness
What eye finding is classically associated with Graves disease/hyperthyroidism?
Exophthalmos/exophthalmia (bulging eyes)
What happens to TSH in primary hyperthyroidism?
TSH decrease
What happens to TSH in primary hypothyroidism?
TSH increases because thyroid hormone levels are low
What is myxedema?
The clinical syndrome associated with severe hypothyroidism
Particularly in adults
A severe form of cutaneous and dermal swelling associated with low thyroid hormone levels
What are classic clinical findings (myxedema) of hypothyroidism?
Fatigue
Apathy
Mental sluggishness
Constipation
Cool skin
What is the congenital root cause of hypothyroidism?
A congenital iodine deficiency
Why is the skin cool in hypothyroidism?
Due to a decrease in blood flow
What is the classic clinical association with severe congenital hypothyroidism?
Cretinism
With impaired physical and mental development
What are the primary causes of hypothyroidism?
Surgery, radiation exposure → Loss of thyroid tissue
Thyroiditis → Destruction of follicles
Iodine deficiency → ↓synthesis of thyroid hormone
Drugs → interfere with normal synthesis
Dyshormonogenetic goiter → Congenital defect in synthesis
Genetic defects in thyroid development
Thyroid hormone resistance (mutation)
What are the secondary causes of hypothyroidism?
Pituitary failure → Defective TSH production
Hypothalamic failure → Defective TSH production
What is thyroiditis?
Inflammation of the thyroid gland
With several distinct etiologies and clinical presentations
What is Hashimoto thyroiditis?
A chronic autoimmune thyroiditis that commonly causes hypothyroidism
What antibodies are classically associated with Hashimoto thyroiditis?
Anti-thyroid peroxidase (anti-TPO)
Anti-thyroglobulin
What are the classic microscopic features of Hashimoto thyroiditis?
Prominent mononuclear inflammation
Lymphoid germinal centers
Hürthle cell metaplasia
Atrophic thyroid epithelium

What is an important neoplastic association with Hashimoto thyroiditis?
Increased risk of thyroid MALT lymphoma
What is the common pathogenesis of Hashimoto thyroiditis?
Autoimmune response against thyroid antigens
Destruction of the gland by CTLs and cytokine-mediated inflammation
What are the clinical features of Hashimoto thyroiditis?
Painless diffuse enlargement of the thyroid
Progressive hypothyroidism
What is the common pathogenesis of subacute granulomatous (de Quervain) thyroiditis?
Postulated to be viral infection of host response to a virus
(A self-limited disease)
What is the characteristic microscopic finding in subacute granulomatous (de Quervain) thyroiditis?
Disrupted follicles
Inflammation
Multinucleated giant cells surrounding thyroid colloid

What are the clinical features of subacute granulomatous (de Quervain) thyroiditis?
Acute onset of:
Neck pain
Fever
Variable thyroid enlargement
Transient hypothyroidism
A painful/tender thyroid, often following a viral upper respiratory infection
Eventual recovery → (6-8 weeks) normal function
What is the common pathogenesis of painless thyroiditis?
Presumed autoimmune
Circulating antithyroid peroxidase antibodies
Family hx
Postpartum period
(also referred to as subacute lymphocytic thyroiditis)
What is the characteristic microscopic finding in painless thyroiditis?
Lymphocytic inflammation
Sometimes with germinal centers
LACK the commonly prominent fibrosis and Hurthle cells
What are the clinical features of painless thyroiditis?
Painless neck mass (goiter)
Often a transient hyperthyroid phase
Followed by hypothyroidism
Eventual recovery
What is the common pathogenesis of Reidel thyroiditis?
IgG4-related disease
What is the characteristic microscopic finding in Reidel thyroiditis?
Extensive fibrosis with scattered lymphoplasmacytic infiltrates with IgG4-positive B cells
Often extend BEYOND the thyroid capsule
What are the clinical features of Reidel thyroiditis?
Hard, fixed thyroid mass
Usually euthyroid
What can the hard thyroid mass of Reidel thyroiditis clinically stimulate?
A thyroid carcinoma
What is this?

A normal thyroid

What is this demonstrating?
Thyroiditis