Cell Injury & Death
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/20

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
21 Terms
What are the two main types of oxygen deprivation that cause cell injury?
Hypoxia (oxygen deficiency) and Ischemia (reduced blood supply).
What are the 4 main intracellular targets vulnerable to cell injury?
Mitochondria, cellular membranes (plasma and lysosomal), DNA (nucleus), and proteins/ER.
Mitochondrial damage leads to what two major cellular consequences?
ATP depletion and increased Reactive Oxygen Species (ROS).
Unfolded or misfolded protein accumulation in the ER triggers what pathway?
The Unfolded Protein Response, which leads to Apoptosis if unresolved.
What failure causes acute cellular swelling in reversible injury?
Failure of energy-dependent ion pumps (e.g., Na+/K+ ATPase) in the plasma membrane, leading to loss of fluid homeostasis.
What is Hydropic Change (Vacuolar Degeneration)?
The microscopic appearance of small, clear cytoplasmic vacuoles in reversibly injured cells, representing pinched-off segments of swollen ER.
In which organs is Fatty Change most commonly seen during reversible injury?
Organs involved in lipid metabolism, primarily the liver.
List 4 ultrastructural changes seen in reversible cell injury.
Plasma membrane blebbing/loss of microvilli, mitochondrial swelling, dilation of ER with ribosome detachment, and chromatin clumping.
Define Pyknosis, Karyorrhexis, and Karyolysis.
Pyknosis: Nuclear shrinkage and increased basophilia. Karyorrhexis: Nuclear fragmentation. Karyolysis: Nuclear dissolution/fading.
What is the hallmark requirement that distinguishes Necrosis from Apoptosis?
Necrosis features plasma membrane disruption leading to leakage of contents and host inflammation. Apoptosis keeps the membrane intact and elicits NO inflammation.

Describe Coagulative Necrosis (cause, sites, microscopic feature).
Cause: Ischemia in solid organs EXCEPT the brain. Microscopic: Preserved tissue architecture ("ghost cells") with loss of nuclei.

Describe Liquefactive Necrosis (cause, sites, appearance).
Cause: Bacterial/fungal infections (abscesses) or hypoxic brain death. Appearance: Complete digestion of tissue into a viscous liquid or pus.

Differentiate between Dry and Wet Gangrene.
Dry Gangrene: Ischemic coagulative necrosis involving multiple tissue layers. Wet Gangrene: Superimposed bacterial infection adding a liquefactive component.

Describe Caseous Necrosis (associated disease, gross, microscopic feature).
Disease: Tuberculosis. Gross: Friable, yellow-white, "cheese-like" appearance. Microscopic: Amorphous pink granular debris surrounded by macrophages (granuloma).


Describe Fat Necrosis (mechanism, gross appearance).
Mechanism: Release of pancreatic lipases or trauma digesting fat into free fatty acids that bind calcium (saponification). Gross: Chalky-white deposits.
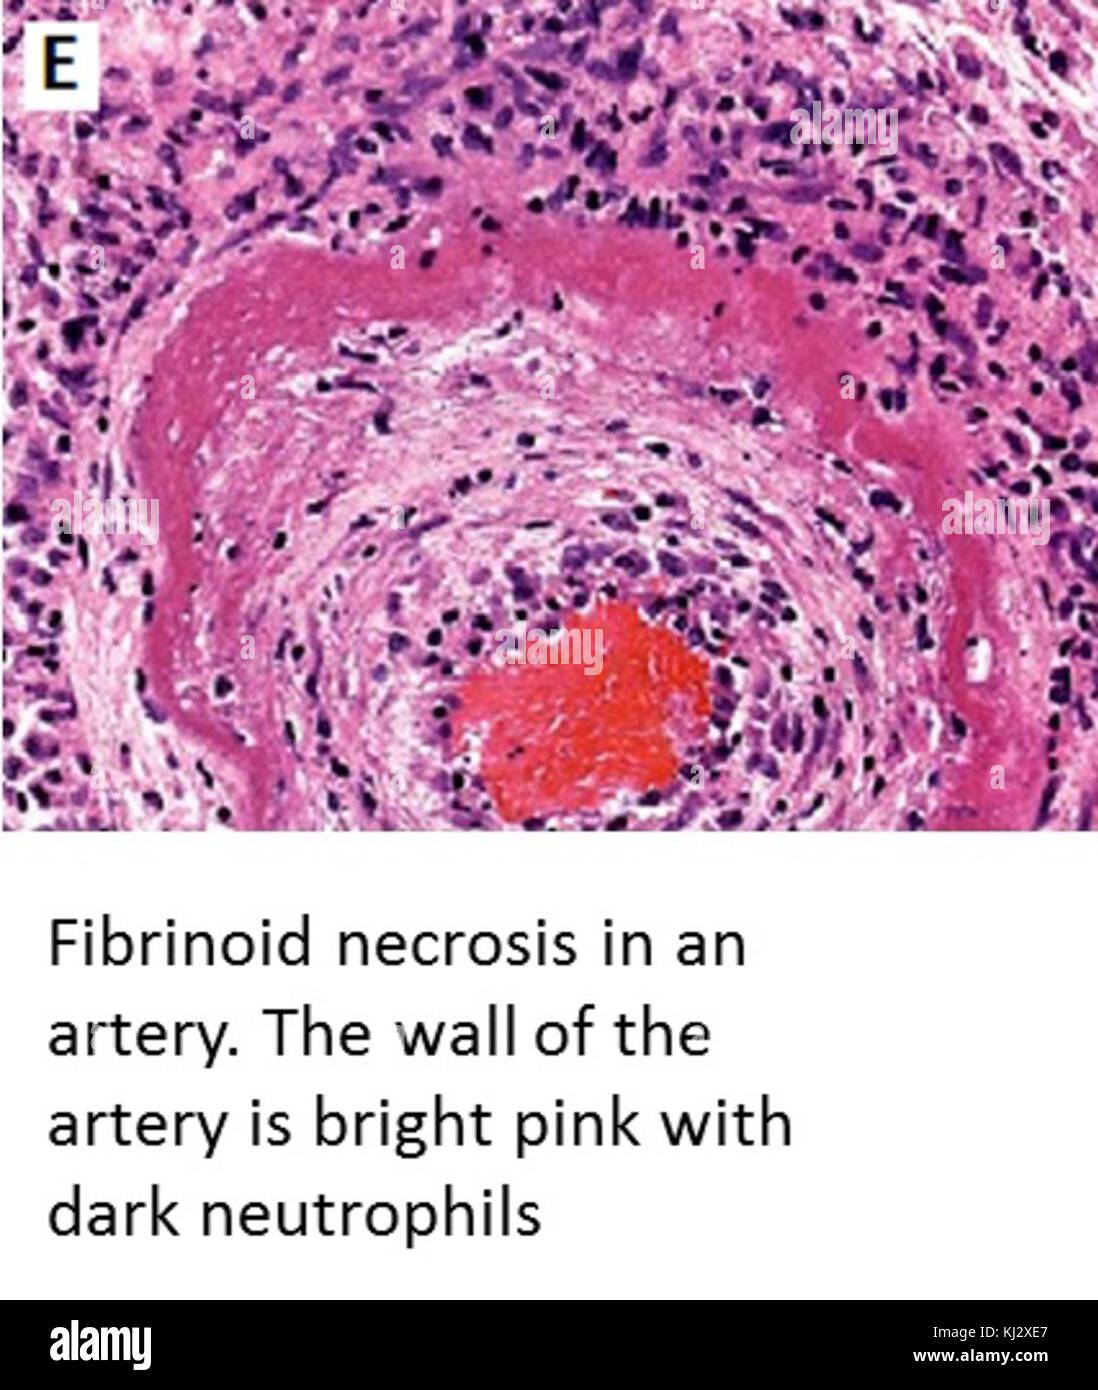
Describe Fibrinoid Necrosis (cause, microscopic feature).
Cause: Antigen-antibody immune complexes deposited in vessel walls (vasculitis, malignant hypertension). Microscopic: Bright pink, amorphous "fibrin-like" ring in arterial walls.
What are Apoptotic Bodies?
Membrane-bound fragments of an apoptotic cell containing cytoplasm and nuclear remnants that are recognized and phagocytosed by macrophages.
Contrast BCL-2 and BAX/BAK proteins.
BCL-2 is anti-apoptotic (inhibits apoptosis). BAX and BAK are pro-apoptotic effectors (form mitochondrial membrane pores).
What molecule is released from mitochondria to initiate the intrinsic pathway of apoptosis?
Cytochrome c, which activates Caspase-9.
What receptors trigger the extrinsic (Death Receptor) pathway of apoptosis?
Fas (CD95) or Type 1 TNF receptor, which directly activate Caspase-8.

What is the classic H&E microscopic appearance of an apoptotic cell?
A round or oval mass of intensely eosinophilic (bright pink) cytoplasm with dense, fragmented dark chromatin.