Patho - Neurovascular pathology
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/113

There's no tags or description
Looks like no tags are added yet.
114 Terms
Stroke - Non-modifiable risk factors
Age - 2x after 55
Woman
Family hx

Stroke - Other risk considerations
Hx of TIA or stroke
Race
SDOH

Stroke - Modifiable risk factors

Stroke is largely preventable:
No alcohol

Risk factors
BP greater than:
Diagnosed with?
Fasting blood sugar greater than:
BMI greater than:
Total blood cholesterol greater than:

Stroke

Ischemic: localized or embolitic (traveling from other part of body)
2 main types of CVA: both have sudden onset of ___ and sx due to disturbance of ___
neuro signs, blood supply to brain
Type of CVA? Hypoxia or decreased oxygenation to brain tissue
Ischemia

Type of CVA - Abnormal bleeding from rupture of cerebral vessel
Hemorrhagic

Sx that disappear and imaging is negative - warning stroke
TIA

Ischemic CVA may be due to?
thrombosis or embolus
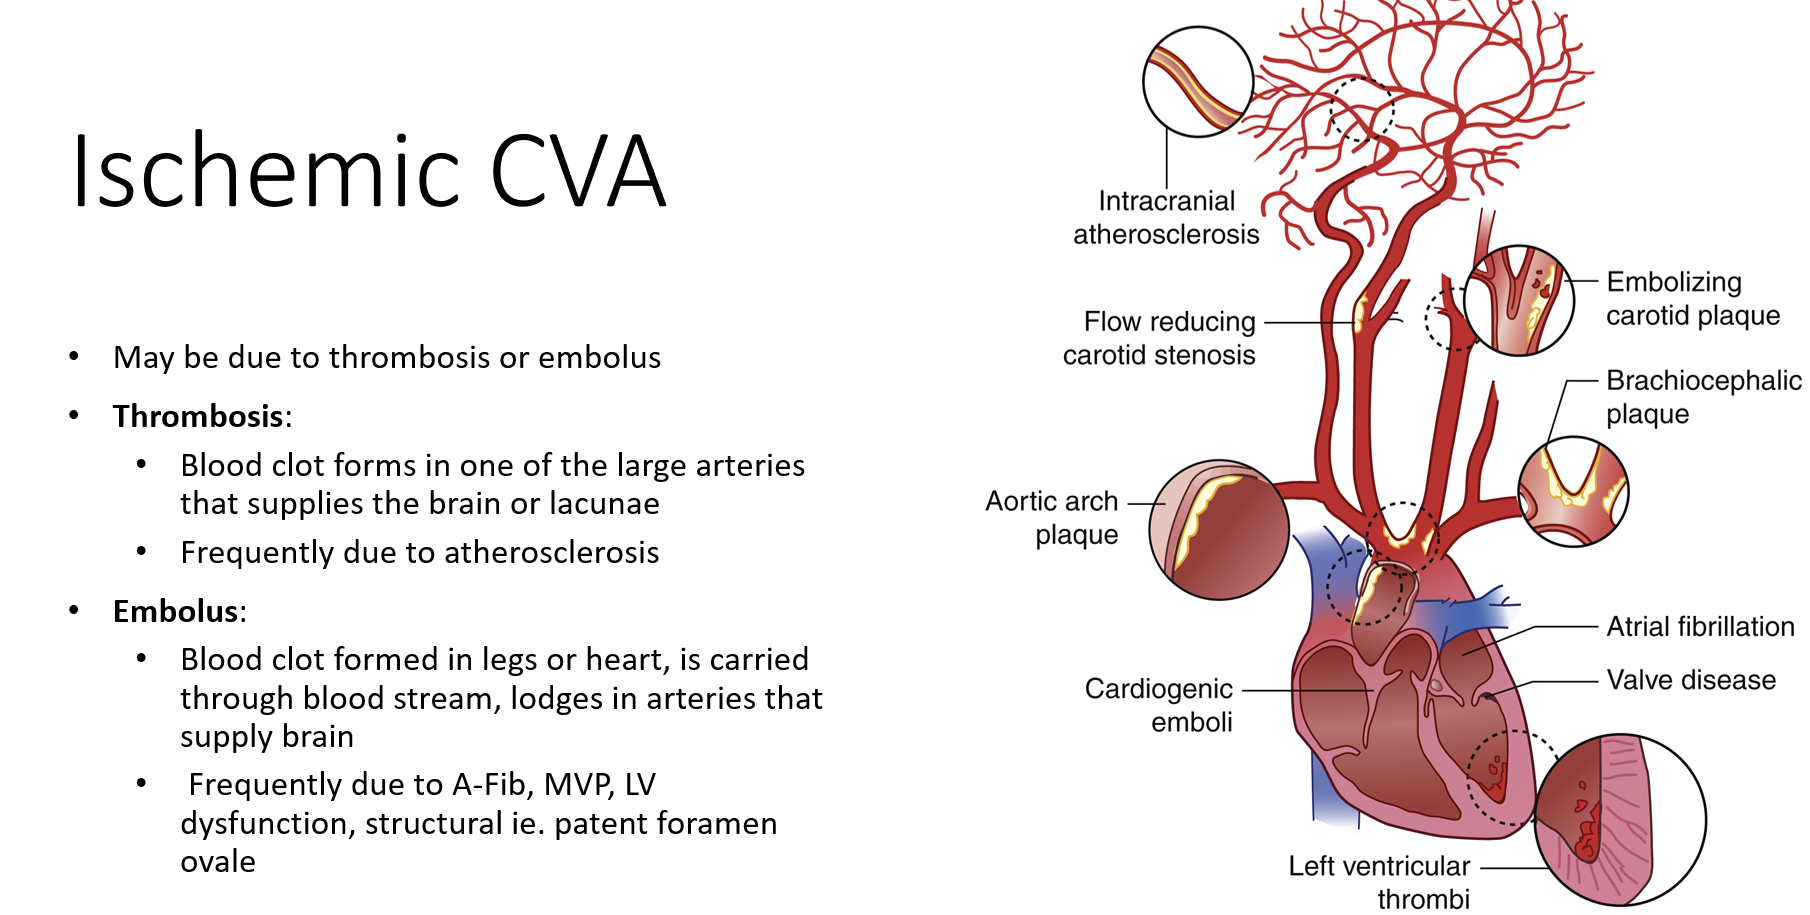
Thrombosis
Blood clot location?
Frequently due to?
large arteries that supplies the brain or lacunae
Atherosclerosis
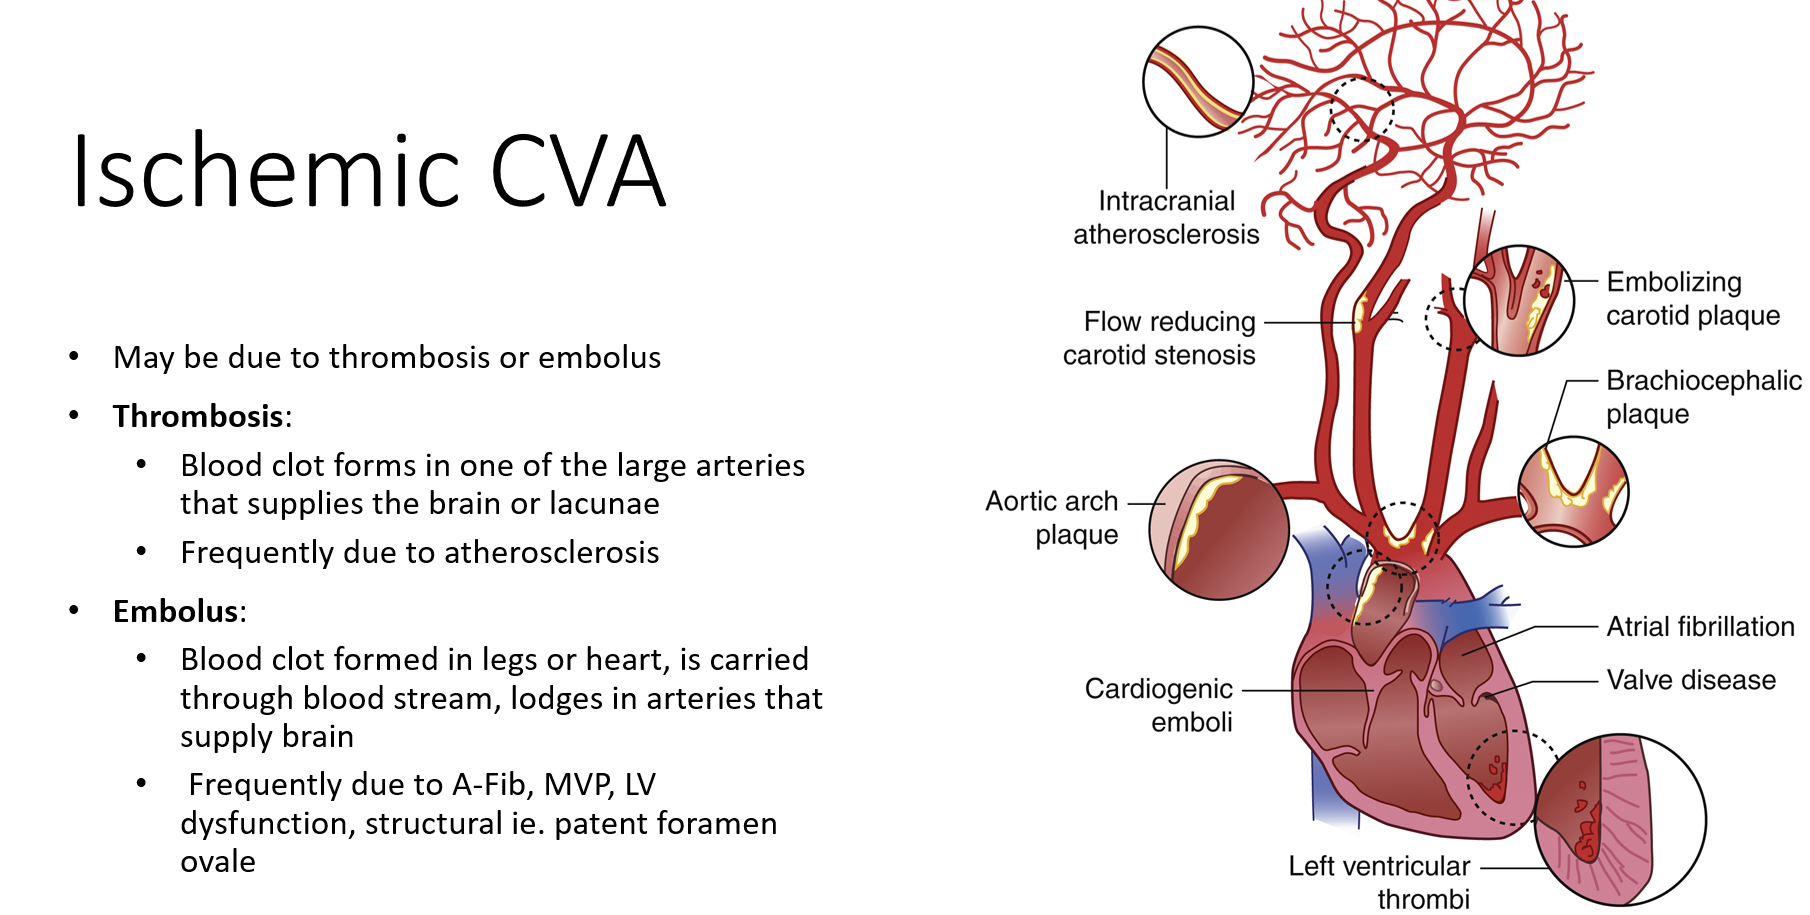
Embolus
Blood clot location?
Frequently due to?
Blood clot formed in legs or heart, is carried through blood stream, lodges in arteries that supply brain
Afib, MVP, LV dysfunction, structural

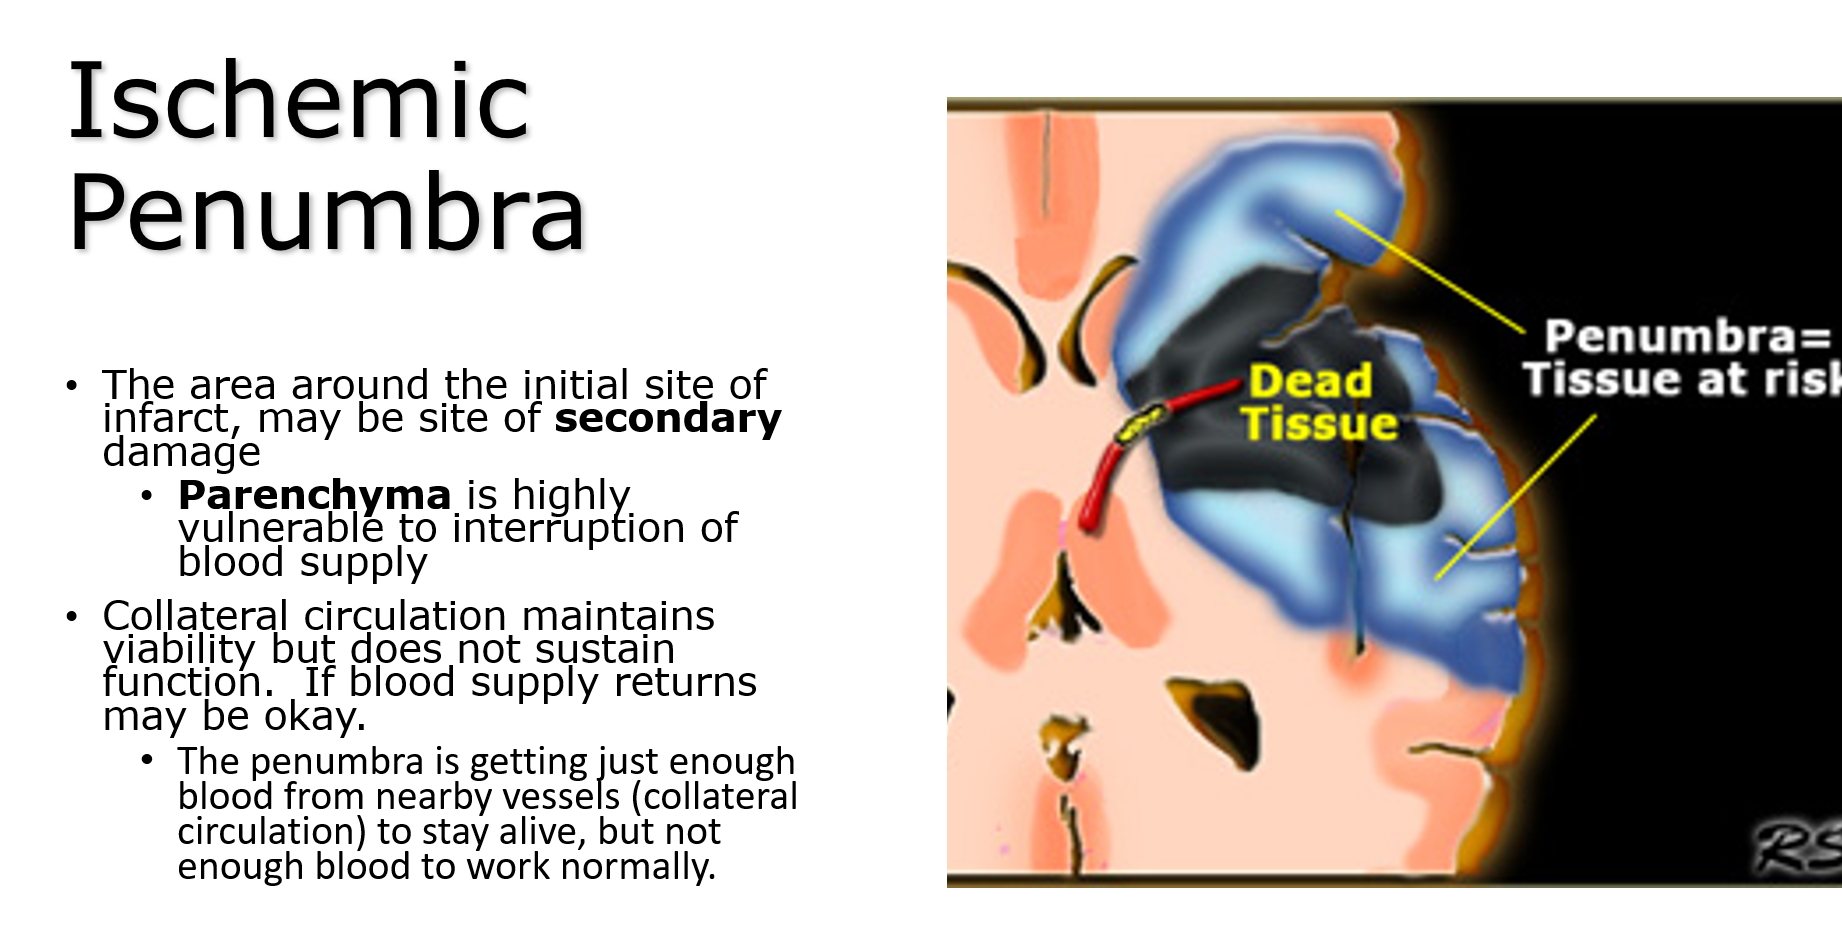
The area around the initial site of infarct, may be site of secondary damage
Ischemic Penumbra
~what makes every stroke unique~
This is the swelling around the initial stroke damage, may stay damaged if blood supply doesn’t return

In Ischemic Penumbra - what is highly vulnerable to interruption of blood supply?
Parenchyma

In Ischemic Penumbra - what happens to collateral circulation?
How to name hemorrhage
Dura, arachnoid, pia = DAB
If blood is below dura – subdural
If blood is below arachnoid layer – subarachnoid
Brain is in blood itself – intracerebral
Increased intracranial hemorrhage
Hemorrhagic CVA - arteries?
Intracerebral & Subarachnoid hemorrhage

Hemorrhagic CVA - may be due to?
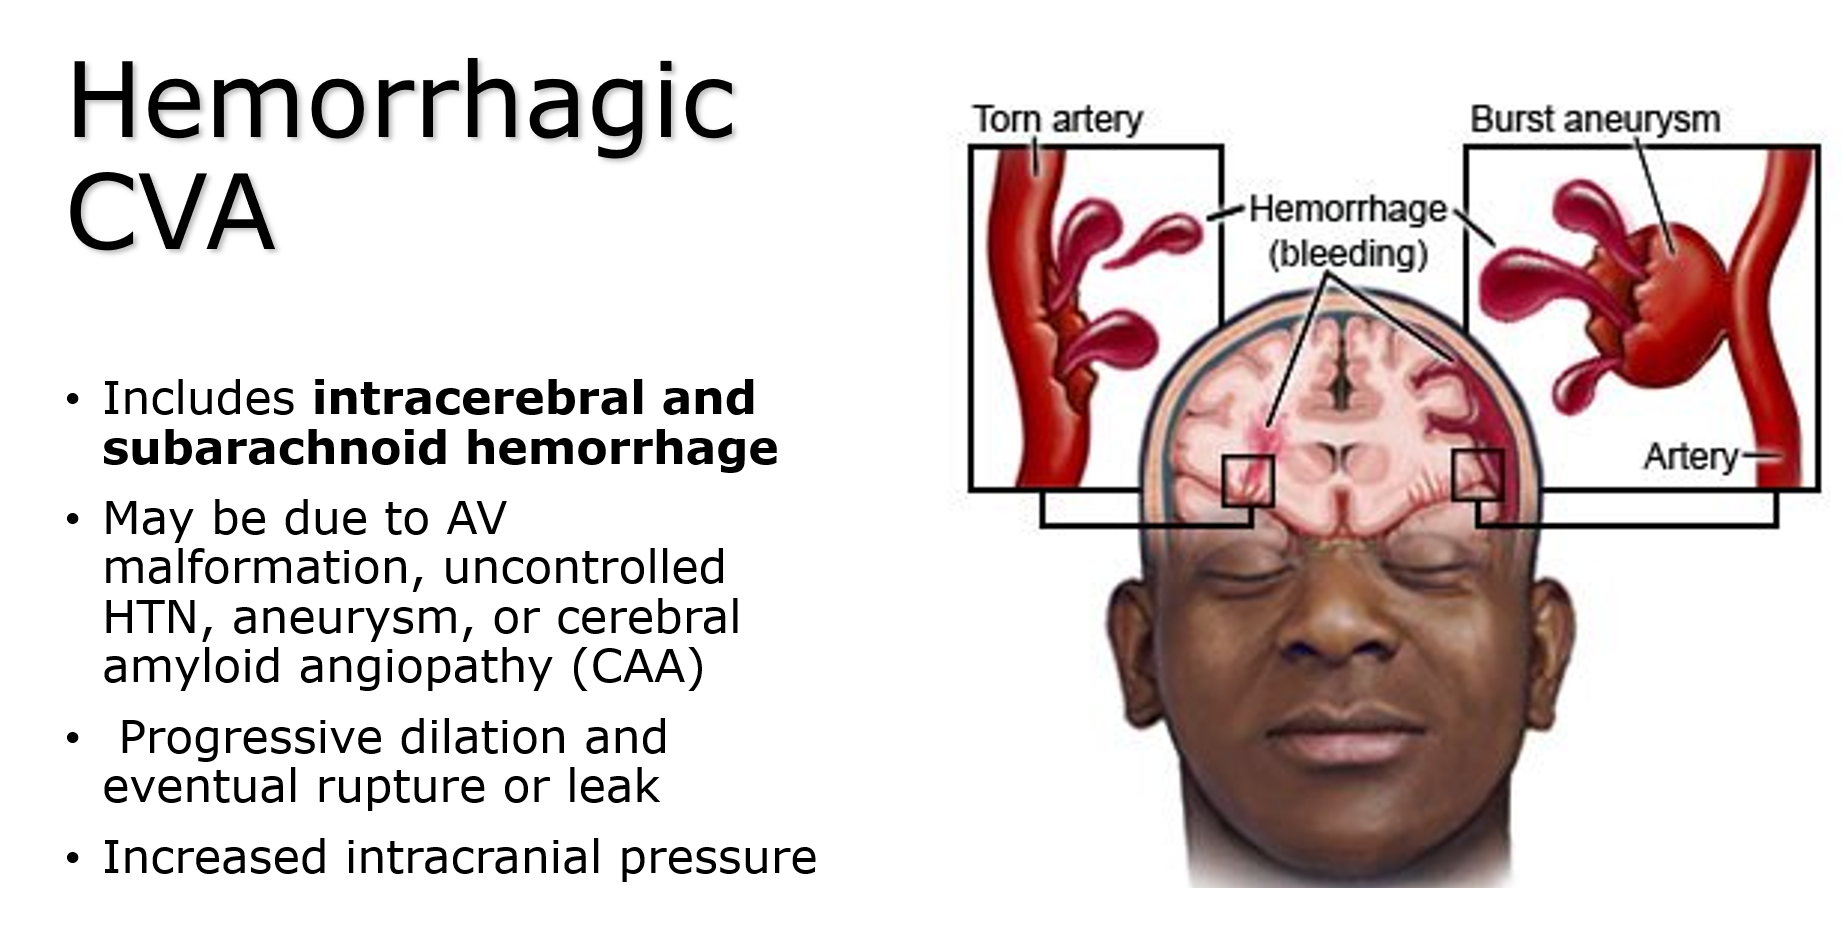
What type of stoke is - Progressive dilation and eventual rupture or leak
Hemorrhagic CVA

TIA - caused by?
focal cerebral, spinal cord, or retinal ischemia

TIA - is there any acute infarction?
No

TIA - symptoms resolve within?
minutes to hours

If a persons stroke symptoms resolve completely, does that automatically mean they had a TIA?
No - may still have ischemic stroke if infarction has occurred

TIA is a warning sign of?
medical emergency - sign of future stroke
17.8% 90-day risk
50% within 2 days

What does BE FAST mean

Early Recognition is Key for Effective Treatment

Brain tissue is very metabolically active - requires constant supply of?
__
__
glucose - 150 gms
O2 - 72 It

Brain Damage - primary injury
__ causes cell death
Changes start in __
Around ___ irreversible changes start

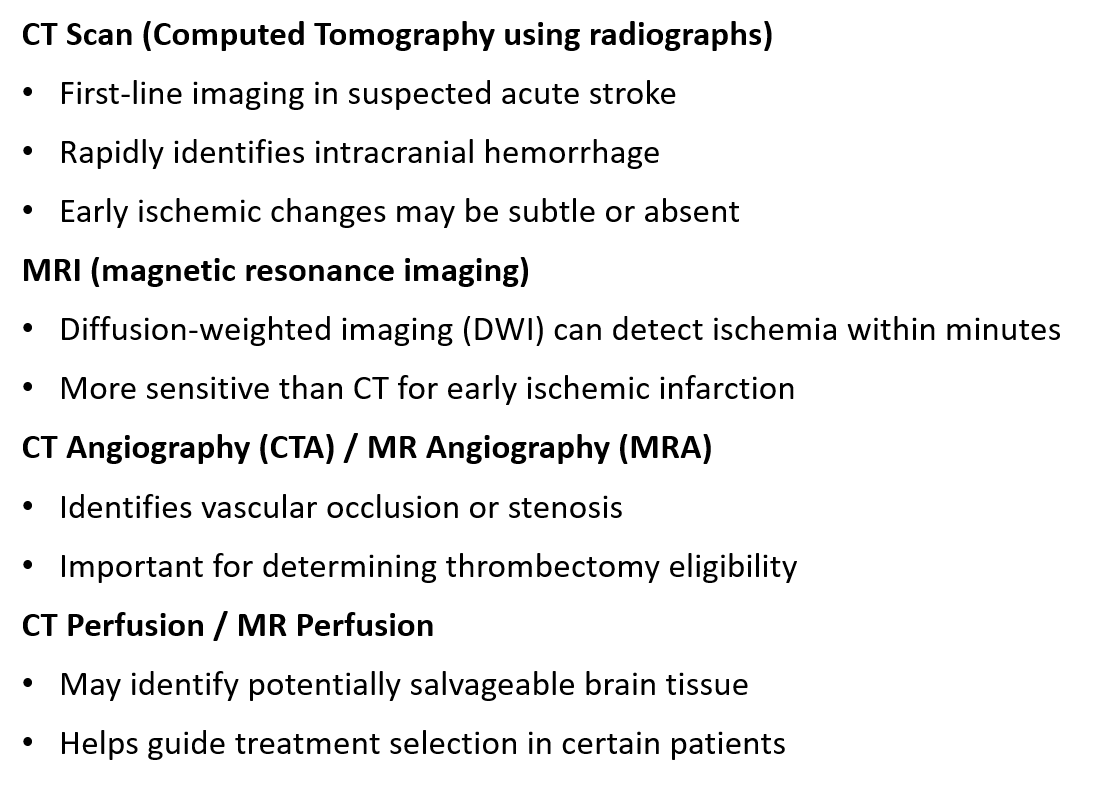
What is the first-line imaging test in suspected acute stroke
CT scan

Why is a CT scan commonly performed first in suspected stroke?
It rapidly identifies intracranial hemorrhage (bleeding).

What is a limitation of CT scans in early ischemic stroke?
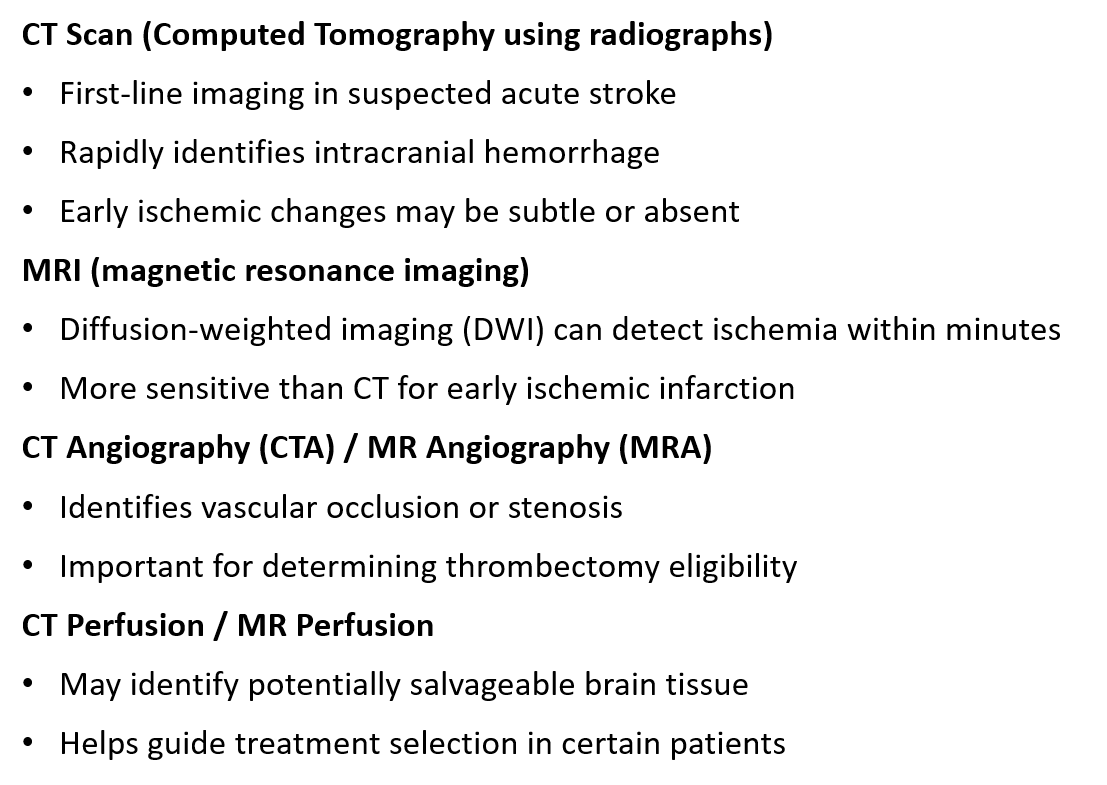
Early ischemic changes may be subtle or absent.
What can detect ischemia within minutes?
DWI MRI

What imaging is best for early ischemic infarction?
MRI

What do CTA and MRA evaluate in stroke patients?
Blood vessels for vascular occlusion or stenosis.

What imaging is Important for determining thrombectomy eligibility
MRA and CTA

What identifies potential salvageable brain tissue?
CT Perfusion / MR Perfusion

What helps guide treatment selection in certain patients
CT Perfusion / MR Perfusion
Acute Management of Stroke - 3 things?
IV thrombolysis
Mechanical Thrombectomy
Monitor for complications

IV Thrombolysis
__ or __ for eligible patients
Standard treatment window?
Monitor closely for?
tPA or TNK
4.5 hours of symptom onset

Mechanical Thrombectomy
endovascular removal of a clot froM?
Can happen up to after how long after sx onset?
Eligibility depends on?

Monitor for Complications
Hemorrhagic transformation
Cerebral edema and neurological deterioration

Acute Medical Management in Stroke - for all patients, even those w/out tPA
Main focus is on?
Improving cerebral perfusion and providing O2 support

Acute Medical Management in Stroke - for all patients, even those w/out tPA
Antiplatelet therapy -
Neurosurgical interventions -
Aspirin
Endarterectomy or aneurysm repair
Acute Medical Management in Stroke - for all patients, even those w/out tPA
Maintain what 2 things?
BP & CO
tx hypo & HTN

Acute Medical Management in Stroke - for all patients, even those w/out tPA
Monitor for neurological deterioration or complications
__ stroke scale
sx:
__
Acute Medical Management in Stroke
Restore __
Maintain ___
Control __
Maintain what 2 things?
__ control

Cerebral edema
Can appear within ___ of acute CVA
Peaks within ___
minutes
3-5 days

Cerebral edema - can increase __, cause __, and become life threatening
Can i, cause brain herniation, and become life-threatening

Cerebral edema - monitor closely for?
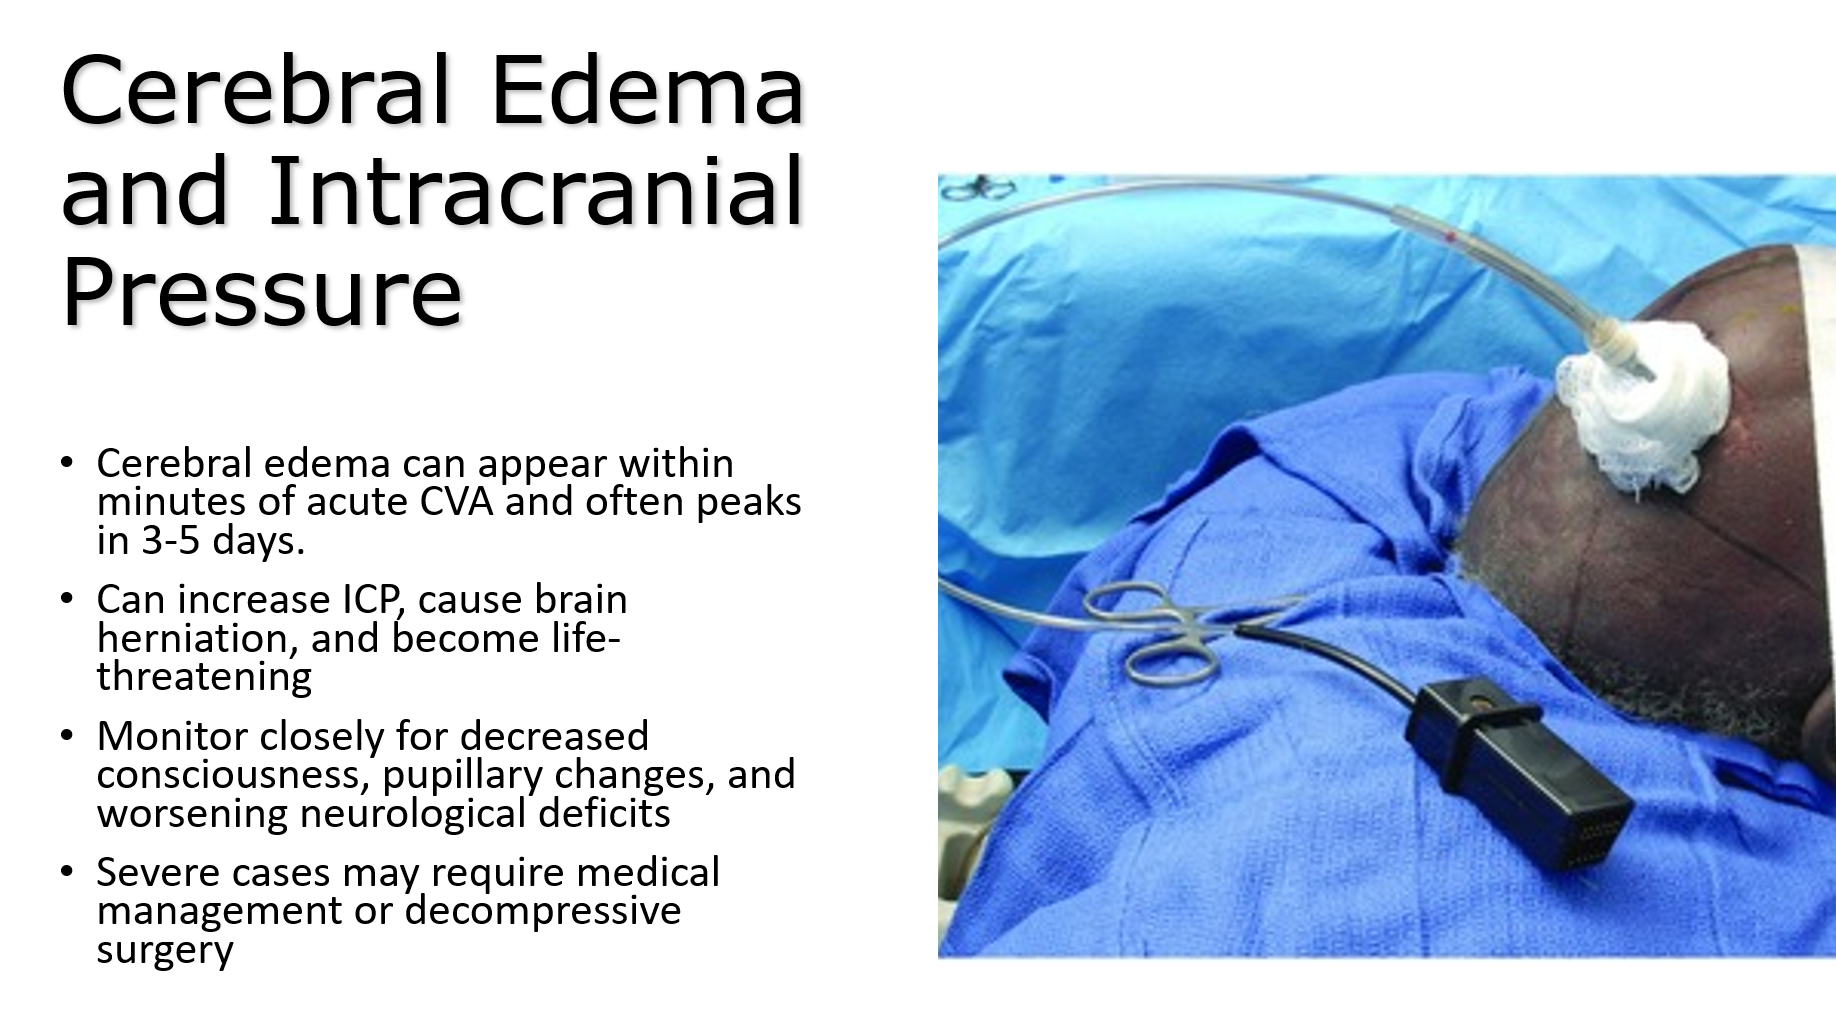
decreased consciousness, pupillary changes, and worsening neurological deficits
Anterior circulation
First aa:
Branches:
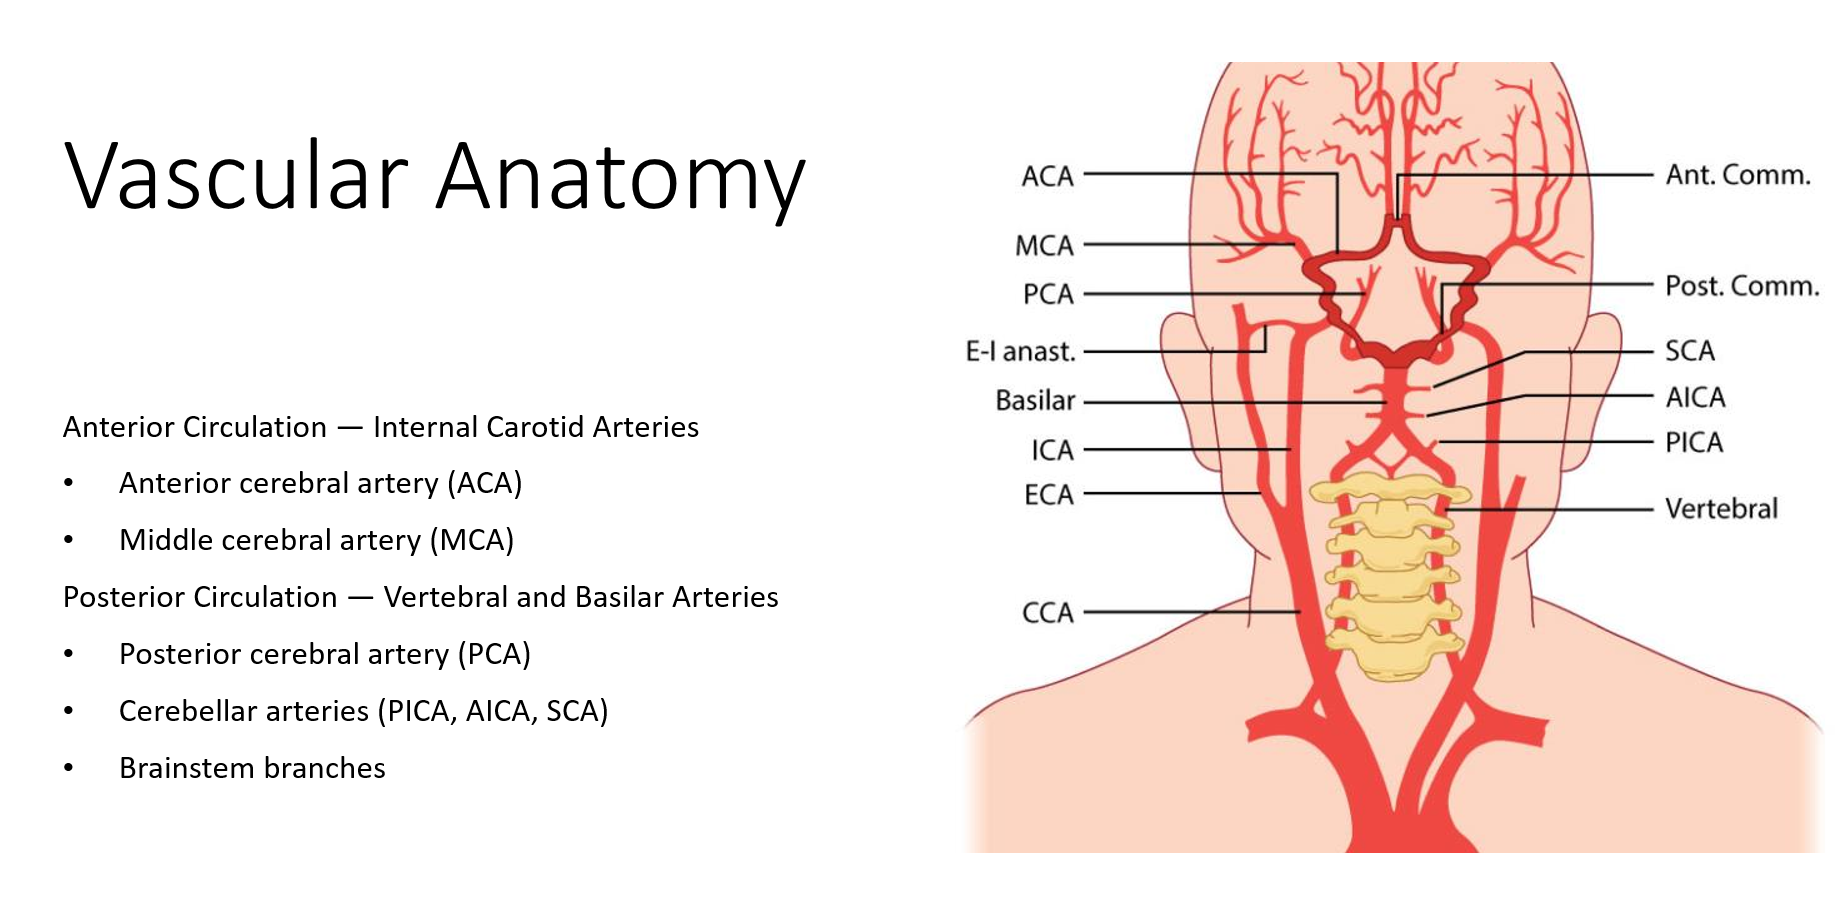
MCA has not collateral vessels - why it is so common and no other blood supply after it’s branch, worse deficits here because there is no other blood supply for this area
Posterior circulation
First aa:
Branches:

Common Post-stroke deficits
Dominant hemisphere - cortical signs

Dominant hemisphere - R handed, L dominant
Speech center on dominant side
Common Post-stroke deficits
Non-Dominant hemisphere - cortical signs

disturbance of motor activity execution
Apraxia(dyspraxia)
does not recognize common things
Wenicks vs brocas aphasia
Agnosia
Broca’s - broken speech
Wernick’s - fluent but doesn’t make sense
Dominant stroke presentation- image
Contralateral - paralysis/weakness, decreased sensation & vision
Speech & understanding language
Behavioral - cautiousness
Difficulty reasoning & organize
Memory issues

Non dominant stroke presentation - image
Contralateral weakness/paralysis, loss of sensation & vision
Neglect (opp. side)
Behavioral - impulsiveness, inappropriate
Decrease in judgement, problem-solving, decision making
Memory issues


Cortical signs are for what strokes
MCA PCA ACA
Middle Cerebral Artery Occlusion (MCA)
Lobes:

Middle Cerebral Artery Occlusion (MCA)
Symptosm

Hemianopsia

L visual fields of each eyes are gone
R side stroke
ACA stroke
Supplies what lobes

ACA stroke
Sensory & motor deficits

ACA stroke
other symptoms

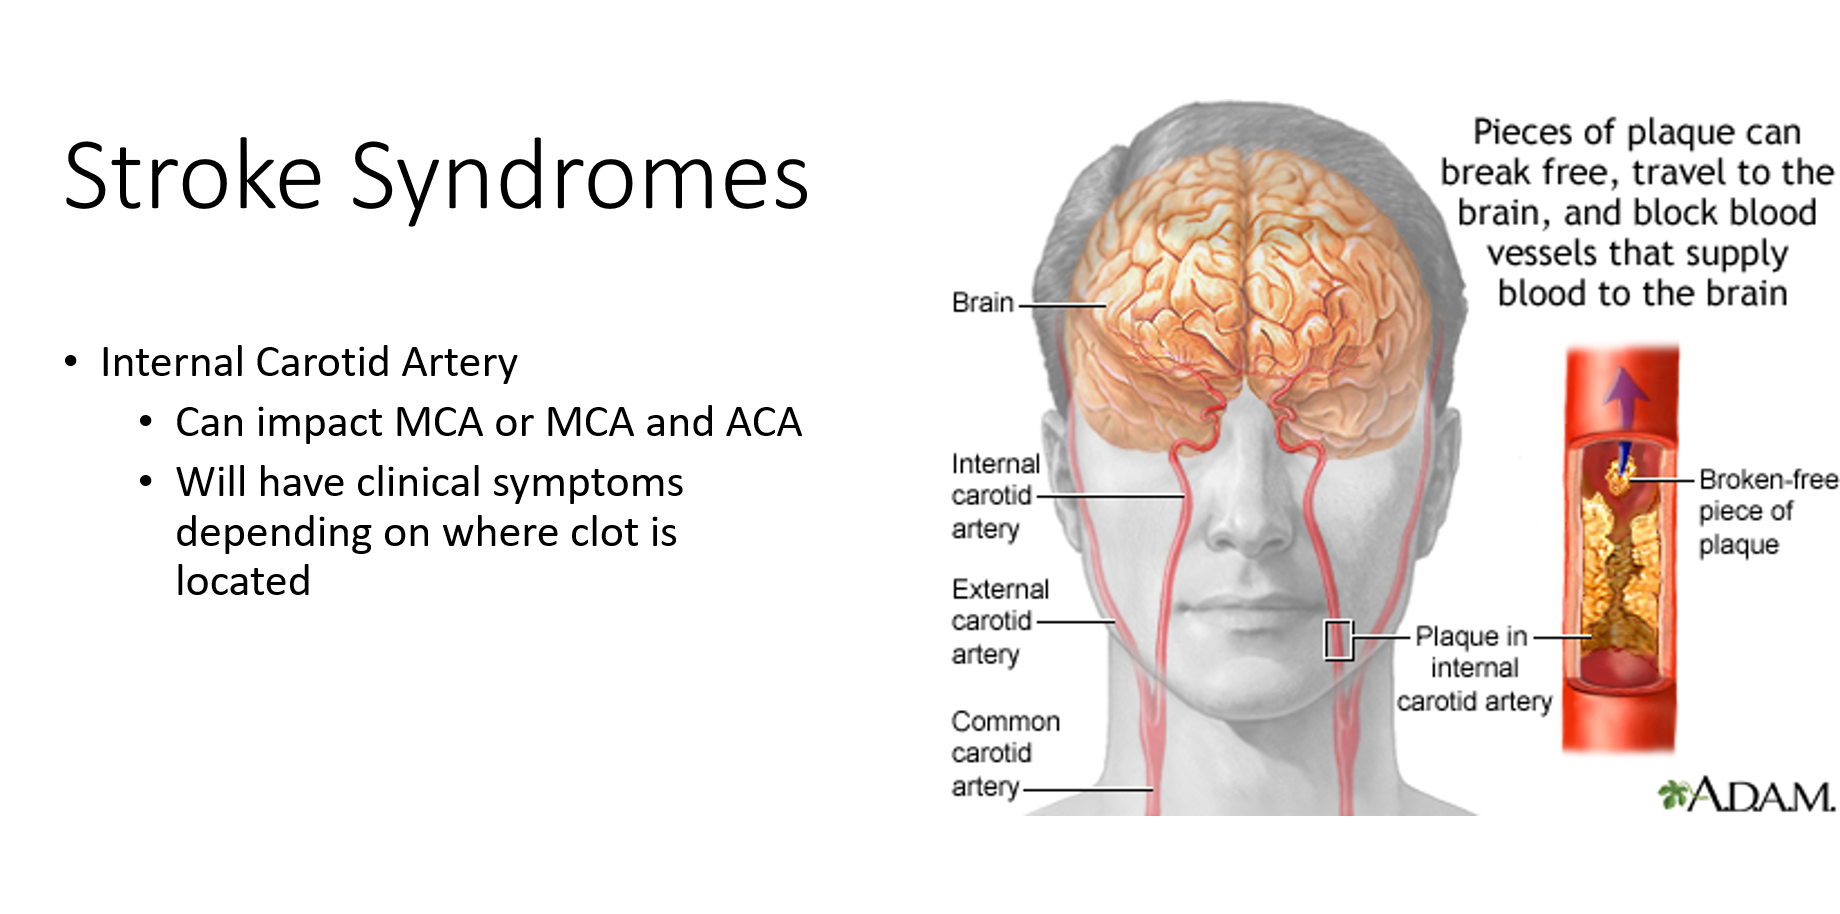
Internal carotid aa stroke
Impacts what arteries:
PCA stroke
lobes

PCA stroke
Symptoms
U/L lesion:
B/L lesion:
U/L lesion: homo
B/L lesion: cortical blindness

What is it called when they deny cortical blindness?
Anton syndrome
PCA
Symptoms
PCA stroke
Midbrain
Claude vs Weber
Claude
Ipsilateral CN III palsy + Contralateral ataxia
Droopy eye (ptosis), dilated pupil, Eye down & in
poor coordination
Weber
Ipsilateral CN III palsy + contralateral hemiplegia
Weakness/paralysis on opp body
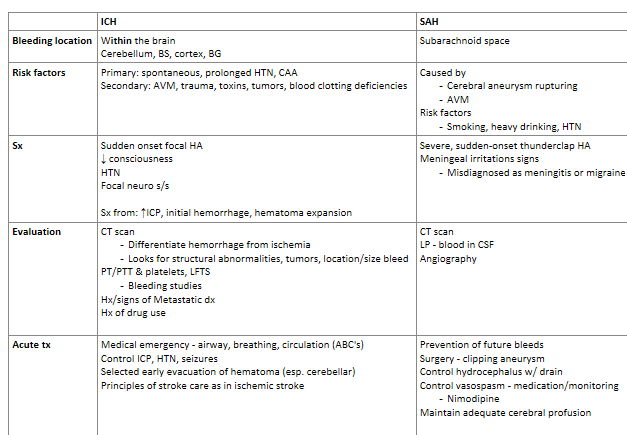
ICH location


What is a primary ICH from?

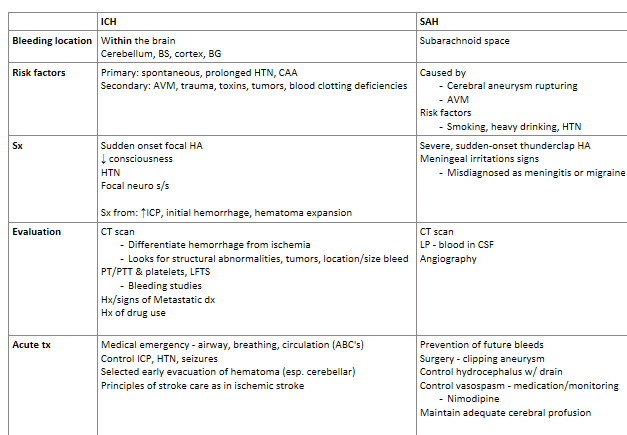
What is a secondary ICH from


ICH causes sudden increase in? more common in ?


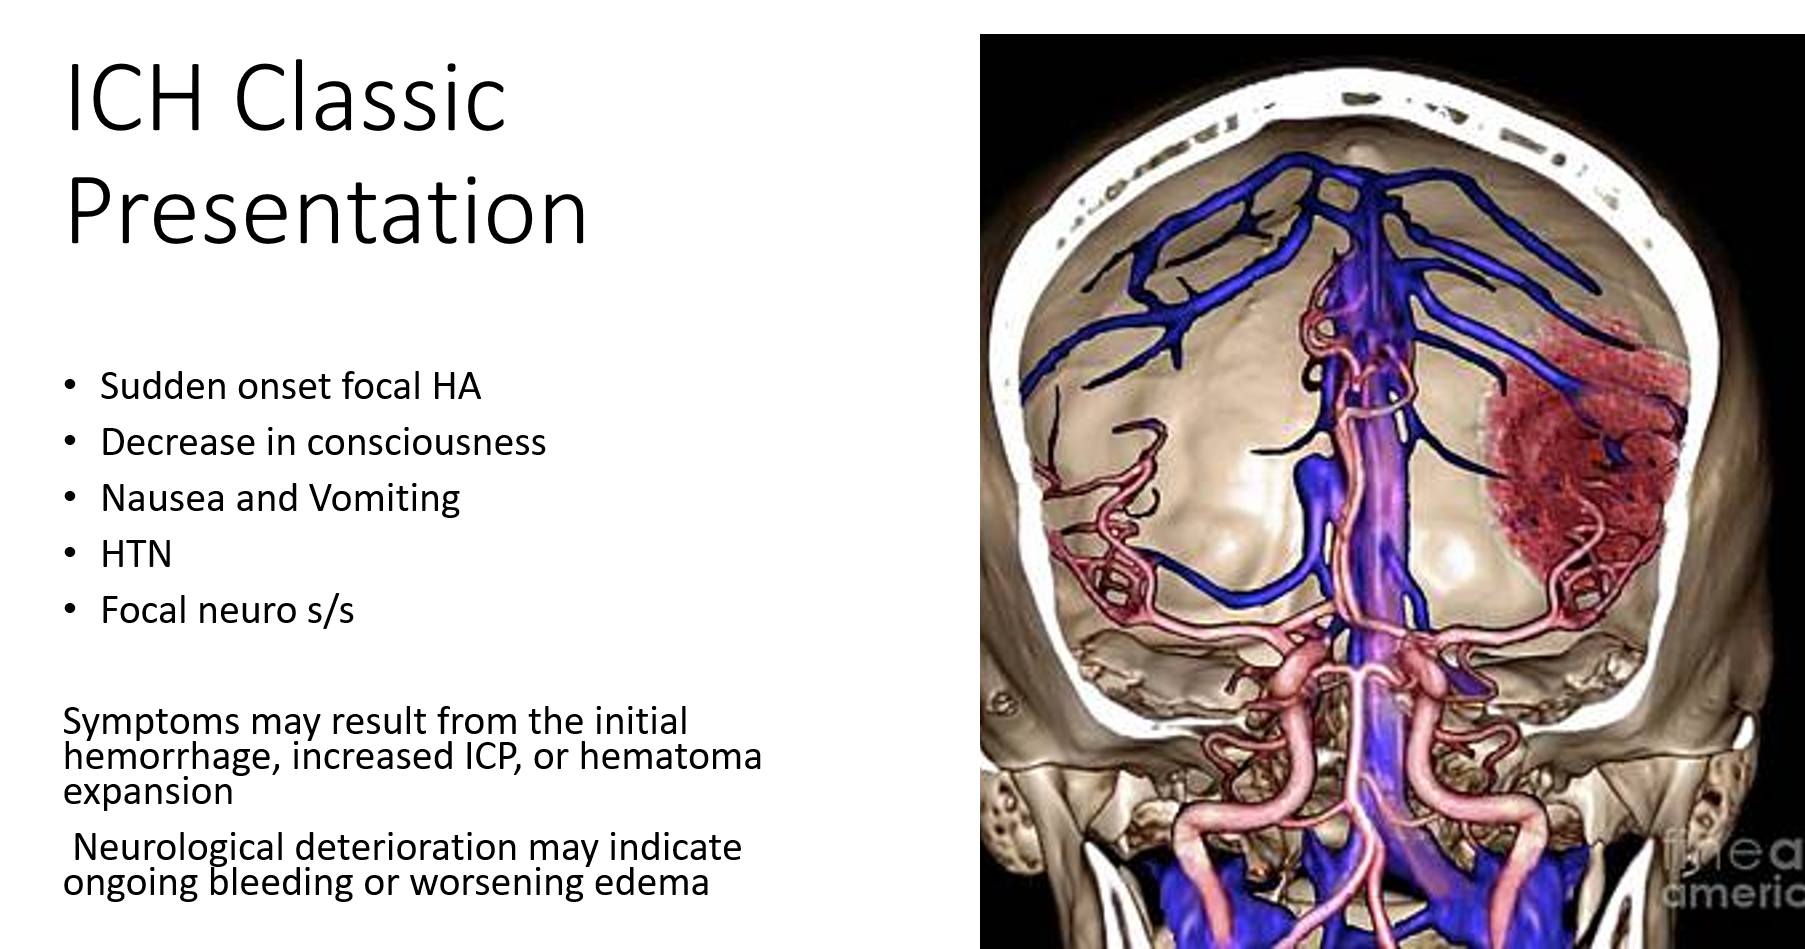
ICH Classic Presentation


ICH - symptoms may result from?


ICH - what may indicate ongoing bleeding or worsening edema
Neuro deterioration

What imaging differentiates hemorrhage from ischemia?
This imaging looks for?

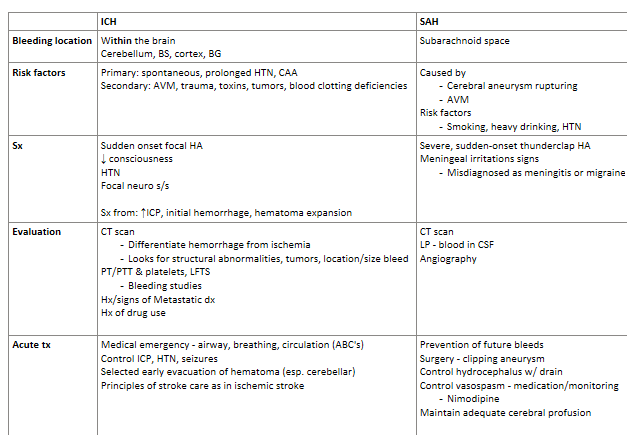
ICH evaluation

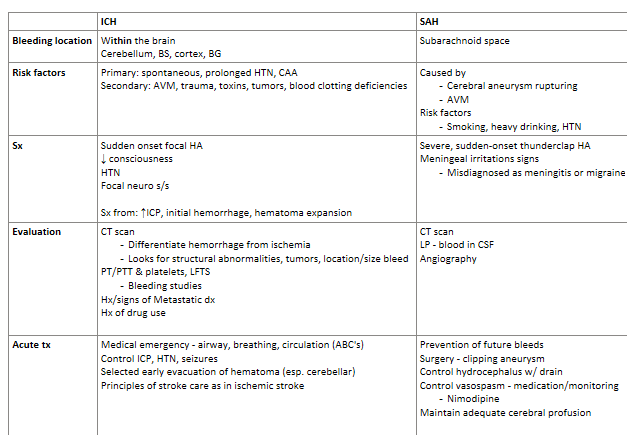
Acute tx of ICH
Is a medical emergency -
Control what 3 things?
selected early evacuation of the hematoma - especially in what type?
Principles pf stroke as in ischemic strokes

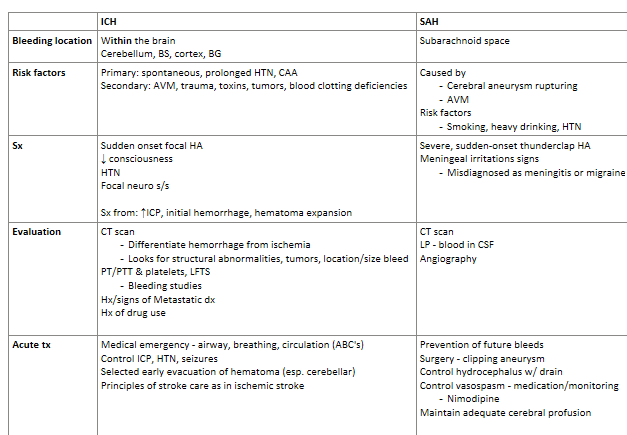
Subarachnoid hemorrhage - caused by?

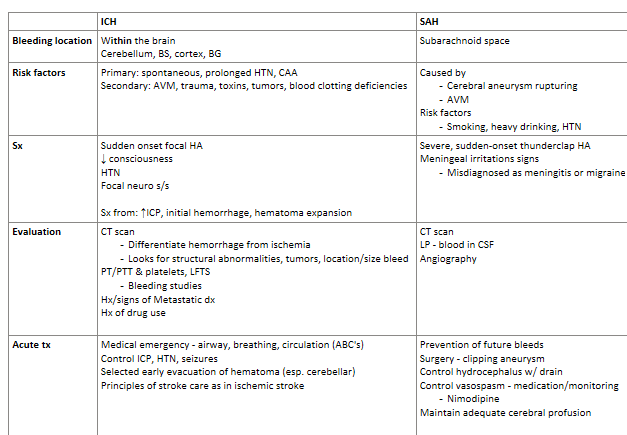
Subarachnoid hemorrhage - classic symptoms

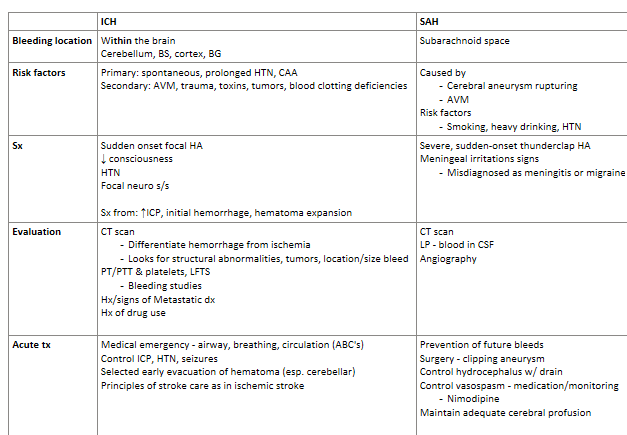
Subarachnoid hemorrhage risk factors

Evaluation of SAH

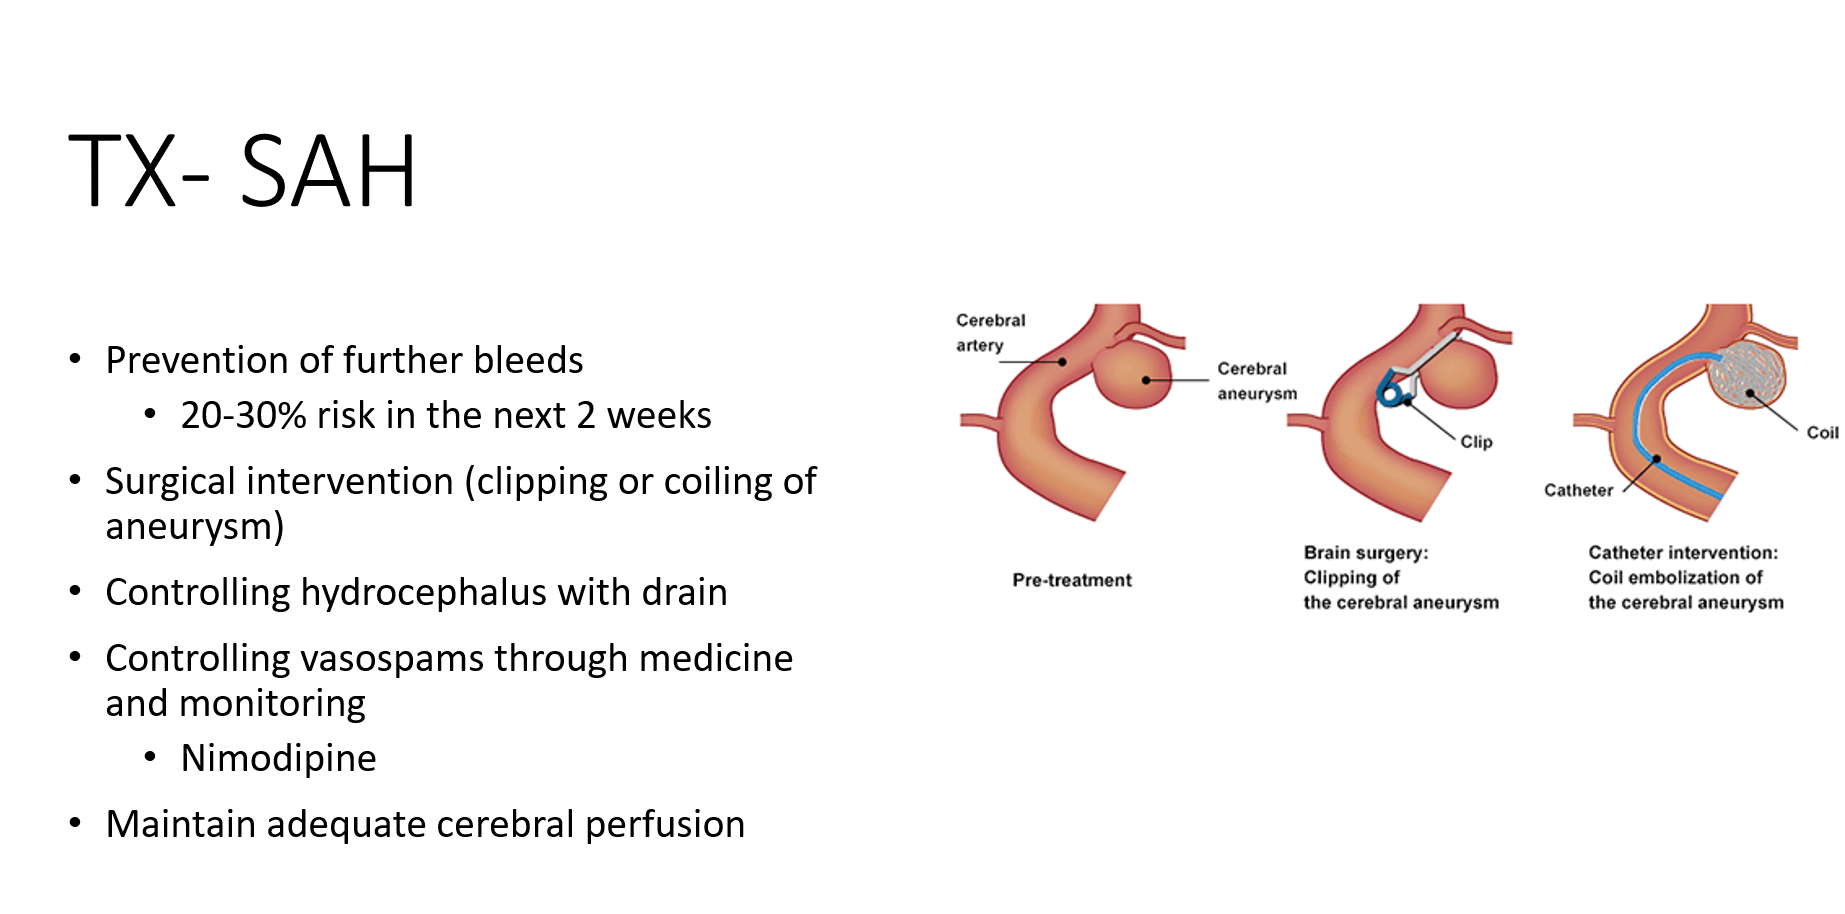
SAH - Tx
Prevention of?
Surgical invention?
Controlling hydrocephalus with?
Controlling vasospasm through?
Maintain adequate?

AV malformation image
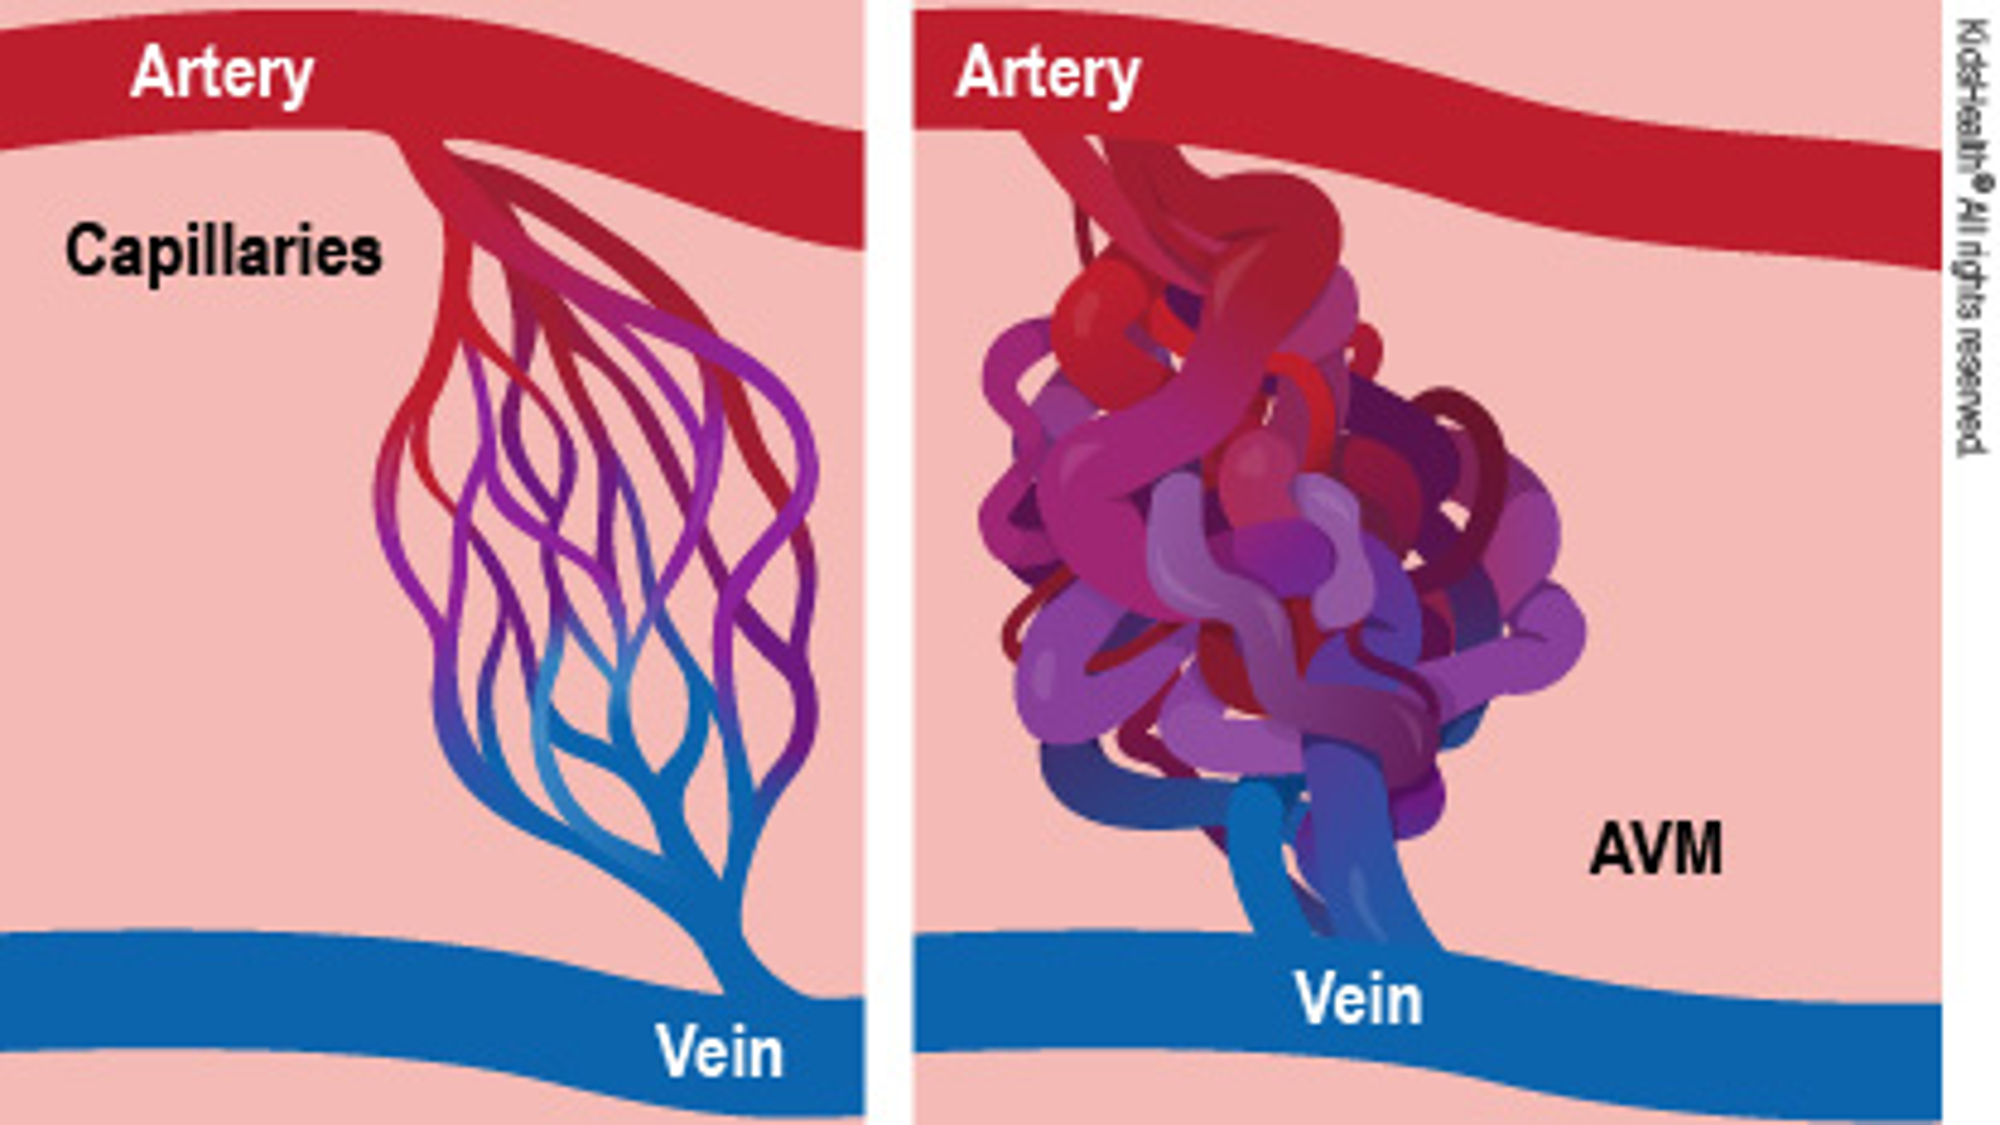
AVM
Abnormal connection between arteries and veins without a normal intervening ___- can lead to weakening and rupture
AVMs may remain asymptomatic or rupture causing what type of stroke?

AVM - treated via?

Stroke Re-occurrence Prevention
Control?
What after surgery?
Vascular surgery

Antithrombotic Therapy for Stroke Re-occurrence Prevention
Medications
Thrombotic?
Embolic?
What needs INR monitoring
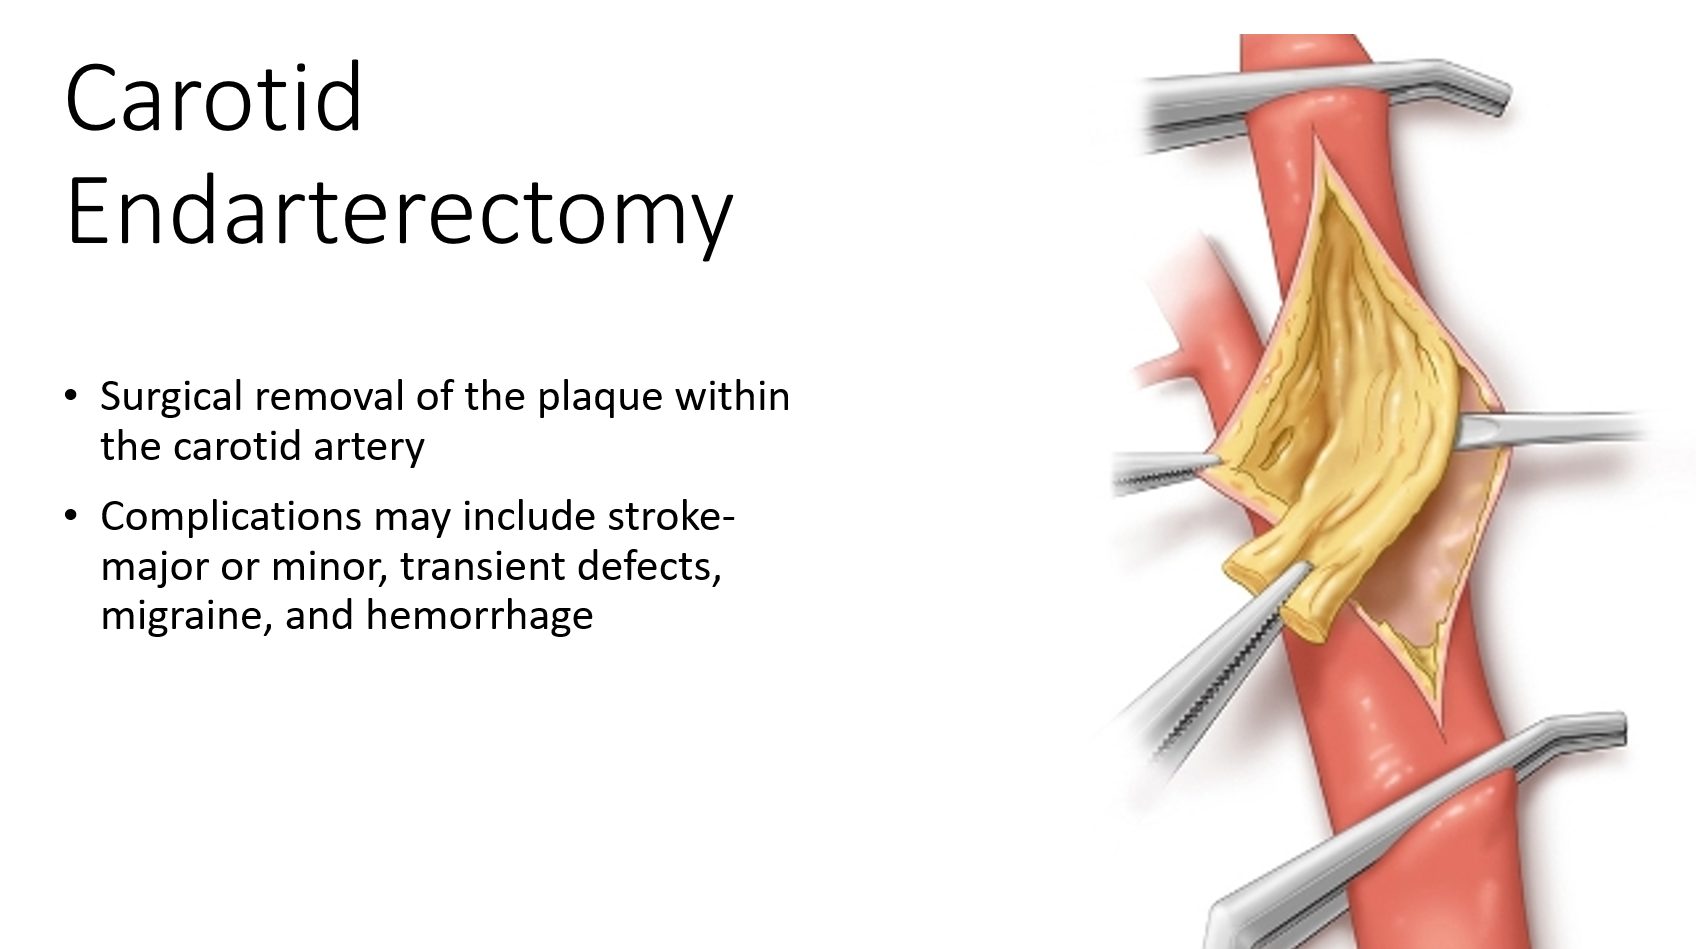
What is a Carotid Endarterectomy
Surgical removed of __ within the __
Complications may include?
Hemorrhagic stroke prognosis

Hemorrhagic stroke - what indicates good prognosis
What predicts hand function at 6 months?
What predicts regaining dexterity at 6 months?

Hemorrhagic stroke prognosis - most improvement in the first how many months?

R MCA stroke - which way would there force gaze deviation point
R - point towards side of lesion
Which side of brain is affected here

R side of brain - optic radiation in MCA & PCA
Only cerebral stroke where you see weird things with cranial nerves
PCA - Midbrain:
Claude: I/L CN III and C/L ataxia
Weber: I/L CNIII and C/L hemiplegia
Thalamic syndrome
severe contralateral pain - PCA stroke
Full cortical blindness
PCA - bilateral lesion