Lab values and Drug monitoring
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/77

There's no tags or description
Looks like no tags are added yet.
78 Terms
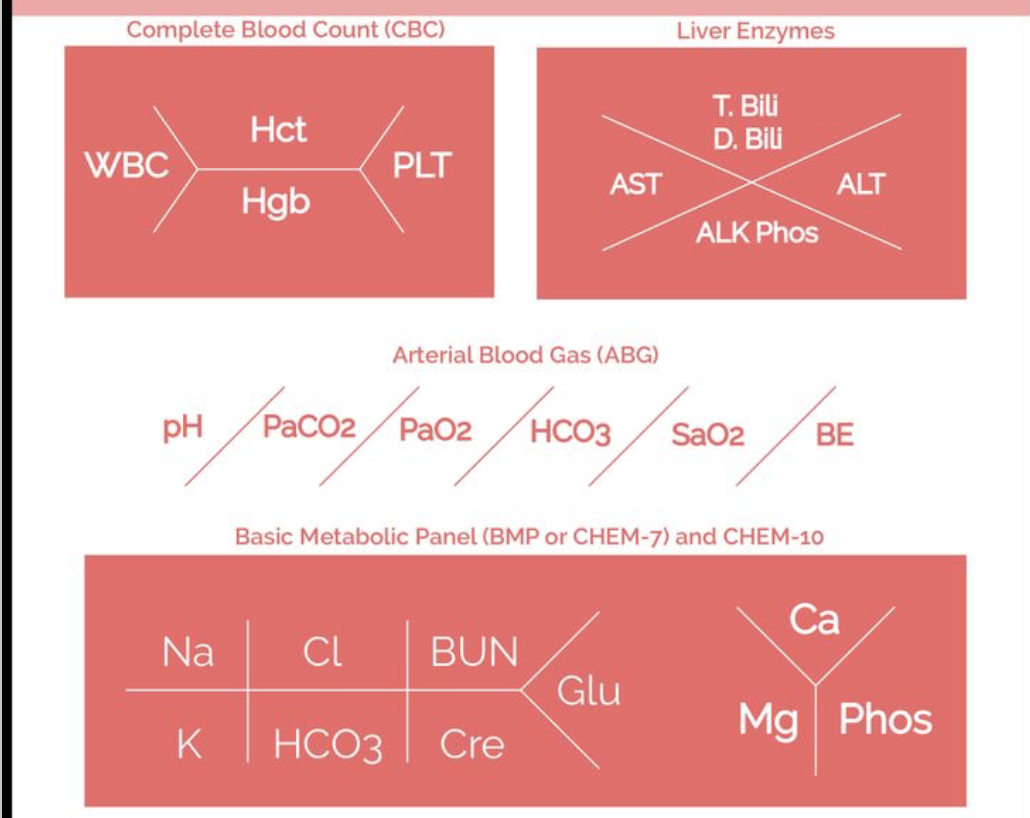
Fishbone diagrams
Define Leukocytosis
High WBC
Define Leukopenia
low WBC
Define Thrombocytosis
high platelets
Define thrombocytopenia
low platelets
Define polycythemia
high red blood cells
Define anemia
low red blood cells
Define myelosuppression
Bone marrow suppression (decrease WBC, RBC, PLT)
What is agranulocytosis?
Decrease in granulocytes (neutrophils, basophils, eosinophils).
What medications can cause agranulocytosis?
Think in 3 clusters:
Antipsychotic → Clozapine (the famous one that requires mandatory REMS monitoring)
Antithyroid duo → Propylthiouracil + Methimazole
The rest → Procainamide, Carbamazepine, Isoniazid, Bactrim
Just remember: “Clozapine + the two thyroid drugs + Procainamide, Carbamazepine, INH, Bactrim”
What can affect Calcium levels?
Levels can be increased via: thiazide diuretics, Vitamin D and calcium supplementation
Levels can be decreased via: heparin, loop diuretics, Cinacalcet, oral bisphosphonates
When do we correct Calcium and what is the formula
We correct it when Albumin is low; correction is not needed for ionized Calcium
Corrected Ca = Ca + 0.8(4 - albumin).
What can cause Mg levels to be low?
Mnemonic: PAD
PPIs
Amphotericin B
Diuretics
Just think: “PAD” = low Mag (like a soft, low pad).
What can lead to high phosphate levels?
CKD
What can effect Potassium levels?
Increased via:
K – Potassium-sparing diuretics
B – Bactrim and non-selective beta-blockers
A – ACE inhibitors, ARBs, and ARNI
N – NSAIDs
K – Potassium supplements and salt substitutes
S – SGLT2 inhibitors; canagliflozin
D – Drospirenone
T – Tacrolimus and cyclosporine
H – Heparin and LMWHs
Decreased via: beta 2 agonists, insulin, SPS
What can effect Sodium levels
Increased: hypertonic saline
Decreased: SCAT
SSRIs
Carbamazepine & Oxcarbzepine
ADH analogs(Desmopressin)
Thiazide diuretics
What can effect Bicarbonate (HCO3) levels?
Increased via: loop diuretics, steroids.
Decrease: topiramate, zonisamide, salicylate overdose
What indicated dehydration?
BUN:SCr > 20:1
What can increase Serum creatinine (SCr)?
meds that impair renal function(nephrotoxic): LANCr
Loop Diuretics
Anti-infectives
NSAIDs
Cisplatin, Cyclopsorine
Radiographic dye
What does an increased anion gap indicate (greater than 12)?
metabolic acidosis
WBC levels can be effected by what drugs?
Increase: systemic steroids
Decrease: “3 C’s and an I”
Clozapine
Carbamazepine
Chemotherapy
Immunosuppressants
Just say:“3 C’s and an I drop the WBC.”
What are neutrophils and what are they used for?
Neutrophils: polymorphonuclear cells/PMNs or Segs
Bands are immature neutrophils released from bone marrow to fight infection; cause a left shift when activated
Used to assess the likelihood of acute infection and to calculate ANC
Eosinophil levels increase when there is
parasitic infection, asthma, drug allergy
Basophils levels increase when there is
hypersensitivity reaction
What can increase and decrease Lymphocytes levels?
Increase: viral infections, lymphoma.
Decrease: bone marrow suppression, HIV, steroids
What can increase or decrease RBCs?
Increase: ESAs
Decrease: chemo, anemias
What can increase and decrease Hemoglobin (Hgb)
Increase: ESAs.
Decrease: anemias, bleeding
What is the MCV and what can effect it?
MCV: size and volume of RBCs
Increase/Marcolytic anemia: B12, folate(B9) deficiency.
Decrease/Microlytic anemia: iron deficiency
Folic acid (B9) can be decreased by what?
“3P + MB”
Phenytoin
Phenobarbital(ASM)
Primidone
Methotrexate
Bactrim
Just say:
“3P + MB decreases folate.”
Vitamin B12 can be decreased by?
PPIs
Metformin
Can → Colchicine
Cause → Chloramphenicol
Just remember the sentence: “PPIs and Metformin Can Cause low B12.”
Drugs that can make a Coombs test positive?
1. Beta-lactams
Penicillins (PCNs)
Cephalosporins
2. Sulfa-related
Sulfas
Dapsone
3. TB drugs
Isoniazid (INH)
Rifampin
4. Parkinson’s / Dopamine drugs
Levodopa / Methyldopa
5. “Quinine family” + others
Quinidine
Quinine
Primaquine
Methylene blue
Rasburicase / Pegloticase
Those G6PD deficiency should avoid what drugs?

What is Anti Xa?
Lab value used to monitor LMWH and UFH
for LMWH: obtain peak 4 hours after dose
for UFH: obtain levels after IV starts and every 6 hours until therapeutic
Recommended monitoring LMWH in pregnancy
What is a Prothrombin Time/International Normalized ratio(PT/INR) and what can it be affected by?
Monitors warfarin levels
false elevations seen with Daptomycin, Oritavancin, Telavancin
You can remember the false elevators for both tests as: “Oritavancin & Telavancin mess with both aPTT and INR.”
What is aPTT/PTT monitor and what can affect its levels?
Monitors UFH & Direct thrombin inhibitors(i.e argatroban)
Falsely elevated by:
Oritavancin(ABx)
Telavancin(ABx)
You can remember the false elevators for both tests as: “Oritavancin & Telavancin mess with both aPTT and INR.”
What can cause Platelet levels to decrease?
Heparins
Fondaparinux
Linezolid
Valproic acid
What is HIT and how is it diagnosed?
when platelets drop > 50% from baseline d/t UFH or LMWH.
Diagnosis: If ELISA + → SRA (serotonin release assay) to confirm
What can decrease Albumin levels and what does drugs are affected?
are decreased in cirrhosis and malnutrition.
Low levels impact highly protein-bound drugs—> warfarin, calcium, and phenytoin
phenytoin and Ca require level adjustment when low
What are AST and ALT
enzymes released d/t hepatic injury
What is Bilirubin used for?
used with other liver tests to determine cause of liver injury and bile duct blockade
What do we use Ammonia levels for and what can affect its levels?
often measured in suspected hepatic encephalopathy
“ammonia associated with confusion”
increases in valproate and topiramate(topamax; confusion)
decreases with lactulose
What is Creatine kinase (CK, CPK) and what can increase its levels?
Assesses muscle inflammation or muscle damage.
can be increased via: “DS + TRD”
Daptomycin
Statins
Tenofovir
Raltegravir
Dolutegravir
Daptomycin + Statins + the integrase inhibitors (Raltegravir & Dolutegravir) + Tenofovir
What is Troponin T(TnT), Troponin I(TnI) BNP, pro-BNP?
TnT and TnI are used in the diagnosis of MI
BNP and NT-pro BNP are are markers of cardiac stress
non-specific to Heart failure or a disease state but higher values indicate a higher likelihood of heart failure
What are the Cholesterol goals?
Total cholesterol: <200 mg/dL
Low Density Lipoprotein(LDL): <100 mg/dL
High Density Lipoprotein(HDL): > 40 mg/dL for men or >50 mg/dL for women
Non-HDL: <130 mg/dL
Triglycerides(TG): <150
What is the Fasting LDL calculated (Friedwald equation)?
LDL = TC - HDL - (TG/5)
Only can be used if TG <400
Meds that increase LDL & TG
• HIV meds (efavirenz, protease inhibitors)
• Atypical antipsychotics (olanzapine)
• Diuretics (loops, thiazides)
• Immunosuppressants (CSA/TAC)
"HADI"
Meds that increase LDL only
• Fibrates (when TG are high)
• Fish oils (except vascepa)
Meds that increase TG only
• Bile acid sequestrants
• Propofol/Clevidipine
How to interpret Fasting plasma glucose results?
DM: >126 mg/dL
Pre-DM: 100-125 mg/dL.
Note: Fasting begins >8 hrs prior to blood draw
What is an HbA1c and the goals for patients based on the ADA and AACE?
HbA1C measures the average blood glucose over the past 3 months
Goal:
ADA < 7%
AACE ≤ 6.5%
What is the ADA glucose goals?
estimated Average Glucose: <154 mg/dL
used to correlate a finger stick with an A1C.
an eAG of 126 correlated with an A1C of 6%
Preprandial(before meals): 80-130 mg/dL
Postprandial(after a meal): <180 mg/dL
What test can be done to distinguish Type 1 and Type 2 DM?
C-peptide(fasting)
insulin is a polypeptide
What are Amylase and Lipase and what can cause there levels to increase?
Pancreatic enzymes
GDVH
GLP-1 agonists
DPP-4 inhibitors
Valproic acid
Hypertriglyceridemia
Just say: “GDVH raises amylase and lipase.”
What medications can cause either increased or decreased TSH levels?
Amiodarone, interferon
What drugs are known to only increase thyroid(TSH) levels?
lithium
carbamazepine
Tyrosine kinase inhibitors (TKIs)
What can increase Uric Acid?
High URIC ACID/GOUT is preventing me from DANCing
Diuretics
ASA (aspirin)
Niacin (B3)
Cyclosporine/ Chemo
What drugs known to cause liver damage?(DILI)
Highest-yield (must know)
Hydralazine
Procainamide
Isoniazid (INH)
These three are by far the most classic and highest risk.
Other important ones
Quinidine
Minocycline
Methyldopa
Chlorpromazine
TNF-α inhibitors (e.g., etanercept, infliximab, adalimumab)
What can be used to indicate immunosuppression?
CD4 lymphocyte count <200
What does a positive Human chorionic gonadotropin (hCG) indicate?
Indicates pregnancy
What does a + Luteinizing hormone (LH) mean?
ovulation
What does lactic acid/lactate indicate and what can increase it?
Indicates anaerobic metabolism
Increased by NRTIs, metformin, alcohol
What drugs can increase prolactin?
Haloperidol
Risperidone
Paliperidone
Purified protein derivative (PPD) skin test is used for
indicating TB exposure/infection
Rapid plasma reagin (RPR) or VDRL is used for
Antibody test for syphilis; requires confirmatory testing if positive
What does Thiopurine Methyltransferase(TPMT) indicate?
increase risk of myelosupression and patients need lower doses of azathioprine and mercatopurine
Drugs requiring Therapeutic Drug Monitoring (TDM)
With Very Persistent People, Therapeutic monitoring Can Definitely Lead To Good Vibes”
Warfarin
Vancomycin
Phenytoin / Fosphenytoin
Procainamide
Theophylline
Carbamazepine
Digoxin
Lithium
Tobramycin
Gentamicin
Valproic acid
Carbamazepine TDM
4-12 mcg/mL
Digoxin level in Afib?
0.8-2.0 ng/mL
Digoxin level HF?
0.5-0.9 ng/ml
Gentamicin & Tobramycin levels
Peak: 5-10 mcg/mL
Trough: <2 mcg/mL
Lithium trough level
0.6-1.2 mEq/L
Phenytoin/fosphenytoin level
Total: 10-20 mcg/mL (correct for low albumin)
Free : 1-2 mcg/mL
Procainamide levels
Procnamide: 4-10 mcg/mL
NAPA: 12.0 to 18.0 mcg/mL
Combined procainamide + NAPA therapeutic range: 10.0 to 30.0 mcg/mL
Theophylline level
5-15 mcg/mL
Valproic acid
50-100 mcg/mL (correct for low albumin)
Vancomycin level
Trough 15-20 mcg/mL for severe (pneumonia, endocarditis, osteo, meningitis, bacteremia) infection or AUC/MIC ratio of 400-600
Trough 10-15 mcg/mL for others (cellulitis)
Warfarin level
INR 2.0-3.0 (2.5-3.5 for mechanical mitral valve)
What is there to know about TDM?
Peak: highest concentration of drug
Trough: the lowest concentration taken right before next dose
Drug levels are Draw at steady-state (5 half-lives)
when drugs have a Narrow Therapeutic index → narrow range between sub- and supratherapeutic toxic concentrations