Wake PA Unit 3: (PHARM) Anti-Platelets & Anti-Coagulants
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/69

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
70 Terms
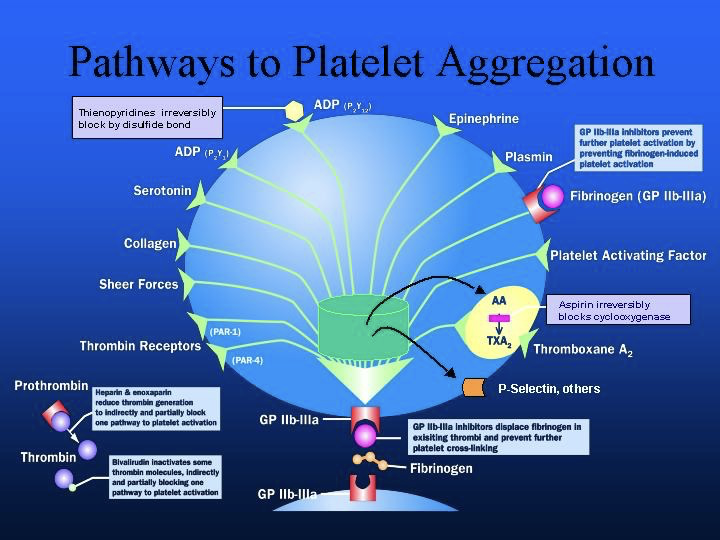
Image of all anti-platelet mechanisms
What is the mechanism of action of aspirin?
irreversible blocks cyclooxygenase —> inhibits arachidonic acid —> thromboxane A2 (AA axis)
What is the onset and duration of aspirin?
Rapid onset (minutes)
Long duration (5 days)
What are the SE of aspirin (outside of bleeding)?
GI upset, angioedema (rare)
What are the indications for aspirin?
ACS, chronic stable angina, stroke prophylaxis, PAD
What is the MOA for clopidogrel and prasugrel?
Thienopyridines: P2Y12 receptor inhibition (irreversible)
*P2Y12 normally binds ADP —> platelet aggregation
What is the onset and duration for clopidogrel and prasugrel?
Rapid onset (hours)
Long duration (5-7 days)
What are the SE of clopidogrel (outside of bleeding)?
Rash, TTP
What are the SE and C/I of prasugrel (outside of bleeding)?
rash
avoid use in TIA/stroke, age > 75, <60 kg
What are the indications for clopidogrel?
ACS (med management or PCI/stent), PAD, thrombotic stroke
What are the indications for prasugrel
ACS: PCI/stent (patients who have had mechanical intervention) *more narrow use
What is the MOA for ticagrelor and cangrelor?
Non-thienopyridines
P2Y12 inhibition (reversible)
*cangrelor is IV ticagrelor used in hospital setting
What is the onset and duration for ticagrelor and cangrelor?
ticagrelor: rapid onset (hours) and long duration (3-5 days)
cangrelor: rapid (minutes) and short duration (< 1 hour)
What are the SE of ticagrelor?
Dyspnea, increased serum creatinine (reversible), hyperuricemia (caution in gout)
What are the SE of cangrelor?
dyspnea
What are the indications of ticagrelor?
ACS (med management or PCI/stent)
What are the indications of cangrelor?
Adjunct to PCI not treated with P2Y2 inhibitor or GP2b3a inhibitor
What is the MOA for dipyridamole?
Inhibits platelet adensoine deaminases and phosphodiesterases ( increases cAMP which decreases platelet aggregation)
What is the MOA for cilostazol?
inhibits platelet phosphodiesterase III (increases cAMP which decreases platelet aggregation)
What is the MOA for vorapaxar
inhibits thrombin and thrombin receptor agonist peptide (TRAP) at PAR-1 receptor
What is the onset and duration for dipyridamole?
Rapid onset (hours) and short duration (hours
What is the onset and duration for cilostazole?
Rapid onset (hours) and short duration (hours)
What is the onset and duration for vorapaxar?
Slow onset (days) and long duration (up to 1 month)
What are the SE for dipyridamole?
dizziness, HA, GI upset
What are the SE for cilostazol?
Dizziness, pedal edema, palpitations, HA, GI upset
What are the SE for vorapaxar?
bleeding, rash
Which anti-platelet therapies are the strongest? Weakest?
Best: GP2P3A blockers and cangrilor
Middle: Oral P2YA
Least: ASA, miscellaneous
List the glycoprotein IIb/IIIa receptor inhibitors
Eptifibatide (Integrilin)
Tirofiban (Aggrastat)
What is the MOA for eptifibatide and tirofiban?
block GP2B3A receptor (reversible)
What is the onset and duration for eptifibatide and tirofiban?
immediate onset, duration hours
What are the SE for eptifibatide and tirofiban?
Bleeding, thrombocytopenia (pseudo- and true)
What happens to clopidogrel in patients who are taking esomeprazole or omeprazole?
clopidogrel prodrug may remain inactive when taken with esomeprazole or omeprazole
What is the MOA of warfarin (Coumadin)?
VKA: Vitamin K epoxide reductase inhibitor (prolongs clotting time by inhibiting synthesis of vitamin K factors II, VII, IX, and X)
Inhibits Proteins C and S
What is the onset and duration of Warfarin?
delayed onset (days to kick in)
delayed duration (days to go away)
What is the metabolism of warfarin and risks
Hepatic —> NUMEROUS drug/diet interactions!!
What is the monitoring requirement of warfarin (Coumadin)?
CBC
INR: usually 2.0-3.0, consider reduced (1.8-2.2) for high bleed risk
What are the side effects of warfarin (Coumadin)?
bleeding, skin necrosis
Which medications increase INR with warfarin? Which decrease INR?
Increase: azole antifungals, most ABX, some anti-arrythmics
Decrease: rifampin, phenobarbital, primidone, carbamazepine, cholestyramine
**run drug interaction screen
What are the food interactions with warfarin (Coumadin)?
the leafier/greener the food, the more vitamin K
Decrease the anticoagulant effect of warfarin!
What is the reversal agents of warfarin?
Vitamin K (po, SC, IV, dietary)
Fresh frozen plasma (factors II, VII, IX, X)
Prothrombin complex concentrates (actived and inactivated factors)
List the direct thrombin (IIa) inhibitor
dabigatran (Pradaxa)
List the factor Xa inhibitors
rivaroxaban (Xarelto)
Apixaban (eliquis)
Edoxaban (savaysa)
What are the advantages of DOACs (direct oral anticoagulants)?
rapid onset/offset, fewer DI, minimal food interactions, more predicable dosing, decrease monitoring
What is the onset and duration of DOACs?
rapid (hours) onset, duration days
What is the monitoring for DOACs?
SCr
What are the side effects of DOACs?
bleeding, N/V
When should you use DOACs?
Patients with non-valvular AF, pulmonary embolism, deep vein thrombosis, secondary prevention of VTE, postop VTE prophylaxis
What are the reversal agents for DOACs?
How do you typically dose DOACs?
Once daily dosing: rivaroxaban, edoxaban, betrixaban
Twice daily dosing: dabigatran, apixaban
Dose reductions warranted for renal dysfunction
*more complex dosing for VTE (loading dose, etc)
When should you avoid use of edoxaban?
when CrCl > 95 mL/min (clears drug too fast)
When should you avoid use of DOACs?
Obesity, mechanical valves, malignancy, decreased renal function
What is the MOA for unfractionated heparin (UFH)?
Binds to antithrombin III, which then inhibits factors IIa, IXa, Xa, XIa, XIIa
Binds to numerous other proteins resulting in unpredictable response
*does not affect clot-bound thrombin or platelet-bound Xa
What is low molecular weight heparin?
Cleaved UFH to minimize protein interactions
List the LMWH/factor Xa inhibitors
Enoxaparin (Lovenox) - inhibits Xa and IIa
Fondaparinus (Arixtra) - inhibits Xa
what is the MOA for LMWH/Factor X inhibitors
Bind to antithrombin III to inhibit factor Xa ( and IIA for Lovenox)
What is the black box warning for LMWH?
What is the monitoring for parenteral anticoagulants?
CBC
What are the side effects for heparin, enoxaparin, and fondaparinux?
Bleeding, decreased platelets
Injection site bruising (enoxaparin, fondaparinux)
What is the MOA for direct thrombin inhibitors (DTI)?
Directly inhibits factor IIa (thrombin)
Bind free and clot associated thrombin
List the DTIs
Bivalirudin, (kidney clearance) argatroban (liver clearance)
*Hospital drugs; IV only
What is the monitoring for argatroban and bivalirudin?
CBC
PTT
LFTs (argatroban)
SCr (Bivalirudin)
What is the reversal agent for parenteral agents?
heparin and LMWH: protamine
fondaparinux, argatroban, bivalirudan: none
What is HIT?
Heparin induced thrombocytopenia
Type I: mild, transient thrombocytopenia
Type II: autoantibodies agains heparin-PF4 complex —> thrombosis
How do we diagnose HIT? (timing, platelets, labs, etc)
Onset 5-10 days after initiation
Platelet decrease >=50%
New thrombosis
+ PF4-heparin Ab
Probability score
How do you manage HIT?
STOP heparin products
Anticoagulate with DTI or fondaparinux (may transition to warfarin)
Treat at least 4 weeks OR 3 months if thrombosis
note heparin allergy
What is the MOA for fibrinolytics (alteplase, tenecteplase)?
Enhance plasminogen to plasmin reaction —> more fibrin breakdown
List the fibrinolytics
Alteplase (TPA)
Tenecteplase
What are the indications for alteplase (TPA) and tenecteplase?
Given in an ambulance or hospital ED
Acute ischemic stroke, STEMI, pulmonary embolus, peripheral arterial occlusion
What is the monitoring for alteplase and tenecteplase?
CBC, resolution of symptoms
What are the SE for alteplase (TPA) and tenecteplase?
bleeding
intracranial hemorrhage