9.24 Dr. Kwon Neuromuscular Disorders Lecture + DMD/BMD/EDMD + CMT
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/13

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
14 Terms
Neuropathies
Both Motor and Sensory Involvement. Symmetric, Distally, in the legs

Myopathies
•Weakness (Motor only)
•Symmetric
•Proximal > Distal
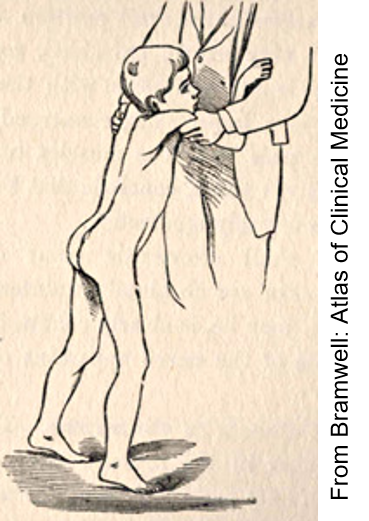
Congenital Myopathies
•Generalized weakness with poor muscle bulk
•Hypotonia, areflexia
•Generally slowly or non progressive
SMA

Genes involved:
SMN1 — the disease-causing gene; SMA results from loss of both copies (almost always via deletion)
SMN2 — a "backup" copy that occasionally gets transcribed correctly, producing a small amount of functional SMN protein. Copy number varies person to person (1, 2, 3, or more copies), which is why complete absence of SMN protein is incompatible with life but reduced SMN protein isn't
Clinical characteristics:
Weakness due to lower motor neuron dysfunction and degeneration
Caused by deficiency of SMN protein, which is needed for motor neuron development
Brain function and cognitive development are normal
Incidence: 1 in 10,000
Duchenne Muscular Dystrophy (DMD)
Genes involved:
DMD gene (Xp21) — the largest known human gene, 79 exons spanning 2.4 million base pairs, 99% intronic
Encodes dystrophin, which connects the muscle cytoskeleton to the sarcolemma (cell membrane)
Causative variants: typically loss-of-function (LOF) mutations
Clinical characteristics:
Incidence: ~1 in 3,500–5,000 live male (XY) births — the most common form of childhood muscular dystrophy
Progressive proximal muscle weakness starting in early childhood
Symptoms present before age 5; wheelchair dependency before age 13
Loss of neck flexor muscle strength
Rapid progression → loss of independent ambulation in early adolescence; respiratory weakness and cardiomyopathy become major later complications; historically fatal from pulmonary complications in the 20s–30s
CK elevated >10x normal range
Female carriers: most asymptomatic, but some have real risk — DMD-related cardiomyopathy (~7–17%) even without muscle weakness, increased peripartum cardiomyopathy risk;
mechanisms include non-random X-inactivation, X-rearrangement at Xp21.2, Turner syndrome, or X-chromosome UPD — some of these carriers may actually meet criteria for DMD themselves
Becker Muscular Dystrophy (BMD)
Genes involved:
Same gene as DMD — DMD (Xp21)
Key difference: mutations are typically in-frame (missense variants, or deletions/duplications that preserve the reading frame) → shorter but partially functional dystrophin, retaining 10–40% normal dystrophin function
Clinical characteristics:
Incidence: ~1 in 18,000–30,000 live male births
Milder, later-onset, more slowly progressive version of the DMD phenotype
Progressive proximal muscle weakness, calf hypertrophy, activity-induced cramping
Wheelchair dependency after age 16 (vs. before 13 in DMD)
Preservation of neck flexor strength (vs. loss in DMD)
CK elevated >5x normal (vs. >10x in DMD)
Highly variable phenotype
Treatments available:
Primarily supportive/complication-directed: PT/exercise (avoiding excessive eccentric injury), contracture management, cardiology monitoring (ECG + MRI, arrhythmia management), pulmonology (PFTs, supportive ventilation as needed)
Bone health, nutrition, psychosocial, occupational support as needed
No disease-modifying therapies listed (unlike DMD) — treatment is individualized given the variable phenotype
Types:
Not subtyped — positioned as the milder end of the DMD/BMD spectrum
Emery-Dreifuss Muscular Dystrophy (EDMD)
Genes involved:
LMNA (1q21.2) — the deck focuses on the LMNA-related form specifically
Encodes lamin A/C, structural proteins of the nuclear lamina/envelope
Autosomal dominant: missense or small in-frame deletions → dominant-negative effect on lamin A/C structure (~65% de novo)
Autosomal recessive: missense, nonsense, or frameshift variants → loss-of-function of lamin A/C
Molecular diagnosis can also implicate: EMD or FHL1 (hemizygous variants), SUN2, SYNE1, SYNE2, TMEM43 (heterozygous variants), or biallelic variants in LMNA or SUN1
Clinical characteristics:
Incidence: ~1 in 250,000–400,000 (much rarer than DMD/BMD)
Prominent joint contractures before age 10 — elbows, Achilles tendons, posterior cervical muscles, and/or entire spine
Bilateral muscle weakness/wasting
Cardiac disease by age 20–30 (conduction disease, arrhythmias, cardiomyopathy) — can initially be asymptomatic or present with palpitations, bradycardia, dizziness, presyncope/syncope, poor exercise tolerance
Childhood onset, slow progression
No cognitive involvement
Pathophysiology: mutated lamin A/C → structurally abnormal nuclear envelope → impaired mechanical resilience → impaired function/survival of skeletal and cardiac muscle cells
Treatments available:
Primarily supportive/complication-directed, with cardiac risk as the priority ("preventing sudden cardiac death may be more immediately life-saving than treating skeletal muscle weakness")
Cardiology: regular ECG, ambulatory monitoring, echo; pacemaker, ICD, or heart-failure therapy if indicated
PT/OT/Surgery: stretching to preserve ROM, moderate activity; orthotics or surgical release for severe contractures
Pulmonology: routine monitoring, noninvasive ventilation if needed
Types:
Deck distinguishes only by inheritance pattern (AD vs. AR), not by numbered subtypes
CMT Overall
Charcot-Marie-Tooth Disease (CMT) — overall
Genes involved:
Genetically heterogeneous: over 130 associated genes, all involved in creating, maintaining, or regulating the myelin sheath or nerve fibers
PMP22 singled out as the most common/notable gene:
Synthesizes/maintains myelin; encodes a protein comprising 2–5% of peripheral (not central) nervous system myelin
Possible role in Schwann cell growth/differentiation
Mutation types: recurrent deletions and duplications, plus point mutations
Duplication → PMP22 overexpression; deletion → reduced expression; both cause Schwann cell dysfunction and abnormal myelin regulation
Clinical characteristics:
Also called Hereditary Motor and Sensory Neuropathy
Length-dependent, chronic neuropathy — longest nerves affected first, so hands/feet show signs earliest
Most common inherited neuropathy; prevalence estimates 1 in 2,500 to 1 in 5,000
First classified in 1886 (independently by Charcot, Marie, and Tooth)
Genetically and phenotypically heterogeneous
Physical findings: foot drop, stork-leg deformity (lower legs waste, upper legs spared), pes cavus, hammer toes; deep tendon reflex changes; breathing/swallowing/speech issues rare (severe cases only); no cardiac monitoring needed (contrast with the muscular dystrophies above)
CMT1
Genes Involved : CMT1A : PMP22 duplication (1.5 Mb), 70% of CMT1; CMT1B = MPZ mutations
~50% of all CMT
Demyelinating
Autosomal dominant
Early, Distal motor weakness/atrophy, moderate NCV slowing, legs > arms
CMT2
Genes Involved : MFN2, GDAP1
~15-30% of all CMT
Axonal
Autosomal dominant
Early, Distal motor weakness/atrophy, moderate NCV slowing, legs > arms
CMTX
Genes Involved : GJB1 (connexin 32) point mutations
10–15%% of all CMT
Demyelinating + axonal
XL
Gait impairment, mild NCV slowing, males more severely affected
CMT3
Genes Involved : ?
Uncommon
Demyelinating + axonal
Autosomal dominant
Early, Distal motor weakness/atrophy, moderate NCV slowing, legs > arms
CMT4
Genes Involved : ?
<10%
Demyelinating
Autosomal recessive
Genetically heterogeneous; may include hypotonia in infancy, cataracts, hearing loss; can be more severe
Hereditary Neuropathy with Liability to Pressure Palsies (HNPP)
Genes involved:
80% of cases: deletion of 17p11.2–p12, which includes the PMP22 gene (or another deletion involving PMP22)
20% of cases: a sequence variant in PMP22
(Note the reciprocal relationship to CMT1A: CMT1A = PMP22 duplication; HNPP = PMP22 deletion)
Clinical characteristics:
Autosomal dominant; ~20% of cases de novo
Usually develops in the 2nd–3rd decade, though earlier onset is possible
Symptoms vary in severity
Pressure-induced sensory and motor neuropathy: fatigue, pain, sensation loss, tingling, weakness in extremities — may be painless
Recurrent, acute episodes with often-full recovery; repeated incidents can cause permanent weakness/sensory loss
Can cause limb paralysis if an unaware patient undergoes strenuous activity
May include pes cavus and (per notes) hearing loss
Often under-recognized: patients may only realize they have the condition after a strenuous/unusual episode, and may be misdiagnosed as stroke, MS, or other polyneuropathy
Treatments available:
Same multidisciplinary/supportive framework as CMT (PT/OT, orthotics, pain medications)
HNPP-specific: activity modification to avoid nerve compression, protective padding, care during surgery to avoid compression