Solid tumour interactive cases
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/24

There's no tags or description
Looks like no tags are added yet.
25 Terms
CASE 1


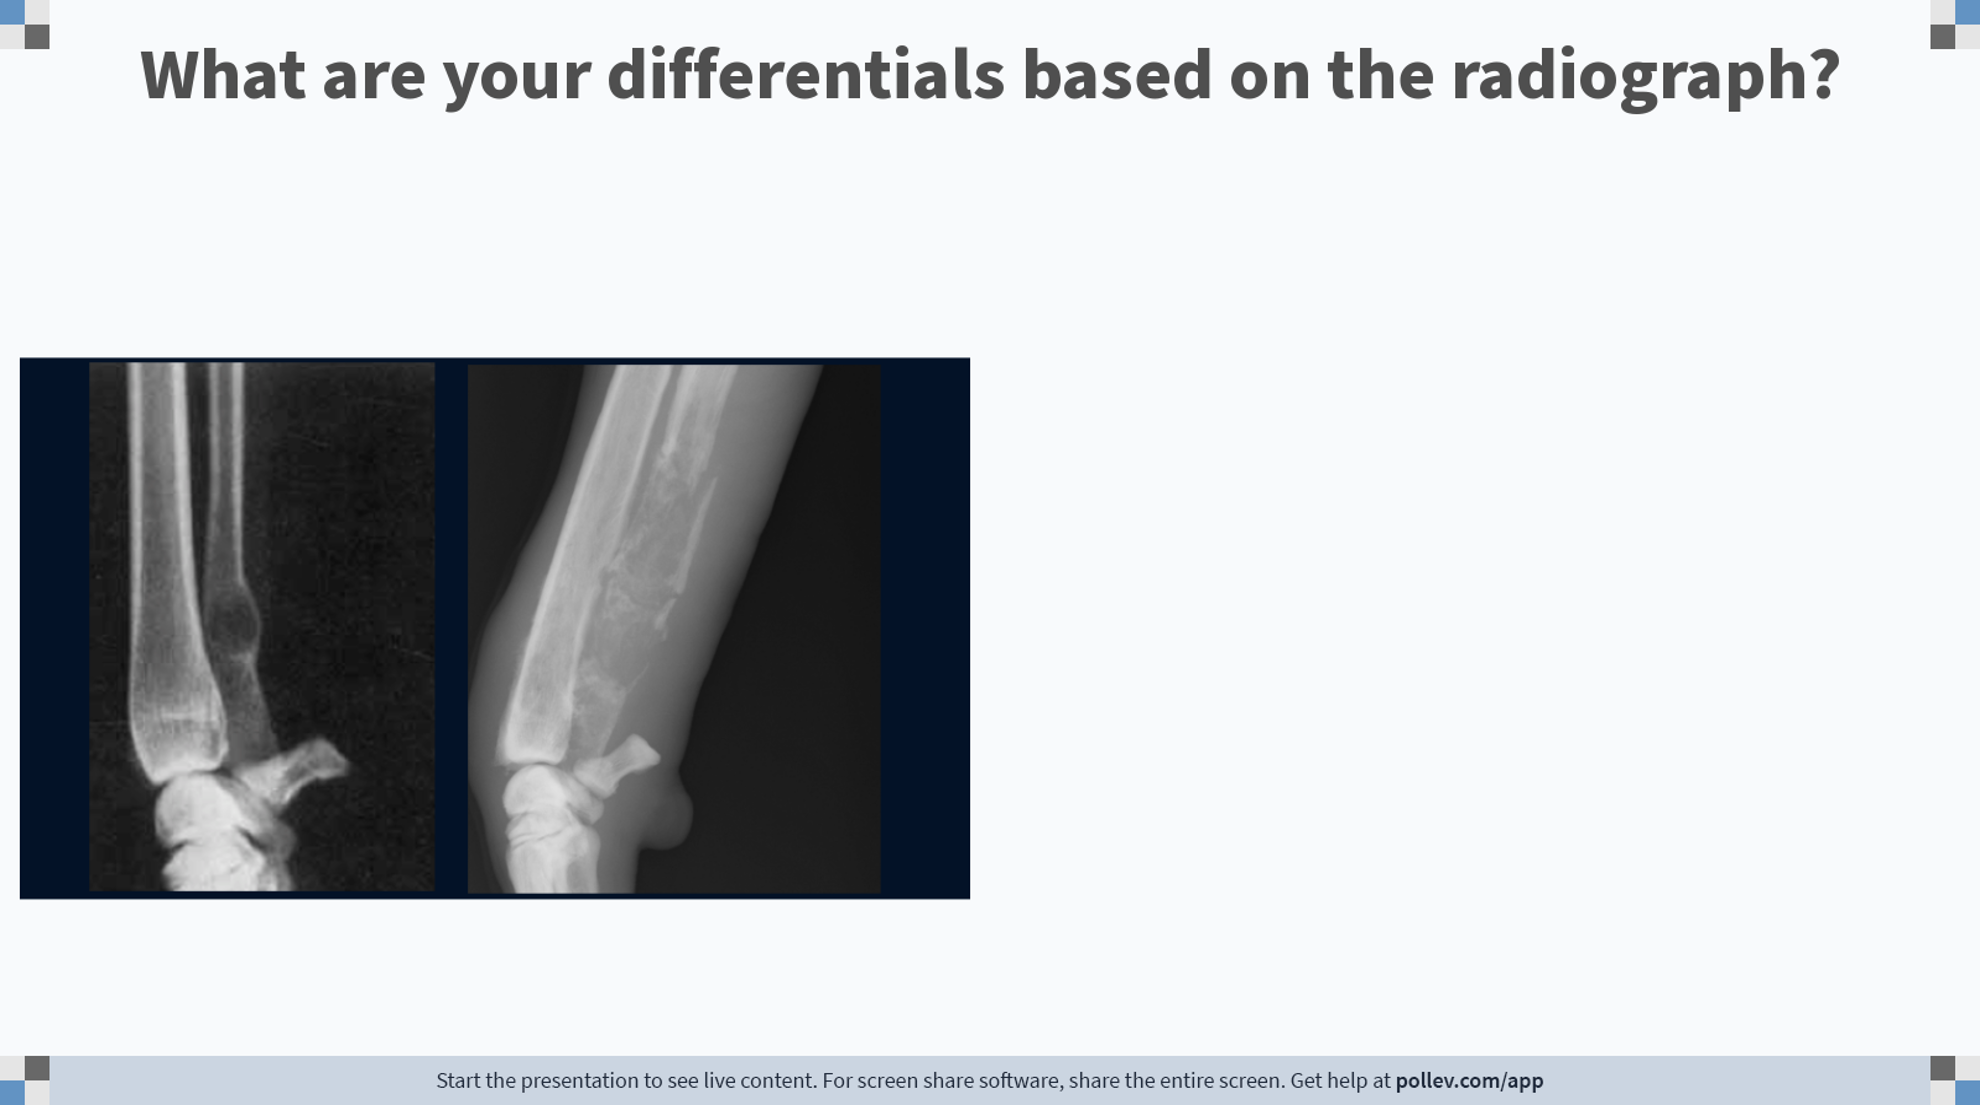
Soft tissue swelling
Osteolysis (permeative and moth eaten) of the metaphysis of the ulna
Interrupted periosteal reaction
Prolonged zone of transition
CASE 1
Neoplastic
Osteosarcoma
Chondrosarcoma
Fibrosarcoma
Histiocytic sarcoma, Hemangiosarcoma
Metastatic lesion less likely
Infectious
Fungal osteomyelitis
Bacterial osteomyelitis less likely
CASE 1
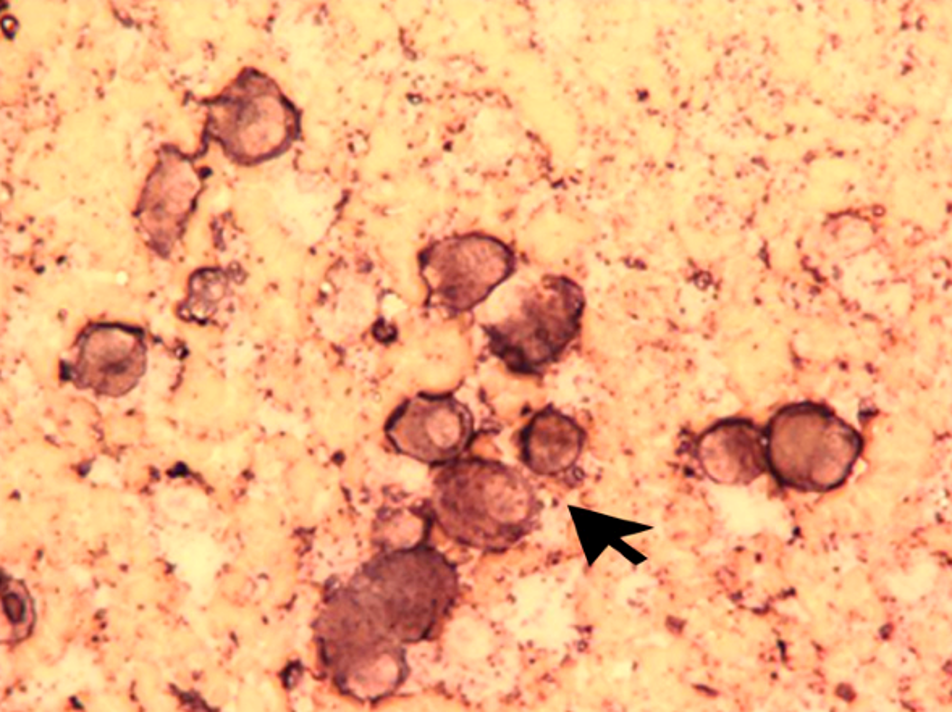
Cytology:

Mesenchymal cell in origin = osteosarcoma likely
may not always be diagnostic:
ALP staining
bone biopsy
Jamshidi needle
CASE 1 bloods:
Haematology was normal
Biochemistry ALP 550U/L (incr by almost 3x upper limit)
Are you worried by the ALP pre-excision?
Yes —> incr ALP is -ve prognostic factor
CASE 1
Which approach is ass. w/ best survival?
Amputation + adjuvant carboplatin
CASE 1
Follow ups
Thoracic rads q. 3 months
or if any suspicion of clinical deterioration —> cough (lung mets), lameness (bone mets), skin nodule w/ cytological diagnosis of mesenchymal tumour
CASE 1
Rads @ 6 month follow up:

Nodular lesions —> metastasis
started toceranib (tyrosine kinase inhibitor)

CASE 2


Haematological findings:
Non-regen (or pre-regen) normocytic, normochromic anaemia
Moderate thrombocytopenia
CASE 2

Schistocytes —> RBCs suffered damage → lost normal circular shape i.e. fragmented
CASE 2

Mild hypoproteinaemia
Mild incr creatinine
Microangiopathic anaemia?
DIC?
Haemorrhage?
Pre-renal azotaemia?
CASE 2
What are the next steps?
Imaging (thorax & abdo)
Coag profile —> DEA -ve
DIC —> signs = spontaneous bleeding / thromboembolism
present in up to half dogs w/ visceral haemangiosarc
clinical path —> low / falling platelet count, prolonged PT & APTT, incr FDPs / D-dimers
Blood type
CASE 2
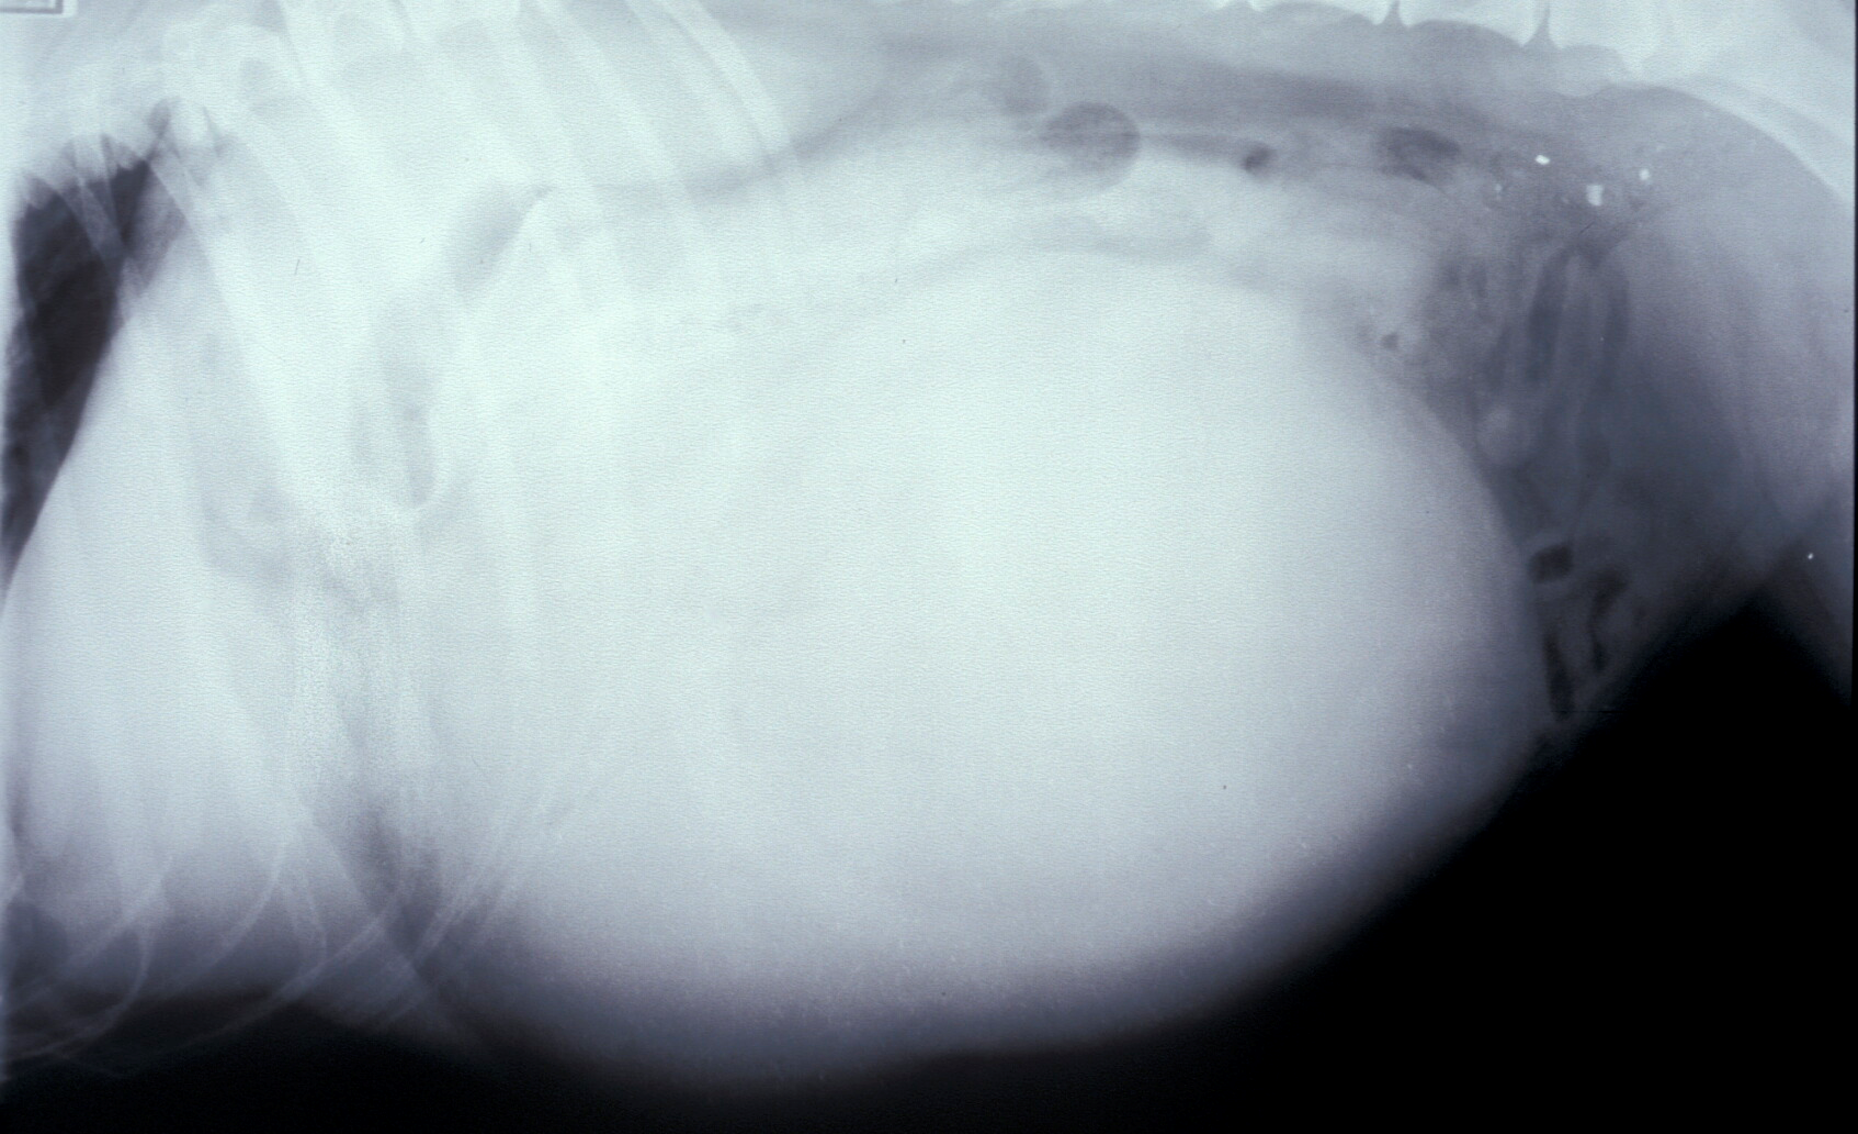
Mass effect displacing intestine dorsally, abdo effusion
CASE 2

Mass in spleen
Free fluid between viscera
CASE 2
Next step —> abdo fluid investigations:
Haemorrhagic looking
PCV 15%
TP 37g/L
On cytology —> see RBCs w/ occ. neutros & minimal lymphos
***
CASE 2
Tx
Transfusion w/ DEA -ve blood (ideally whole blood) then surgery
Surgery —> surgery alone ass. w/ 2-4 months survival —> chemo may incr this e.g. epirubicin

CASE 3
Bloods unremarkable
No abnormalities on thoracic rads & abdo U/S
Recommended tx?
Left total mastectomy or regional mastectomy M3-M5 incl L inguinal LN
(discuss pros & cons w/ owner —> complications higher with total e,g. infection, break down of wound, longer recovery time)
CASE 3
Describe the outcome of spay as tx
Can decr risk of further development of benign tumour
Can improve outcome in grade II mammary tumour w/ oestrogen expression
Make sure to change instrument between spay & mammary tumour removal to avoid seeding
CASE 3
Grade III mammary carcinoma diagnosed
Metastasis to L inguinal node confirmed
Is chem indicated?
Not sure @ this stage —> not enough evidence to say whether improves mammary tumours
What is this?

Inflammatory mammary carcinoma
More extended —> diff from nodular lesions
Poor prog to chemo
CASE 4

DDx?
Most likely:
Oral melanoma
Fibrosarcoma
SCC
Plasma cell tumour
Haemangiosarcoma
Osteosarcoma
Epulis
FB
Transmissible venereal tumour (if hx of travel)
CASE 4
Ddx of melena?
Oral lesion
Nasal lesion
GI lesion
CASE 4
Haemorrhage of mass ddx?
Friable lesion / trauma to mass / poor quality tumour vasculatur
Coagulopathy
CASE 4
L submandib lymphadenopathy ddx?
Reactive inflam
Neoplasia
CASE 4
What test next?
Haematology & coags

= regen anaemia
Thoracic xrays:

no mets
Biopsy

consistent w/ haemangiosarc
CASE 4
Tx options?
To slow down development of metastasis:
High dose chemo w/ doxorubicin / epirubicin
and / or
Metronomic chemo (cyclophosphamide & melox)