Abdominal Imaging II
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/34

There's no tags or description
Looks like no tags are added yet.
35 Terms

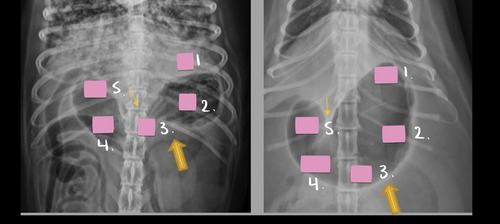
1. Stomach
2. Cecum
3. Ascending colon
4. Descending colon
5. Small intestines

1. Descending duodenum
2. Ascending colon
3. Stomach
4. Trans colon
5. Cecum
6. Ascending duodenum
7. Small intestines
8. Descending colon
9. Rectum
1. Cardia
2. Fundus
3. Body
4. Pyloric antrum
5. Pyloric curvature
Dog vs cat stomach
Cat stomach is smaller, have fat in the submucosa, and pyloric sphincter is on midline or to the left
Dog pylorus is to the right of midline
On a left lateral view, there should be __ in the pylorus and __ in the fundus.
Gas, fluid
On a right lateral view, there should be __ in the pylorus and __ in the fundus.
Fluid, gas
Important view sequence in a suspected GDV
Start w right lateral - most sensitive, diagnostic
VD is next important view
Common presentation of dogs with a GDV
- large/giant breed dog
- non productive retching
- possible abdominal distension
- signs of obstructive shock (tachycardia, hypotension, poor pulse quality)
Radiographic findings of a GDV
PYLORUS DORSAL AND TO THE LEFT
Generally a gas filled stomach
+/- splenomegaly
Compartmentalization - soft tissue “band” that crosses the stomach, represents stomach folding onto itself
Pneumatosis or pneumoperitoneum
Megaesophagus
Small intestinal dilation

What is gastric pneumatosis?
Gas visible within the gastric wall
In cases of GDV, may be a poor prognostic indicator
May have to do some sort of gastric resection in surgery
True or false: food bloat is a surgical emergency.
False
Presentation of dogs with food bloat
- non productive retching
- abdominal distension
- abdominal pain
- lethargy/anorexia
Radiographic appearance of food bloat
- stomach is distended by heterogenous soft tissue opacity (not gas)
- stomach is normally positioned within the abdomen
Food bloat can be difficult to distinguish from...
Pyloric outflow obstruction
How can we differentiate food bloat from a pyloric outflow obstruction?
Repeat rads following medical management (IV fluids, pain meds) and 12 hour fast - gastric content should be moving through GI
Diagnosis of gastric foreign bodies on rads
Repeat rads following a 12 to 24 hour fast - food will have passed into SI and foreign material will likely linger
What view do we need to diagnose a pyloric outflow obstruction?
Left lat
Appearance of pyloric outflow obstruction
Gas halo surrounding soft tissue opaque material in pylorus

Diagnosis of gastric masses
Normally cannot be seen - need contrast study, ultrasound, CT
Common gastric tumors in dogs vs cats
Dogs - adenocarcinoma
Cats - lymphoma
Appearance of uremic gastropathy
Mineralization of the gastric wall on rads/ultrasound
Normal SI size
Dogs < 1.5 x the height of the mid aspect of L5
Cats < 12 mm
What is mechanical ileus and what is seen radiographically?
Obstructed SI lumen
- any combo of opacities
- 2 populations of small intestine, one more dilated than the other
Causes of mechanical ileus
- foreign material
- luminal mass
- extra luminal mass
- stricture
What is functional ileus and what is seen radiographically?
Decreased motility from vascular or neuromuscular abnormalities of the GI wall
- gas opaque
- generalized dilation
SI size parameters in the dog - normal and abnormal
Max serosa-serosa diameter/height L5
Normal is < 1.6 x height of L5 vertebral body
SI max/L5 between 1.6-2.4 may be obstructed
SI max/L5 > 2.4 very likely obstructed
SI size parameters in the cat - abnormal
Abnormal > 1.6 x the height of the cranial endplate of L5
Abnormal > 12mm

Gastric pneumatosis

Mechanical ileus

Functional ileus

Food bloat

Mechanical ileus

Gastric dilation

GDV

Gastric dilation