Adipose Biology and Chronic Disease Risk
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/55

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
56 Terms
What are the two main functions of adipocytes?
lipid (TAG) storage and mobilization (which tend to be highly regulated by hormones)
endocrine functions
Describe some of the endocrine functions of adipocytes (2).
adipokines: bioactive proteins and signaling molecules released by adipose (fat) tissue that regulate metabolism, inflammation, and energy balance
ex: adiponectin and leptin
cytokines: many are produced by adipocytes
ex: TNFa, IL-1, IL-6
What is visceral adiposity?
fat w/n the abdominal area
metabolically active
What is subcutaneous adipose?
adipose that is more readily distributed throughout the body
What is hypertrophy?
enlargement
overweight (BMI 25 - 29.9) and moderate obesity (BMI 30 - 34.9) are characterized by adipocyte hypertrophy
What is hyperplasia?
increase in number
extreme obesity (BMI > 40) is characterized by both hyperplasia and hypertrophy
What happens when adipocytes undergo hypertrophy or hyperplasia?
tend to attract immune cells amongst the tissue, causing inflammation
Describe the characteristics associated with adipose tissue in lean individuals.
insulin sensitive
absence of inflammation
secrete adiponetctin, IL-4, IL-10 (which help to maintain insulin sensitivity)
Describe the characteristics associated with adipose tissue in overweight/obese individuals.
insulin resistant
MCP-1 chemokine recruits more macrophages which secrete
pro-inflammatory cytokines (IL-1beta, TNFa, etc)
secrete more chemokines
hypertrophy and hyperplasia
increase in leptin (and increased can cause our brain to be desensitized to it, making us unaware when we are full) and decrease in adiponectin
hypoxia (body tissues do not get enough oxygen to function properly)
ROS
promotion of lipolysis and release of FFA
What is ectopic fat?
storage of TG in tissues or locations not usually associated with significant adipose tissue accumulation such as liver, muscle, renal, and pancreas (have a lipid overflow and they need somewhere to go)
What is the issue with ectopic fat?
the metabolic inflammation that occurs in excessive adipose tissue with the help of the immune cells, will begin to occur within these different tissues (sub-clinical inflammation)
results in metabolic changes in the liver, muscle, renal function, pancreas, etc.
causes insulin resistance in multiple tissues including the liver and increased glucose output by liver (bc think that we are starving)
beta cell dysfunction in pancreas, causing changes in insulin output
overall has health implications as it increases the risk of type II diabetes and endothelial dysfunction (vascular dysfunction), high BP, and CVD
Describe a way in which immune cells (such as macrophages) communicate with adipocytes in adipose tissue.
adipocytes have cross talk with macrophages and these macrophages overproduce pro-inflammatory cytokines such as TNF-a
TNF-a cytokines can act (paracrine, endocrine, autocrine, etc) to interact with adipocytes inducing NFkB pathway to make more cytokines
additionally cytokine binding on adipocyte contributes to inhibition of insulin signaling pathway
causes insulin resistance and lipolysis (release of FFA)
FFA released from adipocyte can bind to another TLR4 receptor on the adipocyte and macrophage, inducing MORE NFkB activation

What do the adipocytes of obese individuals overproduce?
adipokines
except adiponectin (used for regulation)
Why is NFkB referred to a lot?
it is a central pathway to inflammatory metabolic responses
Why can’t NFkB just be inhibited so that we don’t have inflammation?
bc it contributes to a lot of things alongside inflammation

better off modulating diet
Describe this image:


Describe obesity stats worldwide.
43% of adults are overweight and 16% obese
doubled from 1990
Describe obesity stats in the US.
40.3% of adults are obese and 21.1% of youth are obese
Where is obesity more prevalent?
low income households
varies with racial and ethnic status (black, hispanic, and white)
How many out of the top ten leading causes of death are diet related?
4/10
45% of cardiometabolic deaths are related to suboptimal intake of dietary components and patterns
What are the three contributors to obesity?
behavior and energy balance
genetics (typically polygenic)
environment
obesity is multi-factorial
What is energy balance influenced by?
interaction of genetic and epigenetics; metabolic, hormonal, physiological factors, environment, behavior, lifestyle, gut microbiome, living situation, chronic stress, sleep pattern etc.
What are two different models explaining why there is more obese/overweight people?
Energy Balance Model (EBM)
Carbohydrate-Insulin Model (CIM)
Characteristics associated with the Energy Balance Model (EBM).
obesity is caused by highly palatable foods and obesogenic environments
disrupt food intake signaling, resulting in a positive energy balance
Characteristics associated with the Carbohydrate-Insulin Model (CIM).
obesity is caused by alterations in fuel partitioning
favors storage (ex: via fructose pathway) due to high intake of rapidly digestible carbohydrates
rapid high insulin promotes adipose storage
What are the two categories of mechanisms that help to regulate our food intake/energy balance?
homeostatic mechanisms
non-homeostatic mechanisms
What are non-homeostatic mechanisms that help to regulate our food intake/energy balance?
hedonics (taste, smell, emotional memory)
stress (cortisol)
What are two types of homeostatic mechanisms that help to regulate our food intake/energy balance?
adipokines (long term signals)
gut hormones and physical (short term gut-brain axis signals, tells us the presence of food and nutrient metabolism)
What are two adipokines?
leptin
adiponectin
Role of leptin.
synthesized by adipocytes
signals to reduce appetite and increase energy expenditure
obesity: leptin production in increased but neurons in brain are resistant to its actions
Role of adiponectin.
synthesized by adipocytes
signals to improve insulin sensitivity
obesity: adiponectin production is decreased
What gut hormone signals hunger?
ghrelin
synthesized by stomach
What three hormones can signal satiety?
CCK
GLP-1
Insulin
Characteristics of CCK.
stimulated by protein and fat
secreted by I cells in proximal small intestine
helps to regulate the release of pancreatic enzymes and bile
Characteristics of GLP-1.
produced by L cells in the distal small intestine (ileum)
regulates pancreatic alpha and beta cells and insulin response
What is the difference between hunger and appetite?
hunger
physical need for food
response to low blood glucose
physical sensation in stomach
appetite
desire for food with or without hunger
includes sensory and emotional aspects and is tied into brain reward systems
can be dysregulated in eating disorders
What is the influence of the gut microbiota on obesity?
gut microbiota can produce neuroactive peptides (ex: serotonin) and SCFA which can affect host metabolism and appetite
gut microbiota profiles and ecology differ in obesity (which is associated with increase capacity for energy harvest from dietary intake)
can play a role in metabolic disorders
colonization of germ free mice w/ gut microbiota from obese human resulted in increased total body fat compared to lean gut microbiota
NOT the only determinant it is a lot more complex
changed in gut microbiota was determined by high fat diet NOT obesity state
How do you define a disease?
it is a pathological condition of a part, organ, or system of an organism resulting from various causes, and characterized by identifiable signs and symptoms, with potential adverse health consequences and outcomes
What are the three general features of disease?
recognizable etiologic agents
consistent anatomical alterations, related to pathophysiology
identifiable signs and symptoms, features of impaired health
Is obesity considered a disease?
Yes

its a chronic and relapsing disease, not something that can be fixed by a quick diet
What are the different organizations that consider obesity a disease? (9)

Describe health insurance coverage as it relates to obesity.
medicare/medicaid will cover some obesity related treatments (ex: behavioral therapy and bariatric surgery if necessary) HOWEVEr, it does not routinely cover anti-obesity medications
large variations in what treatments insurance companies will reimburse for when considering obesity treatment, and many will pay for treating conditions caused by obesity but not the underlying obesity condition
What are the different body fat percentages associated with obesity in men vs women?
males: > 25%
females: > 33%
Definition of obesity.
having an excess of adipose tissue or a very high amount of body fat in relation to lean body mass
What are three indirect measures of obesity?
waist circumference
waist:hip rati
body mass index
Describe waist circumference in relation to obesity.
men: >102 cm (> 40in)
women: > 88 cm (> 35in)
Describe waist-hip ratio in relation to obesity.
disease risk increase when WHR is > 0.95 in men and > 0.8 in women
Describe BMI in relation to obesity.
high risk > 30
BMI = weight in kg/(height in m squared)
Interpret BMI levels.

BMI does not take into account body fat distribution or muscle mass
Do we directly track BMI for children and teens?
not really
use a BMI-for-age tracking chart in order to ensure that they track with rate of growth and development
Describe the different weight classifications in terms of percentiles for BMI-for-age.

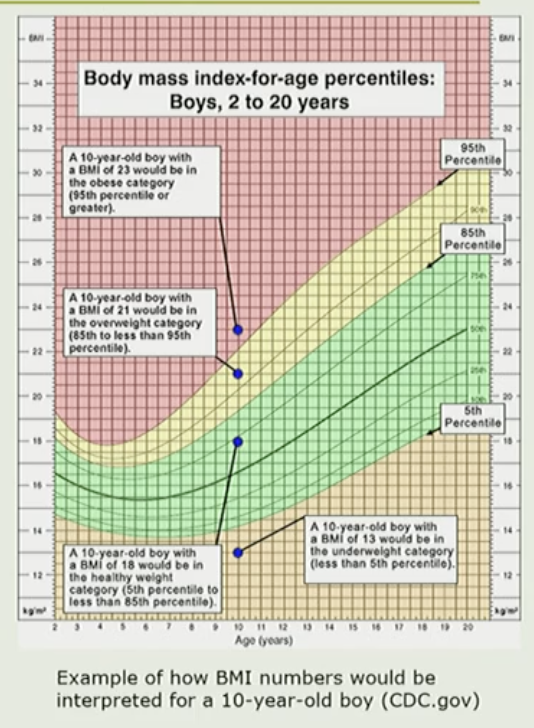
What type of fat is a predictor of risk for obesity-related diseases?
abdominal fat, especially visceral fat in that region
terms “apple” shaped
central or upper body distribution
android distribution
central/visceral adiposity is strongly and consistently related to metabolic risk of chronic disease
What type of fat stores is less of a risk for obesity-related diseases?
lower body or gluteofemoral distribution
gynoid distribution
“pear” shape
What has a higher metabolic risks, visceral adiposity or lack of moderate to vigorous physical activity?
visceral adiposity has more
technically both impact metabolic risk
What proportion of obese youth have the “adult” co-morbidities of obesity?
1/3