SA cancer therapies 2 - medical therapies
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/33

There's no tags or description
Looks like no tags are added yet.
34 Terms
What is chemoherapy?
Genotoxic (DNA damaging) tx of dx using chemical substances —> esp tx of cancer by cytotoxic & other drugs
What are the different ways chemotherapy can be used?
Primary chemotherapy —> common with lymphoma (sole anti-cancer tx)
Adjuvant Chemotherapy —> after surgery to remove any mets
Neoadjuvant chemotherapy —> given before surgery to shrink tumour & incr chance of successful resection (mast cell tumour)
How does chemotherapy work?
Active against rapidly proliferating tissues
does not specifically target cancer cells —> cannot differentiate between cancer cell & normal cell
those not actively dividing are relatively resistant to chemo
At what time point is chemotherapy most likely to be effective?
Before a mass can be identified —> the more cells the more likely there is going to be a resistant one
What are the factors that affect chemotherapy success?
Tumour cell heterogeneity (evolution of resistance) —> linked to tumour size
Inherent tumour sensitivity
Origin tissue
Growth fraction
Drug dosage
Tumour blood supply / oxygenation
Interval between txs
Other drugs (steroids when treating a lymphoma)
How do you minimise drug resistance?
Treat as early as poss
Follow properly evaluated protocols
Use correct doses
Avoid pre-tx w/ drugs that induce resistance
@ relapse, act ASAP
What considerations need to be made about drug pharmacology?
Administration —> dose & ability of oral drugs to get in blood stream
Distribution —> size of molecule & blood barriers
Metabolism —> drug activation / deactivation e.g. glutathionine
Excretion —> clearance —> abnomral GFR correlates w/ adverse effects of some drugs
(issues with animals with hepatic and renal problems)
How do you dose obese patients?
Estimating lean weight
Other than obesity, what other types of patients pose dosing problems?
Collies & others w/ known drug sens
Animals w/ hepatic functional compromise
Animals w/ reduced renal function
What needs to be considered when choosing a chemotherapy agent?
Indication?
Evidence of benefit?
Often palliative (longer or shorter term)
Signalment, ADME, co-morbidities
When is single agent chemotherapy used?
Sensitive tumours —> Transmissible venereal tumour (TVT)
Tends to select rapidly for drug resistance
selection pressure high → rapid dominance of progeny of resistant cells
How does the risk of toxicity differ between sequential and combined polychemotherapy?
combined (several drugs given @ diff times) > sequential (several drugs given same time)

What routes of administration are used for chemotherapy?
Oral
IV
Bolus (rapidly)
Infusion (slowly)
IM/SC
Intracavitary
try to avoid topical & intratumoural agents —> incr risk of environmental & personnel exposure
(always wear appropriate PPE when doing this and consider environmental risk)
How is dosing worked out for patients?
Start at the maximum tolerated dose (will be the dose listed in protocol) —> reduce if there are adverse effects
Dosing based on body surface area —> correlates w/ liver/kidney blood supply (metabolic capacity) better than weight
For smaller patients (<10kg) some drugs are administered on mg/kg
carboplatin, doxorubicin, epirubicin
double check & record all doses & calculations
What is the interval between txs for?
Allow recovery of normal tissues
Rapidly dividing tissues e.g. bone marrow & GI tract tend to repair more rapidly than most tumours (treatments too close together leads to toxicity of normal tissue)
What needs to make up Pre-chemotherapy assessment?
Discuss tolerance of any previous tx
Assess patient
Assess tumour status
Biochem
Haematology prior to each tx —> neutros & platelets
neutropenic → acute bacterial infection from gram -ve bacteria in gut
Urinalysis start of tx , prior to cyclophosphamide
What are the different responses you can have to the therapy?
Complete remission CR - all lesions gone, no new lesions
Partial remission PR - ≥ 30% reduction in size, no new lesions
Stable disease SD - between PR and PD
Progressive disease PD - ≥20% increase or new lesions
(can only monitor this for primary and neoadjuvant chemo)
for adjuvant tx —> individual response assessment not poss

How common are side effects from chemotherapy?
30 – 50 % of patients have some side effects during tx course
Most side effects —> transient & self resolving
<10 % have side effects → hospitalisation
1 – 2 % chance of death (usually sepsis)
What immediate toxicities (<24hrs) can you get?
What tx would you use for these?
Anaphylaxis/hypersensitivity —> dexamethasone IV, IVFT, H1 blocker, adrenaline
Cardiac arrhythmia
Emesis —> Metaclopromide or ondansetron
What is acute tumour lysis syndrome?
Rapid destruction of cancer cells in patients w/ large tumour burdens
First 24-48hrs
Electrolyte abnormalities
Hyperkalaemia
Hyperphosphatemia
Hypocalcemia
AKI
How would you deal with a patient with high tumour burdens?
Careful monitoring of at risk patient —> keep in the hospital for 24-48 hours
Early IVFT if you see signs
Management of AKI
What longer term side effects can you see?
Bone marrow low WBC count(7-10 days)
Alopecia —> uncommon, specific breeds
Gastrointestinal —> does not usually last longer than the first 4 days
(Rapidly dividing cells most affected)
What signs will you see w/ GI tox?
1-5d post tx
Anorexia, nausea, V+, D+
Disrupted mucosal barrier w/ neutropenia incr risk of sepsis (bacterial translocation)
How can you manage GI toxicity initially?
Maropitant —> dispense for home use to prevent vomiting
Pre-tx fasting reduces D+
Consider dispensing smectite in case of D+ (VBS clay)
(probiotics ineffective)
What do you do if signs of GI toxicity last longer than 24 – 48 hours?
(patient unwell/off food & owner concerned?)
Supportive tx 48-72hrs:
IVFT
Anti-emetics —> metoclopramide (for nausea), ondansetron
D+ → maropitant, smectite
Be aware of incr risk of sepsis if patients become neutropenic
Describe pyrexic neutropenic patients 7-10d post chemotherapy and how to treat them
Medical emergency —> may be septic
Translocation of bacteria from patient’s own GI flora
Hospitalisation until systemically well
Stop all cytotoxic drugs —> dose reduction next time
Barrier nurse & aseptic techniques
Supportive therapy —> bactericidal ABs
How does your approach differ depending on the amount of neutrophils?
Neutrophil count <1x10⁹/L
ABs (amox/clav 20mg/kg bid 7d or TMPS)
Drug discontinuation (if on tablets)
Check temp
Subsequent dose reduction
Neutrophil count 1-1.5x10⁹/L
If next dose due will need to be delayed
No ABs unless good reason
Neutrophil count 1.5-2.5x10⁹/L
Dose may require postponement / modification depending on schedule.
What are some drug ass. complications?
Cumulative cardiotox (DCM) —> doxorubicin
Sterile haemorrhagic cystitis —> cyclophosphamide
prevention —> furosemide, incr drinking, freq outdoor access (incr urine output to reduce contact w/ bladder)
Hepatotox —> lomustine (dogs)
Nephrotoxicity —> cisplatin, doxorubicin (cats), lomustine (dogs)
Fatal non-cadiogenic pulmonary oedema (cisplatin)
Fatal CNS signs
What can reduce the risk of hepatotoxicity?
SAM-E
What is being shown here?
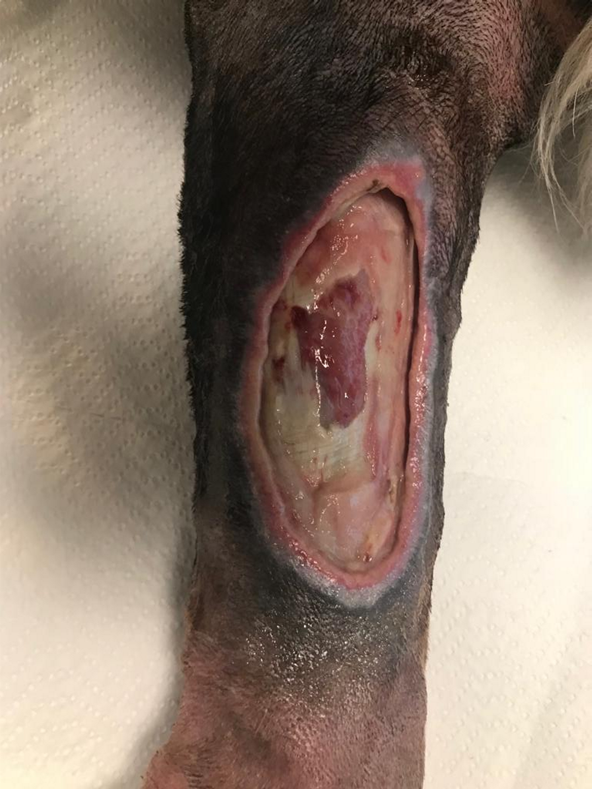
Extravasation
ALWAYS use a cleanly placed first stick catheter, never leave unsupervised & flush before removal
Monitor for any swelling, discomfort, changes in resistance to injection or rate of infusion
Do not use syringe driver / pump
Flush catheters appropriately before cath removal
What are the txs for extravasations?
Doxorubicin / epirubicin / actinomycin D —> apply cold packs
consider (immediate) surgical debridement
vincristine / vinblastine —> apply warm compresses
What are the features of metronomic chemotherapy?
Daily low dose chemotherapy
Direct action on tumour cells & stim immune response → angiogenesis
Prevent local recurrence soft tissue sarcoma
Slow metastatic dx haemangiosarcoma
Usually low dose cyclophoshamide w/ piroxicam (or other NSAIDs)
monitoring via haematology & urine dipstick
What is MOA of Receptor Tyrosine Kinase?
Inhibit the activation of specific signalling pathways involved in specific types of cancer
Two oral drugs targeting the RTK KIT (toceranib and masitinib) licensed for tx of mast cell tumours in dogs
licenced for incomplete excision & generally used for metastatic dx
What side effects can be seen with receptor tyrosine kinase inhibitors?
D+ & anorexia
35 – 45 %, but only severe in 10%
Many owners report soft stools
Usually managed by tx pauses
Bone marrow suppression
Around 10 % not typically severe