Emergency Seizure Management
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/47

There's no tags or description
Looks like no tags are added yet.
48 Terms
Types of seizure considered an emergency
- cluster epileptic seizures
more than 2 seizures in 24hr with complete recovery inbetween
may be regular type for the patient
- status epilepticus
sustained seizure activity >5 mins,
or cluster seizures w/o complete recovery inbetween
what does seizure activity in close succession create
- vasogenic and cytotoxic oedema - promotes more epileptic activity
- mortality rate 25.3-38.5% - irreversible brain damage - oxygen deprivation, systemic complications
How could you medicate an emergency seizure patient in hospital ? different ways
- oral bolus/ loading
- rectal bolus
- intranasal bolus
- IV bolus
- IV loading
- CRI
How could you medicate an emergency seizure patient at home? different ways
- oral bolus/ loading
- rectal bolus
- intranasal bolus
short acting medications in emergencies for seizures
- benzodiazepines
- ketamine
- medetomidine
- propofol
long acting medications in emergencies for seizures
- levetiracetam
- phenobarbitone
mechanism of action of benzodiazepines
Binds to GABA-A receptor:
increases Cl- influx into post-synaptic neuron
causes hyperpolarization -> decreases neuronal excitability

bzd examples
Midazolam, diazepam, Lorazepam
pharmacokinetics of benzodiazepines
Routes of administration: IV, IM, Intranasal, rectal (slow)
Time to effect: 1-5 minutes depending on route (IV <3 mins, rectal has poor efficacy).
Duration: 20-30 minutes
Metabolism: Hepatic
In hospital and at home administration available
dosing of benzodiazepines
for your info

mechanism of action of ketamine
Ketamine is a non-competitive NMDA receptor antagonist
Blocks the NMDA receptor
Decreased influx of Na+ and Ca2+ via ion channel into post synaptic neurone
- No depolarization
- No neuronal excitation

pharmacokinetics of ketamine
Routes of administration: IV
Time to effect:
dosing of ketamine
for your info

pharmacokinetics of (dex)medetomidine
Routes of administration: IV, IM
Time to effect: 1-2 minutes (IV)
Duration: 1-2 hours (peak effect 5-15 minutes)
Metabolism: Hepatic
In hospital administration only
sedation for patient, not anti-epileptic (for post ictal signs)
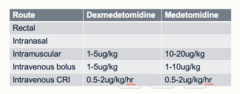
dosing of (dex)medetomidine
for your info
mechanism of action of propofol
Binds to GABA-A receptor: different site to benzos
increases Cl- influx into post-synaptic neuron - increasing duration of channel opening
causes hyperpolarization ->decreases neuronal excitability

pharmacokinetics of propofol
Routes of administration: IV
Time to effect:
dosing of propofol
for your info
to effect

mechanism of action of Levetiracetam
Binds to synaptic vesicle protein 2A in the pre-synaptic neuron:
This modulates release of excitatory neurotransmitters (glutamate) into the synaptic cleft
decreased glutamate release -> decreases neuronal excitability

pharmacokinetics of Levetiracetam
Routes of administration: IV (hospital), oral, rectal, (IM)
Time to effect: <5 minutes (IV), 1-2 hours (oral)
Duration: 4-6 hours
Metabolism: renal excretion without major metabolism
Can be given in hospital or at home
dosing of Levetiracetam
for your info

mechanism of action of phenobarbitone
Phenobarbitone is a GABAa receptor agonist. They prolong the duration of GABAa chloride channel opening.
Binds to GABAa receptors on Cl- channels
Influx of Cl- into post-synaptic membrane
Hyperpolarisation
Harder for the threshold of that neuron to be reached
Action potentials are not propagated

pharmacokinetics of phenobarbitone
Routes of administration: IV, oral
Time to effect: 5-20 minutes (IV), 4-8 hours (oral)
Duration: 12 hours
Metabolism: hepatic metabolism
In hospital administration only (IV)
can load→ lot in short succession so dont need to wait for 3wks for it to build up
dosing phenobarbitone
for your info
emergency = IV
Loading 20mg/Kg/day - 2-3mg/kg bolus

initial management of emergency seizure
1. IV Access
2. Administer benzodiazepine bolus
3. Haematology, biochemistry and electrolytes
4. Administer a longer acting AED
5. IVFT
6. Consider whether this patient needs a CRI starting
7. Consider if this patient needs to be loaded with a longer acting AED

mneumonic to remember management of emergency seizure
I Bet Bigfoot Makes Fantastic Ice Lollies
IV, Benzos, Bloods, Medications, Fluids, Infusions, Loading
why is IV access needed in seizure patients ?
- first - admin bolus of benzodiazepines IM, helps you place IV
- vital for cluster and status - require IV meds and fluids
- take blood IV
continue care
which Benzodiazepine is your choice for Bolus ?
what do you do once you have given it?
midazolam = more potent for emergency
- start a stopwatch
- gives you 20 minutes to execute rest of plan
- successful response - seizure cessation
Blood decisions for seizuring patients
- naive seizure patient - systemic screen for reactive causes of seizures
- access the safety of AED (liver for pheno)
- If patient is long term AED - take serum sample before IV admin occurs
what on bloods would alter your decisions on medications ?
liver parameters - phenobarbitone
take serum before bolus - so not altered
How do you decide which long acting medication to give: levetiracetum
Levetiracetam: First choice - safety
- Initially 60mg/kg bolus followed by 20mg/kg TID
- Can go up to QID
- Shown to be safe up to 70mg/kg QID dosing
How do you decide which long acting medication to give: phenobarbitone
Phenobarbitone:
- Initially 3mg/kg bolus
- If naïve 3mg/kg IV TID for first 24hrs then BID dosing.
- Loading do not exceed 20mg/kg/day, 2-3mg/kg boluses spread out by at least 20-minutes between.→ give enough time to set in
veteran patient: on pheno long term
- wait for serum level before adjusting,
- cautious use can be implemented.
- Start with the normal mg/kg IV dosing following the initial bolus at same time of day.
- avoid phenobarbitone toxicosis
Is fluid therapy indicated in seizuring patients? why
yes
- Help systemic perfusion
- Restores losses may have had during seizure
- Seizures cause huge metabolic demand
- Hypovolemia -> hypotension and decreased cerebral perfusion
- Decreased cerebral perfusion can lead to brain ischemia and neuronal injury
What options do you have for CRI?
- BZD
- ketamine
- (dex)medetomidine
- propofol
why use cri
contantly giving seiure meds
dont ened repetitive bouse
buying time for longer time drugs to kick in —————-
How do you load phenobarbitone and when?
- how well have they responded to previous treatments ?
- are they still having repetitive seizures ?
what are the risks of loading with pheno
- Neurological abnormalities
- comatosed
maximum 20mg/kg/day - hospitalise while side effects wear off
What is weaning in regards to seizure medication?
Ideally 12-24hrs on CRIs seizure free before start weaning medications
Then decrease CRIs incrementally from the last one added to the first one added
Decrease by 25-50% of the dose every 4-6hrs
Complications of seizures
Cushing's reflex (bradycardia, hypertension, worsening neurological status)
Aspirational pneumonia - gag impacted by seizure and medication
Lacerations to tongue
Intubation
Ventilation
Post-ictal signs vs permanent neurological dysfunction→ see back
Phlebitis
Hyperthermia
Death
At home management of emergency seizures
- midazolam - Intranasal (better response, tip on device vaporises)
- rectal diazepam (dose is fixed in applicator, have to give multiple, but is the only liscenced one)
-Levetiracetam

how use levetiracetam at home
- If naïve start pulse therapy so 60mg/kg bolus and then 20-30mg/kg TID until seizure free for 48hrs.
- If veteran 60mg/kg bolus and can increase to 60mg/kg QID for 48hrs until seizure free.

Happened before
What look like
Access to meds?
Giving whats been prescribed
How recovered, complete?

Probs post ictal -> resee in 7 d
Diagnostics: biochem and haem, eletrolytes, neuro exam

im midazolam
Get iv acess, bloods from catheter

Wait for bloods,
Look out for seizure activity: focal, twitich of face, generalised tonic clonic

Fast acting as bolus: more midazolam,
Follow up pehno -> act in 20 mins

On midazolam cri
Ket bolus to work quick-> monitoring: breathing, gag affected, sedated now
Thhink abt loading pheno at this point bc having seizure events despite all the meds

Wean of cri -> another 24hr in hospital at least
Send home with phenobarbitone
Test bloods in 3 weeks
And send rectal or nasal midazolam-> administer immediately when seiure starts -> bc can take 5 mins to work