DENT 267: LO4 LS3- Plan Perio Therapy for Mucogingival Deformities
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/22

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
23 Terms
plan perio therapy for mucogingival deformities
-depends on the etiology/severity of attachment loss
-non-traumatic biofilm control
-debridement
-elevate tissues
-perio surgery may or may not be required
what is the goal of perio therapy for mucogingival deformities?
-restore progressive loss of tissue and restore gingival heights to cover exposed root surfaces if possible
when should we refer to a dentist/periodontist for a surgery consult?
-MGI type 1 or 2
-if surgery is indicated (mod to sev periodontitis)
-recession is progressing
-localized areas of advanced recession
-significant root exposure
-potential abutment teeth or teeth receiving intracrevicular restos w/ mucogingival concerns
-frenal concerns
-esthetic concerns
-pre-ortho tx
what are the types of surgery to treat defects?
-grafting
-frenal surgery
-flap surgery
care plan for mucogingival deformities
-ortho movement
-replacement of overhanging or over-contoured restorations
-replacement of impinging prostheses
-occlusal adjustment
-elimination of deleterious habits
client education for mucogingival deformities
-biofilm control and elimination of traumatic toothbrushing
-treat perio disease early
-prosthesis and ortho contraindicated if teeth have inadequate zones of attached gingiva and/or the presence of inflammation
-treat occlusal trauma early
aspects of recession that make it clinically significant
-attachment loss
-susceptible to caries, erosion, abrasion
-dentinal sensitivity
-hyperemia of the pulp
-interprox recession
-esthetics
mucogingival deformities & conditions around teeth: colour change
-abnormal colour
-gingival colour change can be associated w/ metallic pigmentation and systemic factors/diseases
what are some more mucogingival deformities
-melanoplakia
-Smoker's melanosis
-drug induced pigmentation (antimalarial, minocycline)
-amalgam tattoo
metallic pigmentation
-the ingestion/inhalation of metals such as mercury, lead and bismuth in medicinal compounds and through industrial contact can result in oral manifestations
-may also be systemic signs of intoxication if doses are high
-rare condition, more common previously when health conditions treated with heavy metals
metallic pigmentation: results from
-perivascular precipitation of metallic sulfides in the sub epithelial CT
where does metallic pigmentation occur on gingiva
-in areas of inflammation where there is an increase in vascular permeability
how can metallic pigmentation be eliminated?
-by decreasing inflammation
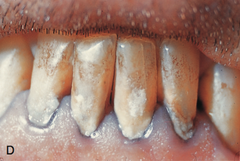
metallic pigmentation: lead
-lead exposure may cause a red or blue linear pigmentation of the gingival margin (Burtonian line)
-lead paint, lead solder in plumbing, contaminated water, soil, handling lead batteries
lead exposure
-coated tongue, spotty macules on mucosa, hypersalivation
-most prominent sign is gray-black lead line along marginal gingiva
-reversible if exposure to lead is eliminated
silver exposure (argyria)
-causes a violet marginal line which may accompany a diffuse bluish-grey discoloration
-silver has anti-bacterial properties and has been used in the past to treat STIs, the common cold, and epilepsy
-rare and most often results from prolonged exposure to silver containing ocular, oral or nasal meds
-nasal inhalation of solution containing silver salts have a propensity deposit on the palatal mucosa
treatment for silver exposure
-withdraw medication containing silver
metallic pigmentation: bismuth
-diarrhea meds which if used for the long-term, results in deposition of the metal in the gingiva
-metallic taste and burning mucosa are common symptoms
-bismuth line is blue-black
metallic pigmentation: mercury
-mercury poisoning can be acquired by absorption, inhalation, or ingestion
-mercury was tx for syphilis in early 20th century
-occupational exposure possible
-mercury poisoning may also cause other symptoms: headaches, burning mouth, abdominal pain, anorexia, abnormal discolourations on the gingiva
care planning for metal pigmentation
-eliminate pigmentation by removing local factors, biofilm, etc. and restoring tissue health, decreasing inflammation, decrease exposure
gingival colour changes associated w/ systemic factors
-melanin pigmentation
-Addison's Disease, Peutz-Jegher's Syndrome, Albright's Syndrome and Von Recklinghausen's Disease may produce areas of oral pigmentation
-certain drugs such as oral contraceptives, antipsychotic agents, anti-malarial agents can cause mucocutaneous pigmentation
-Nevi (mole) melanoma
Addison's Disease
-gingiva may look spotted brown
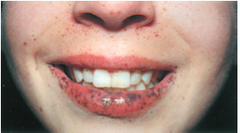
Peutz-Jegher's Syndrome
-melanotic macules may appear near mouth, lips, genitalia, palms and soles