CF - Rever
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/73

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
74 Terms
What is Cystic Fibrosis? (CF) What are some misconceptions?
mutation of the CFTR gene, which is an autosomal recessive gene inherited by both parents. It is a progressive disease that fx the exocrine gland. Onset is varied.
misconceptions: contagious, always diagnosed at birth, only a pediatric disease
What are the 5 different types of CF? (I-V)
no CFTR gene
misfolding → does not reach cell surface
channel doesn’t open properly
function is faulty
not enough quantity
What is the general clinical presentation of CF?
thick and sticky mucus
most common in Europeans > hispanics, blacks
salty tasting skin
persistent cough w phlegm
frequent lung function
wheeze/SOB
poor growth/wt gain
greasy/bulky stools
nasal polyps + infections
fingers/toes clubbing
Describe the absorption of CF
Increased GI acidity due to low duodenal pH and ovorectal transit time
bile acid dysfunction
describe the distribution of CF?
hypoalbuminemia decreases protein binding
less adipose tissue and lower body mass
describe the metabolism and execretion of CF
M: increased CYP2C8 and CYP1A2 clearance
E: increased renal clearance
Newborn Screening (NBS) is a mandatory test done within the first few days after birth. What does it check for?
heel prick blood draw and placed on Guthrie car to check immunoreactive trypsinogen (IRT)
high IRT = CF or bc baby is preterm
When is the sweat test indicated? What indicates CF?
positive NBS; measure chloride in sweat by using pilocarpine + elecrical stimulation
≤ 29mmol/L = unlikely
30-59 = need more testing
≥ 60mmol/L = CF
patient presents with cough w/wo sputum/phlegm, wheezing, repeat infections, SOB, and has difficulty exercising. In their lower respiratory tract they have an infection, inflammation, and damage. And in upper respiratory tract they may have sinusitis and nasal polyps. What tests can you do to diagnose the patient?
chest xray, PFTs, sputum culture, blood work
What are complications in the respiratory system for a CF patient?
bronchiectasis, pneumothorax, hemptysis, allergic bronchopium aspergillus (ABPA), infection (pseudomonas aeruginosa), pulmonary execerbations, lung transplant
If a patient with CF has a lung infection, which pathogens should you cover in ABX?
pseudomonas aeruginosa
If patient has a pulmonary exacerbations, what should you give the patient?
continue chronic therapies and ACT
When is a patient indicated for a lung transplant?
Advanced lung disease, early referral INC survival
What is the MOA for CF on the respiratory system?
thick mucus prevents cilia from cleaning dust/bacteria from lungs and blocks the airways
What is the MOA of CF in the GI system?
weak esophageal sphincter
slow motility in stomach, intestine, colon
thick secretions prevent nutrient absorption
CF pt presents with N/V/C, bloating/gas, ab pain, distention, heart burn, acid reflux, and bacterial overgrowth. What are the the potential complications if this isn’t treated?
poor nutrition
GERD
meconium ileus
distal intestinal obstruction syndrome (DIOS)
rectal prolapse
fibrosing colonopathy
intussusception
appendicitis
small intestine bacterial overgrwoth (SIBO)
c.diff colitis
colorectal cancer
What is the MOA of CF on the pancreatic system?
thick mucus blocks pancreatic ducts which prevents enzymes from secreting to breakdown foods. Leading to pancreas scarring.
pt presents with ab distention, frequent bulky, foul/smelling oily stools, and stools that float to stick to the bowl. What test should you give them and what does this indicate?
fecal elastase <200mcg = pancreatic insufficiency
may be pancreatic insufficiency or pancreatitis (if sufficient)
what are the complications of pancreatic insufficiency/pancreatitis in an untreated CF pt?
poor growth
malnutrition
fat soluble vitamin def (ADEK)
bone disease
CF related diabetes (B cell dysfunction)
If patient has CF-related diabetes (CFRD), what is used for screening and what is the treatment?
OGTT (not HbA1c); insulin
What is the MOA of CF on the hepatobiliary system?
CFTR is on the apical membrane of biliary epithelium instead of the hepatocyte which creates a thick bile. This leads to biliary obstruction, inflammation, and biliary fibrosis
pt presents with INC AST, ALT, ALP, GGT, bilirubin; DEC platelets and albumin. Has liver stiffness, an abnormal ultrasound/MRI, fibrosis, steatosis, cholestasis. What might the patient have?
CF hepatobiliary involvement (CFHBI) or advanced CF liver disease (ACFLD) like cirrhosis, non-cirrotic portal HTN
What are some complications of a CF patient with a compromised hepatobiliary system?
portal HTN
variceal bleeding,
hepato pulmonary syndrome
porto pulmonary HTN
cirrhosis
HF
What tests should you use to screen for CFHBI? What is the treatment?
Liver function tests and abdominal US
treatment: CFTR modulators (?), liver transplant
DONT GIVE URSODIAL
What is the MOA for CF on the reproductive system (m/f)
male: congenital bilateral absence of vas deferens (CBAVD) → sperm can’t reach semen
female: thick cervical mucus → sperm cant penetrate
pt has infertility, delayed puberty, irregular ovulation due to CF. What is the treatment?
IVF and CFTR modulator to increase pregnancy
What is the MOA for CF on the skeletal system?
DEC osteoblast, INC osteoclast activity
pt presents with low bone mineral density (BMD), frequent fractures, and kyphosis. What are some contributing factors to this?
malabsorption, DEC bone mass, low BMI
physically inactive
sex steroid deficiency, delayed puberty
corticosteroids
INC inflammatory cytokines
chronic infections
pancreatic insufficiency, diabetes
pt presents with low bone mineral density (BMD), frequent fractures, and kyphosis. What should you test them to diagnose?
DEXA scan; T/Z = 2.0
What impact does CF have on the skeletal system on adults vs children?
adults: femoral neck, total hip, lumbar spine, forearm
children: body less head, lumbar spine, femur, forearm
If patient has low BMD and frequent fractures they are likely to have CF related bone disease (CFBD). What is the screening technique and what is the method of treatment?
DEXA
bisphosphonates
What is a nonpharmacological treatment for CF?
Airway Clearance Therapy (ACT) and physical activity (atleast 150min/wk, indiv therapy, fluids + electrolytes)
What are the different types of ACT?
coughing, huffing
chest physical therapy
high frequency chest wall oscillation
autogenic drainage
positive expiratory pressure
active cycle breathing technique
What are the different mechanisms of CFTR modulators?
correctors: make mature CFTR protein and move to cell surface
potentiators: open channel to increase Cl- and bicarb mvt across cell
triply therapy combo: do both
Which medication is indicated for CF in children ≥ 6years old and taking 2 tablets in the morning
alyftrek (vanzacaftor/tezacaftor/deutrivacaftor)
Which medication is indicated for CF in children ≥ 2 years old and taking 2 tablets in the morning and 1 tablet in the evening?
trikafta (elexacaftor/tezacaftor/ivacaftor)
Which two CFTR modulators are highly effective modulator therapies? (HEMT)
Alyftrek and Trikafta
Which medication is indicated for CF in children ≥ 6 years old and taking 1 tablet in the morning and 1 tablet in the evening?
Symdeko (tezacaftor/ivacaftor)
Which medication is indicated for CF in children ≥ 1 year old and taking 2 tablets Q12H?
orkambi (lumacaftor/ivacaftor)
Which medication is indicated for CF in children ≥ 1 month old and taking 1 tablet Q12H
Kayldeco (ivacaftor)
What are the ADE of CFTR modulators?
neuropsychiatric effects
GI upset
cough/upper respiratory symptoms
BP increase
What should you take CFTR modulators with?
take with fat-containing food to improve absorption (INC AUC 2-4) DO NOT EAT GRAPEFRUIT/GF JUICE
What is the BBW for CFTR modulators?
drug induced liver injury and liver failure
What is the LFT monitoring schedule?
monitor at baseline
every month x 6 mo
every 3 months x 12 months
annually
What decreases HEMT exposure? Should you continue to use them?
CYP3A4 inducers: rifampin, carbamazepine, phenytoin
avoid use
What increases HEMT exposure? Should you continue to use them?
CYP3A4 inhibitors: ketoconazole, clarithromycin
reduce HEMT dose
What substrates have increases exposure with both Alfytrek and Trikafta? This will require more frequent monitoring.
CYP2C9 substrates: warfarin, glipizide, glimepiride
P-gp substrates: digoxin, tacrolimus, cyclosporine
What substrates have increases exposure with alfytrek only?
BCRP substrates: rosuvastatin, sulfasalazine
What substrates have increases exposure with trikafta only?
OATP substrates: statins, glyburide, nateglinide, repaglinide
HEMT and warfarin interactions requires what?
more INR monitoring
What is the MOA of Pancreative Enzyme Replacement Therapy? (PERT)
combo of protease, amylase, lipase to digest fats, proteins, carbs, vitamins, and nutrients. It is to improve pancreatic insufficiency sympoms, fecal fat absorpiton, and maintain healthy weight.
PERT formulations are NOT interchangeable and they are enteric coated to prevent stomach degradation. How would you counsel a patient on PERT?
take before meals and snack with fat, protein, and/or complex carbs.
do not crush/chew
side effects of constipation and perianal ulcers
keep in cool/dry place
open capsule and put in applesauce
controversial may give PPI or H2RA
What is the dosing for PERT?
oInitial = 500 lipase units/kg/meal
oMaintenance = 500-2500 lipase units/kg/meal
oMax dose per meal = 2500 lipase units/kg
oMax dose per day = 10,000 lipase units/kg
Larger doses (> 6,000 lipase units/kg) associated with fibrosing colonopathy or colonic strictures
Bronchodilators relaxes and opens airways. You would usually give a CF pt a MDI w spacer or nebulizer soln:
albuterol (proair, ventolin), levalbuterol (xopenex)
How would you counsel a patient on this medication?
ADE: tremor, N/V, tachcardia
use 15-30 min before ACT, mucolytics, ABX, and perhaps exercise
Which bronchidilators will you give a CF patient?
MDI w spacer or nebulizer soln: albuterol (proair, ventolin), levalbuterol (xopenex)
mucolytics can thin mucus in the lungs to clear out with coughing. When are they used?
After using a bronchodilator and before ACT
indicated for children > 6 years old
What are the formulations of mucolytics?
hypertonic saline (3% or 7%) 4ml nebulized BID
Dornase Alfa (Pulmozyme) 2.5mg nebulized BID
Mannitol (Bronchitol) DPI BID
What are the ADE of mucolytics?
hypertonic saline: cough/sore throat, chest tightness
dornase alfa: change in voice dizziness
To suppress bacteria in mucus and prevent chronic lung infection what medication should you give?
inhaled ABX after bronchodilator+muclytic+ACT
aerol neb (DPI/MDI) 28 days on and 28 days off
A pt has a mild pulmonary exacerbation. What should you give them?
oral ABX
if its mod-severe or oral doesn’t work then give IV ABX.
What is reserved for chronic pseudomonal infection/frequent exacerbations and can be given to suppress inflammation in the bronchial tubes?
azithromycin 250mg QD or 500mg 3x weekly
REVIEW ABX COVERAGE

a pt is on IV tobramycin. How should you monitor this patient?
high dose extended interval (QD, preferred)
peak 20-35mcg/ml
trough <1mcg/ml
patient has impaired absorption of fat soluble vitamins (ADEK). What medications are indicated and what should you monitor for?
AquaADEKs, DEKAs, MVW complete formulation
maintain 25-hydroxyvita D lvls ≥30ng/mL (take cholecalciferol D3 > ergocalc D2)
pt has iron deficiency. What should you give them?
ferrous sulfae, ferrous gluconate, ferrous fumarate
take every other day wiht vitamin C to increase absorption
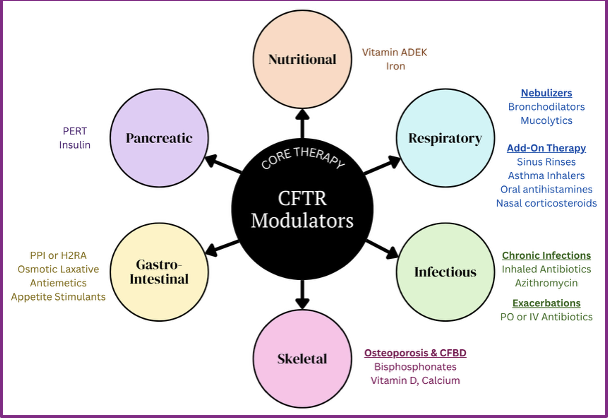
What are additional medications to take for CF?
asthma inhalers
nasal rinse
oral antihistamine
steroid nasal sprays
osmotic laxatives
antiemetics
appetite stimulant
What is the order of inhaled therapy?
bronchodilator: open airway
hypertonic saline: pull water into thin mucus
dornase alfa: breaks DNA to further thin mucus
ACT: physically shakes and clears mucus from lungs
ABX: cleans airways wo mucus blocking
corticosteroids: reduce inflammation
REVIEW CF TREATMENT OVERVIEW

pulmonary function tests (PFTs) are done with spirometry where it is performed 3x and record best results. This is done in pts > 5-6 years old. What indicates infection and how should you counsel the patient?
reductions in FEV1 indicate infection/obstruction
counsel:
avoid smoking 1hr, heavy exercise 30 min, large meal 2hr before
monitor at each clinic visit to compare to pt baseline
What are common complications of pregnancy in CF pts?
premature delivery
more frequent pulmonary exacerbations
gestational diabetes
constipation
vitamin A toxicity
HTN
REVIEW LABS AND IMAGING

What screenings should you do?
routine clinic visit: Q3M, Q4-6M if ≥6yrs and stable
BP: annual
mental health: annual @12yrs old
colonoscopy: every 5 years @40 yrs old
immunizations: influenza, RSV, pneumococcal, COVID19
What is the role of the pharmacist?
counsel + educate
med rec
ID DDIs
mitigate access barriers
cost effective strats
liaison
med management services
prevent and screen
write/med prescription
order/review labs
manage home IV ABX
non-CF therapy
Summary
