(20) Adrenergic beta selective agonist
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/25

There's no tags or description
Looks like no tags are added yet.
26 Terms
Give me all Adrenergic Agonist
Catecholamine
Archetype Adrenergic Agonists -
Norepinephrine (NE)
Epinephrine (EPI)
Isoproterenol (ISO)
Other Catecholamines
Dopamine
Dobutamine
β2 Adrenergic Agonists
SABA - Short-Acting
LABA - Long Acting Agonists
ULABA - Ultra-long-acting
α-Adrenergic and Mixed-Acting Agonists (NEED TO REVIEW)
Phenylephrine
Ephedrine / Pseudoephedrine
Midodrine (prodrug)
L-DOPA (discussed in prodrug section)
Arylimidazolines
Oxymetazoline
Xylometazoline
Three Archetype Adrenergic Agonists
Tell me about it
Drug | N-substituent | Receptor preference |
|---|---|---|
Norepinephrine (NE) | H (small) | α + β; α-like effects |
Epinephrine (EPI) | CH₃ (methyl) | α + β; slightly β-favored |
Isoproterenol (ISO) | Isopropyl (bulky) | β1 + β2; essentially no α |
Three Archetype Adrenergic Agonists
Have similar?
All three contain catechol (two adjacent phenolic OH groups).
Three Archetype Adrenergic Agonists
receptor preference
α → NE ≥ EPI >> ISO
β1 → ISO >> EPI ≥ NE
β2 → ISO >> EPI > NE
Three Archetype Adrenergic Agonists
Draw

skip brand names for now
Dopamine
Tell me about it
Receptor | Immediate effect → Outcome |
|---|---|
β1 | ↑ Contractility + ↑ HR → ↑ Cardiac output |
D1/D2 | Renal vasodilation → ↑ Urine formation |
α (high dose) | Vasoconstriction → ↑ BP |
use: Heart failure and shock.
Dopamine
Why professor favors dopamine over NE for shock?
Dopamine → Stimulates heart + Dilates renal vessels → ↑ Cardiac output without as much BP increase as expected.
Pharmacophore & SAR of adrenergic agonist drugs
Structure feature | Effect |
|---|---|
Small N-substituent | Activates α and β (NE/EPI) |
Bulky N-substituent | ↑ β selectivity (ISO) |
Catechol | COMT metabolism → Short action |
Non-catechol | Avoids COMT → Longer action |
Para-OH | ↑ β affinity |
Long hydrophobic N-chain | Membrane binding → Longer action |
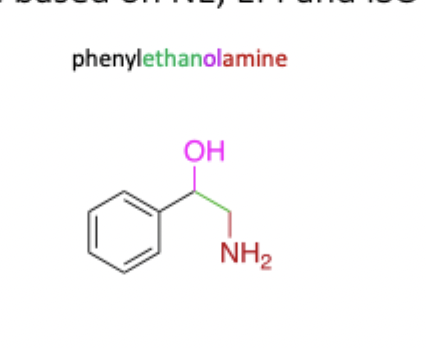
What is the structural framework of the adrenergic agonist called?
Phenylethanolamine pharmacophore
Phenylethanolamine pharmacophore
Explain and Draw
Protonated amine → Interaction with aspartate.
β-OH and catechol OH → Hydrogen bonding.
Aromatic ring → Hydrophobic interactions.
EPI vs. NE vs. ISO
BP Effects
NE: α + β; α-like effects
α1 → Vasoconstriction → ↑ Diastolic BP → Baroreflex → → ↑ Vagal/ACh activity → ↓ HR.
β1 → ↑ Contractility in isolated tissue.
EPI: α + β; slightly β-favored
β1 → ↑ HR/force → ↑ Systolic BP
β2 → Vasodilation → ↓ Diastolic BP
β1 + β2; essentially no α
β1 → ↑ HR/force → ↑ Systolic BP
β2 → Vasodilation → ↓ Diastolic BP.
EPI vs. NE vs. ISO
Overall effects
1. Peripheral Resistance
NE → ↑ (α1 vasoconstriction)
EPI → ↓ (β2 vasodilation)
ISO → ↓↓ (strong β2 vasodilation)
2. Overall BP / Mean Arterial Pressure (MAP)
NE → ↑
EPI → Approximately unchanged
ISO → No increase; may ↓
3. Clarify the BP changes
NE → ↑ Both systolic and diastolic BP
ISO → Slight ↑ systolic BP, large ↓ diastolic BP
Drug | Systolic (top) | Diastolic (bottom) |
|---|---|---|
NE | ↑ | ↑ |
ISO | Slight ↑ | ↓↓ |
Epinephrine
Effects: (SAME INFO, MAY SKIP)
α + β; slightly β-favored
High dose → α activation → Vasoconstriction.
METABOLISM: (SAME INFO, MAY SKIP)
Catechol → COMT/MAO metabolism
Rapid metabolism; poor oral bioavailability
Hydrophilic → Does not cross BBB.
Use
Anaphylaxis (drug of choice): b2
glaucoma: a2
with local anesthetics to prolong their action: a1
Not preferred for routine asthma because of short duration (due to rapid COMT metabolism)
Important risks/interactions:
Digoxin/digitoxin + EPI → Severe arrhythmia risk.
Cocaine → Excess adrenergic stimulation.
Hyperthyroidism → ↑ Adrenergic sensitivity.
Anxiety, tremor, headache; possible pulmonary edema or cerebral hemorrhage.
Norepinephrine
Use: Shock.
Interactions: NE + Atropine → Atropine blocks vagal effects → Tachycardia risk.
Isoproterenol
Sses: Heart failure; asthma/COPD.
Dobutamine
structure

Dobutamine
Effects
β1 selective at normal doses.
Positive inotropic → ↑ Contractility.
No chronotropic increase at normal doses (MAJOR ADVANTAGE)
Heart beats harder, not faster
High dose → α activation.
Used in heart failure/shock.
Risk: Atrial fibrillation → Rapid ventricular response.
β2 Adrenergic Agonists
β2 Adrenergic Agonists
Drug Classification
Class | Duration | Drugs |
|---|---|---|
SABA (Short-acting) | 4–8 hours | Terbutaline, Metaproterenol, Albuterol |
LABA (Long-acting) | 6–12 hours | Salmeterol, Formoterol |
ULABA (Ultra-long-acting) | 24 hours | Indacaterol, Olodaterol, Vilanterol |
ADMIN STUFF:
The professor did not mark these with
***:, so I will skip for now memorizing the structures
Dopamine
Terbutaline
Olodaterol
Vilanterol
Memory Trick
SABA- TAMANAH MET AISHWARYA
LABA - SALMAN FUCKBOY
ULABA - I Own Vans
β2 Adrenergic Agonists
General Rules — Apply to These Drugs
Rule | What it means |
|---|---|
β2 selective | Bronchodilation → Opens airways |
Bulky N-substituent | ↑ β selectivity |
Para-OH | ↑ β-receptor affinity |
Non-catechol | Avoids COMT metabolism |
Long hydrophobic N-chain | Membrane binding → Longer action |
SABA-specific facts:
Used for short asthma attacks.
Better oral bioavailability than epinephrine, but inhalation preferred.
Longer action than EPI because they avoid COMT and undergo slower MAO metabolism.
SABA (Short-acting)
Draw and tell me about structures of - Terbutaline, Metaproterenol, Albuterol

Drug | ✏ Structure to recognize | Why it matters |
|---|---|---|
Terbutaline | Resorcinol | Non-catechol → Avoids COMT |
Metaproterenol | Resorcinol | Non-catechol → Avoids COMT |
Albuterol | Salicyl alcohol | Non-catechol → Avoids COMT |
LABA(Long-acting)
Draw and tell me about the structures of Salmeterol and Formoterol


Salmeterol | Long hydrophobic N-chain | Membrane binding → Longer duration |
Formoterol | methoxy + formamide-related group | Extra receptor interactions → ↑ β2 affinity |
ULABA
Draw and tell me about the structures of Indacaterol, Olodaterol, and Vilanterol

Indacaterol | Quinoline ring + bulky hydrophobic N-group | Metabolic stability + longer duration |
Olodaterol | Benzoxazinone-containing structure | Recognize as ULABA |
Vilanterol | Structure shown on PPT slide 26 | Recognize as ULABA |
β2 Adrenergic Agonists
metabolism
Drug | 🔁 Metabolism process | Elimination |
|---|---|---|
Albuterol (SABA) | SULT1A sulfation | urine |
Salmeterol (LABA) | CYP3A4 hydroxylation → Glucuronidation | feces |
Formoterol (LABA) | O-dealkylation and/or glucuronidation | feces |
Indacaterol (ULABA) | CYP3A4 hydroxylation and/or glucuronidation | feces |
SKIP FOR NOW (idk if i need to know in this much detail)
β2 Adrenergic Agonists
metabolism - draw


