CYP2C19 Polymorphisms
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/30

There's no tags or description
Looks like no tags are added yet.
31 Terms
affected drugs of CYP2C19 Polymorphism
clopidogrel (antiplatelet)
PPIs
pantoprazole, omeprazole, lansoprazole, dexlansoprazole
Voriconazole (antifungal)
SSRIs
sertraline
citalopram, escitalopram
TCAs
amitrriptyline
imipramine, trimipramine, clomipramine
doxepin
how many alleles for CYP2C19
49 core alleles
CYP2C19 alleles
*1
*2, 3, 4, 5, 6, 7, 8
*17
* 1 = wild type
*2, 3, 4, 5, 6, 7, 8 = reduced function
*17 = increased expression/function
CYP2C19 phenotypes
Wild Type 1/1
Heterozygous *1 / (reduced func.)
Homozygous for reduced function
Heterozygous for reduced function
Heterozygous 1/17
Homozygous 17/17
Wild Type 1/1 = normal/extensive metabolizer
Heterozygous *1 / (reduced func.) = immediate metabolizer
Homozygous for reduced function = poor metabolizer
Heterozygous for reduced function = poor metabolizer
Heterozygous 1/17 = rapid metabolizer
Homozygous 17/17 = ultrarapid metabolizer
CYP2C19 phenotypes: common by ethnic group
africans / americans → normal or ultrarapid (*1, *17)
east / oceanian → *1, 2, 3
clopidogrel: a — requiring CYP2C19 metabolism for activation
prodrug
rapidly absorbed in liver → 85% inactive metabolite + 15% active
active metabolite of clopidogrel
block P2RY21 receptor (antiplatelet effect)
CYP2C19 metabolism: inactive prodrug → active clopidogrel
increased CYP2C19 function
decreased CYP2C19 function
increased function
increased active clopidogrel = increased side effects (bleeding)
decreased function
decreased activity → decreased efficacy (risk for stroke, MI, thrombosis)

A =
D =
A = ultrarapid metabolizer (more active drug)
D = poor metabolizer (less active drug)
do not use clopidogrel with — inhibiting CYP2C19
alternative?
Omeprazole or PPIs
alternative = Rabeprazole or H2RAs
BBW for metabolism of clopidogrel by CYP2C19
effectiveness dependent on CYP2C19 and poor metabolizer have higher CV rates
cardiovascular indications (ACS, PCI)
ultrarapid or rapid, normal
intermediate
poor
ultrarapid or rapid and normal (17/17, 1/17, 1/1)
increased platelet inhibition or normal
label rec dosage and admin
intermediate (1/2, 1/3, 2/17. 3/17) and poor (2/2, 2/3, 3/3)
reduced platelet inhibition
increased risk of ADE
use Prasugruel, Ticagrelor
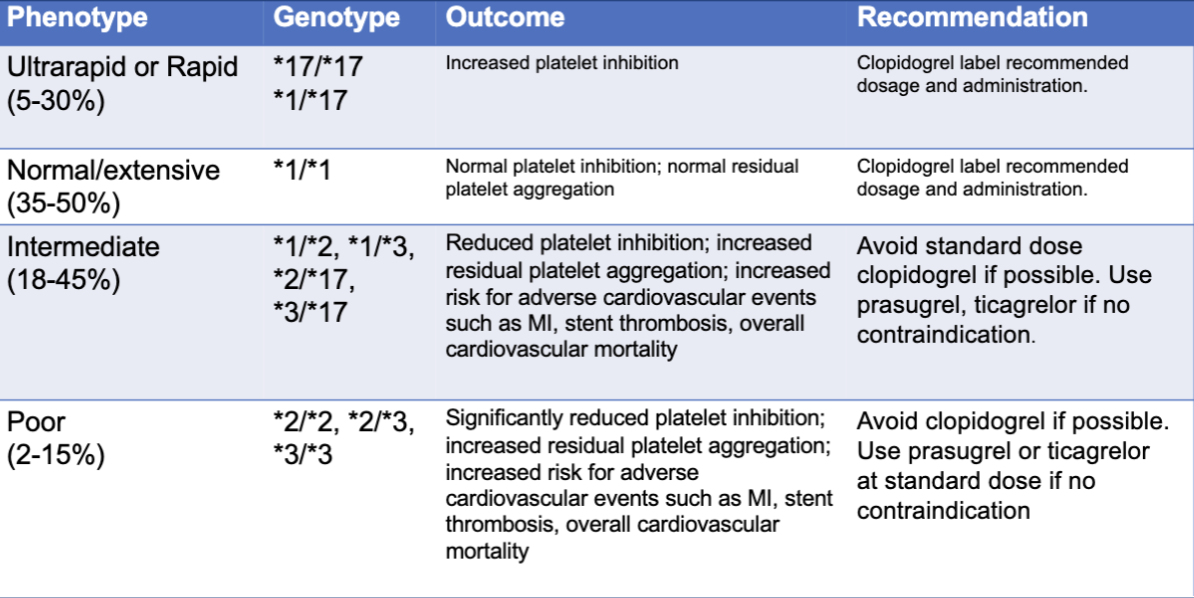
neurovascular indications (stroke, TIA)
ultrarapid or rapid, normal
intermediate
poor
ultrarapid or rapid and normal (17/17, 1/17, 1/1)
increased active metabolite formation or normal
no recommendation (UM) or label rec dosage and admin (NM)
intermediate (1/2, 1/3, 2/17. 3/17) and poor (2/2, 2/3, 3/3)
reduced clopidogrel active metabolite formation
increased risk of ADE
consider alternative P2Y12 inhibitor (Ticagrelor and Ticlopidine)

what medication is contraindicated in pts w/ hx of stroke or TIA?
Prasugruel
contraindications
Clopidogrel
Prasugruel
Ticagrelor
Clopidogrel
hypersensitivity
active bleeding
Prasugruel
hypersensitivity
active bleeding
prior TIA or stroke
Ticagrelor
hypersensitivity
active pathological bleeding
hx of intracranial hemorrhage
comparison of different P2Y12 inhibitors
Clopidogrel
Prasugruel
Ticagrelor
Clopidogrel
prodrug
2 step activation
inexpensive
Prasugruel
prodrug
1 step activation
inexpensive
Ticagrelor
not a prodrug
no activation required
expensive

phenoconversion
mismatch between genotype and predicted phenotype
2C19 and 2D6 show this the most
causes of CYP2C19 phenoconversion
Inhibitors (shift to poor metabolizer phenotype):
SSRIs: fluvoxamine, fluoxetine
Antifungals: voriconazole, ketoconazole, itraconazole
PPIs: omeprazole, esomeprazole, lansoprazole
Antiplatelets: ticlopidine
Inducers (shift to ultrarapid phenotype):
– Rifampin
— and — are prescribed along with clopidogrel to minimize risk of GI bleeding
PPIs and H2RAs
concurrent use of omeprazole or its S isoform (esomeprazole) can
lead to significant decrease in clopidogrel efficacy resulting in treatment failure (increased risk of CV events
H2RAs
famotidine, cimetidine
omeprazole is metabolized by — and it also inhibits —
CYP2C19
omeprazole competes w/ clopidogrel and reduces its
conversion to the active metabolite
Patients with reduced function alleles are at an even higher risk for therapeutic failure
SSRI metabolism: pts w/ reduced function alleles of CYP2C19 will have
higher concentrations of sertraline, citalopram, and escitalopram, thus a
higher risk of side effects
SSRI side effects
insomnia
HA
GI and sexual dysfunction
arrythmias
QT prolongation
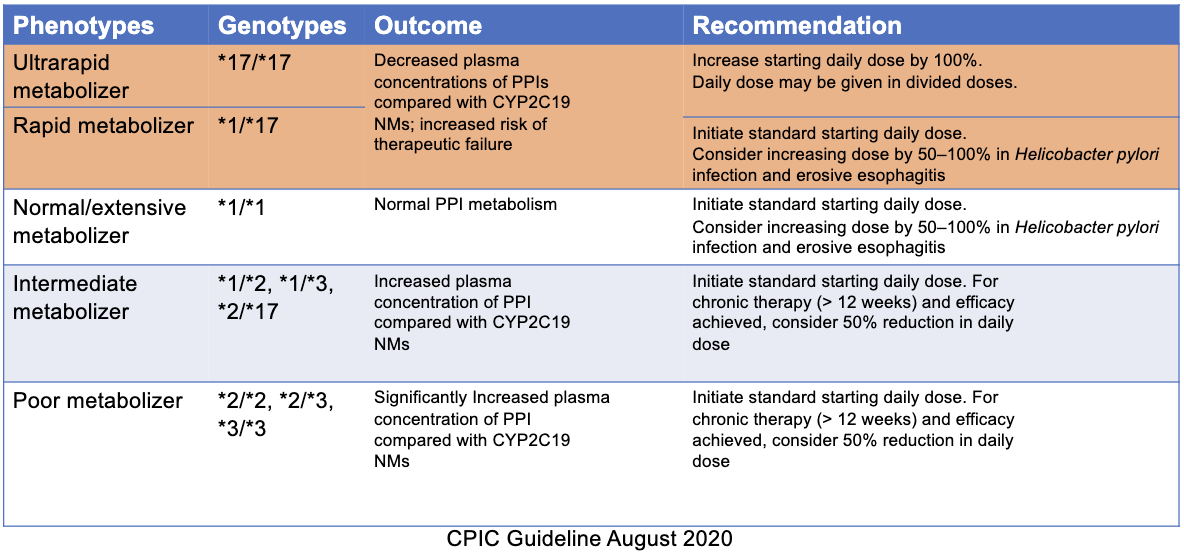
CYP2C19 recommendations for PPIs
UM (17/17)
RM (1/17)
UM (17/17)
decreased plasma concentration of PPIs
increase starting daily dose by 100% (divided doses)
RM (1/17)
increased risk of tx failure
standard daily dose
consider increase dose by 50-100% in Helicobacter pylori infection and erosive esophagitis
CYP2C19 and Voriconazole Metabolism
A triazole antifungal indicated for invasive aspergillosis
Wide interpatient variability
MOA
Like all azole agents, inhibits CYP450 dependent cell membrane ergostrerol à ergosterol synthesis by fungi
CYP2C19 recommendations for Voriconazole
UM (17/17) or RM (1/17)
PM (2/2, 2/3, 3/3)
UM (17/17) or RM (1/17)
increased metabolism → therapeutic concentration small
alternative agent (isavuconazole, liposomal amphtercin B, posaconazole)
PM (2/2, 2/3, 3/3)
greatly reduced metabolism → high concentration
alternative agent (isavuconazole, liposomal amphtercin B, posaconazole)
if voriconazole most appropriate → adminster at lower dose w/ TDM (trough = 0.5-0.6)

CYP2C19 recommendations for SSRIs
UM
RM
PM
UM
Sertraline = recommended starting dose
Citalopram/escitalopram = alternative agent not metabolized by CYP2C19
RM
Sertraline = recommended starting dose
Citalopram/escitalopram = recommended starting dose OR titrate or alternative agent not metabolized by CYP2C19 OR if no response
PM
50% reduction of starting dose/titrate OR alternative agent
CYP2B6 recommendations for sertraline
IM (1/6, 1/18, 4/6, 4/18)
PM
IM
reduced metabolism
recommended starting dose
slower titration and lower maintance dose
optional
PM
greatly reduced metabolism → high concentration/side effects
lower starting dose, titration, 25% reduction of maintenance dose
optional

CYP2B6 and CYP2C19 recommendations for Sertraline
UM/RM
NM
IM
PM
