ANP 2 Exam 1
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/40

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
41 Terms
What are the major functions of blood?
Transports dissolved gases, nutrients, hormones and metabolic wastes. Regulates pH and ion composition. Restriction of fluid losses at injury sites. Defense against toxins and pathogens. Stabilization of body temperature.
What is blood? What are its components?
Plasma=matrix. Blood is connective tissue. Made up of RBC (erythrocytes), WBC (leukocytes), and platelets
What types of protein are found in plasma? What are the major functions of these plasma proteins?
Albumins (60%) - major contributors to osmotic pressure and aid in transport of fatty acids, thyroid hormones, steroid hormones, and other
Globulins (35%) - antibodies and transport glubulins bind small ions, hormones and compounds that have low solubility in water
Fibrinogen (4%) - functions in clotting
Remainder (1%) - circulating enzymes hormones and prohormones
Describe RBCs. What are the key features? Describe its anatomy
Red=hemoglobin. Carry O2. No organelles lifespan of 120 days. Bioconcave disc with thin central region and thicker outer margin.
Describe hemoglobins structure and function
A subunit consisting of 2 alpha chains and 2 beta chains. Each chain hold heme molecule (iron ion that binds with oxygen)
What occurs during RBC recycling? What components are recycled? Where does this occur?
Macrophages of liver, spleen, and BM monitor condition of circulating RBC and engulf. If hemolyzed in bloodstream macrophages remove Hb molecules and cell fragments. Fe and subunits are recycled. Heme turns into biliverdin (green) then Bilirubin (yellow) goes into kidney and turn urine yellow and bile to turn feces into brown
Describe hemopoiesis. Where does it occur? What does it produce? What are the major cells involved?
Formation of formed elements. In Red Bone Marrow
Lymphoid stem cells: lymphocytes (T,B,NK) and 4 WBC
Myeloid stem cells: all other formed elements with hemocytoblast and megacarocytes to platelets
What are the major cells involved with erythropoiesis?What cell loses its nucleus? What are the major chemicals regulating RBC production?
Hemocytoblast → myeloid → proerythroblasts → Hb & normoblast (ejects nucleus) → reticulocyte → RBC.
Amino acids, iron, and vitamins regulate
Describe WBCs. What are the major types? What are characteristics and functions. How are WBCs different from RBCs?
Protect body from invasive things.
Have organelles lack Hb.
2 classes
Granular leukocytes: neutrophils, eosinophiles, basophils
Agranular leukocytes: monocytes, lymphocytes
All 5 main WBC
Neutrophils - first cels @ site of injury or infection, attack/digest bacteria (phagocytic)
Eosinophils - fights parasites needs Antibodies to phagocyt
Monocytes - turns into macrophages
Lymphocytes - T cell attack abnormal cells, B cell make antibodies, NK cell are natural killer
Basophils - helps increase local inflammation
Describe structure function and production of platelets
Small membrane-bound cell fragments containing enzymes and other substances important in clotting process. Release of chemicals for clotting. Formation of patch in walls of damaged BV.
Produced in bone marrow and stimulated by TPO and IL-6 (hormones) and multi-CSF
Describe clot formation which controls blood loss after an injury. Describe major phases involved in hemostasis. What are the main events of each of these phases? What vitamin, mineral, and proteins are the chemical reactions dependent upon? What is the last chemical reaction information of a clot: give the soluble protein, enzyme, insoluble protein?
1) Vascuar phase - vascular spasm (smooth muscle @ injury site tightens the injury), changes in endothelium @ injury to be sticky
2) Platelet phase - platelets get stuck @ sticky shit, platelets change and release chemicals
3) Coagulation phase - multiple chemical reactions. Final one is fibrinogen encounters thrombin (enzyme made from the reactions) to make fibrin. Fibrin and everything trapped by sticky shi and platelets is the clot
Dependent upon Vitamin K and Ca2+
What is clot retraction? Why is this neeeded after a clot is formed?
Platelets within fibrin mesh work contracts together make the clot smaller. Brings muscle fibers closer together to speed up healing
What is fibrolysis? What enzyme is involved?
Gradually dissolving of clot. Plasmin enzyme digests fibrin strands
Describe general features of the heart, gross anatomy
RA, LA, RV, LV.
Aortic arch
Pulmonary trunk
Pulmonary veins
SVC, IVC, Coronary sinus
Apex
What is the pericardium? What is its function? What is pericardial fluid and its function?
Lining the pericardial cavity. Protect and anchors heart, reduces friction, limits movement.
Visceral pericardium/epicardium - covers and adheres closely to outer heart
Parietal pericardium - lines inner surface of pericardial sac
Pericardial sac/fibrous pericardium - dense network of collagen fibers stablizes the position of heart and vessels
Pericardial cavity - space between visceral and parietal and contains pericardial fluid, reduces friction

What are the 3 different parts of the heart wall? What type of tissues do you find in these 3 layers?
Epicardium - visceral pericardium
Myocardium - muscular wall forms atria and ventricles contains muscle tissue BV and nerves
Endocardium - inner surfaces (like heart valves) simple squamous epithelium continuous with vessels
Describe the chambers of the heart and associated structures. What is the function of each of the chambers?
Right Atrium - gets deoxygenated blood and sends it to the RV thru R AV valve.
Right Ventricle - pumps blood from RA to pulmonary semilunar valve into pulmonary trunk
Left Atrium - receives blood from L and R pulmonary veins and sends oxygenated blood thru L AV valve
Left Ventricle - larger than R ventricle with thicker walls. Sends blood through Aortic valve (semilunar valve)
Name the valves of the heart and state their location and function
Right AV Valve/tricuspid - RA to RV valve
Pulmonary valve/semilunar valve - RV to pulmonary artery
Left AV valve/mitral/bicuspid - LA to LV valve
Aortic valve/semilunar valve - LV to aortic arch
List the features of cardiac muscle. What is their function?
Short striated with lots of mitochondria
Intercalated discs - interlocking adjacent membranes that propagate AP quickly
Interatrial septum - separates atria, muscular partition
Interventricular septum - separates ventricles, thicker muscular partition
AV valves - fibrous tissues
Describe the flow of blood through the heart and name each of the chambers and structures through which the blood passes. Is the blood oxygen rich or oxygen poor at each stage?
RA - oxygen poor blood from SVC IVC and coronary sinus
RV - oxygen poor blood to pulmonary valve/artery to go to lungs/exchange capillaries
LA - oxygen rich blood from pulmonary veins
LV - oxygen rich blood sent to aorta
What is the coronary circulation? What are the major vessels of this coronary circulation? What do the arteries branch off, what do the veins drain into?
coronary circulation is part of the systemic circuit that supplies blood to the heart wall. Major arteries are R and L coronary arteries branching off of the ascending aorta. Most of the blood leaving heart wall will eventually collect in the coronary sinus (a large thin-walled vein) before returning to the right atrium.
What is the difference between contractile and conducting cells?
Conducting cells - interconnects 2 nodes, distributes stim throughout myocardium. Smaller than contractile cells and AP spread by cell to cell contact
Contractile cells - produce contractions and propel blood
Describe how the AP forms and travels through the conducting system. Why does the AP pause at the AV node? How does the AP generated at the SA node/AV node? Why is the NS not required? How does the NS affect how fast depolarization to threshold occurs at SA node/AV node?
1) SA node at right atrium generates AP
2) Internodal pathways spread around adjacent cells
3) AV node pause here to stagger for ventricle so not everything contracts at once
4) AV bundle - after AV
5) R&L bundle branches - down from AV in the middle
6) Purkinje fiber - move from apex to up around the heart
NS not needed cause it spontaneously depolarizes. NS can add more neurotransmitters to increase or decrease speed of threshold.
What is absolute refractory period? Why can’t a second AP occur on the sarcollemma during the absolute refractory period? Why is this significant for cardiomyocytes? Why is it important for cardiocytes to not summate? What keeps them from being able to summate? (Look at graphs for Cardiac AP, Cardiac myogram vs skeletal muscle AP and skeletal muscle myogram)
Membrane cannot respond at all. Na channels are already open or closed and inactive so AP cannot occur on sarcollemma. Prevents twitches from summating. Heart needs to relax to allow blood to fill then contract.
Explain the structure and function of the conduction system of the heart.
1) SA node at right atrium generates AP
2) Internodal pathways spread around adjacent cells
3) AV node pause here to stagger for ventricle so not everything contracts at once
4) AV bundle - after AV
5) R&L bundle branches - down from AV in the middle
6) Purkinje fiber - move from apex to up around the heart
Explain what the ECG is measuring? What is the x and y axis (and in units). Describe various waves of the ECG. What do these waves represent? how is 1 heartbeat represented on the ECG
Records electrical heart with voltage over time. mV in mSec.
P wave - atria depolarize/systole
R peak - ventricular begin systole (atria begin diastole)
End of T wave - ventricle begin diastole

Describe the cardiac cycle and the relationship between contraction of each of the chambers, the pressure in each of the chambers, parts of the ECG, and the heart sounds
Systole - contraction and pushes blood into adjacent chamber or trunk
Diastole - relaxation, chamber fills with blood
Pressure goes from high to low
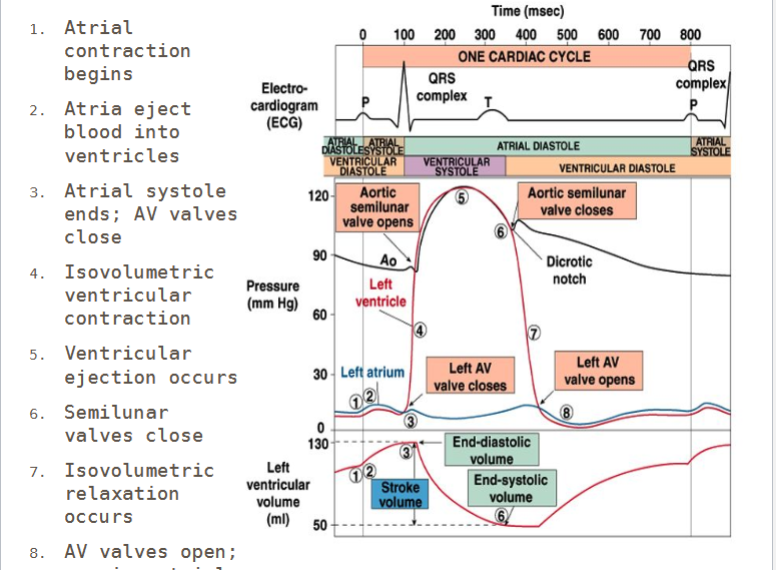
All phases of Cardiac Cycle
AS - filled with 70% blood atrial pressure pushes blood into ventricles
AD - continues until start of next cycle
VS - blood pushed through systemic and pulmonary circuits toward atria. V pressure higher than A pressure shut AV valves. Ventricles contract and pressure is higher than arterial trunk and exit ventricle. P falls rapidly near end. SV =blood ejected from each ventricle around 80ml.
VD - both atria and ventricles are relaxed for 430 msec. Ventricles passively fill to 70%. Last 100 msec atria are in systole which fill ventricle up to 100%. . At beginning all valves are closed

What are the heart sounds? Which valves closing are related to S1/lubb vs S2/dubb? Explain what is heard with a leaky valve vs stenosed valve. What wuld be the potential issues with leaky AV and semilunar valves and stenosed AV and semilunar valves. Note any differences between R and L valves.
S1/lubb - AV valves close at start ventricular contraction
S2/dubb - semilunar valves close at beginning of ventricular filling
Leaky valve - swishing noise immediately after closure/sound. Blood goes back where its coming from
Stenosed - opening is narrow and swishing sound precedes closing. Blood doesnt escape completely
R&L can hear where its at

What is cardiac output (CO)? How is it calculated?
Amount of blood pumped by left ventricle in 1 minute
CO=HRxSV
CO= 75bpm x 80ml/beat = 6L/min
What are factors influencing HR and thus CO?
Sym and para affect HR? Describe cardiac reflexes that target the SA ndoe and HR. Use O2 levels, CO2 levels, pH and BP as initial stim
Sympathetic fibers - depolarize to threshold faster and increase HR which increases CO.
Parasympathetic fibers - depolarize slower so decreases HR which decreases CO
Cardiac Reflex - 1) receptors detect change in BP, O2, CO2 and pH. 2) sends info to control center (heart center in Medula oblongata). 3) heart center receives and processes info and forms instructions and sends to effector. 4) effector does something
Ex BP, O2, down and CO2 up. Decreases blood pH
Barareceptors send info to center. Center SA node depolarizes to threshold faster and increases HR and CO which increases BP which increases O2 and pH and decreases CO2
How does venous return affect the SA node and HR and thus CO (bainbridge reflex)
How do Epi, NE, and TH affect HR and thus CO?
Increase venous return HR adjusts. Walls of right atrium stretch and triggers sympathetic activity. Epi, NE, TH increase HR by binding to receptors at SA nodes
What are the factors influencing SV and thus CO?
What influences EDV and ESV
Factors influencing SV: EDV and ESV.
Factors influencing EDV: blood filling time, rate of venous return, preload proportional to EDV
Factors influencing ESV:preload, contractility of ventricle, after load
Factors influencing CO: HR and SV (thus autonomic innervation, hormones, EDV, ESV)

Discuss preload, contractility, venous return in regards to EDV, ESV, SV, and CO
Preload: Ventricle stretching
If EDV is increased (more blood) contractility increases which increases SV and increases CO and decreases ESV
What is afterload? What would cause a high afterload how is SV affected in someone with a high afterload?
How much force to let blood out. High after load would be from hypertension or something like that or too much blood which requires longer time to build tension to eject. Less time for blood to eject so there is less blood ejected so lowers SV.
What happens to CO if the HR gets over 180bpm? Why do you get this response?
If HR gets too high the EDV is too low which lowers SV and lowers CO.
Be familiar with the figure for the cardiac cycle, pressures, and heart sounds
Be familiar with the figure for the cardiac action potential
Be familiar with the figure of an ECG reading