specific sx conditions of GIT 2 - stomach, SI, LI, rectum, anus
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/49

There's no tags or description
Looks like no tags are added yet.
50 Terms
Hiatal hernia - def
Herniation of cardia through oesophageal hiatus
Grade 1-4
Hiatal hernia - Common effect
Gastro oesophageal Intussusception
Hiatal hernia - Tx
Sx - suture hiatus, oesophagopexy, L fundic gastropexy

Gastrotomy - access
Ven midline coeliotomy
Pack off stomach
Stay sutures
Incise between greater + lesser curvature (Stab + scissors)

Gastrotomy - stomach Closure
½ layer
Mucosa/ submucosa simple cont/ int/ inverted
Serosa/ muscularis/ submucosa inverting
Why can inverting pattern be used for stomach + not intestine
Large lumen so no stricture
Partial gastrectomy - casue
Necrosis, Neo, ulcer
Partial gastrectomy - types
Invagination of necrotic tissues + suture healthy together → slough off
Sharp excision
Surgical staplers
GDV - common breeds + why
Purebred large/ giant dogs - setter, poodle, weinmeraner, Great Dane, St Bernard
Inc thoracic depth : width ratio (deep chested)
Rapid eating, few meals fed
Aggressive
Relative
GDV - Common rotation + effects
180 degrees clockwise → pylorus L ven, fundus R dor → compress oeseophagus, stretch duo → gas accumulation
GDV - Effects on body
Dec abd blood return → cardiogenic shock, splenic congestion
Inc abd P → limit diaphragm
Dec perfusion → myocardial Ischaemia
Inc gastric P → compress BV → necrosis → bact transfer to blood
Free radicals → Reperfusion injury

GDV - Dx
Breed
Swollen cr abd
Drum like abd (Percuss)
Reverse C rx
Inc PCV, stress leukogram
Inc bilirubin, pre renal azotaemia, inc lactate
GDV - Immediate tx
Shock Fluid therapy
Decompress stomach
GDV - How to administer large vol in shock IVFT
Wide cannula
2 cephalic cannulae
Infusion pump/ compression sleeve
Avoid HL cannula
GDV - How to decompress stomach
Conscious Stomach tube with lube + mouth gag
Flank paracentesis of fundus
LA Temp Gastrostomy
GDV - Temp Gastrostomy to decompress sotmach process
LA
Prep flank
5cm incision cd + parallel to costal arch
Stay suture stomach
Decompress stomach with needle/ stab incision
Suture gastric mucosa to skin
Re suture stomach before coeliotomy
GDV - How to prevent recurrence for torsion/ volvulus in all cases
Gastropexy
We keep talking about stay sutures, but how do we actually use them to manipulate the tissue after we’ve placed them?
Assistant moves
Held in 1 hand
Clip to drapes/ equipment
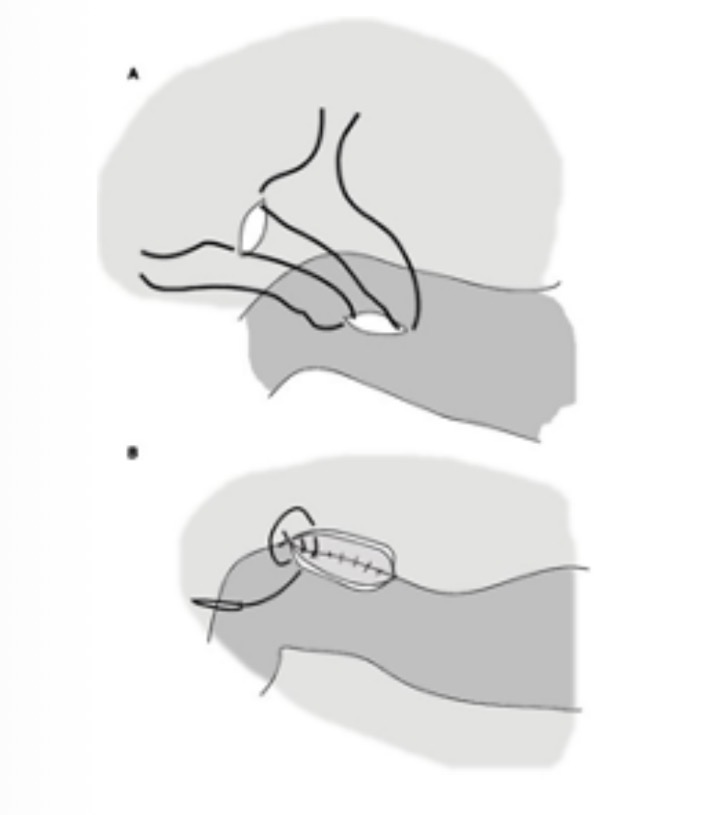
GDV - gastropexy process
Rotate stomach to norm → Fix pylorus to R abd wall (suture incisions/ Foley catheter)→ permanent fibrous adhesion → prevent torsion + volvulus, can still dilate

GDV - When is splenectomy needed (congestion normally resolves when stomach sorted)
Thrombi in splenic BV
Splenic torsion
GDV - When is gastrectomy needed
Gastric necrosis (grey/ green wall, no active bleeding, no pulse, thin wall)
GDV - Meaning of red/purple vs grey/ green stomach wall colour
R- congestion, intramural H → recovers
G- non viable → remove
GDV - Post op care
Fluids
Monitor ECG, Electrolytes
NBM 1-2d → water, small food
Gastric mucosa protectants - sucralfate, antacids
V → Metaclopramide, delay food
GDV - Long term manamgent
Small frequent meals
Avoid exercise after meals
GDV - Common ECG issue post op
VPC
Gastric outflow obstruction - causes
Neo, pyloric stenosis, hypertrophic gastritis, pyloric m hypertrophy/ dysfunction
Gastric outflow obstruction - Tx
Pyloroplasty (YU antral flap)
Gastroduodenostomy + gastrojejunostomy - billroth numbers
1= duo
2= Jejuno
Gastroduodenostomy + gastrojejunostomy - Purpsoe
Reset large amount dist stomach + pylorus

Enterotomy - process
Isolate + pack
Evacuate contents
Occlude lumen (doyen, finger)
Longitudinal antimesenteric incision
Closure - simple int/ appositional
Check closed with saline inj

Enterectomy - process
Isolate + pack
Evacuate contents
Occlude lumen (doyen, finger) - crushing + non crushing
Lig BV
Cut along crushing clamps (with antimes>mes)
Ensure lumen sizes match up (cut antimes)
Closure - simple int/ cont
Check closed with saline inj


Enteroectomy - SI closure
3-4mm from edge
Antimes + mes border knots
When you’re clamping off the intestinal lumen to do an enterectomy, which set of clamps (crushing or non-crushing) should you put on first? + why
Crushing - boundaries for resection, dec time clamped, small patients
Non crushing - can remove contents
Complications of SI/LI sx
Dehiscence
Stricture
Linear FB - tx
DONT PULL
Fixed at tongue + no peritonitis → cut + leave → in faeces 3d later
Not fixed at tongue/ peritonitis → multiple enterotomys (dist → prox)
Linear FB - Effects
Peritonitis
Cut through mesentery
Gut perforations

Intussusception - common cause
Young dogs
Hypermotility (parasites, D)
Intussusception - Common location
Ileocolic junction
Intussusception - Effects
Obstruction, Ischaemia, adhesions, necrosis

Intussusception - Dx
V
Palp mass
US

Intussusception - Tx
Manually reduce
Enterectomy
Check rest of intestine
Suture SI to each other to prevent reoccurrence
Rectal prolapse - causes
Persistent tenesmus
Defects in rectal/anal support
Anal sphincter denervation
Rectal prolapse - Tx
Treat underlying cause
Reduce
Sx- Purse string suture 1-5d, colopexy, resect + anastomosis
Rectal prolapse - Post op care
Stool softeners
Low bulk diet
Sed to dec tenesmus (acepromazine)

Anal furunculosis - def
Chronic ulcerative fistulas surrounding anus
Anal furunculosis - Common animals
German shepherd, lab, setter, collie
Anal furunculosis - CS
Tenesmus, pruritus, tracts around anus
Anal furunculosis - Tx
Immunosupp - ciclosporin
Sx excision

Anal sac adenocarcinoma - removal options
Open - probe + dissect anal sac
Closed - incision over anal sac, don’t enter anal sac
How can you differentiate a rectal prolapse from an intussusception protruding from the anus?
P- can’t separate tissue + edge of anus
I- probe between tissue and edge of anus