health assessment- breast, vascular/lymphatic, head/neck
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/98

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
99 Terms
landmarks
aorta, SVC, IVC, right atrium, right ventricle, pulmonary artery, left ventricle, left atrium
apex
bottom of the heart
base
top of the heart
Point of maximal impulse (PMI)
apex beats/ apical impulse
diastole
relaxation; filling with blood
systolic
contraction; blood is pumped
S1 (lub)
Mitral (M1) and Tricuspid (T1) closes and makes sounds; beginning of systole
S2 (dub)
aortic (A2) and pulmonary (P2) valve closing; end of systole
S2 split
A2 and P2 are heard separately. duuuuub sound
S3
ken-tuck-y I II
physiologic- disappears when patient sits up
pathologic- persists when patient sits up
heard after S2
S4
ten-ne-ssee II I
physiologic- adults > 40, after exercise, no CVD
pathologic- CAD, MI, HTN
before S1
grade I murmur
faint, only heard by expert, no thrill, not heard in all positions
grade II murmur
soft, heard in all positions, no thrill
grade III murmur
moderately loud, no thrill
grade IV murmur
loud and palpable thrill
grade V murmur
very loud, thrill, heard with stethoscope partially off chest
grade VI murmur
loudest, with thrill, heard with steth off of chest
benign murmurs
infants, children/adolescents, athletes, fever, anemia, adult over 50, pregnant
increased velocity over normal aortic and pulmonic valve
grade I-II
P
atrial depolarization
QRS complex
ventricular depolarization
T wave
ventricular repolarization
infants and children
heart starts at 3 weeks of gestation
lungs are nonfunctional, so blood is redirected to heart (strengthens ventricles)
apex in 4th intercostal until 7
pregnancy
increase in blood plasma and RBC
SV increases then returns to normal after 10 days post partum
arterial bp decreases and is lowest during the 2nd trimester
aging adults
systolic bp may increase; diastolic decrease
arrythmias may occur
ECG change
subjective data (heart)
chest pain
dyspnea
cough
fatigue
cyanonsis/pallor
edema
nocturia
past CV history
family CV history
CV risk factor
inspection (heart)
sitting supine
inspection (heart)
varicrose veins
scarring around chest
nail clubbing
JVD
video on measurement
arterial insufficiency
ischemic ulcer
cyanosis
cool and pale
claudication (pain with walking/exercise)
diminished/absent pulse
venous insufficiency
stasis ulcer
present pulse
warm and red/brown
edema
aching pain, worse at end of the day
anklebrachial index
dopler steth and bp cuff
record and divide
use lowest finding
deep vein thrombosis
1-3 cm= mild lymphedema
3-5cm= moderate lymphedema
>5 cm = severe lymphedema
> or= 2cm can occur with DVT
1-2 score is moderate risk
>3 is high probability
palpation
PMI
edema, cap refill, skin temp
pulse
arterial pulses
radial, brachial, femoral, popliteal, doralis pedis, posterior tibial
pulse guidelines
4- bounding
3- stronger than normal
2- normal
1- diminished
0- absent, not palpable
absent pulse
use doppler
capillary refill
should refill within 1-2 seconds
after 2 seconds may indicate issues with perfusion/vasoconstriction
pitting edema
1- 2mm
2- 4mm
3- 6mm
4- 8mm
modified allen test
ulnar and radial arterial pulses
heart sound locations
A- aortic valve
P- pulmonary valve
E- erb’s point
T- tricuspid valve
M- mitral valve
(ape to man)
thrill
palpable
bruit
auscultatory
CV disorders
dizziness, syncope, fatigue, papitations, chest pain, dyspnea
CN VII
facial nerve
inspection (head, scalp, face)
note expression, tics
shape- normocephalic
symmetry
lesions
palpate (head, scalp,face)
contour
mass
depression
tenderness
tension
spans across forhead, can occur in eye
migrainw
tend to be one sided, but can be on both side
cluster
occur behind eye, more common in men
allergic salute and crease
crease forms on nose from children wiping it
allergic shiners & dennie-morgan lines
caput succedaneum
tissue edema, crosses over a suture
goes away after a couple of days
cephalhematoma
well defined and confined (does not cross over suture)
goes away after weeks or months
hydrocephalus
CSF accumulation, increasing intracranial pressure
face looks small compared to head
Ventroperitoneal shunt can divert CSF
plagiocephaly
asymmetry of cranium
treat w tummy time, pt, corrective headwear
craniosynostosis
premature closing of 1 or more cranial sutures
results in malformation
most treated with surgery
trisomy 21
up-slanted eyes
flat nose
protruding, thick tongue
ear dysplasia
short, web neck
small hands with single palmar crease
paget’s disease
localized rapid bone turnover
affects skull, femur, tibia, pelvic bones, vertebrae
acromegaly
excess of growth hormone that results in enlargements of peripheral body parts and soft tissue after fusion of epiphyseal plates occurs without increase in height
cushing’s
excess secretion of ACTH and chronic steroid
develop rounded “moon like” face, red cheeks, hirsutism (beard in women) on upper lid, lower cheeks, and chin; acneiform rash on chest
parkinson
deficiency of dopamine and degeneration of substantia nigra of basal ganglia in brain
produce face that is flat and expressionless, elevated eyebrows, staring gaze, oily skin, drooling
cachectic
accompanies chronic wasting diseases such as cancer, dehydration, and starvation
sunken eyes, hollow cheeks, exhaustion, defeated expression
scleroderma
complication of autoimmune diseases affecting connective tissues of skin, blood vessels, and internal organs
skin and SQ tissue becomes increasingly hard and cannot be pinched up from the underlying structures (looks like botox)
cerebrovascular accident (CVA)
forehead wrinkling intact and symmetrical
palpebral fissure not widened
nasolabial fold is flat
mouth drooping
supranuclear lesion within the brain due to bleeding or ischemia
bell palsy
nasolabial fold is flat
mouth drooping
forehead not wrinkling and asymmetrical
palpebral fissure widened
affects the facial nerve (V)
sternomastoid
rotation and flexion
CN XI
trapezius
shoulders and extend/turn
CN XI
Torticollis
twisted neck
symptom of injury or shortening related to sternomastoid
“wry neck”
inspection (neck)
symmetrical, no masses, full ROM
palpation
trachea midline- slide finger to each side
carotids- one at a time
auscultation
carotids- with bell 3x
thyroid for bruits
thyroid
T3 and T4- synthesis and secretion of hormones that control rate of cellular metabolism
vascular endocrine gland
hyperthyroidism s/s
goiter, nervousness, tachycardia, weight loss, excess sweating, SOB, heat intolerance
hypothyroidism s/s
constipation, fatigue, dry coarse hair, dry skin, weight gain, myxedema
lymphatic locations

lymph node assessment
palpate both sides at same time for comparison
gentle circular motions
deep cervical chains- tilt head to side being examine, press under muscle
supraclavicular- hunch shoulders
lymphadenopathy
enlargement >10cm
infection- tender, enlarged, bilat, firm but freely movable
cancerous- hard, unilateral, nontender, fixed
breast anatomy

quadrants
upper inner
lower inner
upper outer
lower outer
axillary tail of spence
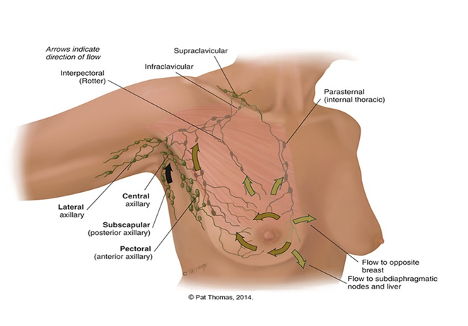
axillary nodes
drain 75% of lymph
central axillary nodes
pectoral nodes
subscapular nodes
lateral nodes
lymph flows up from central to infraclavicular and supraclavicular nodes
supernumerary nipple
where an extra nipple can form
pregnant women
breasts enlarge and feel nodular; nipples are larger
areolae enlarge and become darker; venous pattern is prominent
changes begin in 2nd month of pregnancy
colostrum
precursor for milk, contain same amount of protein and lactose, practically no fat
first few days after birth
rich in antibodies
lactation
1-3 days postpartum
emulsified fat and calcium caseinate
aging
glandular tissue atrophies after menopause
adipose tissue decreases
axillary hair decreases
lactiferous ducts are more palpable; feel firm and stringy bc of fibrosis and calcification
inner structures more palpable
self breast exam
monthly, starting at 20
4-7 days after period
menopause or no cycle- same day each month

screening
ultrasound- younger women bc of dense tissue
family hx, mammogram at least 10 years before onset
american cancer society- begin at 40-44, annual mam from 45-54, biennial mam 55+ or continuation of annual
clinical breast exam
same as self exam
palpate lymph nodes
palpate breast
compress nipple to assess for discharge
large breasts- bimanual technique
mutations
BRCA 1 and BRACA 2
men
1% of breast cancer
gynecomastia
noninflammatory enlargement of male breast tissue
puberty mild and transient
older men- appear due to testosterone deficiency
mastitis
inflammatory
one quad, tender, hot, swollen
treat- antibiotics, heat, frequent feedings

abcess
mastitis worsens
pus pockets
treat- antibiotics, incision/drainage
feed on unaffected side

dimpling
skin retraction from contracting of suspensory ligaments

carcinoma
nipple discharge possible/ deviation possible
usually unilateral
may not always have mass

benign breast disease (fibrocystic breast disease)
makes breast exam difficulty
nodularity
swelling/tenderness

lymphedema
post radiation/axillary node removal
interstitial fluid build up
edema (peau d’orange)
lymph obstruction
pig skin/orange peel
usually suggests CA

fixation
usually CA
fibrosis fixes breast to underlying structure
