physio exam 5
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/107

There's no tags or description
Looks like no tags are added yet.
108 Terms
internal v. external respiration
occurs where / bt what
external → internal
internal respiration = oxidative phosphorylation
occurs in systemic tissue “the actual use of O2”
happens at the cellular level = use O2 release CO2
external = what needs to be done before internal can happen
pulmonary ventilation,
exchange b/t lungs/blood
diffusion = alveoli → blood
transportation in blood
exchange b/t blood/tissue
diffusion = blood → alveoli

acid-base balance:
controlled by what
equation that determines pH
which is controlled by respiratory system
respiratory system
pH = HCO3/CO2
2 controlled variables
CO2 is controlled by lungs
HCO3 controlled by kidneys
respiratory system:
upper airways =
respiratory tract =
conduction zone =
starts/ends where
respiratory zone =
starts/ends where
structures of thoracic cavity
upper airways = air or food (head/neck airways)
respiratory tract = only air (pharynx → lungs airways)
conduction zone = has air but no gas exchange
start larynx, end terminal bronchial
respiratory zone = has air and gas exchange happens
start respiratory bronchiole, end alveoli
structures of thoracic cavity
conducting zone (CZ):
function of 2 epithelium =
goblet cells =
purpose
ciliated cell
purpose
anatomic dead space = mL?
2 purposes
2 epithelium = respiratory elevator
goblet cells = make mucus
1st protective mech keeps foreign objects out of lungs
ciliated cells = hair like projections
brings mucus/trapped debris up into throat so you can spit or swallow
conduction zone = anatomic dead space = 150 mL of air but no gas exchange
function = warm + humidify air
1 breath = ____ mL
mL conduction zone (CZ)
mL respiratory zone (RZ)
1 breath = 500 mL
150 mL stuck in conduction zone
350 mL respiratory zone (RZ)
respiratory zone:
epithelium structure =
function =
alveoli =
capillaries =
alveolar pores =
thin epithelial cell layer of alveoli and basement membrane
gas exchange via diffusion
alveoli = site of gas exchange
capillaries = form mesh over alveoli bc exchange happens b/t alveoli and capillaries
alveolar pores = pressure equalization
alveoli:
2 cell types in order
type 1 alveolar cells =
structure
outside?
type 2 (secondary) alveolar cells =
purpose =
surface tension =
type 1 alveolar cells = 1st = gas exchange
structure = simple squamous epithelium
considered outside the body until you cross type 1 alveolar cells
type 2 (secondary) alveolar cells = secrete surfactant
surfactant = secreted to reduce surface tension so breathe easy
surface tension = H’s from H2O in CZ tend to attract one another and collapse alveoli towards the center

respiratory membrane:
what is it =
2 sides
alveoli side=
capillary side=
thickness
membrane is a barrier you have to cross for diffusion
sides
alveoli side = Type 1 cells and basement membrane
capillary side = capillary endothelial cells and basement membrane
very thin
structures of the thoracic cavity
chest wall = purpose
bones =
3 muscles =
pleura =
pleural sac =
visceral pleura =
intrapleural space =
parietal pleura
chest wall = airtight, protect lungs
bones = sternum, ribs, thoracic vertebrae
muscles = internal/external intercostals and diaphragm
pleura = membrane lining of lungs/chest wall
2 pleural sacs = 1 around each lung
visceral pleura = on lungs
intrapleural space =
parietal pleura = chest wall
Forces of pulmonary ventilation:
ventilation =
how air move
inspiration =
when stop
expiration =
when stop
ventilation = bulk flow driven by pressure gradient
air moves high pressure → low pressure
inspiration (inhalation) = lung pressure < atm pressure
when stop = lung pressure = atm pressure
expiration = lung pressure > atm pressure
when stop = lung pressure = atm pressure
3 steps what drives ventilation
Boyl’s law =
inhalation
exhalation
3 steps
muscle movement comes first
volume change
causes change in Patm, Palv, Pip, and Ptp
causes air movement high to low
Boyl’s law = pressure inversely related to volume
inhalation = inhaling muscles contract, lung expands (high lung volume), low lung pressure, air moves in
exhalation = relax inhaling muscle, contract exhaling muscle, lung collapses (low lung volume) , high lung pressure, air moves out

Patm (atmospheric pressure) =
what is it
lung pressures given relative to ___
low v high altitude
Patm = 760 mm Hg at sea level
lung pressures relative to atm pressure (Patm = 0)
low altitude = high atm pressure
high altitude = low atm pressure
Palv (alveolar pressure) =
what is it
given relative to ____
how drive ventilation?
Palv = pressure of air in alveoli/alveolar sacs
relative to Patm
difference b/t Palv and Patm drives ventilation
inspiration: Palc < Patm
expiration: Palv > Patm
no air movement: Palv = Patm
Pip (interpleaural pressure) =
always ____ and ____
why?
why doesn’t visceral and parietal pleural come apart?
inhalation v exhalation
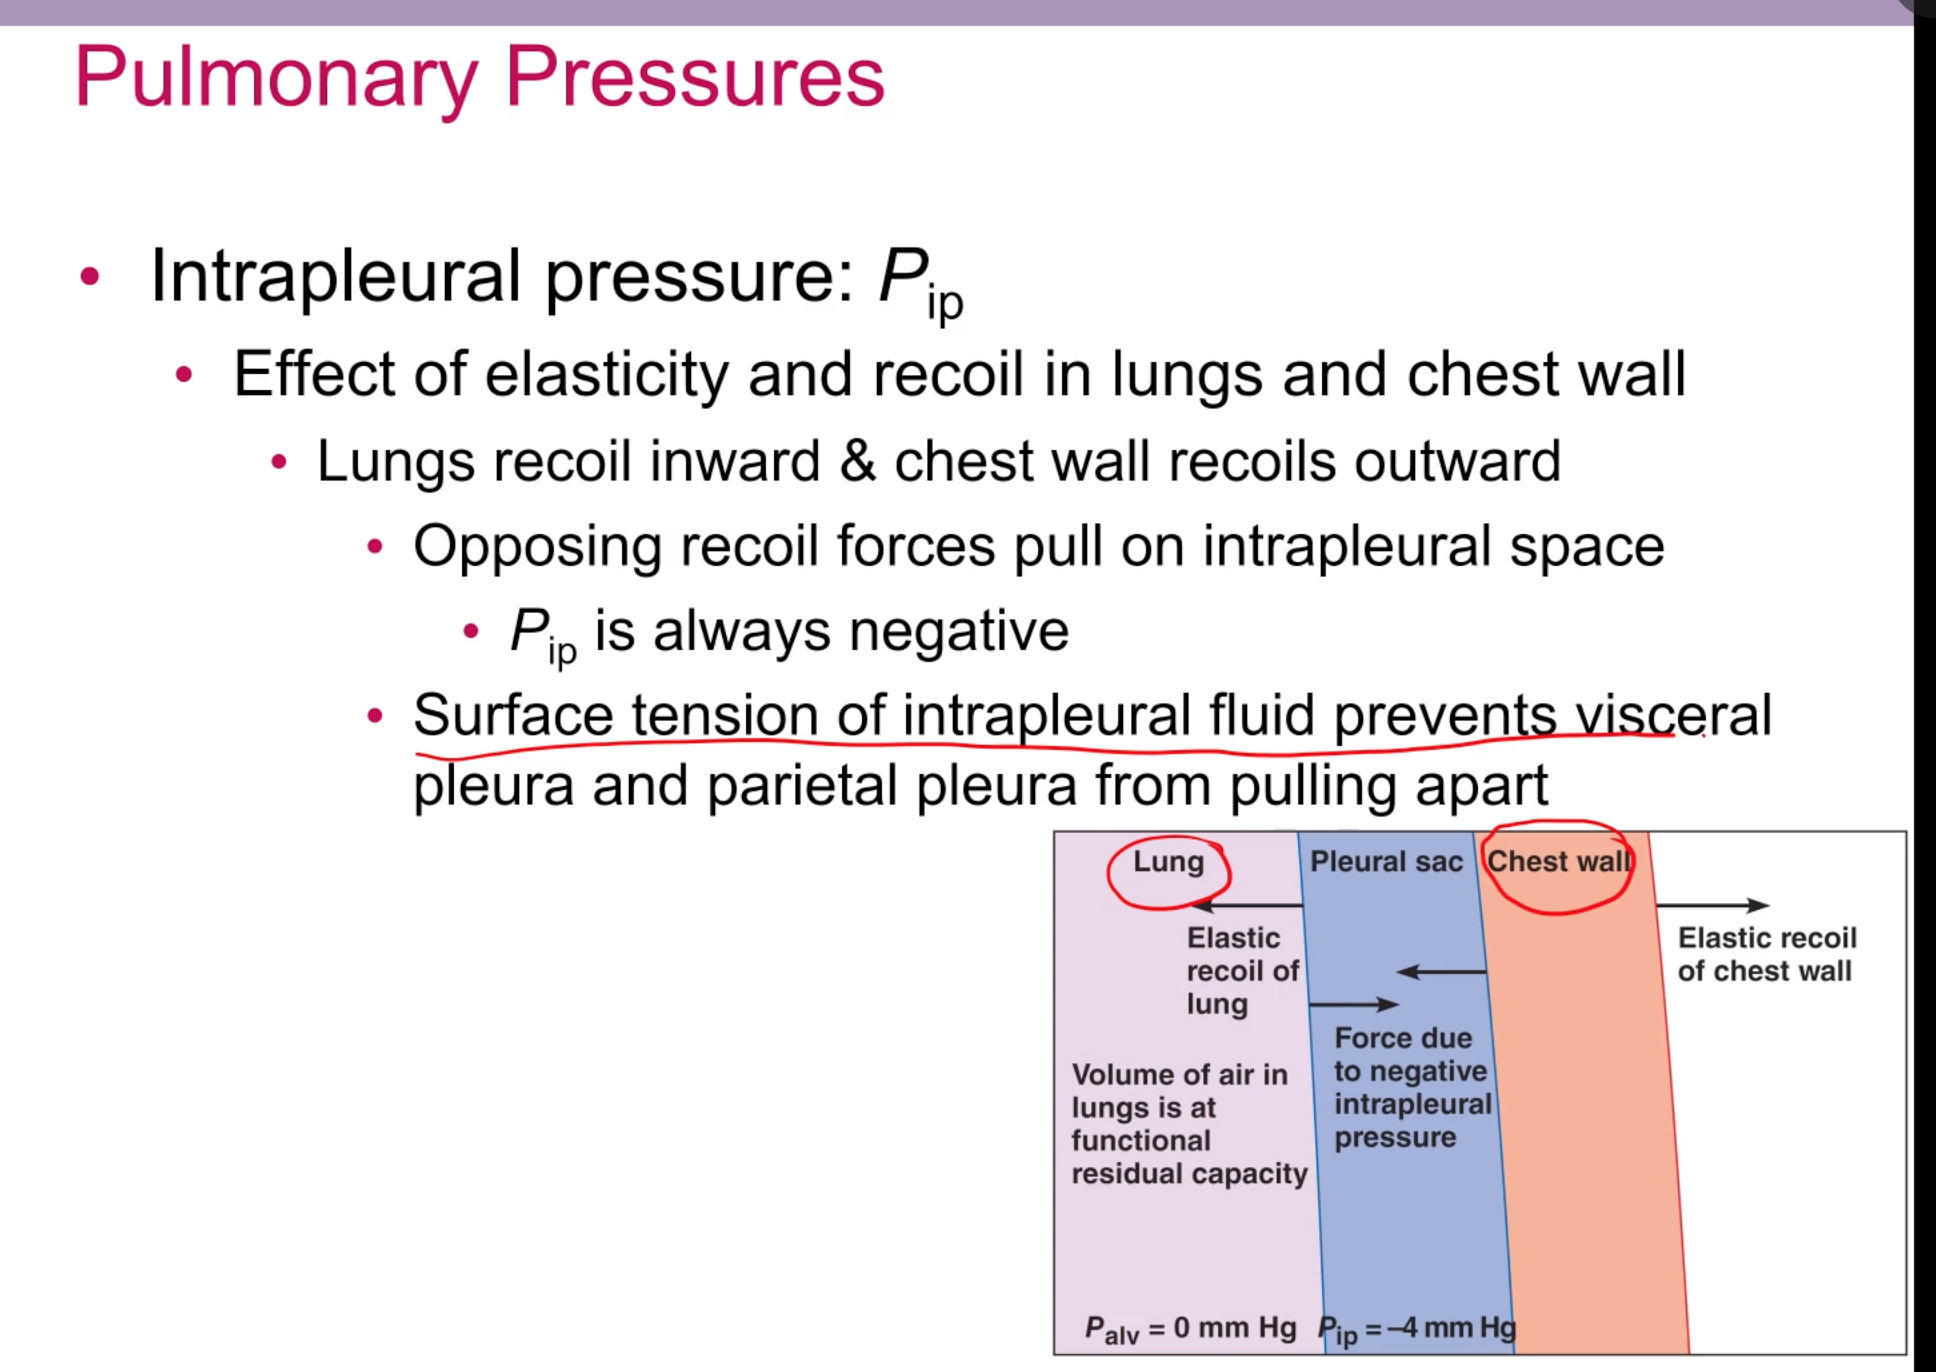
Pip = pressure inside pleural sac
always negative (-4 mm Hg)
opposing elastic recoils of lung (inward) and chest wall (outward) pull on pleural sac/space from both sides
surface tension of intrapleural fluid (H from H2O)prevents visceral and parietal pleural from pulling apart
always less than Palv
if more would push alveoli and they’d collapse
inhalation = more negative = more pull on the lungs (expanding)
exhalation = less negative = less pulling on the lungs (collapse)
Ptp (transpulmonary pressure) =
equation =
inhalation v. exhalation
Ptp = distending pressure across the lung wall
Ptp = Palv - Pip
inhalation = Ptp increases
Pip becomes more negative
exhalation = Ptp decreases
Pip becomes less negative
Pneumothorax:
what is it
open v. closed
Pip = ?
Pip = ?
Palv = ?
what happens to lungs?
pneumothorax = an opening of pleural sac into the intrapleural space
open (trauma/stab wound) = from the outside, sucking chest wound
Pip = Patm (open to the atmosphere)
closed (spontaneous) = from the inside,
Pip = less neg, Patm (sac needs to be closed to maintain neg)
both lose distending pressure across lungs, so alveoli/lungs collapse
Palv = Patm
breathing cycle:
start =
Pip =
Palv =
breathing cycle =
mechanics of breathing steps
start = at rest
Pip = -4 mm Hg
Palv = Patm
breathing cycle = inspiration and expiration
mechanics (muscles) → volume change → pressure gradient change → air movement
flow:
what is it
equation
pressure gradient (DP)=
how move?
2 causes of resistance (R)
flow = air flow during a breathing cycle
flow = (Patm - Palv) / R
pressure gradient (DP) = force for flow
Changes in Palv affect gradient, Patm is constant
Palv > Patm = exhale
resistance (R) from airway radius and mucus
2 determinants of intra-alveolar pressure:
functional residual capacity (FRC) = not the equation
change in Palv over a breathing cycle
amount of air in alveoli
functional residual capacity (FRC) = amount of air in alveoli at the start of breathing cycle
volume of alveoli
lung recoil → volume decrease → pressure increase

2 inspiratory muscles =
2 expiratory muscles =
2 step exhalation mechanism =
2 inspiratory muscles =
diaphragm = moves down when contracting
external intercostals
2 expiratory muscles =
internal intercostal
abdominal muscles
exhalation =
passive exhalation = relax inhaling muscles
lung/chest recoil back to original positions
active expiration = contract expiratory muscles
greater and faster decreases
what happens to the pressures during inhalation and exhalation:
Patm (atmospheric)
Palv (alveolar)
Pip (inter pleural)
Pap (trans pulmonary)
Patm (atmospheric) = static
Palv (alveolar)
inhalation = low
exhalation = high
Pip (inter pleural) = always neg
inhalation = more neg
exhalation = less neg
Pap (trans pulmonary)
inhalation = increases
exhalation = decreases
events in process of inhalation bad card delete
external intercostals and diaphragm contract
Pip increases
Ptp increases
volume increases
Palv decreases

events in process of inhalation (in order, remember it all order doesn’t seem to matter except starts with muscles)

2 forces that affect alveoli =
compliance =
when needed
type of pulmonary disease
recoil =
when needed
type of pulmonary disease/problem
which pulmonary disease has high CO2/acidic blood
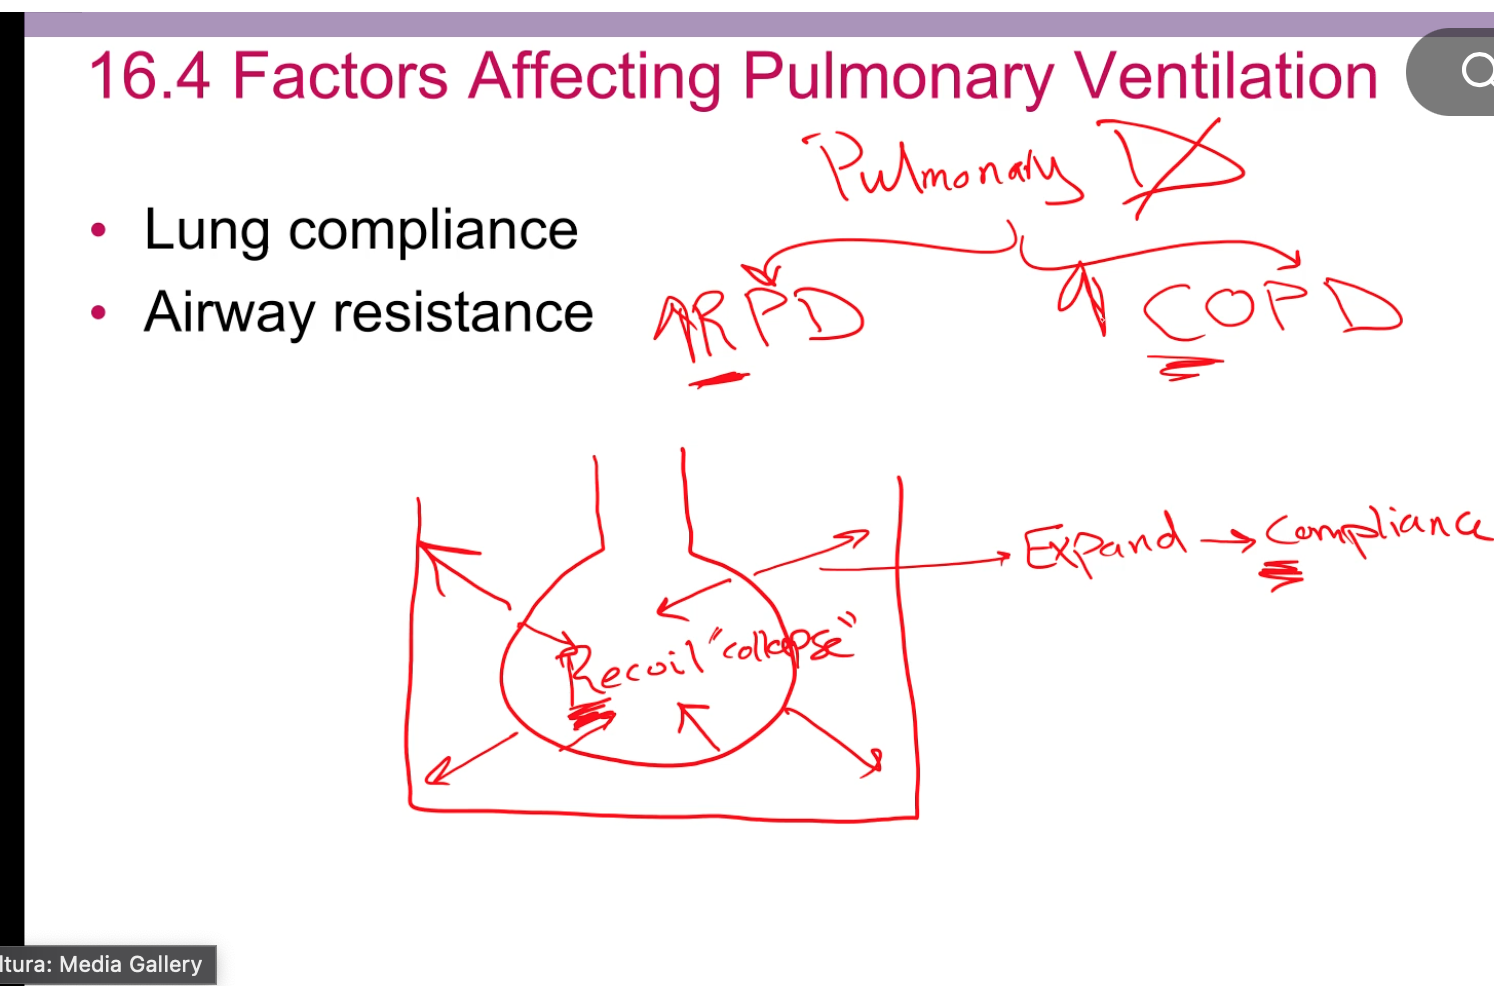
2 forces that affect alveoli = compliance and recoil
compliance = outward/expansion force (helps inhalation)
COPD = problem is high compliance = trouble exhaling
high CO2/acidic blood
recoil = collapse force (helps exhalation)
RPD = problem is high recoil = trouble inhaling
lung compliance:
what is it
equation
2 factors affecting lung compliance
elasticity
surface tension of lungs
ease of lung stretching/inhalation
lung compliance = DV / D(Palv-Pip)
2 factors affecting lung compliance
elasticity = more elastic recoil → less compliant
surface tension of lungs = more surface tension → less compliant
surfactant:
what is it
secreted by
does what to compliance/inspiration
prevent what
more important in small or big alveoli?
detergent that decreases surface tension
type 2 cells
increases lung compliant/makes inspiration easier
prevent collapse
important for small alveoli
conditions associated with decreased compliance:
restrictive pulmonary disease (RPD) =
affect on compliance and recoil
infant respiratory distress syndrome =
when
restrictive pulmonary disease (RPD) = stiffening/thickening lung tissue
low compliance high recoil
infant respiratory distress syndrome = non functional type 2 cells (no surfactant production)
premature birth, lungs not fully developed
airway resistance:
relationship to radius/flow
hard to breathe = affect on pressure/volume
4 factors that affect airway reistance:
changes in Ptp = inhalation v exhalation
tractive forces = inhalation v exhalation
smooth muscle = bronchoconstriction v dilation
mucus secretion =
high resistance (hard to breathe) = low radius, low flow (inversely proportional)
hard to breathe = SAME VOLUME of air is moved, just takes more pressure
factors that affect resistance:
changes in Ptp
inspiration = increase Ptp, airways open
expiration = decrease Ptp, airways recoil
tractive forces
inspiration = tissue pull away from airways, airways open
expiration = tissues no longer pulled away, airway recoil
smooth muscle
broncho constriction = contracts, dec radius, inc resistance
broncho dilation = relaxes, inc radius, dec resistance
mucus secretion =
excess production or inability to clear = inc resistance

airway resistance:
cystic fibrosis =
chronic bronchitis =
how smoking cause?
COPD or RPD?
cystic fibrosis = thick mucus bc has less water
chronic bronchitis = excessive mucus
chronic smoking → larger goblet cells → over secreting mucus → block airways with mucus
type of COPD
extrinsic control of bronchiole radius = which nervous system
parasympathetic = bronchoconstriction or dilation?
sympathetic =
hormonal control =
intrinsic control of bronchiole radius
histamine =
when released
CO2 =
autonomic nervous system
extrinsic control
parasympathetic = contract smooth muscle (bronchoconstriction)
sympathetic system = relaxation of smooth muscle (bronchodilator)
hormonal control = epinephrine (bronchodilator)
intrinsic
histamine = bronchoconstriction/inflammation
allergic reactions
CO2 = bronchodilator

diseases that increase airway resistance:
asthma =
treatment =
COPD =
emphysema =
chronic bronchitis =
treatment =
asthma = acute increase in airway resistance (histamine → inflammation)
treatment = bronchodilators/antiinflammatory corticosteroids
COPD = chronically increased airway resistances
emphysema = destruction of alveolar sacs. inflammation loss of tractive elasticity → small airways collapse
chronic bronchitis = inflammation, thickening of airway, fibrosis
treatment = same
RPD v. COPD:
problem =
how affect capacities and volumes
trouble breathing in or out
respiratory acidosis = ?
RPD = high recoil, can’t breathe in
volume/capacities decrease
COPD = high compliance, can’t breathe out
volume/capacities increase
respiratory acidosis = high CO2 → low pH
2 types of RPD:
interstitial pulmonary fibrosis (IPF) = ventilation/perfursion
what’s normal
extrapulmonary RPD
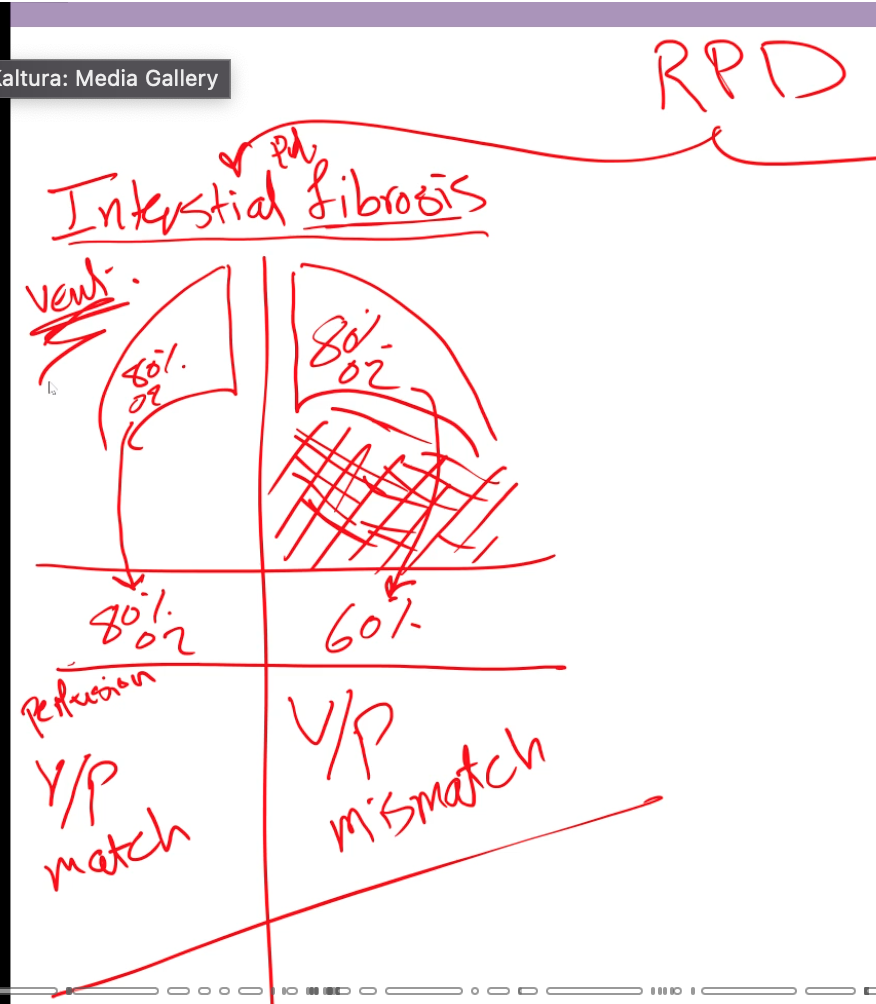
interstitial pulmonary fibrosis (IPF) = interstitian (area b/t tissue and capillary) is dead fibrosed
ventilation (lungs)/perfusion (blood vessel) mismatch
ex. ventilation (lungs) 60% O2 = blood vessel 20% O2
normally = ventilation/perfusion match
ventilation (lungs) 60% O2 = blood vessel 60% O2
extrapulmonary RPD = problem is outside lungs and prevents expansion
muscle, nerve, or abnormality
3 types of COPD:
untreated chronic asthma = permanent
asthma normally reversible unless untreated
chronic bronchitis = enlarged goblet cells over secreting mucus (smoking)
emphysema = destruction of alveolar sacs/ducts
cor pumonale:
what is it
how get it
heart disease where right side heart enlarged and eventually fails due to high pulmonary blood pressure
mech
COPD/RPD = less O2 → pulmonary hypertension → heart disease

spirometry:
purpose =
forced vital capacity FVC =
low indicates what
forced expiratory volume FEVx =
normal FEV1/FVC =
COPD FEV1/FVC = higher or lower
RPD FEV1/FVC = higher or lower
spirometry purpose = give FEV and FVC to calculate FEV1/FVC
FVC = max inhalation followed by max exhale as fast as possible
FEVx = % of FVC that can be exhaled w/in time frame “x” (we care about FEV1
normal FEV1/FVC = 80%
capable of exhaling 80% of FVC capacity in first second
COPD FEV1/FVC = less than 80%
both decrease, FEV1 decreases more
RPD FEV1/FVC = greater than 80%
both decrease, FVC decreases more

lung volumes =
lung capacities =
spirogram = shows what,
top of graph v bottom
peak expiratory flow rate PEFR =
normal for men / women
restrictive v obstructive
lung volume = cannot be subdivided
capacity sum of 2 or more volumes
spirogram = volumes and capacities (top of graph = exhale, bottom = inhale)
(PEFR) = computerized spirogram
men = 9L/sec, women = 7L/sec
both decrease PEFR, obstructive does more so

lung volumes (don’t memorize the #s):
tidal volume = n
inspiratory reserve volume IRV =
expiratory reserve volume ERV =
residual volume RV =
why important
tidal volume = normal breathe in and out, unforced
IRV = after normal breaking in, volume you can still inspire
don’t memorize the #
ERV = after normal breathing out, volume you can still expire
RV = volume left after ERV (cannot remove)
prevents airway collapse that would be hard to open again
inspiratory capacity IC =
vital capacity VC =
functional reserve capacity FRC =
total lung capacity TLC = 3 diff ways to calculate
what can’t you measure with a spirometer
IC = TV + IRV
VC = TV + IRV + ERV
FRC = ERV + RV
TLC = TV + IRV + ERV + RV
or IC + FRC, or VC + RV
spirometer can’t measure anything with RV in it

minute ventilation (Ve) =
same thing as _____
equation
alveolar ventilation (Va) =
equation
minute ventilation v. alveolar ventilation = specific?
minute ventilazioni (Ve) = total air V entering and leaving respiratory system each minute
same thing as pulmonary ventilation
Ve =Vt tidal volume (500mL) x RR
alveolar ventilation = volume of air reaching gas exchange areas per minute
Va = (Vt 500mL - DSV 150mL) x RR
alveolar ventilation = is specific for gas exchange (subtract dead space), minute is not! (both RZ and PZ included
2 ways to change alveolar ventilation:
change rate (RR) = proportional or not
change depth (TV) =
which is better
when do we adjust both?
low to moderate exercise =
intense exercise =
why changing depth not enough
exercise conditioning =
muscles v. lungs
change rate RR = proportional difference to alveolar ventilation
depth TV = not proportional difference
better/larger change
adjust both during exercise
low to moderate exercise = depth (TV) increase only (up to 65%)
intense exercise = add on a rate RR increase too
TV max change is 65% of VC
exercise conditioning = better contraction heart/respiratory muscles→ hypertrophy
muscles can change, can’t change lungs (TLC stays the same)
within systemic arterial blood, O2 and CO2 levels ______
O2 direction / rate
CO2 direction / rate
respiratory quotient =
what’s normal
how vary
where does deoxygenated blood and oxygenated blood begin in pulmonary circuit
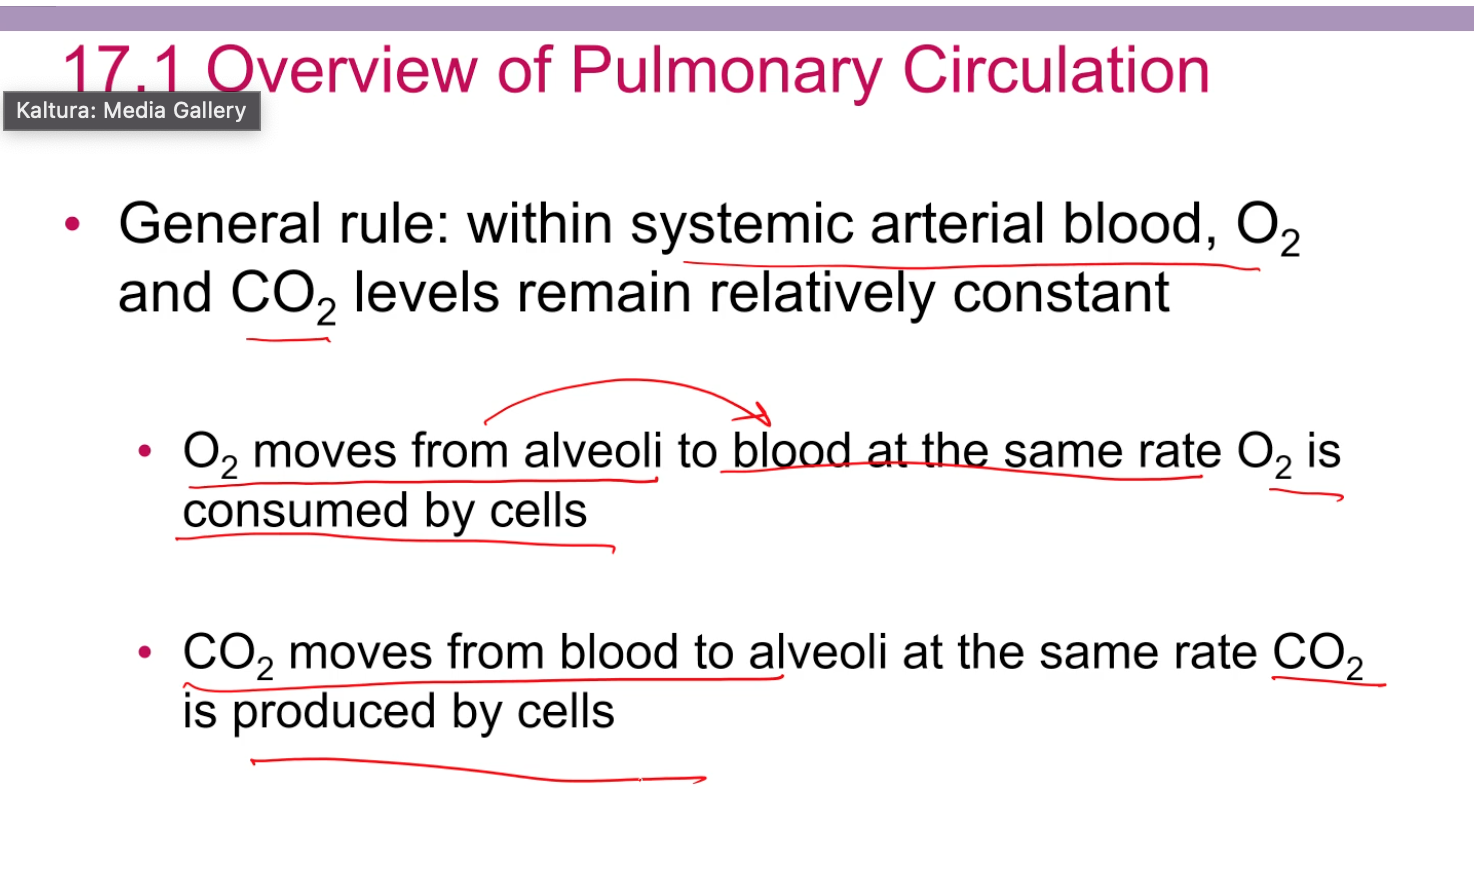
O2 and CO2 levels remain constant
O2 moves alveoli → blood at same rate O2 consumed by cells
CO2 moves blood → alveoli at same rate CO2 produced by cells
respiratory quotient = ratio CO2 consumed/O2 consumed
at rest = 200mLCo2/250mLO2 = .8
varies w/ diet
dox v ox
oxygenated begins in pulmonary capillaries after diffusion
deoxygenated begins in systemic capillaries after diffusion
respiratory membrane:
thickness/surface area?
structure
Type 1 epithelial cells =
fused basement membranes of the 2 cells
endothelial cells =
thin, large SA
type 1 epi cells = gas exchange, alveolar side
fused basement membranes of the 2 cells
endothelial cells = blood vessel side

gas exchange/diffusion:
what does diffusion in capillaries depend on
presence of other gases?
speed of diffusion
what third of capillary gas exchange /why
at rest v exercise
Dalton’s law
4 things pressure of gas (P) depends on
gases diffuse down partial pressure gradients high to low PP
presence of other gases irrelevant as gases diffuse down their own PP gradient
diffusion is rapid
location
first 1/3 of capillary = for at rest h
other 2/3 = needed during exercise
Dalton’s Law = PV = nRT, P depends on
V volume, n number of gas mCs, R universal rate constant, T temp

Total pressure of a gas mixture =
equation
Partial pressure of specific gas =
equation
partial pressures atmosphere v lungs
affect of humidity
why does gas exchange in lungs happen
Total pressure of a gas mixture = sum of pressures of all individual gasses
Total = P1 + P2…
Partial pressure of specific gas = proportion of Total that is due to an individual gas
Pgas = %gas x Ptotal
partial pressures atm v lungs =
Patm = PN2 + PO2 (CO2 neglible)
Lungs = PN2 + PO2 + PH2O
why does gas exchange in lungs happen
difference in gas partial pressures (higher in atmosphere) bc humidity in lungs lowers lung partial pressure, moves high to low
O2 and CO2 solubility:
at equilibrium, partial pressures of a gas in the air v. in solution =
mols?
comparing solubility of 2 diff gasses… which is more soluble?
partial pressure of gas in atm (vaporized) equals partial pressure of the same gas dissolved in solution
mols differ based on solubility
at equilibrium, gas w/ more mols in solution at the same partial pressure = more soluble

2 places gas exchange of O2 and CO2 happens:
lungs
pulmonary edema =
how affet difusion?
respiring tissues =
direction
what does amount of O2 and CO2 exchanged in a capillary bed depend on?
mixed veinous blood =
lungs
thickening of the thin respiratory membrane (pulmonary edema) slows diffusion
respiring tissues = in the cells
still high to low PP
amount of exchange depends on metabolic activity of cells
high metabolic activity = more active cells = more O2 and CO2
mixed veinous blood = systemic veins and pulmonary artery have same PO2 and PCO2
why is PP higher in air than in lungs?
2 groups of same PP = gas exchange?
2
3
partial pressures in cells/systemic tissue vary based on?
presence of water lowers PP of other gases
no difference in PP = no gas exchange
alveolar air (lung), pulmonary veins, systemic arteries = same PP
systemic cells, systemic veins and pulmonary arteries = same PP
vary based on metabolic activity

3 factors affect alveolar partial pressures
rate of alveolar ventilation = _____
3 factors affect alveolar partial pressures
PO2 and PCO2 of inspired air
minute alveolar ventilation
rate of metabolism
rate of alveolar ventilation = rate of metabolism
eupnea =
what PP changes
when
hyperpnea =
hypoventilation =
hyperventilation =
eupnea = normal ventilation matches cellular demand
hyperpnea = increased ventilation due to increased cellular demand (exercise)
minimal change in arterial PO2 and PCO2
hypoventilation = ventilation doesn’t meet cellular demands
arterial PO2 decrease, PCO2 increase
hyperventilation (panic) = ventilation exceeds cellular demands
arterial PO2 increases, PCO2 decreases

2 forms of O2 transport in blood = what %
oxyhemoglobin v deoxyhemoglobin
path from air
path from
total O2 in blood = 1.5% O2 dissolved, 98.5% O2 transported by hemoglobin
oxyhemoglobin (Hb-O2) v deoxyhemoglobin (Hb + O2) = whether bonded to O2 or not
alveoli: alveolar air → plasma → RBC → Hb + O2 → Hb-O2
systemic capillaries: Hb-O2 → Hb + O2 (RBC) → plasma → tissue
what binds / how many
heme =
globin =
Hb saturation =
% saturation relationship to PP
arterial blood v. mixed venous blood % saturation
how O2 bind Hb =
law of ___
what binds
heme = 4 O2, CO
globin = CO2
Hb saturation = 4 O2 on 1 Hb
higher PP = more % at saturation
arterial = 99% saturation
mixed venous = 75% saturated
O2 bind Hb = nonlinear + cooperativity
more O2 → more O2 binding. easier for to bind 2nd than 1st, easier to bind 3rd than 2nd, etc..
law of mass action
why doe knowing Hb amount (hematocrit) matter?
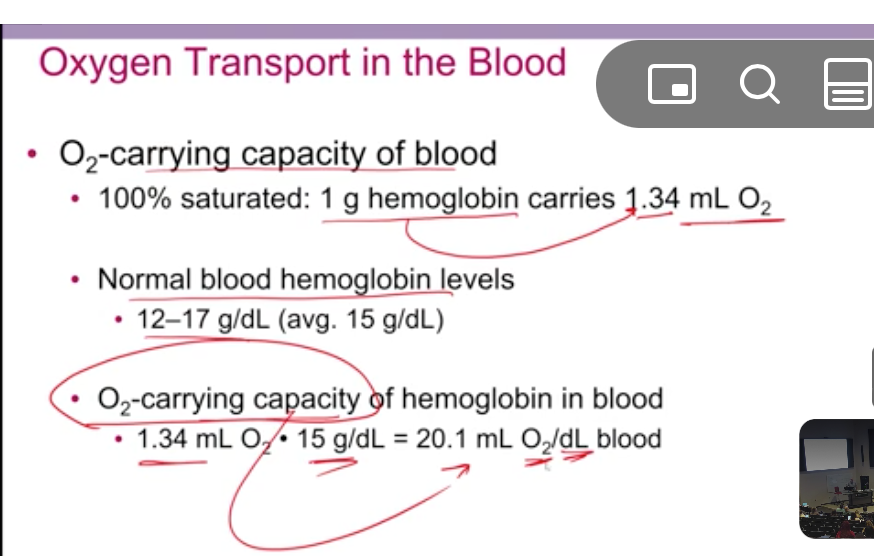
calculate O2 carrying capacity
Hb determines O2 carrying capacity
calculate
multiply amount of O2 1g of 100% saturated Hb carries (1.34mL O2) by hemoglobin levels
HB-oxygen dissociation curve
shows what
moving right vs. left affect on affinity
at rest systemic arterial blood v. systemic venous blood
% saturated
affinity high or low
more unloading or loading
Hb affinity for O2
move
left = high affinity, association (holding onto O2)
right = low affinity, dissociaiton (easily give O2)
at rest
systemic arterial blood Hb: 98.5% saturated, less affinity (more unloading)
systemic venous blood Hb: 75% saturated, higher affinity (more loading)
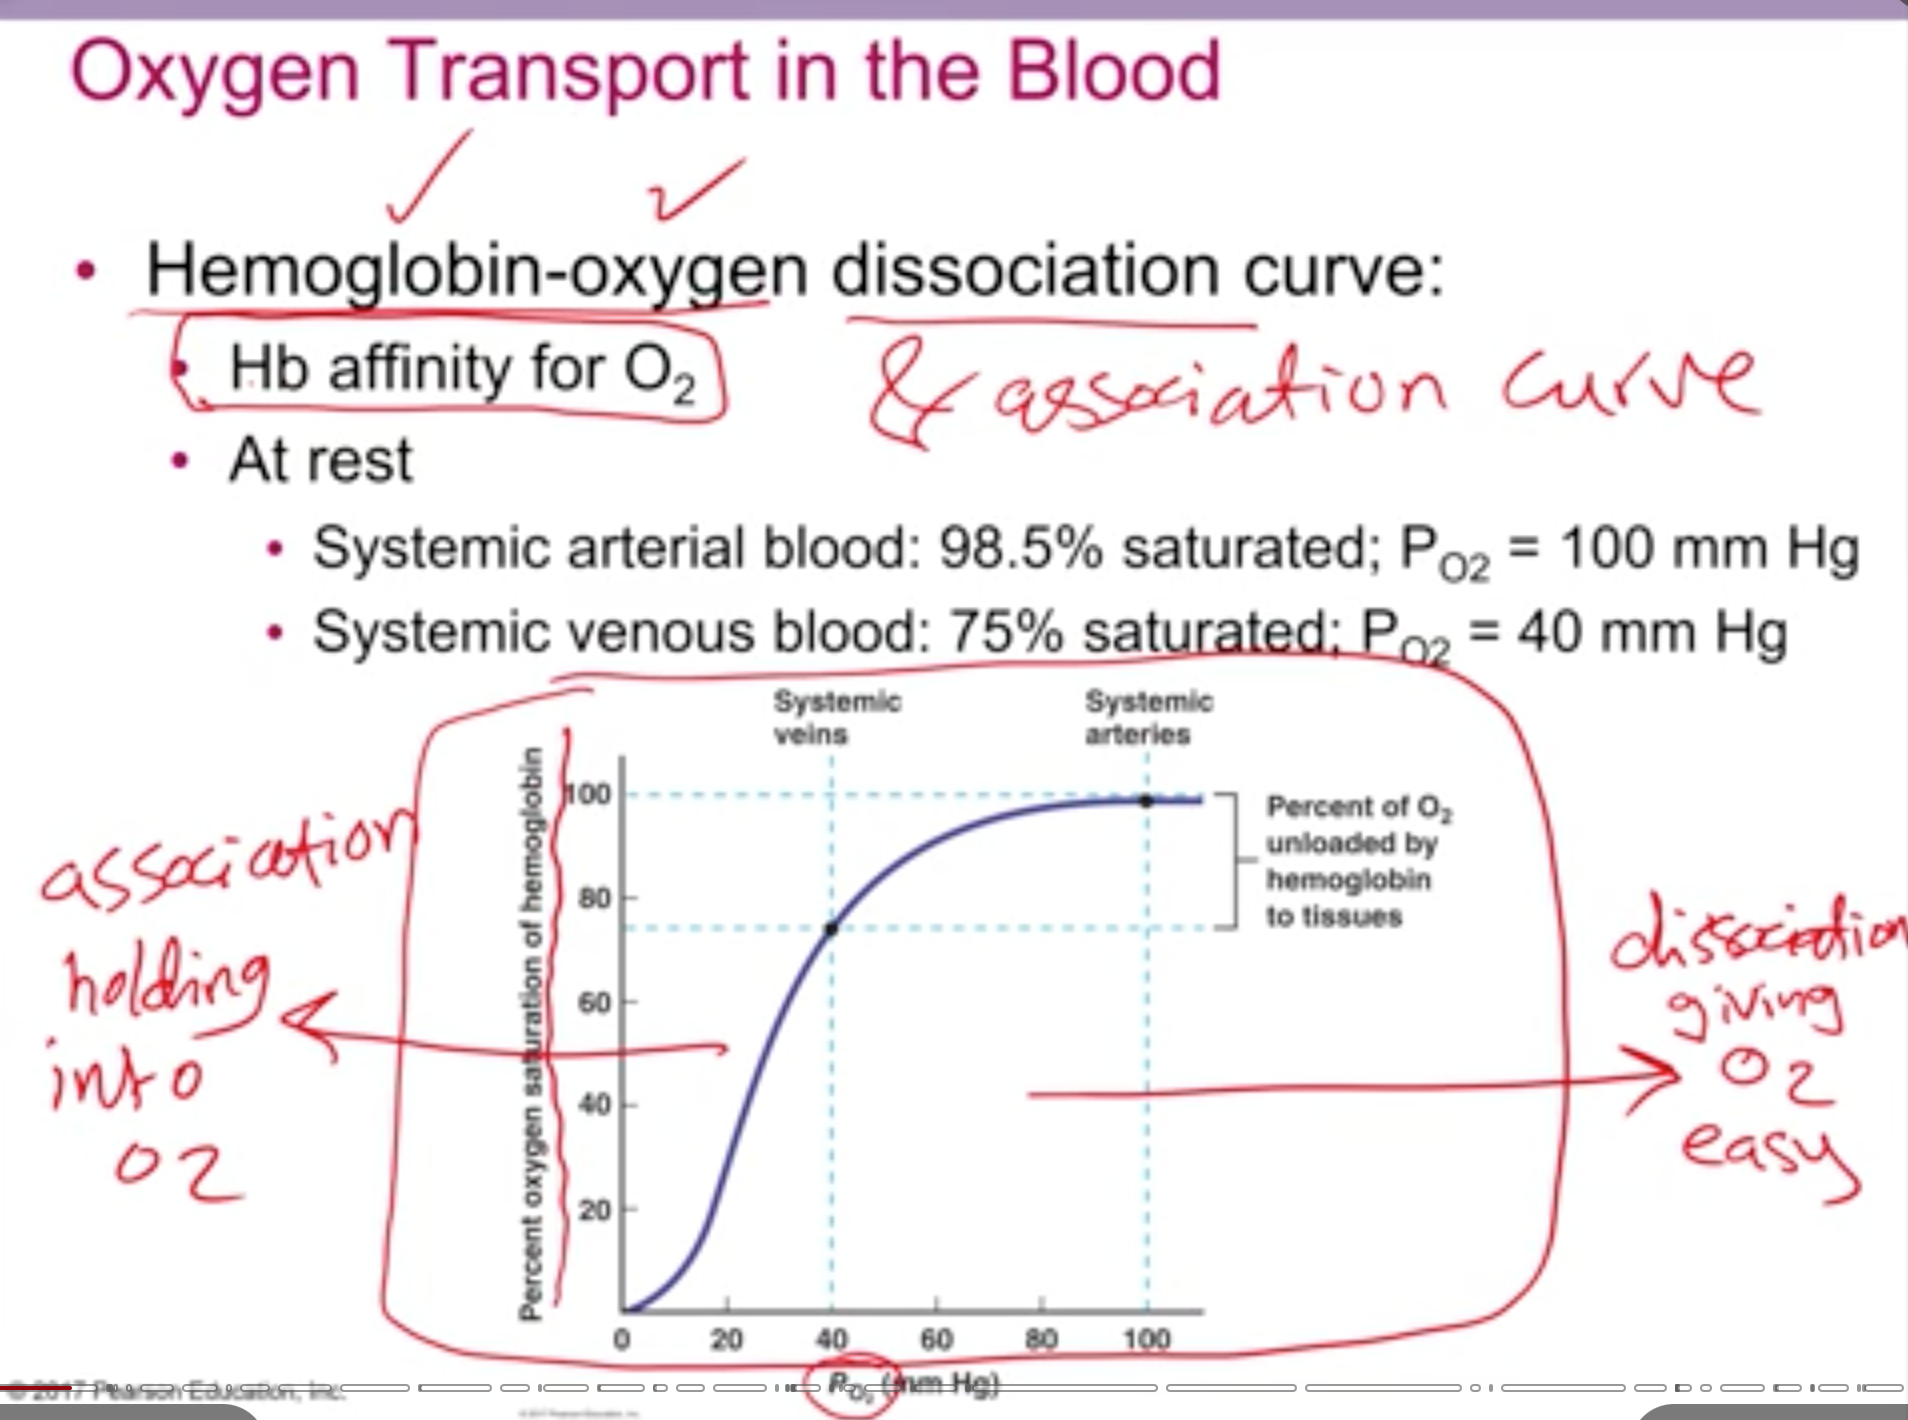
Hb-Oxygen association/dissociation curve:
how curve shift
high Temp =
why high temp occur =
low pH =
Bohr affect =
high CO2 =
carb amino affect =
high 2,3-BPG =
when/why produced =
CO =
asphyxiation v. suffocation
high Temp = shift right
high bc of metabolic activity
low pH = (Bohr affect) shift right
metabolic acids from high activity
high CO2 = shift right
carb amino affect = carbaminohemoglobin has lower O2 affinity
high 2,3-BPG = shift right
produced in RBC during hypoxia
CO = shift left
binds tighter to heme than O2 = lack of O2 = asphyxiation
suffocation = preventing ventilation
3 forms CO2 transported in blood
carbaminohemoglobin =
why?
carbonic anhydrase reaction =
law of mass action =
CO2
5% dissolved in plasma
5% on globin portion of hemoglobin
“carbaminohemoglobin” when binded
90% dissolved in plasma as bicarbonate HCO3-
mainly as bicarbonate bc RBC has carbonic anhydrase enzyme
CO2 + H20 ←(carbonic anhydrase)→ H2CO3 (carbonic acid) ←> H+ + HCO3- (bicarbonate)
law of mass action = increase in CO2 causes increase of bicarbonate and H+

CO2 exchange in blood:
steps
free H+ v. bound H+
tissue to blood
cells → plasma (5% CO2 stays)→ RBC: carbonic anhydrase and H20 = HCO3- + H+
the H+ ‘s made bind hemoglobin
the HCO3- made moves out of RBC (90% CO2 stays) in exchange for Cl-
remaining CO2 binds hemoglobin (5%)
blood to alveoli
pic (reverse)
free h+ lowers pH, bound H+ doesn’t

Haldane effect =
tissue capillaries v. lung capillaries
Bohr affect =
carb amino affect =
systemic tissue v alveoli = O2/CO2 loading/unloading
Haldane effect = inverse relationship, high PO2 → low CO2
tissue cap = high Hb CO2 affinity (low PO2)
lung = low Hb CO2 affinity (high Po2)
Bohr affect = low pH (high Co2/H+) → low O2 affinity
carb amino affect = CO2 direct bind Hb into carbaminohemoglobin
systemic tissue = O2 unloading, CO2 loading
alveoli = O2 loading, CO2 unloading
acid-base disturbances in blood
what blood do you normally test for this
normal pH
lethal range
what systems regulate pH/how
affect small changes of pH/why
arterial blood
normal = 7.4 (7.35-7.45)
below 6.8 or above 8 are lethal
respiratory and renal system regulate pH
lungs = CO2
renal = HCO3
small change = big affects bc alter protein activity
acid-base disturbances in blood:
how calculate pH
normal pH, HCO3, CO2 levels
pH disturbances = which is faster
metabolic vs respiratory
hyper v hypoventilating
alkalosis/alkalemia =
2 cause
effect
acidosis/acidemia =
2 cause
effect
pH = HCO3-/CO2
pH 7.35-7.45, HCO3 22-26, CO2 35-45
pH disturbances
metabolic = HCO3 is the problem (kidney)
respiratory = CO2 is the problem (lungs)
faster
respiratory alkalosis = hyperventilation
respiratory acidosis = hypoventeniation
alkalosis/alkalemia = above 7.45
cause = HCO3- increase or CO2 decrease
acidosis/acidemia = below 7.35
cause = HCO3- dec or CO2 inc
acid-base disturbances in blood:
5 steps to figure out which type of acidosis/alkilosis
steps
alkalosis or acidoses = pH high or low
example = given high pH, alkalosis
determine 2 possible causes of the pH
example alkalosis = high HCO3 or low CO2
determine if actual HCO3 and CO2 values are high low or normal
compare possible cause to actual value. if match = that’s the reason for the pH
determine compensation if applicable = following the problem to fix it


acid-base disturbances in blood:
what type is…
PH 7.2, CO2 50, HCO3 24
PH 7.6, CO2 40, HCO3 30
PH 7.2, CO2 50, HCO3 20
PH 7.6, CO2 30, HOC3 20
PH 7.2, HCO3 20, CO2 30
is subject hyper or hypoventilating
PH 7.2, CO2 50, HCO3 24
resp acidosis
PH 7.6, CO2 40, HCO3 30
met alkalosis
PH 7.2, CO2 50, HCO3 20
resp met acidosis
PH 7.6, CO2 30, HOC3 20
resp alkalosis w/ met compensation
PH 7.2, HCO3 20, CO2 30
met acidosis w/ resp compensation
hyperventilating (getting rid of CO2)

4 urinary system structures
macro kidney anatomy
renal capsule
renal cortex
renal medulla =
renal pelvis =
renal hilus =
4 urinary system structures
2 kidneys, 2 ureters, bladder, urethra
macro kidney anatomy
renal medulla = nephrons and collecting ducts
renal pelvis = cavity
renal hilus = where BVs exit kidney (afferent and efferent arterioles)
nephrons:
2 types
cortical
juxtamedullary renal corpuscle =
parts
renal corpuscle =
glomerulus = afferent arteriole, efferent arteriole, filtrate
bowman’s capsule
nephron tubules =
proximal tubule
loop of Henle =
distal convoluted tubule =
collecting duct =
2 types
cortical = most common, short loop of Henle
juxtamedullary = long loop of Henle
nephron parts
renal corpuscle = 1st, receives filtrate gives it to proximal tubule
glomerulus = afferent arteriole, efferent arteriole, filtrate
bowman’s capsule
nephron tubules =
proximal tubule
loop of Henle = reabsorb water (concentrate urine)
distal convoluted tubule =
collecting duct = not part of nephron
juxtaglomerular apparatus:
where
macula densa =
granular cell =
juxtaglomerular apparatus = b/t afferent arteriole (entrance) and efferent arteriole (exit)
macula densa = cells that screen filtrate in distal tubule
granular cells = secrete renin when low BP or low flow to kidney
5 steps blood flow in nephron
before (BV) =
nephron
mowman’s capsule =
PCT =
loop of Henle =
DCT =
collecting duct =
before =
new blood (filtrate) enters via afferent arteriole → diffuses into Bowmans capsule → filtered blood exits through efferent arteriole
nephron
Bowmans capsule = 1st part, engulf capillaries
PCT = reabsorb H2O
loop of Henle = reabsorb water
descending then ascending
DCT = where filtrate is monitored by macula dense in b/t afferent and efferent arterioles
collecting duct = hormones work (ADH)

filtration =
how increase/dec?
reabsorption =
tubule v. plasma?
blood osmolarity?
secretion =
excretion =
difference b/t filtration and excretion tell us____
if filtered 80 units and excreted 120, ____
if filtered 80 and excreted 60, ____
filtration = bulk flow glomerular capillaries (glomerulus) → bowman’s capsule
increase = dilate afferent, constrict efferent
reabsorption = nephron (tubule)→ blood (plasma)
secretion = blood (plasma→ back to nephron (tubule)
excretion = what exits outside body
tells us how much was secreted v reabsorbed
40 units secreted
20 units reabsorbed
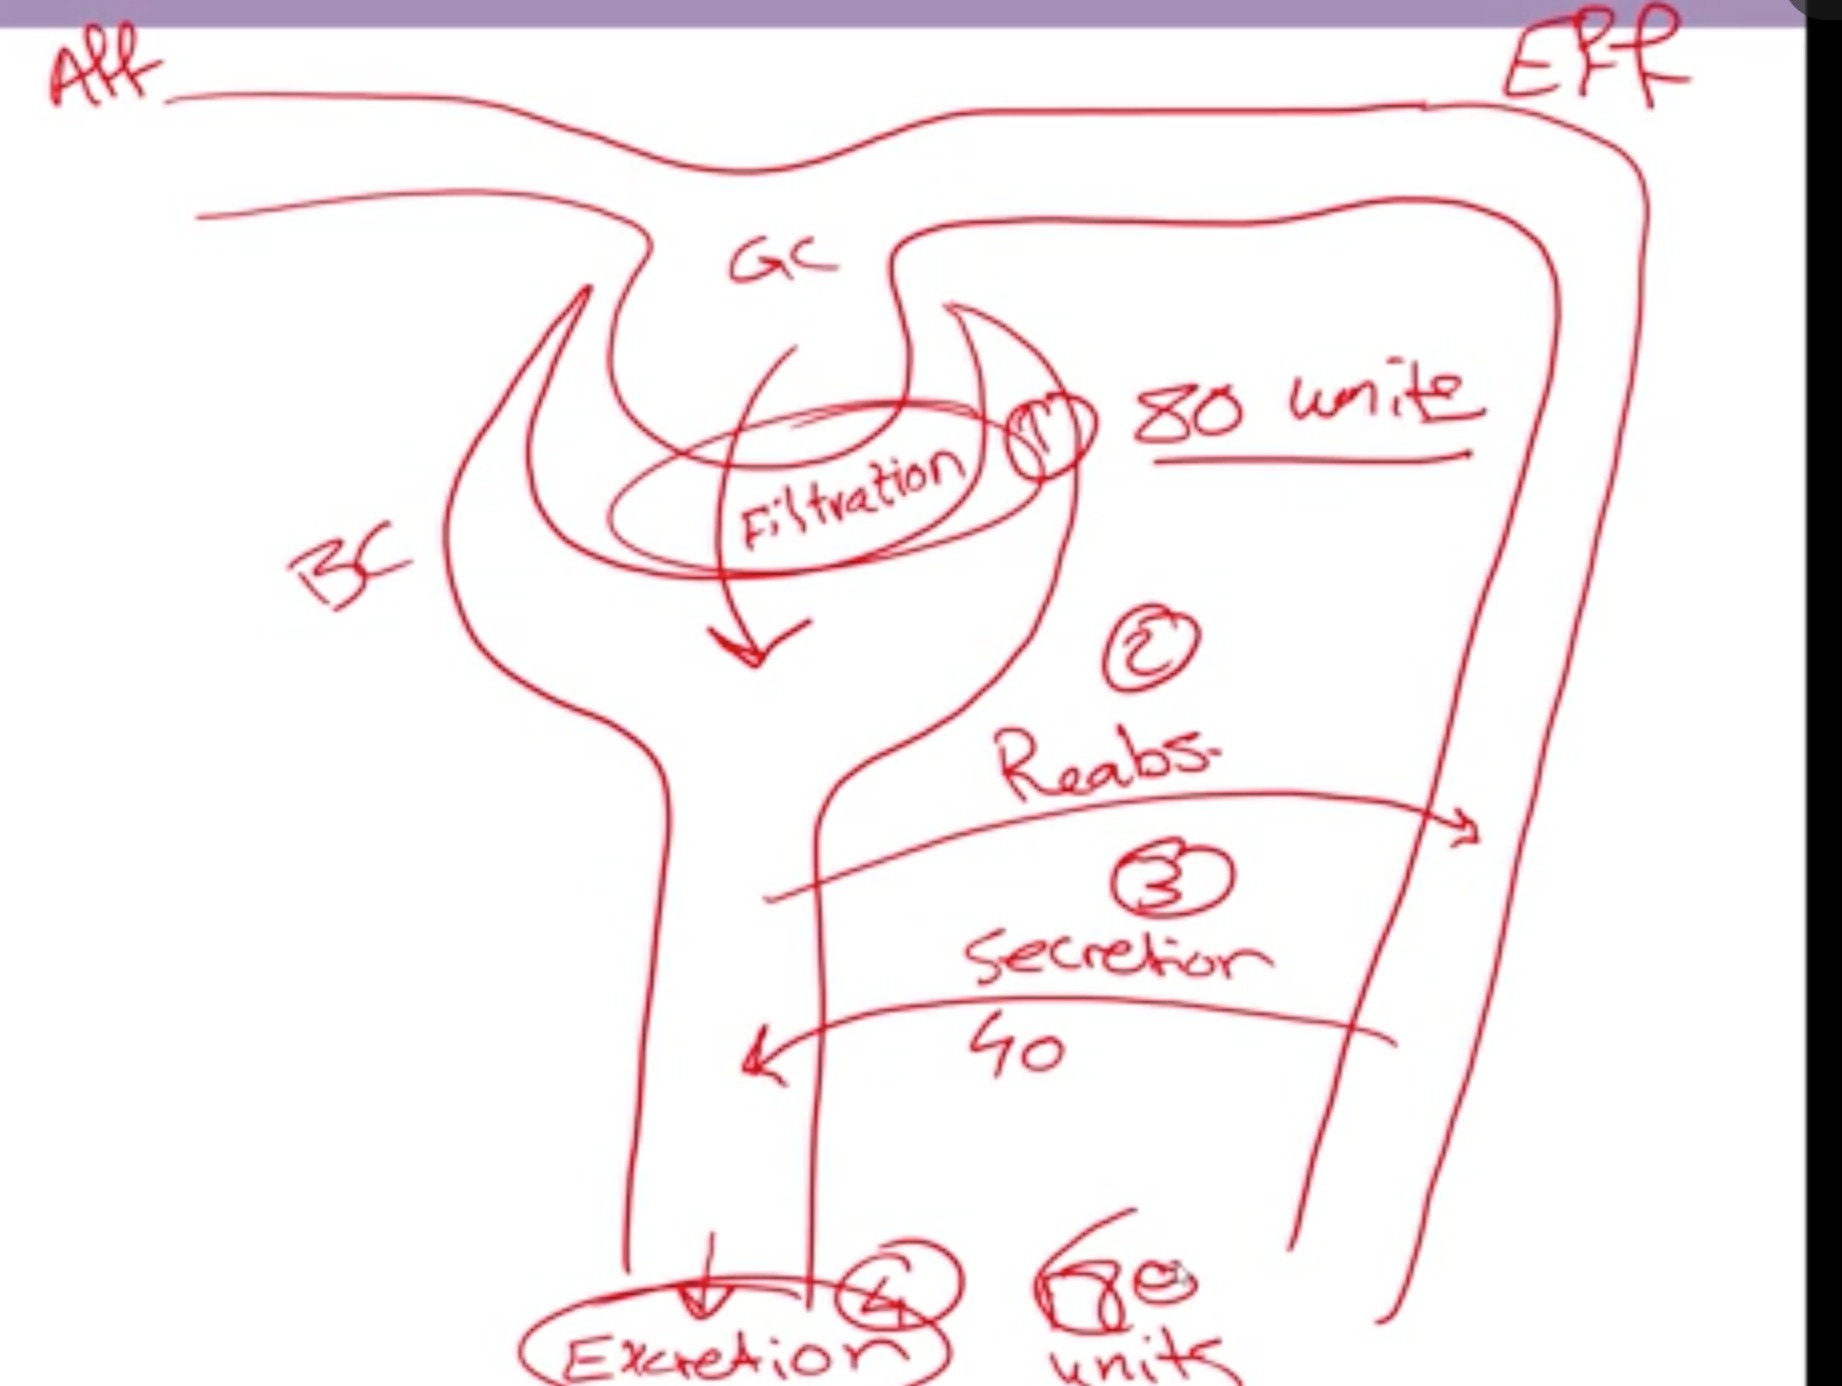
nephron:
osmolarity vs. specific gravity
plasma v tubule
reabsorption v secretion
reabsorption = tubule (nephron) → plasma (blood)
secretion = plasma → tubule
osmolarity = concentration of solute in blood plasma
specific gravity = concentration of solute in urine
glomerular filtration:
what can be filtered
glomerular filtration rate GFR =
why don’t we pee that much
total plasma volume filtered every
3 layers glomerular filtration membrane:
protein-free plasma (proteins too large to be filtered)
GFR 100 mL/min but 99% is reabsorbed so we aren’t peeing all the time
total plasma volume filtered ever 22 minutes
3 layers
capillary endothelial layer
basement membrane connecting 2 layers
capsule epithelial layer
glomerular starling forces:
hydrostatic pressures
Pgc (glomerular capillaries)
Pbc (bowman’s capsule)
oncotic pressures
piGC
piBC
which is normally 0, why?
which 2 are filtering forces?
what is the net starling force across nephron
piBC = 0 bc proteins can’t be filtered
Pgc and piBC are filtering forces, other 2 are against filtration
60 (filtering) - 44 (against filtering) = 16 mm Hg favoring filtration

filtration fraction =
equation
what does it mean
filtered load =
equation
concentration in plasma = ____
filtration fraction = how much blood to kidney is filtered
filtration fraction = GFR/renal plasma flow = 125mL/625 = 20%
filtered load = quantity of solute filtered per unit time
filtered load = GFR x Px
Px = concentration of filtrate in plasma
concentration in plasma = concentration in filtrate

Regulation of GFR:
dilattion of aff/constriction of off = ____
GFR depends on _____
MAP v. GFR plot:
MAP range where GFR is maintained
what happens above/below
= higher Pgc = more filtration = higher GFR
higher MAP = higher Pgc = higher GFR
MAP → GFR, maintain MAP to maintain GFR
MAP v. GFR plot
GFR constant (125mL) when MAP b/t 80-180
MAP > 180, GFR raises
MAP < 180, GFR decreases
intrinsic control of GFR:
when
3 types
myogenic regulation = triggered by what
what happens
tuboglomerular feedback =
mesangial cells =
intrinsic regulation of GFR = maintain GFR
3 types
myogenic regulation = triggered by high MAP stretching afferent arteriole
vasoconstrict afferent arteriole to lower MAP/GFR
tuboglomerular feedback = triggered by macula dense detecting high Na+ in DCT (high Na+ = high water volume)
vasoconstrict afferent arteriole to lower MAP/GFR
mesangial cells = triggered by stretching capillaries
mesangial cells act like precapillary sphincter that constrict around glomerular capillaries to decrease their surface area
extrinsic control of GFR:
via what/when
detected by what
neural pathway
what happens when:
high MAP
low map
if bleeding
extrinsic control = via sympathetic nervous system when intrinsic mech can’t correct
baroreceptors detect stretch in aorta/carotid
baroreceptors -CN 9→ CNS -CN10→ heart
high map = baroreceptors in aorta/carotid fire → decrease sympathetic activity
low map = baroreceptors in aorta/carotid fire → increase sympathetic activity (constrict afferent arteriole) → lower GFR
bleeding = increase sympathetic → lower GFR to maintain flow to other places
ADH/vasopressin =
secreted by
what receptors/do what
when secreted
aldosterone =
secreted by
ANP =
secreted by
ADH = maintain water balance (kidneys reabsorb water)
made by hypothalamus, stored/realesed from posterior pituitary
osmoreceptors = detect osmolarity of plasma
secreted when osmoreceptors detect thick blood (concentrated plasma)
aldosterone = raises Na+, lowers K+
made by zona glomerulosa of adrenal cortex
ANP = stop reabsorbing Na+, lowering blood volume and BP
secreted by atrium when walls stretch due to high BP
reabsorption:
what / how move
mostly happens where
2 reasons
how much glucose
path
water/solutes (protein free plasma)
mostly move high to low concentration gradient, some bc of hormonal control
mostly proximal convoluted tubule (PCT), some DCT
100% glucose reabsorbed (should not be in urine)
pathway:
lumen of tubule → epithelial cells → basement membrane → peritubular space (renal interstitial fluid) → basement membrane → endothelial cells of capillaries → plasma of capillary
tubule → epi, mem → p-space → mem,endo,→ plasma
mechanisms of solute reabsorption:
how water move =
effect on concentration of filtrate/plasma?
active solute reabsorption =
primary active =
secondary active =
passive solute reabsorption =
reabsorbing sodium only,
water moves low to high osmolarity (follows solute)
. if high Na+ outside, H2o goes out
reabsorption concentrates filtrate (water leaves tubule), and dilutes plasma (water enters plasma)
active solute reabsorption = uses transporters
primary active = direct use of ATP against gradient
secondary active = facilitated diffusion down ATP established gradient
passive solute reabsorption = high to low concentration
transport maximum (Tm) =
what happens at Tm?
renal threshold =
applies to what solute
glucose =
glucose has a ____ and ___
normally filtered/absorbed?
glucose normally ___ filtered/ ____ reabsorbed where?
what does glucose in urine mean?
is glucose actually 100% reabsorbed?
transport maximum = rate of transport when carriers are saturated
if carrier saturated, excess solute is excreted (urine)
renal threshold = solute concentration in plasma that causes Tm
glucose = 180 mg/dL ( for solutes normally 100% absorbed)
glucose has both transport maximum and renal threshold
glucose normally freely filtered at glom and 100% reabsorbed at PCT
glucose in urine means transporters are saturated bc blood glucose is high (above 180
glucose 100% reabsorbed up to 180

Reabsportion:
apical membrane =
basolateral membrane =
solutes
glucose = transport across apical/basolateral membranes
apical membrane = b/t tubule and epithelial cells
basolateral membrane = b/t epithelial cells and peritubule space
glucose
apical = 2ndry active w/ Na+ (symported)
baso = facilitated diffusion
regional specialization of renal tubules:
PCT (majority) = what type of reabsorption
what does it reabsorb/secrete
DCT =
loop of Henle =
CD =
PCT (majority) = non regulated absorption
reab everything, secrete H+
DCT = regulated absorption
reab water (in descending)
loop of Henle = water conservation
reab Na+ and water, secrete H+ and K+
CD = regulated absorption
reab Na+ and water, secrete H+ and K+
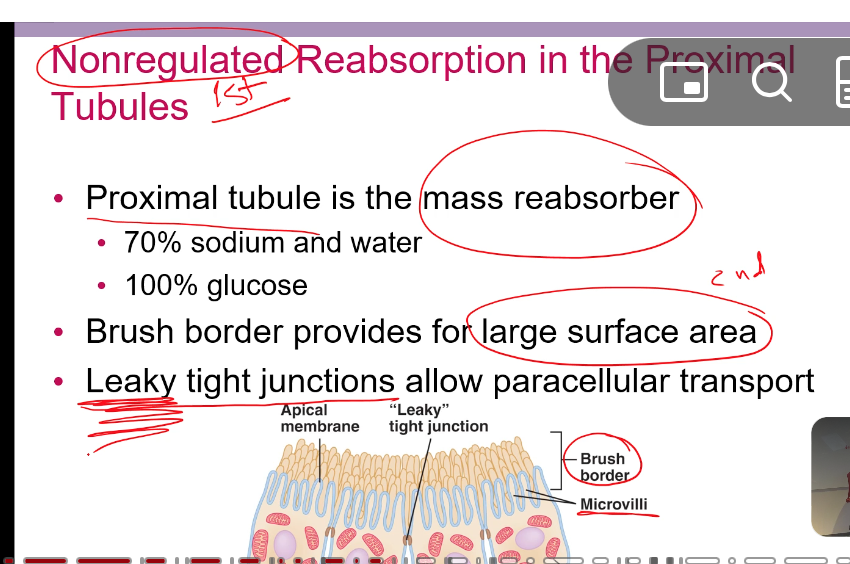
non regulated reabsorption = where
mass reabsorber =
3 reasons why
brush border?
tight junctions?
regulated reabsorption =
tight junctions?
transport via
transport how?
water conservation =
purpose
juxtamedullary nephron =
CD?
non regulated reabsorption = PCT
mass reabsorber = PCT bc
non regulated = no need for hormone
has brush borders = large SA
leaky tight junctions
regulated reabsorption = DCT and CD
transport through cells
tight junctions = limit paracellular transport (b/t adjacent cells)
transport = specific and directed reab/secretion
water conservation = loop of henle and CD
concentrate urine
juxtamedullary nephron = bc longer loop of henle
excretion:
what is it
equation
3 factors that determine
what excretion rate is less than filtered load? (E<F)
what if F>E
excretion = how much of substance released in urine
E = F + S - R
amount filtered + amount sec - amount reab
3 factors = filtered load, secretion rate, reabsopriotn rate
E < F. solute reabsorbed. E>F, solute secreted

clearance:
what is it
equation
Ux , V , Px
clearance = volume of plasma from which a substance has been removed by kidneys per unit time
clearance = (Ux x V) / Px = excretion rate / plasma concentration
Ux = [solute] in urine
V = volume of urine
Px = [solute] in plasma
to estimate GFR
clearance:
clinical use
how does it work?
inulin?
what’s the problem w/ inulin
what do we use instead now?
estimate GFR
inulin allows GFR estimation bc it is freely filtered substance (inulin) that isn’t secreted or reabsorbed
that means inulin F = inulin E, which makes clearance = GFR
inulin problem = body doesn’t make it
we use creatinine instead but it a small amount is secreted, so estimated value is slightly higher than GFR

clearance:
if C < GFR, ____
if C > GFR, ____
glucose clearance (freely filtered/completely reabsorbed) =
PAH clearance (freely filtered/not reabsorbed/fully secreted) =
why
if C < GFR, must have reabsorbed
if C > GFR, must have secreted
glucose clearance = 0 mL/min
PAH clearance = renal plasma flow
bc filtered, not reabsorbed, and fully secreted
whatever kidneys get will be excreted
inulin
freely filtered?
reabsorbed?
secreted?
excretion (E)?
creatinine
glucose
PAH
estimate for ___
K+
Cl-
Na+
inulin = FF yes, S no, E = F
creatinine = FF yes, R no, S a little, E a little > F
glucose = FF yes, R 100% up to 180, S no, E = 0
PAH = FF yes, R no, S 100%, E > GFR and E = renal plasma flow
PAH = renal plasma flow
micturition:
urine pathway
detrusor muscle?
internal v. external urethral sphincter
formed in nephrons, ends up in CD
1 CD collects from multiple nephrons
drains into renal pelvis → ureter → bladder
bladder has detrusor muscle = smooth muscle (ANS control)
bladder → urethra → internal urethral sphincter → external ureth sphinct
internal = smooth muscle (ANS control)
external = skeletal muscle (SNS)
how to tell if any sphincter is smooth muscle or skeletal?
ask “is it closer to the inside or outside of my body”
closer to inside = always smooth
closer to outside = always skeletal
micturition reflex:
what is it =
override?
what kind of reflex =
involuntary control
detrusor muscle = how innervated
internal urethral sphincter = how innervated
voluntary control
external urethral sphincter = how innervated
micturition reflex = urination
spinal reflex w/ voluntary override
override = have control up to a certain point and then autonomic takes over and urination happen
involuntary control
detrusor muscle = parasympathetic innervation
internal urethral sphincter = sympathetic innerv
voluntary control
external urethral sphincter = somatic motor control

micturition reflex:
what do you have voluntary control over?
valsava maneuver
have control over stopping micturition
valsava maneuver = abdominal cavity compression helps stimulate micturition
Sodium balance:
where is it mainly
critical for
regulated or unregulated?
2 hormones involved
secretion? how get rid of?
hyperatremia v. hypoatremia
Na+ primary solute in ECF (outside cell)
critical for osmotic pressure/excitable cells
both
unregulated = co and counter transport across PCT apical membrane
regulated = Na+ and K+ channels both regulated and unregulated (DCT and CD)
hormones = aldosterone and ANP
no Na+ secretion = have to stop reabsorbtion to lessen
hyperatremia = high plasma osmolarity (concentration) , cells shrink
hypo = low plasma osmolarity, cells bulge
aldosterone:
what is it
what does it do
apical/basomembrane
what stimulates its release
ANP:
what is it
what does it do
how
steroid hormone secreted by adrenal cortex
increases sodium reabsorption / K+ secretion
apical membrane = inc open Na+/K+ channels
basolateral membrane = inc Na+/K+ pumps
low plasma Na+ or high K+ = aldosterone release
reabsorb Na+
secreted by atrial cells of heart in response to distension of atrial wall
increase Na+ excretion
increases GFR (dilate aff art, constrict eff art)
decrease Na+ reab (close apical membrane Na+ channelS)
K+ and function of excitable cells:
how regulated?
principal cells =
hyperalkemia v hypoalkemia
polarize?
excitable?
how excite cells?
directly regulated by aldosterone = high K+ → aldosterone release → secrete K+
principal cells = active secretion of K+ in DCT
hyperalemia = high plasma K+
K+ enters cell, depolarizes but difficult to repolarize
cell less excitable bc sustained K+ in cell
hypoalemia = low plasma K+
K+ leaves cell, hyperpolarizes
cell less excitable
have to keep K+ normal, too high or too low = less excitable
renin-angiotensin-aldosterone system (RAAS):
3 ways triggers renin release:
low pressure and flow reaching kidney
low MAP in aff arteriole
baroreceptor reflex
macula densa detect low Na+ and Cl- in distal tubule filtrate
RAAS:
triggered by
4 steps mech
triggered low pressure and flow reaching kidney
low MAP in aff arteriole
baroreceptor reflex
low GFR = macula densa detect low Na+ and Cl- in distal tubule filtrate
mech
liver secretes angiotensinogen (inactive)
juxtaglomerular cells in kidney afferent arteriole secrete renin in response to low kidney MAP/flow
renin converts angiotensinogen → angiotensin 1
lung provide angiotensinconverting enzyme (ACE) converts angiotensin 1 → angiotensin 2
angiotensin 2:
4 effects
raises MAP
vasoconstriction = sympathetic
stimulate aldosterone release
adding volume
stimulate hypothalamus for ADH release + thirst
add volume
calcium:
why important
hyper calcemia v hypocalcemia
low or high excitability/why
2 hormones
calcitonin
parathyroid hormone
exocytosis, secretion, and excitation/contraction
calcemia
hyper calcemia = low excitability bc raises Na+ channels activation threshold (needs more depol)
hypo calcemia = high excitability bc lowers activation threshold
hormones =
calcitonin = lowers Ca+
secreted by thyroid gland
parathyroid hormone = raises Ca
secreted by
calcium balance:
what controls
3 ways to get Ca+
vitamin D
resorption
calcification
PTH
kidney regulates
how to get Ca+
need vitamin D to absorb Ca+ in digestive tract
bone
resorption = breakdown bone release Ca+
calcification = calcitonin add Ca+ to bone
parathyroid hormone stimulates kidney reabsorb Ca+