Hormones
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/39

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
40 Terms
biopharmaceuticals
Recombinant products and nucleic acids ← genetically engineered as cell-based products (made in an organism)
genetically engineered as cell-based products
categories of biopharmaceuticals
recombinant clotting factors
recombinant thrombolytics
anticoagulants and other blood-related products
recombinant hormones
recombinant growth factors
recombinant interferons, interleukins and tumor necrosis factor
vaccines
monoclonal-antibody-based products
biologics
produced by living cell cultures
high MW
complex, heterogenous structure
strongly process-dependent
not entirely characterizable
unstable
immunogenic
ex. insulin
small molecule drugs
produced by chemical processes
low MW
well-defined structure
mostly process dependent
completely characterizable
stable
nonimmunogenic
ex. Piroxicam
hormones
chemical or polypeptide protein released by a cell or a gland that
modifies the function and metabolism of other cells in the body
endocrine vs exocrine glands
endocrine
secrete into blood
exocrine
secretion through ducts
hormones function by
binding to receptors on the cell surface or inside the cell
hormones classified as
peptide (e.g., insulin) or nonpeptide (e.g., progesterone, estrogen) hormones
peptide hormones
purified from animal sources or human sources
If from animals → can have animal proteins or be contaminated
Smaller peptides can be chemically synthesized → most protein hormones are recombinant
non-peptide / recombinant / synthetic hormones
— is the first recombinant hormone
insulin
why difficult to administer insulin by oral route?
degraded by enzymes in GI tract
insulin
produce —% pure insulin
structure
Produce >98% pure insulin
Structure:
Small 51 AA protein secreted by beta cells in pancreas (has A and B chain)

insulin association
insulin monomer becomes dimer w/ increased concentration
dimer becomes hexamer w/ addtion of zinc (bind)
w/ phenolic preservative, becomes longer acting
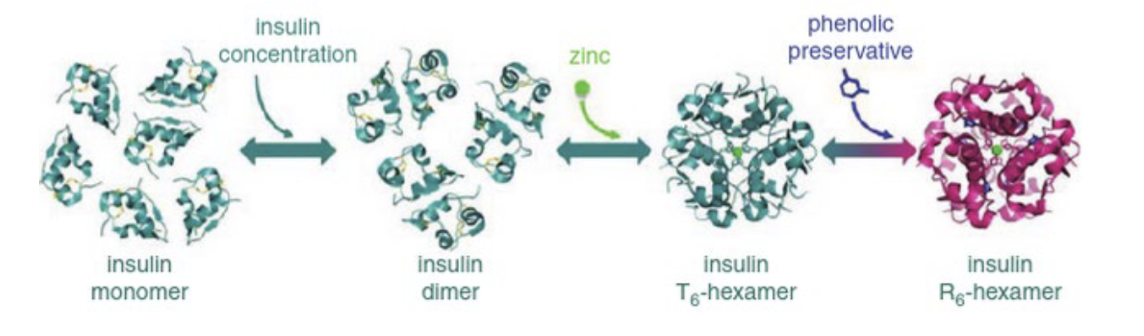
insulin analogs
ultra rapid (monomers)
rapid (monomers)
short acting (monomers)
intermediate acting (dimers)
long acting (hexamers)
insulin analogs
ultra rapid
Insulin apart (Fiasp)
Insulin lispro (Lyumjev)
Insulin oral inhaled (Afrezza)
→ shortest; no buffer/preservative
insulin analogs
rapid
Insulin aspart (Novolog)
Insulin lispro (Humalog, Admelog, Liprolog)
Insulin glulisine (Apidra)
insulin analogs
short acting
Insulin regular
(Humalin R, Novolin R)
insulin analogs
intermediate acting
Insulin NPH (Humalin N, Novolin N)
insulin analogs
long acting
Insulin glargine (Lantus; Basaglar; Toujeo; Semglee, Rezvoglar)
Insulin degludec (Tresiba)
rapid onset and short DOA insulin preparations
insulin aspart
insulin lispro
insulin glulisine
insulin (afrezza) — oral inhalation
insulin regular
intermediate onset and duration
isophane insulin (NPH)
prolonged duration
insulin degludec
insulin detemir
insulin efsitora alfa
insulin glargine
insulin icodec
solution products
regular insulin
insulin lispro (Humalog, Admelog, Liprolog)
insulin aspart (Fiasp)
insulin glulisine (Apidra)
only inhaled insulin
Afrezza (ultra-rapid)
preparation for ultra-rapid insulin
2 types of pumps (traditional and patch)
basal insulin suspension preparations
insulin NPH
modifying protein: protamine
all cloudy appearance
basal insulin solution preparation
insulin glargine (Lantus, Basaglar, Toujeo)
insulin degludec (Tresiba)
2 new products of basal insulin solution preparation
Insulin Efsitora alfa (Onswik)
time to peak: 3 - 4 days
Insulin Icodec (Awiqli FlexTouch)
time to peak: 15 hrs
dosing frequency: once weekly due to phenol and benzyl alcohol
pharmaceutical concerns
chemical stability
Hydrolysis of amide to acids
Asparagine to aspartic acid
Deamidation of Asn in B chain
Formation of high MW proteins
Covalent dimers formed by insuli
pharmaceutical concerns
physical stability
Noncovalent aggregation
Destabilized hexamers = more monomers
Suspensions are MORE susceptible to changes in physical stability
Clumping + aggregates adhering to the storage container
clinical aspects of insulin formulation
Insulin syringes (should match the strength of the insulin that is to be administered)
stored in cool place that avoids sunlight
Resuspension is required for suspension formulations d/t to aggregation/clumping
Mix back and forth by rolling vial between the palms to make it uniform and milky looking
new needle and syringe for each injection
extememporaeous mixing
human growth hormone (hGH)
structure
Produced in bacteria, yeast, mammalian cells
Just know the diff. between the structures of hGH and insulin if you look
AA = 191
4 helixes

hGH
function
GH receptor is a monomer → when bound, dimerizes and becomes active
hGH
regulation
Endogenous GHRH excreted by hypothalamus to stimulate pituitary
Pituitary excretes GH to liver, adipose, muscle and bone
Somatostatin from hypothalamus DECREASES GH release by negative feedback look
IGF-I will stimulate positive feedback
rGH products
produced in E.coli
genotropin
norditropin
nutropin AQ
humatrope
zomaction
omnitrope
rGH product
produced in mammalian cells
Serostim (AIDS wasting)
LonaPEGsoatropin
long acting prodrug
contains PEG and linker
weekly dosing compared to daily somatropin due to longer DOA
FSH
function
release controlled by hypothalamic releasing factor GnRH
females: stimulates follicular development and estrogen synthesis
males:
plays a role in spermatogenesis
promotes testicular growth and enhances the synthesis of androgen-binding proteins
increases the number of oocyte
FSH
structure
has alpha and beta subunit

formulations of FSH
follitropin alfa
follitropin beta
folliptropin delta
