5) Positioning & Maintenance
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/135

There's no tags or description
Looks like no tags are added yet.
136 Terms
define functional residual capacity (FRC)
volume of lungs after passive exhalation (reserve)
patient positions from biggest FRC to smallest
standing > sitting > prone > lateral > supine
define supine position
laying on back, neutral neck, hands supinated/neutral, legs uncrossed, compression stockings
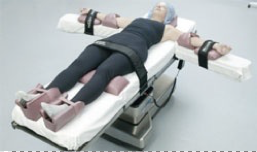
main benefit of supine position and why
hemodynamics best maintained bc body at level of heart
padding for supine position
heels, elbows, occiput, pillow under knees
define trendelenburg
supine but head down
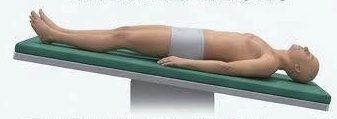
what surgeries use trendelenburg position?
lower abdominal, gyne & urology
↑ or ↓: venous return in trendelenburg
increase
↑ or ↓: central venous pressure in trendelenburg
increase
↑ or ↓: intracranial and intraocular pressure in trendelenburg
increase
in trendelenburg, swelling of what can occur and how is it fixed?
swelling of face, larynx, tongue can be fixed by head up
↑ or ↓: FRC in trendelenburg and why
decreased bc cephalad movement of abdominal organs
in mechanically ventilated patients in trendelenburg, what changes?
increased peak inspiratory pressures
in spontaneously ventilated patients in trendelenburg, what changes?
increased breathing work
define reverse trendelenburg
supine but head up

what surgeries use reverse trendelenburg position?
upper abdominal, lap chole, breast
↑ or ↓: venous return in reverse trendelenburg
decreased
↑ or ↓: perfusion to brain in reverse trendelenburg
what do you have to pay attention to because of this change?
decreased, MAP
↑ or ↓: FRC in reverse trendelenburg
increased
define lithotomy position
supine but legs abducted 30-45 degrees and hips flexed 80-100 degrees

what surgeries use lithotomy position?
gyne, rectal, urology
how are legs supported and moved in lithotomy?
stirrups, raised and lowered together
if the foot section is lowered in lithotomy position, what should you watch out for?
fingers for crush injury
↑ or ↓: venous return in lithotomy
increased
↑ or ↓: FRC in lithotomy
decreased
common nerve injuries in lithotomy
common peroneal: outside of fibula presses against stirrups
sciatic: hyper-flexion of hips
what surgeries use lateral decubitus position?
thoracic, hip

if surgeon must have arms >90 degrees, how do you make sure patient is comfortable?
bend elbows
right side lateral decubitus = ________ side down
right
dependent arm = ↑ or ↓ arm
down
in lateral decubitus, why is an axillary roll used?
avoid compression injury to dependent brachial plexus and blood vessels
in lateral decubitus, where do you put the axillary roll?
caudal and 1 hand width away from dependent axilla

independent lung = ________ lung
operative
how are legs positioned in lateral decubitus?
flexed at 90 degrees, pillow between knees
why is bean bag used in lateral decubitus?
keeps patient from rolling
in lateral decubitus, what arm do you put pulse ox and blood pressure and why?
dependent to monitor arterial compression
how and why is kidney rest used in lateral decubitus?
under iliac crest to avoid inferior vena cava compression

define hypoxic pulmonary vasoconstriction (HPV)
lung shunts blood to areas with better ventilation
how is V/Q affected in the dependent lung in lateral decubitus?
decreased ventilation, increased perfusion
what causes changes to V/Q in lateral decubitus?
mediastinum weight, cephalad pressure of abdominal organs, gravity
dependent lung in lateral decubitus has ________ V/Q
low
how is V/Q affected in the independent lung in lateral decubitus?
increased ventilation, decreased perfusion
independent lung in lateral decubitus has ________ V/Q
high
define prone position
laying face down

what surgeries use prone position?
posterior skull, posterior spine, perirectal
in prone, if belly can hang freely (no abdominal pressure), pulmonary function is…
retained
why is wilson frame used in prone position?
lets belly hang free to maintain lung compliance and decrease bleeding

when to intubate when using prone position
on stretcher before positioning
what to check after patient is turned prone?
bilateral breath sounds
compressed abdomen causes decreased…
venous return and FRC
where to put chest rolls in prone position?
iliac crest to clavicle

when moving patient from stretcher to OR table, it is important to maintain…
head/neck in line with spine and control of ETT
when turning patient prone, ________ circuit
disconnect
prone position safety checks
pressure points, supported shoulders, neutral neck, breasts/genitalia free of pressure
in prone, where are ECG leads placed?
back
what surgeries use mayfield tongs/horseshoe?
neurosurgery
what surgeries use sitting/beach chair position?
head, shoulder
what about sitting/beach chair position can cause risk of venous air embolism?
heart is below surgical site, areas above have sub-atmospheric venous pressure so if vein gets nicked, air can be entrained
in sitting/beach chair position, how is head positioned?
fixed in pins or special holding device
in sitting/beach chair position, how is the neck positioned?
>2 finger widths between mandible and sternum
in shoulder surgery using beach chair position, where do monitors go?
IV, NIBP, pulse ox on same side
in beach chair position, is the NIBP a good representation of cerebral perfusion pressure?
no, pressure at brain is lower
hypotension is important to monitor in sitting/beach chair position because…
blood can pool in lower extremities
for every 1 inch of vertical height between heart and brain, pressure decreases by…
1.86 mmHg
for every 1 foot of vertical height between heart and brain, pressure decreases by…
22.4 mmHg
symptoms of ulnar nerve injuries begin…
24 hrs after surgery
how to avoid ulnar nerve injuries
avoid pressure on postcondylar groove of humerus (elbow)
brachial plexus can be injured from…
stretch & compression
how to avoid brachial plexus injury
avoid shoulder braces, excessive lateral rotation of head, and high axillary roll
how to avoid sciatic and common peroneal nerve injury
minimize time in lithotomy, avoid excessive flexion of hips and pressure on peroneal nerve, move legs together
most common eye injury
corneal abrasion
perioperative vision loss (POVL) is caused by…
ischemic optic neuropathy (ION)
prolonged hypotension
prolonged prone position
large crystalloid use
large blood loss (anemia)
what MAC will prevent movement in 95% of surgical patients?
1.2 MAC
what MAC will prevent movement in 99% of surgical patients?
1.3 MAC
factors that increase MAC (less potent)
acute amphetamines
chronic alcohol
young (highest at 6 months)
hyperthermia
red hair
factors that decrease MAC (more potent)
chronic amphetamines
acute alcohol
old
hypothermia
hypnotics
opioids
volatile anesthetics cause shapid breathing, what does this mean?
increases respiratory rate, decreases tidal volume
what are the main 3 drawbacks of volatile anesthetics?
trigger malignant hyperthermia, decrease BP, financial/environmental impact
what gas uniquely has analgesic properties?
nitrous oxide
benefits of nitrous oxide?
odorless, lowers MAC of halogenated agents, rapid on/off
drawbacks of nitrous oxide
increase PONV, many contraindications (ex: high intra-ocular pressure), stays in atmosphere for over 100 years
what receptors do opioids bind to?
mu1, mu2, kappa, delta
what do opioids do?
mitigate transfer of pain to brain
side effects of opioids
nausea, pruritus (itching), respiratory depression
why can people have allergic reactions to morphine?
histamine release
morphine dose
10mg
morphine onset
5-10 min
morphine peak
>30 min
morphine duration
3-4 hrs
hydromorphone (Dilaudid) dose
1.5mg
hydromorphone (Dilaudid) onset
10-15 min
hydromorphone (Dilaudid) peak
10-20 min
hydromorphone (Dilaudid) duration
2-3 hrs
fentanyl (Sublimaze) dose
100mcg
fentanyl (Sublimaze) onset
1-2 min
fentanyl (Sublimaze) peak
3-5 min
fentanyl (Sublimaze) duration
0.5-1 hr
ketorolac (Toradol) inhibits what?
cyclooxygenase (COX), prostaglandin synthesis, platelet aggregation
ketorolac (Toradol) onset
10 min
ketorolac (Toradol) peak
1-2 hrs