SLAP
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/28

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
29 Terms
concomitant w/ RC repair is Arthroscopic Subacromial Decompression. Procedure includes
Subacromial bursectomy
Coracoacromial ligament resection
Resection of undersurface of anterior acromion
Resection of osteophytes
Arthroscopic Subacromial Decompression precautions include post surgical pain & avoid
impingement positions (horizontally adduction, arm overhead)
Common concomitant procedure w/ RC repair
Arthroscopic Subacromial Decompression recovery at ~10-14 weeks post-op goals
Restore Pain Free AROM: MT, Ther Ex
Strengthening: Scapular Stabilizers, RC, Shoulder Prime Movers
SAD vs Sham procedure: No difference
Indications for a Superior Capsular Reconstruction
Massive Irreparable RC tears >5cm
>= 2 Tendon tears
Intact GH joint (minimal joint degeneration)
Superior capsular reconstruction consists of re-enforcement via
Tensor fascia autograft
Prevents superior migration of humerus
Superior Capsular Reconstruction has mixed outcomes & limited
long-term data
May prove superior to TSA
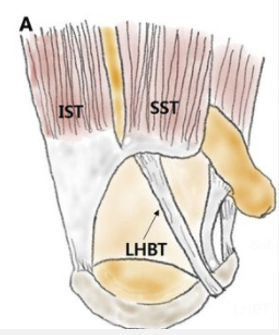
Long Head of Biceps Tendinopathy biomechanical MOI & comorbidity
Repetitive traction
Friction
Glenohumeral rotation
Comorbid w/: RC & Labral Tears
Biomechanically the long head of biceps provides
anterior superior stability to GH Joint
Long Head of Biceps Tendinopathy sxs are anterior shoulder pain, signs are
Pain w/ resisted movements:
Speeds test
Yergason's Test
Impingement Tests
Neer’s/HK
Long head of biceps tendinopathy conservative management includes
RC & Scapular Strengthening: stabilizes & off loads biceps tendon
Tendon Loading based on irritability, eventually must do it (scapular exercises 1st, supine eccentrics into shoulder extension)
Long Head of Biceps tendinopathy surgical managements include
Resection (Tenotomy)
Tenodesis (younger patients): Often performed w/ other procedures, RC repair or Labral Repair
Biceps Brachii- Long Head Rupture common MOI
Degenerative (smokers, metabolic disease)
Max Lifting injury
Older Males: Lower tissue quality, Highly activity
Prognosis for a Biceps Brachii- Long Head Rupture
Minimal loss in biceps strength ~10%
Small ↑ in anterior instability of GH joint
Usually will not repair/heal
Bulged appearance will ↓ as those unused muscle fibers atrophy
Superior Labral Tears Anterior to Posterior (SLAP Tears) is an injury of the
superior aspect of the labrum extending A→P
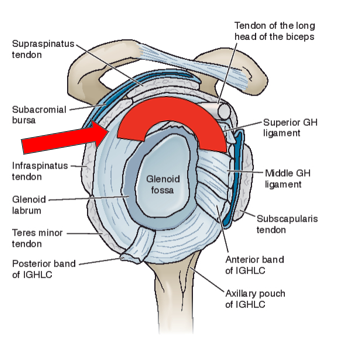
Superior Labral Tears Anterior to Posterior (SLAP) MOI
Repetitive overhead motion (pitchers, swimmers, quarterbacks, volleyball)
“Peel-back Mechanism” (principle theory)– wind-up position peels labrum peeled back off of glenoid fossa (humeral head rolling posteriorly & superior labrum peeling)
Forceful eccentric biceps contraction (biceps attached to superior labrum, slowing arm down)
FOOSH
SLAP injuries are usually do not present in isolation. What other concomitant pathology may present?
25% w/ RC tears
37% Bankart lesion
Instability
OA
Symptoms/signs of a SLAP tear
Posterior shoulder pain that ↑ w/ overhead motion
Painful popping/clicking
Sense of looseness
(+) Impingement signs
Whole arm weakness due to loss of stability in GH jt (disrupts force transfer system)
SLAP special tests for diagnosis
O’Brien’s Anterior Compression
Biceps load test
Crank test
Clunk test
Speed’s test
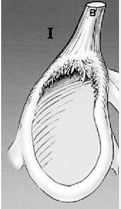
Type 1 SLAP Lesion
Fraying or degeneration of superior labrum (no bicep involvement)
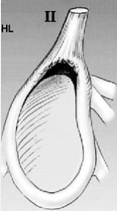
Type II SLAP Lesion
Fraying or degeneration of superior labrum
Biceps tendon detached from glenoid
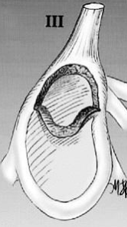
Type III SLAP lesion
Bucket-handle tear of superior labrum
Biceps tendon is intact
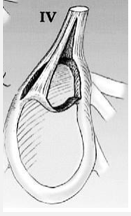
Type IV SLAP lesion
Bucket-handle tear of superior labrum
Biceps tendon is also torn
Surgical Interventions for type I SLAP Tear
Conservative Treatment
Maybe Debridement of superior labrum
Surgical Interventions for type II SLAP Tear
Repair superior labrum
Biceps tendon tenodesis
Surgical interventions for type III SLAP tear includes a
surgical removal of bucket-handle tear
Surgical Interventions for type IV SLAP Tear
Surgical removal of bucket-handle tear
Resection of damaged biceps tendon
Reattachment of labrum
Repair of remaining biceps tendon
Precautions for SLAP Tear ROM
Limit A/PROM ER to <30° for 4-8 weeks (peel back lesions)
Rehab is specific to method of treatment of SLAP Tear. Starting w/ immobilization in a sling for
~4 weeks & w/ an abduction pillow in IR
Rehab of SLAP Tear, ROM considerations
Elbow & hand ROM immediately
NO bicep strengthening for 4-8 weeks