EQ peri-parturient problems in the mare
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/56

There's no tags or description
Looks like no tags are added yet.
57 Terms
List the possible pre parturient problems in the mare
Colic
Over- large mare
Ventral oedema
Pre-pubic tendon rupture
Hydrops —> hydrallantois; hydramnios
Placentitis
Varicose veins
Orthopaedic disease
List some of the possible causes of pre parturient colics
Intra-uterine foal movement (mild-mod, common)
should respond to mild-mod analgesia (buscopan / phenylbutazone)
GI colic (+ other forms of colic)
Actually foaling / aborting (do vaginal exam to check if cervix is open)
Ischaemia/ necrosis/ rupture of caecum & colon
Due to weight of foal applying pressure to viscera / stretching blood vessels
difficult to diag —> look for signs of peritonitis / endotoxaemia
Uterine torsion
How does uterine torsion usually present?
Usually last 1/3 preg
Usually low grade chronic / intermittent but can be severe
How is uterine torsion diagnosed?
Rectal —> palpate one tight broad lig
Vaginal exam not helpful —> unlike cattle, twist cranial to cervix
How is uterine torsion treated?
Surgery
Standing flank laparotomy
GA & midline laparotomy (± caesarean?)
Rolling under GA NOT recommended
prog = 50% for live foal, 70% for live mare
Why may mares get ventral oedema pre parturient (near term)?
Compression of lymphatic draiange by foal
If mare is well, oedema uniform & non painful —> will recover post foaling (make sure isn't anything more serious)
Important to differentiat from other causes of abdo enlargement

How does pre-pubic tendon rupture present?
Due to weight of foetus —> more common in older mares
Large plaque of painful oedema, continuous with udder (“dropped” udder).
Maybe bloody discharge in milk
Often gives colic signs
Mare often spends more time recumbent.
How is pre pubic tendon rupture treated?
Bute
Will need assistance w/ foaling —> unable to use abdo muscles to contract foal out
C-section?
Often progressively becomes more painful → euthanasia
DON'T BREED FROM HER AGAIN
never heal fully & will rupture again (permanently damaged)
What is Hydrops aminion/Hydrops allantois?
Excessive fluid in allantoic / amniotic space
May eventually cause colic, dyspnoea, recumbency, circulatory collapse
Foals usually deformed
How is Hydrops aminion/Hydrops allantois diagnosed?
Rectal exam —> huge fluid filled uterus but foal out of reach
How is Hydrops aminion/Hydrops allantois treated?
Induce foaling / abortion
Dilate cervix, drain fluid off slowly
Manually remove foal
IV fluids to maintain systemic blood pressure?
How do you assure an owner that a mare is just fat?
Do rectal exam to confirm foal is present & alive; rule out pathological problems
What agents cause placentitis?
Strep. spp., E.coli, Aspergillus.
What are the signs of placentitis?
Asc. infection from cervix
Eventually leads to abortion
Premature udder development and lactation ± vaginal discharge
How is placentitis diagnosed?
C/S
U/S —> placental thickening

Cervical swabs if discharging
How is placentitis treated?
Potentiated sulphonamides
Bute
What is the most common cause of vaginal bleeding in a horse?
Varicose veins (more likely in pregnant / older mares)
How do you treat varicose veins?
Usually no tx required —> more concern to owner than mare
List the intrapartum problems in a mare?
Dystocia
Red bag delivery
Uterine Rupture
Uterine tear
Cervical tear
Perineal tears
Describe orthopaedic dx during pregnancy
Extra weight / bulk of late preg can substantially exacerbate effects of orthopaedic dx —> arthritis, laminitis etc.
Which drug is effective in management of orthopaedic dx during pregnancy?
Phenylbutazone
What are the types of phenylbutazone available?
Equipalazone solution —> can be used during preg & lactation
Butagran oral powder —> care if admin to preg mares, foetotoxic @ high dose levels
avoid use around time of parturition
potential benefits should be weighed against potential hazard to mare and / or foal
What equip & meds are needed during a dystocia case?
Sedation (and ketamine?)
Clenbuterol or buscopan
Local anaesthesia (epidural)
Doxapram
Foaling ropes
Lubricant
Hibiscrub
Needles/syringes
Waterproofs
How do you handle a dystocia case?
Check mare not in shock/haemorrhaging
Clean perineum & vaginal exam w/ plenty of lube to check presentation
Decide if vaginal delivery poss
If no clear progress within 15 minutes reassess
consider C section or controlled vaginal delivery under GA or terminal C section (GA mare, cut foal out, then euthanise mare)
avoid embryotomy (last resort)
What is the prognosis for each of these presentations?


What is a controlled vaginal delivery?
Vaginal delivery under GA
Pref w/ hindquarters hoisted
Can proceed to C sec, terminal C sec or euthanasia
What is the prognosis of uterine rupture/ tears in mares?
Complete rupture —> v. bad, foal may fall into abdomen (extract foal & consider euthanasia)
Smaller tears —> may not be noticed & only suspected when show signs of peritonitis after foaling (better but still guarded prog)
some may not be full thickness
How is uterine rupture/ tear diagnosed?
Clinical signs
Rectal/vaginal exam
U/S
Peritoneal tap
How is uterine rupture/ tear treated?
Medical tx as for peritonitis
Ex lap & repair for full thikness tears
What is red bag delivery?

Allantochorion (membrane that attaches foal to mare —> should burst early during stage 2 of parturition) fails to rupture
Foal will rapidly asphyxiate
How do you treat a red bag delivery?
Instruct client to puncture bag & clear foal's nostrils
Tough —> may need scissors / knife
How do you treat low grade perineal lacerations?
(Common during foaling)

Many heal w/o intervention
Lacerations which substantially disrupt perineal anatomy should be repaired, esp. if natural healing will alter perineal conformation
done immediately or delayed for a few days if severe bruising
AB, NSAIDs, tetanus cover
What is a third degree perineal laceration?
Where foals foot has penetrated rectum & torn through anus.
Rectum, vulva & vagina all communicate
How do you treat a third degree perineal laceration?
Do not repair immediately —> will break down
AB, NSAIDs, Tetanus cover
Repair required if mare to conceive again
Delay surgery for @ least 4-6 weeks until granulated
Surgery often difficult (several attempts needed before complete repair occurs)
What is a second degree perineal laceration?
Recto-vaginal fistulas —> treat in same manner as third degree → delayed repair
How do you treat a cervical laceration?
Usually spontaneous healing
May need surgical repair
Delay one month post partum until uterus involuted & inflam subsided
note & monitor if cervical incompetence occurs —> mare will be sub-fertile
List the post parturient priblems you can get in the mare?
Colic
Prolapse
Retained placenta
Metritis
Hypocal
Tetanus
What do you need to consider about post-partum colic?
Some can be rapidly fatal, although most not serious —> careful assessment & montioring
Make sure foal does not get injured if mare colicking violently
What are the possible causes of colic in a post partum mare?
Uterine cramps
no sign of endotoxaemia
mild-mod colic
should resolve w/ buscopan / phenylbutazone
Normal GI colic
Iscahemia/ necrosis/ rupture of caecum and colon (expulsive forces of foaling)
Inversion of uterine horn
Colonic torsion
Uterine artery rupture
Describe inversion of uterine horn as a cause of post-partum colic
After forceful foaling / too forceful removal of retained membranes
Colic which reoccurs despite analgesia
If cont. to strain → may proceed to uterine prolapse
How is inversion of uterine horn diagnosed?
Vaginal & rectal exam
How is inversion of uterine horn treated?
Analgesia
Smooth m. relaxants (buscopan / clenbuterol)
Manual replacement
Uterine lavage
What causes a colonic torsion in post partum mare? How is it treated?
Due to sudden increase of space in abdomen post foaling
Rapidly fatal unless quick surgical intervention
How may a rupture of uterine artery present?
Mild to mod colic signs
Haemorrhage into broad lig / into abdo
may be contained within broad lig, but if ruptures / mare haemorrhaging directly into abdo → rapidly fatal
May not respond well to NSAIDs —> painful
How is uterine artery rupture diagnosed?
Gentle palpation of broad lig per rectum
Abdo & rectal U/S
How is uterine artery rupture treated?
Keep quiet —> sedate?
Analgesia
IV fluids —> judiciously (don't want to raise BP)
Blood transfusions
Clotting agents —> amino caprionic acid?, 10ml 10% formalin in 1 litre saline?
What is the cause of uterine prolapse?
After excessive traction on foal / retained membranes or after difficult foaling or if mare exhausted

What can uterine prolapse lead to?
May rupture uterine vessels & cause fatal internal haemorrhage
Even after replacement, death from metritis / endotoxaemia not uncommon
How is uterine prolapse treated?
Clean uterus.
Replace under epidural anaesthesia.
Oxytocin once replaced
Treat w/ broad spec AB & NSAIDs for anti-endotoxic effects
At what stage are foetal membranes not passed abnormal?
On average pass within 2 hours after foaling
Over 4 hours considered abnormal
Treat if still retained 4-6hrs post foaling
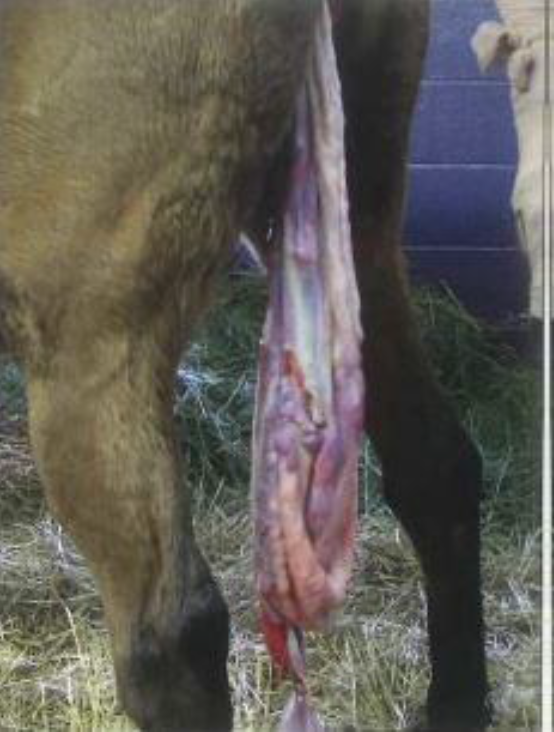
What happens if membranes are retained?
Decompose rapidly → metritis → induces endotoxaemia → severe laminitis & death
(depends on invidivual how prog is e.g. heavy horses considered v. suscep to effects)
How do you treat RFM?
Treat promptly as can cause endotoxaemia
Oxytocin, broad spec AB; flunixin for anti-endotoxic effect, check tetanus cover
Oxytocin may be enough to stimulate passage
Gentle manual removal can be used (potentially controversial —> endometrial damage)
Gentle traction, if does not work twist
What should you do once you have removed RFM?

Check for retained fragments (tip of pregnant horn most likely)
If can't located retained fragments, lavage until fluid runs clear
Admin more oxytocin after lavage , turn mare out
AB (3-5d), NSAIDs
keep lavaging until uterus involuting & little uterine fluid being generated
What are the features of metritis?
Maybe due to unnoticed partial retention of placenta or due to contamination of uterus during foaling
May cause fatal endotoxaemia ± laminitis if untreated
Tx —> ABs , Nsaids, oxytocin & lavage exactly as described for RFM
How does hypocal present in mares? How do yout treat it?
M. fasciculations, recumbency, tetany, Diaphragmatic flutter “thumps”
Give calcium diluted in saline
What do you need for an orphan foal?
Source of colostrum
Milk replacer
Bottle/teat
Feeding protocol
Ideally foster mare
Hand rearing not recommended
What are the problems with orphan foals?
Hand-rearing foals is not recommended
Expensive
Hugely time consuming
Growth problems common
Socialisation and behavioural problems
Adult hand-reared horses can be exceptionally dangerous.