Electrolytes and acid-base
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/20

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
21 Terms
what are electrolytes
substance that ionises when dissolved in water
sodium Na+
potassium K+
chloride Cl-
where are they distributed
distributed within body water
around 60% body weight lean adult
intracellular fluid (ICF) - around 40% body weight
Extracellular fluid (ECF) ~20% body weight
▪ Interstitial fluid (15%)
▪ Plasma (5%)
60:40:20 rule
Changes in body water distribution may affect electrolyte values
Interpretation of electrolyte measurements should take into consideration ECF volume
where are they distributed

how they are maintained in health
kidneys
Distribution of electrolytes depends on
Osmolality- distribution of solutes
Electroneutrality — Acid base status-anion gap

osmolality
All body fluids seek an isotonic balance with each other in health
Electrolytes (primarily Na+ )
• Bicarbonate (HCO3 - )
• Glucose
• Urea

regulation of sodium through diff means….
Regulation of blood volume
Hypovolaemia (low blood volume-low blood pressure - so make fluid concentrated to increase osmosis)
▪ Activation of RAS-> Angiotensin II- > resorption of Na+, Cl - and H2O proximal tubule
▪ Aldosterone stimulates active absorption of Na+ in the collecting tubules
▪ ADH secreted-> resorption of Na+, Cl - and H2O medullary thick loop of Henle
Increased blood flow
▪ ANP (lowers blood pressure and decreases blood volume) -> promotes Na+ excretion in distal nephron
Regulation of plasma osmolality
Hyperosmolality (too much protein in fluid/blood)
▪ Thirst centres stimulated - > increased H2O intake
▪ ADH released -> increased resorption of H2O
Hypoosmolality
▪ Decreased H2O intake
▪ ADH secretion diminished -> less resorption of H2O

regulation of potassium - cellular uptake
regulation of potassium through renal excretion
Aldosterone stimulates the
• Secretion of K+ by principal cells of the collecting tubules
High flow rate (of aldosterone) promotes excretion
Low flow rate inhibits excretion
Hypochloraemia (very low Cl)
• Resorption of Na+ without Cl leads to secretion of K+ (because Cl- is negative and Na+ is positive, when they leave the urine together it keeps the electric balance neutral, when Cl- is low Na+ keeps the urine/ lumen negatively charged, pulling magnet K+ out of cell into urine)
just go over this with gemini icba ffs

alterations in potassium
Acidoses and Alkaloses affect serum K+ Inorganic or mineral acidosis may cause K+ to shift out of the cells -> hyperkalaemia in peripheral blood
Organic acidoses eg lactate or ketoacidosis typically will not
• When lactate or ketone body enters the cell H+ goes with them
• Acidaemia may promote movement of K+ out of cells, but K+ is excreted in urine with the anions
Metabolic alkalosis may cause mild hypokalaemia
how do we measure them
Ion Selective Electrode
• The ISE has a selective membrane which only allows the ion of interest to enter.
• The difference between the two electrodes is calculated and the concentration of the ion is determined from this
if lipid is present then electrolytes are not in the lipid fraction BUT the machine will calculate as if all the plasma is in the aqueous phase
Except when it is a direct ISE

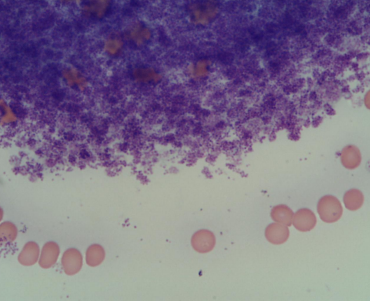
when platelets clot what happens
K+ is released
Thrombocytosis may result in higher serum K+
Prolonged contact of erythrocytes and serum (>2hours) may also increase K+ particularly with some dog breeds, horses and ruminants
what happens in disease
Solute loss in excess of water-loss of hypertonic fluids
Isotonic loss
Water loss in excess of solute- loss of hypotonic fluids
hypernatraemia
H2O deficient
• Inadequate intake
• Pure H2O loss
• H2O loss> Na+loss
▪ Renal
▪ Alimentary
Na+ excess
• Salt poisoning
• Administration of hypertonic saline or sodium bicarbonate
• Decreased renal excretion-hyperaldosteronism
normonatraemia when dehydrated
Net loss of isotonic fluids
• Alimentary Loss
• Renal Loss
• Skin loss-sweating horses
Net retention of isotonic fluids leading to oedma or transudate
• Congestive heart failure
• Hepatic cirrhosis
• Nephrotic Syndrome
hyponatraemia
Na+ deficit Na+loss >H2O loss
• Alimentary
• Renal
• Cutaneous
• Third space
H2O excess
• Oedematous disorders
Shift of H2O from ICF to ECF
• Hyperglycaemia
Shift of Na+ from ECF to ICF
• Acute muscle damage
Shift of Na+ from intravascular to extravascular
• Uroperitoneum

hyperkalaemia
Shifting of K+ from ICF to ECF
• Metabolic acidosis (inorganic acids)
• Rhabdomyolysis or other muscle damage
• Massive tissue necrosis
Increased total K+
• Decreased renal excretion
▪ Renal insufficiency particularly oliguric or anuric CKD
▪ Urinary tract obstruction or leakage
▪ Addisons
▪ Trimethoprim
Increased intake
???
• Peritoneal effusions
hypokalaemia
Shifting of K+ from ECF to ICF
• Metabolic alkalosis with alkalaemia
• (Rapid) increase in insulin activity
• Endotoxaemia
Decreased total body K+
• Decreased intake
• Increased renal loss
• Increased alimentary loss
???
• Hypokalaemic renal disease in cats
chloride
Generally will follow sodium
Will also be affected by bicarbonate levels
If normochloraemia present with hypernatraemia may be increased anion gap
• Lactic acidosis
• Ketoacidosis
• Renal failure
• Ethylene glycol or methanol poisoning
overview
Multiple processes affect electrolyte measurements
The measured electrolytes in the serum are only a small part of the total body values
Values should be interpreted in conjunction with
• Knowledge of volaemic state
• Knowledge of acid base status
• In conjunction with clinical presentation and other biochemistry parameters
image example right bar on D - increase of HCO-3 and decrease in Cl- = acidosis?


measurement of acid-base
types of acid-base disturbance
Disorders may be a combination of primary, and compensatory Mixed acid base disorders are less common but may also be seen.

blood gas data in simple acid-base disorders

algorithmic approach
