N401- Alterations in Neurological Function
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/92

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
93 Terms
The nervous system is the body’s primary?
communication and control system. It receives information from the environment and inside the body, processes that information, and coordinates appropriate responses.
The nervous system is divided into two main anatomical divisions:
Central Nervous System (CNS)
-Brain – processes information, controls thoughts, emotions, movement, sensation, and many automatic functions.
-Spinal cord – carries information between the brain and body and serves as a major center for reflexes.
Peripheral Nervous System (PNS)= Includes all nerves outside the brain and spinal cord.
-Connects the CNS with muscles, organs, skin, and sensory receptors.
The PNS can be further divided into:
Somatic nervous system – controls voluntary skeletal-muscle movement and carries sensory information to the CNS.
Autonomic nervous system (ANS) – regulates involuntary functions such as heart rate, blood pressure, digestion, and pupil size.
Autonomic nervous system (ANS) includes?
Sympathetic division: prepares the body for activity or stress ("fight or flight").
Parasympathetic division: promotes rest, digestion, and energy conservation ("rest and digest").
Enteric nervous system: regulates much of the activity of the gastrointestinal tract.
Neurologic function refers to?
how the brain, spinal cord, and peripheral nerves receive information, process it, and produce appropriate responses.
What is the 🧠 Frontal lobes function and clinical associations?
Voluntary movement, planning, judgment, personality, behavior, speech production
Identifiers= Weakness, personality changes, poor judgment, Broca aphasia
What is the Parietal lobes main function and key clinical associations?
Touch/sensation, spatial awareness, sensory integration
Identifiers= Loss of sensation, neglect, difficulty with spatial tasks
What is the Temporal lobes main function and key clinical associations?
Hearing, memory, emotion, language comprehension
Identifiers= Memory problems, Wernicke aphasia, auditory disturbances
What is the Occipital lobes main function and key clinical associations?
Vision and visual processing
Identifiers= Visual field defects, visual processing problems.
What is the neurological function?
Level of consciousness and mental status= Alertness and orientation, Attention, memory, and ability to follow commands, Speech and language.
Cranial nerve function= Vision and eye movements, Facial sensation and movement, Hearing and balance, Swallowing and gag/cough function, Shoulder and tongue movement
Motor function= Muscle strength and tone, Ability to move the limbs, Coordination and control of movement, Presence of tremor, weakness, or involuntary movements
Sensory function= Ability to perceive light touch, pain, temperature, vibration, and position, Comparison of sensation between sides of the body.
Reflexes= Deep tendon reflexes, such as the knee jerk, Superficial and pathologic reflexes, Reflexes help assess pathways involving the brain, spinal cord, and peripheral nerves
Coordination and cerebellar function= Finger-to-nose and heel-to-shin testing, Rapid alternating movements, Balance and gait
Autonomic function= Regulation of heart rate and blood pressure, Sweating and body temperature, Bowel and bladder function, Other involuntary body functions.
What are the 12 Cranial Nerves?
# | Cranial nerve | Type | Major functions |
I | Olfactory | Sensory | Smell |
II | Optic | Sensory | Vision |
III | Oculomotor | Motor | Most eye movements, eyelid elevation, pupil constriction |
IV | Trochlear | Motor | Moves the eye downward and inward |
V | Trigeminal | Both | Facial sensation; chewing |
VI | Abducens | Motor | Moves the eye laterally |
VII | Facial | Both | Facial expression, taste from anterior ⅔ of tongue, tears and saliva |
VIII | Vestibulocochlear | Sensory | Hearing and balance |
IX | Glossopharyngeal | Both | Taste from posterior ⅓ of tongue, swallowing, sensation from pharynx |
X | Vagus | Both | Swallowing, voice, parasympathetic control of heart, lungs, and GI tract |
XI | Accessory | Motor | Shoulder elevation and head turning |
XII | Hypoglossal | Motor | Tongue movement |
Cranial nerve testing can provide important information about neurologic function:
CN I: identify familiar odors
CN II: visual acuity and visual fields
CN III, IV, VI: pupil response and eye movements
CN V: facial sensation and jaw movement
CN VII: facial expressions
CN VIII: hearing and balance
CN IX and X: voice, swallowing, palate movement, gag/cough reflexes
CN XI: shoulder shrug and head rotation
CN XII: tongue movement
The Cranial nerves are so important because The cranial nerves allow the nervous system to?
see, smell, hear, taste, move the eyes and face, swallow, speak, move the tongue, and regulate important internal organs. Abnormal findings can help healthcare professionals identify the location and possible severity of neurologic dysfunction.
Glasgow Coma Scale (GCS)
is a standardized tool used to assess a person's level of consciousness and neurologic function, particularly after traumatic brain injury. It evaluates three areas: eye opening, verbal response, and motor response.
GCS Components
Component | Response | Score |
Eye Opening (E) | Spontaneous | 4 |
| To speech | 3 |
| To pressure/pain | 2 |
| None | 1 |
Verbal Response (V) | Oriented | 5 |
| Confused | 4 |
| Inappropriate words | 3 |
| Incomprehensible sounds | 2 |
| None | 1 |
Motor Response (M) | Obeys commands | 6 |
| Localizes pressure/pain | 5 |
| Withdraws from pressure/pain | 4 |
| Abnormal flexion | 3 |
| Abnormal extension | 2 |
| None | 1 |
When GCS score is calculated?
The scores are added together: GCS = E + V + M
Highest: 15
Lowest: 3
A commonly used clinical description is:
-13–15: mild impairment
-9–12: moderate impairment
-≤8: severe impairment; may indicate coma and often prompts consideration of airway protection
These categories are useful for communication, but the individual components and changes over time are also very important.
Why GCS is Important
The GCS helps healthcare professionals:
Establish a baseline neurologic assessment
Monitor changes in consciousness
Communicate the patient's neurologic status
Assess severity after TBI
Identify deterioration that may require urgent intervention
Important Considerations for GCS
can be difficult to interpret when a patient is intubated, sedated, paralyzed, has severe facial injuries, or has language/hearing limitations. In these situations, the individual components should be documented rather than relying only on the total score.
Key point: A declining _ is clinically significant and should prompt reassessment for causes such as worsening cerebral edema, intracranial bleeding, hypoxia, or increasing intracranial pressure.
Basic Neuro Assessment
Mental status → pupils → cranial nerves → motor → sensation → coordination → reflexes → gait/balance.
Cerebral Edema
is an abnormal accumulation of fluid in or around the brain that causes brain swelling. Because the skull is rigid and cannot expand, significant swelling can increase intracranial pressure (ICP) and potentially reduce blood flow to the brain. Severe cerebral edema can become life-threatening.
Cerebral edema can result from:
Traumatic brain injury (TBI)
Stroke, particularly large ischemic strokes
Brain tumors
Intracranial bleeding
Central nervous system infections, such as meningitis or encephalitis
Hypoxia or lack of oxygen to the brain
Metabolic disturbances, including severe electrolyte abnormalities
High-altitude exposure in some circumstances
Types of cerebral edema
Type | Basic mechanism |
Cytotoxic | Cell swelling, often caused by inadequate oxygen or energy, such as in ischemic stroke |
Vasogenic | Breakdown of the blood-brain barrier allows fluid to move into brain tissue; commonly associated with tumors, inflammation, or trauma |
Interstitial | Cerebrospinal fluid moves into brain tissue, often associated with hydrocephalus |
Osmotic | Changes in blood osmolarity cause water to move into brain cells |
Symptoms of Cerebral edema?
Symptoms depend on the severity and location of the swelling but may include:
Headache
Nausea and vomiting
Confusion or changes in mental status
Drowsiness or decreased level of consciousness
Vision or speech changes
Weakness or difficulty moving
Seizures
Changes in pupil size or reaction
Abnormal breathing or heart-rate patterns in severe cases
A significant increase in ICP can cause decreased cerebral perfusion, meaning the brain receives less blood and oxygen.
Intracranial Pressure (ICP)
is the pressure inside the skull created by the brain tissue, blood, and cerebrospinal fluid (CSF).
In adults, normal ICP is generally about 5–15 mmHg. Sustained ICP above approximately 20–22 mmHg is considered concerning in critically ill patients and may require treatment, depending on the clinical situation.
🧠 The Monro-Kellie doctrine= The skull is essentially a fixed space containing three major components: Brain tissue, Blood, CSF
If one component increases—for example, from a brain hemorrhage, tumor, cerebral edema, or hydrocephalus—the body initially compensates by reducing another component, primarily CSF and venous blood.
Nursing Management for increased ICP
Positioning= Elevate the head of the bed, commonly around 30°, when appropriate. Keep the head and neck in a neutral alignment. Avoid excessive neck flexion or rotation because it can impair venous drainage.
Maintain oxygenation= Prevent hypoxemia. Maintain adequate ventilation. Avoid unnecessary prolonged hyperventilation; it can reduce cerebral blood flow.
Reduce factors that increase ICP= Treat fever. Control pain and agitation. Minimize unnecessary stimulation. Prevent coughing/straining when possible. Manage seizures promptly.
Medications/therapies= Depending on the cause, clinicians may use:Hypertonic saline, Mannitol, Sedation/analgesia when appropriate, Antiseizure medications when indicated, Treatment directed at the underlying cause
In severe causes of ICP, may require?
External ventricular drain (EVD)
Surgical decompression
Evacuation of a hematoma
Treatment of hydrocephalus
What is Cerebral Perfusion Pressure?
A very important concept is: CPP = MAP − ICP
Where: CPP = cerebral perfusion pressure
-MAP = mean arterial pressure
-ICP = intracranial pressure
-So if ICP increases, cerebral perfusion can decrease unless MAP is maintained.
Normal/target range
For adults, a typical CPP is approximately 60–100 mmHg.
Increased ICP → think:
🧠 Headache
🤢 Vomiting
👁 Pupil/vision changes
😴 Decreased LOC
💪 Motor changes
⚠ Cushing triad = late sign
Diagnosis of ICP
Evaluation may include:
Neurologic examination
CT or MRI of the brain
Monitoring of vital signs and neurologic status
Laboratory testing to identify contributing metabolic or systemic problems
In selected critically ill patients, intracranial pressure monitoring
Treatment of ICP
Treatment focuses on reducing brain swelling, controlling intracranial pressure, and treating the underlying cause. Depending on the situation, management may include:
Elevating the head and optimizing positioning
Maintaining adequate oxygenation and blood pressure
Osmotic therapy, such as hypertonic saline or mannitol, when appropriate
Treating seizures, fever, or other complications
Treating the underlying cause, such as stroke, infection, tumor, or trauma
Surgery, including decompressive procedures, in selected severe cases
How does Mannitol work to decrease ICP?
is an osmotic diuretic.
Effect: increases plasma osmolality → draws water from brain tissue → increased urinary water excretion → decreased brain volume and ICP
Important monitoring includes: Renal function, Serum osmolality, Electrolytes, Urine output, Blood pressure and volume status
_may be less appropriate in certain patients, particularly those with significant hypotension, hypovolemia, or renal failure.
For acute cerebral edema with elevated ICP, remember:
Hypertonic saline + mannitol = primary osmotic therapies
The choice between them depends on the patient's blood pressure, fluid status, kidney function, sodium level, type of brain injury, and overall clinical condition. Severe cerebral edema may also require interventions such as CSF drainage or surgery; medications alone are not always sufficient.
The important relationship to remember is:
Brain injury or disease → cerebral edema → increased intracranial pressure → reduced cerebral blood flow → possible brain ischemia and herniation
Medications Used to Treat Cerebral Edema
depends on its cause, severity, and whether intracranial pressure (ICP) is elevated. The main medications used to reduce brain swelling are hyperosmolar agents.
Hypertonic saline (NaCl) | Increases blood osmolality, pulling water from swollen brain tissue into the bloodstream | Monitor serum sodium, osmolality, fluid status, and renal function |
Mannitol | Osmotic diuretic that draws water out of brain tissue and increases its excretion by the kidneys | Monitor serum osmolality, renal function, blood pressure, and fluid balance |
Cerebral herniation
is a medical emergency in which increased pressure forces brain tissue into abnormal positions. It can cause severe neurologic injury or death and requires immediate treatment.
A head injury is trauma involving?
the scalp, skull, or brain. Head injuries range from minor injuries, such as a scalp bruise, to life-threatening conditions involving bleeding, brain swelling, or increased intracranial pressure.
Head injuries can result from:
Falls
Motor-vehicle or bicycle accidents
Sports injuries
Physical assault
Workplace accidents
Penetrating injuries
Concussion
A type of mild traumatic brain injury (mTBI).
May cause temporary changes in brain function without obvious structural damage on routine imaging.
Symptoms can include headache, dizziness, confusion, memory problems, nausea, and sensitivity to light or noise.
Contusion
A bruise of the brain tissue caused by trauma.
Can produce localized bleeding and swelling.
Skull fracture
A break in one or more skull bones.
May be linear, depressed, or involve the skull base.
A fracture can occur with or without an underlying brain injury.
Concussion symptoms?
Physical= Headache or pressure in the head, Dizziness or balance problems, Nausea/vomiting, Sensitivity to light or noise, Blurred or double vision, Fatigue
Cognitive= Difficulty concentrating, Feeling slowed down or “foggy”, Memory problems, Trouble thinking clearly.
Emotional/behavioral= Irritability, Anxiety, Sadness, Increased emotionality
Sleep= Sleeping more or less than usual, Difficulty falling asleep
Concussion Assessment
Level of consciousness and mental status
Orientation and memory
Pupils and eye movements
Balance and coordination
Neurological findings
Symptoms and their progression
Imaging such as a CT scan is not routinely required for every concussion; it is generally used when there are concerning features suggesting a more serious intracranial injury.
Concussion Management
Initial management generally involves:
Physical and cognitive rest for the first 24–48 hours
Gradual return to normal daily activities as tolerated
Gradual return to exercise/sports under appropriate guidance
Avoiding another head injury while recovering
Follow-up if symptoms persist or interfere with normal activities
Concussion Red Flags
After a head injury, urgent/emergency evaluation is needed for symptoms such as:
Increasing or severe headache
Repeated vomiting
Increasing confusion or unusual behavior
Seizure
Weakness, numbness, or difficulty speaking
One pupil larger than the other
Increasing difficulty staying awake or being awakened
Loss of consciousness or significant deterioration
Key point: A concussion can occur without loss of consciousness, and symptoms can develop or become more noticeable after the initial injury.
Basilar skull fracture
is a fracture involving the base of the skull, often occurring after significant blunt head trauma. It can involve the temporal, occipital, sphenoid, or ethmoid bones.
Battle sign | Bruising behind the ear (mastoid area) |
Raccoon eyes | Periorbital bruising, often without direct eye trauma |
CSF rhinorrhea | Clear CSF leaking from the nose |
CSF otorrhea | Clear CSF leaking from the ear |
Hemotympanum | Blood behind the tympanic membrane |
Cranial nerve deficits | Possible CN VII or VIII involvement, especially with temporal bone injury |
Epidural hematoma
Blood collects between the skull and the dura mater.
Often associated with injury to a meningeal artery.
Can cause rapidly increasing intracranial pressure.
Subdural hematoma
Blood collects between the dura mater and arachnoid mater.
Often results from tearing of bridging veins.
Can develop rapidly (acute) or more gradually (chronic).
Subarachnoid hemorrhage
Bleeding into the space containing cerebrospinal fluid between the arachnoid and pia mater.
Traumatic subarachnoid hemorrhage can occur after significant head trauma.
Intracerebral hemorrhage
Bleeding directly into brain tissue.
Epidural vs. Subdural Hematoma
Both are types of intracranial bleeding, commonly associated with head trauma, but they differ in location, blood vessel involved, presentation, and CT appearance.
Clinical priority= Both conditions can increase intracranial pressure, reduce cerebral perfusion, and cause brain herniation. A patient with a head injury who develops worsening headache, repeated vomiting, confusion, decreasing consciousness, seizures, unequal pupils, or weakness requires emergency evaluation.
Subarachnoid vs. Intracerebral Hemorrhage
Both are types of intracranial hemorrhage, but the key difference is where the blood accumulates.
Subarachnoid hemorrhage
Think: Blood → around the brain → subarachnoid space
A classic presentation is a sudden thunderclap headache, often described as reaching maximum intensity very quickly. Patients may also develop: Neck stiffness, Nausea and vomiting, Photophobia, Loss of consciousness, Seizures, Neurologic deficits
A ruptured cerebral aneurysm is an important nontraumatic cause. Traumatic SAH can also occur after significant head injury.
Intracerebral hemorrhage
Think: Blood → inside the brain tissue
Symptoms depend heavily on the location and size of the hemorrhage. Common findings include:Sudden weakness or numbness, often on one side, Difficulty speaking, Loss of coordination, Vision changes, Severe headache, Vomiting, Decreased level of consciousness, Seizures
-Chronic hypertension is an important cause of spontaneous ICH.
Depending on severity, a person may develop:
Headache
Dizziness or loss of balance
Nausea or vomiting
Confusion or disorientation
Memory problems
Loss of consciousness
Seizures
Slurred speech
Weakness or numbness
Unequal pupils
Changes in behavior or level of alertness
Clear fluid or blood draining from the nose or ears
Symptoms can sometimes worsen after the initial injury, particularly when bleeding or cerebral edema develops.
Assessments to perform when Hematoma is suspected?
Airway, breathing, and circulation (ABCs)
Level of consciousness and the Glasgow Coma Scale (GCS)
Pupillary size and response
Motor strength and sensation
Speech and orientation and Vital signs
Evidence of skull or facial injury
CT of the head is commonly used when significant intracranial injury is suspected. MRI may be useful for certain injuries that are less apparent on CT.
Treatment for hematomas?
depends on the injury and its severity. It may include:
Observation and symptom management for uncomplicated mild injuries
Preventing secondary brain injury by maintaining adequate oxygenation and blood pressure
Treatment of intracranial pressure or cerebral edema when present
Management of seizures
Surgical evacuation of certain hematomas
Surgical repair of selected skull fractures
Rehabilitation for persistent neurologic deficits
A major goal after head trauma is to prevent?
secondary brain injury.
Primary injury: damage that occurs at the moment of trauma
↓
Secondary injury: additional damage caused by bleeding, cerebral edema, increased intracranial pressure, reduced oxygen/blood flow, seizures, or other complications.
Red flags after a head injury include worsening headache, repeated vomiting, increasing confusion or sleepiness, seizure, weakness, unequal pupils, loss of consciousness, or difficulty waking the person. These require immediate emergency medical evaluation.
What are Seizures?
is a sudden, abnormal burst of electrical activity in the brain that temporarily changes a person's movement, behavior, sensation, awareness, or consciousness. Seizures can have many causes and do not necessarily mean that a person has epilepsy.
Seizures may occur because of:
Epilepsy
Head or brain injury
Stroke or brain tumor
Central nervous system infections
Low blood glucose
Electrolyte abnormalities
High fever, particularly in young children
Drug or alcohol withdrawal
Certain medications or toxins
Lack of sleep or other individual triggers
Sometimes, no specific cause is identified.
Focal seizures
Begin in a specific area of one cerebral hemisphere.
May occur with preserved awareness or impaired awareness.
Symptoms depend on the area involved and may include abnormal movements, sensory changes, unusual smells or sensations, or changes in behavior.
Generalized seizures
Involve networks on both sides of the brain from the beginning.
Types include:
-Tonic-clonic: stiffening followed by rhythmic jerking, usually with loss of consciousness.
-Absence: brief periods of impaired awareness, often appearing as staring.
-Myoclonic: brief, sudden muscle jerks.
-Atonic: sudden loss of muscle tone, which may cause falls.
-Tonic: sustained muscle stiffening.
-Clonic: repeated rhythmic muscle contractions.
What Happens During a Seizure?
The presentation varies considerably. A person may experience:
Altered or lost consciousness
Staring or unresponsiveness
Muscle stiffening or rhythmic jerking
Sudden loss of muscle tone
Abnormal sensations or movements
Confusion
Loss of bladder or bowel control in some cases
After some seizures, the person enters a postictal period, during which they may be confused, tired, have a headache, or temporarily have difficulty speaking or moving.
Preictal vs. postictal phases
These are periods before and after a seizure.
Preictal | Before the seizure | The brain is becoming increasingly prone to seizure activity | Aura, unusual smell/taste, déjà vu, anxiety, dizziness, visual changes |
Ictal | During the seizure | Active seizure occurs | Altered awareness, staring, muscle stiffening/jerking, automatisms, loss of consciousness |
Postictal | After the seizure | Brain recovers from the seizure | Confusion, sleepiness, headache, muscle soreness, amnesia |
Preictal period
is the time leading up to a seizure.
Some people experience a prodrome hours or even days beforehand, such as:
Mood or behavioral changes
Irritability
Difficulty concentrating
Sleep changes
Immediately before or at seizure onset, some patients experience an aura, which is actually a focal aware seizure and can include:
Déjà vu
Unusual smell or taste
Rising sensation in the abdomen
Fear or anxiety
Visual or auditory changes
Postictal period
begins after the seizure ends and can last minutes to hours.
Common findings: Confusion/disorientation, Drowsiness or sleep, Headache, Muscle aches, Temporary memory loss, Difficulty speaking, Temporary weakness (Todd paralysis)
Diagnosis of seziures?
Evaluation may include: Detailed history and description of the event
-Neurologic examination
-Electroencephalogram (EEG) to evaluate electrical brain activity
-Brain imaging such as CT or MRI
-Blood tests to identify metabolic or infectious causes
-Additional testing depending on the suspected cause
Treatment of seizures?
depends on the cause and type of seizure. It may include:
-Antiseizure medications
-Treatment of an underlying condition
-Avoidance of known triggers
-Dietary therapy in selected patients
-Vagus nerve stimulation or other devices in selected cases
-Epilepsy surgery for some people whose seizures arise from a surgically treatable area
What Should You Do If Your Patient is Having a Seizure?
During: Protect the person from injury by moving nearby objects away.
-If possible, turn them onto their side to help maintain an open airway.
-Cushion the head.
-Remove glasses if present.
-Do not restrain the person.
-Do not put anything in their mouth.
-Do not give food, drink, or medication until they are fully alert.
-Time it.
A useful way to remember seizures is:
Abnormal electrical brain activity → temporary neurologic changes → possible postictal recovery
A single seizure does not automatically mean epilepsy. Epilepsy is a neurologic disorder characterized by an enduring tendency to have recurrent unprovoked seizures.
Antiseizure medications (ASMs)
work by reducing abnormal electrical activity in the brain. The choice depends on the seizure type, patient factors, other medications, and side-effect profile.
Medication | Common use / key point |
Levetiracetam (Keppra) | Broad-spectrum; commonly used; can cause irritability/mood changes |
Valproate (Depakote) | Broad-spectrum; effective for several seizure types; important pregnancy and liver considerations |
Lamotrigine (Lamictal) | Common for focal and generalized seizures; rash is an important adverse effect |
Carbamazepine (Tegretol) | Mainly focal seizures; can cause dizziness, hyponatremia, and drug interactions |
Phenytoin (Dilantin) | Focal/generalized tonic-clonic seizures; important drug interactions and long-term adverse effects |
Phenobarbital | Effective but causes significant sedation; more commonly used in specific situations |
Topiramate (Topamax) | Broad-spectrum; may cause cognitive slowing, weight loss, and kidney stones |
Ethosuximide (Zarontin) | Specifically useful for absence seizures |
Benzodiazepines (lorazepam, midazolam, diazepam) | Used for acute seizures/status epilepticus, rather than routine long-term control |
Status epilepticus
A prolonged seizure or repeated seizures without recovery is a medical emergency. Benzodiazepines are typically first-line, followed by additional antiseizure medication if seizures continue.
Nursing points= When caring for a patient taking antiseizure medication, monitor: Seizure frequency and characteristics, Level of consciousness, Medication adherence, Adverse effects, Drug levels when appropriate, Safety precautions and injury prevention
Easy memory:
Benzos = stop an acute seizure
ASMs = prevent future seizures
Intracranial pressure (ICP)
is the pressure within the skull created primarily by the brain tissue, blood, and cerebrospinal fluid (CSF). Increased ICP occurs when the volume of one or more of these components rises and the body can no longer compensate.
Because the skull is rigid, continued pressure can compress brain tissue and blood vessels, reduce cerebral blood flow, and potentially cause brain herniation.
Increased ICP can result from:
Traumatic brain injury
Cerebral edema
Intracranial hemorrhage or hematoma
Brain tumors or other masses
Hydrocephalus
Stroke
Central nervous system infections
Abnormalities in CSF circulation or absorption
Severe hypoxia
What are some symptoms of ICP?
Early or progressive findings may include: Headache, Nausea and vomiting, Changes in level of consciousness, Restlessness or confusion, Blurred or impaired vision, Pupillary abnormalities, Weakness or other focal neurologic deficits, Seizures
A late and concerning pattern associated with increased ICP is Cushing's triad: Increasing systolic blood pressure/widening pulse pressure
Bradycardia
Abnormal or irregular respirations
Cushing's triad is a late sign and may indicate significant brainstem compression.
Effects on the brain- As ICP rises:
Increased ICP → decreased cerebral perfusion → reduced oxygen delivery → brain ischemia → additional brain swelling → further increase in ICP
Severe pressure can force brain tissue through structures within the skull, producing cerebral herniation. This is a life-threatening emergency.
Assessment and Diagnosis for ICP?
Frequent neurologic examinations
Level of consciousness
Glasgow Coma Scale (GCS)
Pupillary size and reaction
Motor strength and response
Vital signs and respiratory pattern
CT or MRI to identify causes such as bleeding, edema, or masses
In selected critically ill patients, direct ICP monitoring may be used
Treatment for ICP focuses on?
protecting cerebral perfusion, controlling ICP, and treating the underlying cause.
Depending on the situation, treatment may include:
Elevating the head and maintaining appropriate positioning
Maintaining adequate oxygenation and blood pressure
Treating fever and seizures
Hyperosmolar therapy, such as hypertonic saline or mannitol
CSF drainage when appropriate
Treatment or removal of an intracranial mass or hematoma
Decompressive surgery in selected severe cases
The most important relationship to remember in ICP is?
Increased ICP → decreased cerebral perfusion → brain ischemia → worsening brain injury
Therefore, a patient with suspected significantly increased ICP requires rapid assessment and treatment, particularly if there are changes in consciousness, pupils, breathing, or motor function.
Traumatic brain injury (TBI)
is damage to the brain caused by an external force, such as a blow, jolt, or penetrating injury. _ can range from mild concussion to severe, life-threatening brain damage.
Causes TBI
Falls
Motor-vehicle collisions
Sports or recreational injuries
Assault
Workplace accidents
Penetrating injuries
Concussion
Usually considered a mild TBI.
Causes temporary changes in brain function.
Symptoms can include headache, dizziness, confusion, memory problems, and sensitivity to light or noise.
Contusion
A bruise or area of damaged brain tissue.
May cause localized bleeding and swelling.
Diffuse axonal injury (DAI)
Results from rapid acceleration, deceleration, or rotational forces.
Causes stretching or tearing of axons throughout the brain.
Can produce prolonged unconsciousness or coma.
Intracranial hemorrhage
Trauma can cause bleeding within or around the brain, including:
Epidural hematoma
Subdural hematoma
Subarachnoid hemorrhage
Intracerebral hemorrhage
Skull fracture
May occur with or without direct brain injury.
Depressed or basilar skull fractures can be particularly concerning.
Primary injury
occurs at the moment of trauma and may include: Tissue bruising, Axonal injury, Hemorrhage, Skull fracture.
Secondary injury
develops afterward and can worsen the original damage. Causes include:
Cerebral edema
Increased intracranial pressure
Reduced cerebral blood flow
Hypoxia
Hypotension
Seizures
Metabolic abnormalities
A major goal of TBI management is therefore to prevent secondary brain injury.
Symptoms Depending on severity and location, TBI may cause:
Headache, Dizziness or balance problems, Nausea or vomiting, Confusion or disorientation Memory problems
Loss of consciousness
Seizures
Slurred speech
Weakness or numbness
Vision changes
Behavioral or personality changes
Decreased level of consciousness, Unequal or abnormal pupils
Symptoms may be immediate or develop/worsen over time, particularly when bleeding or swelling occurs.
Assessment TBI
Initial management follows ABC priorities: Airway → Breathing → Circulation
Neurologic assessment includes: Glasgow Coma Scale (GCS)
Level of consciousness
Pupillary size and reaction
Motor function
Sensory function
Speech and orientation
Vital signs
Evaluation for other traumatic injuries
CT of the head is commonly used to identify acute bleeding, fractures, swelling, or other structural abnormalities. MRI can provide additional information in selected cases.
Treatment TBI
depends on the severity and type of injury and may include:
Maintaining adequate oxygenation and blood pressure
Preventing additional trauma
Monitoring neurologic status
Managing increased ICP or cerebral edema
Treating seizures when indicated
Surgical evacuation of certain hematomas
Repair of selected skull injuries
Rehabilitation for cognitive, physical, or behavioral problems
A useful way to remember TBI is:
Trauma → primary brain injury → possible secondary injury → neurologic dysfunction
The most dangerous complications include intracranial bleeding, cerebral edema, increased ICP, reduced cerebral perfusion, and brain herniation. Any head injury accompanied by worsening consciousness, repeated vomiting, seizure, severe/worsening headache, unequal pupils, weakness, or difficulty waking requires urgent emergency evaluation.

🧠 Decorticate
FLEX
Arms bend toward the chest
Elbows flex
Wrists/fingers may flex
Legs remain extended
Memory trick: “——→ core.”
The arms move toward the core.
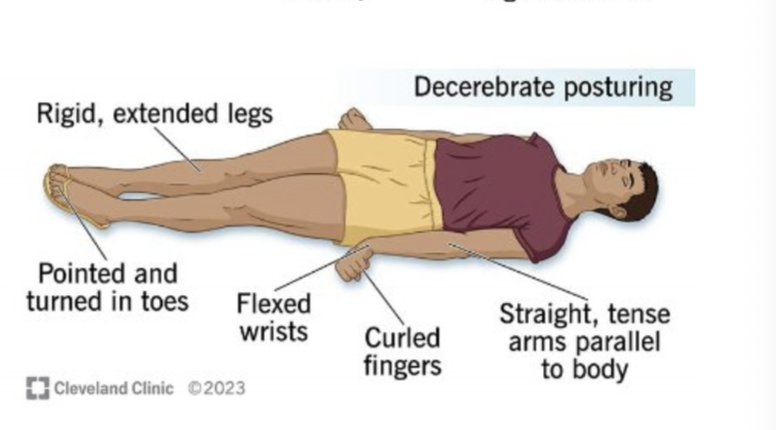
🧠 Decerebrate
EXTEND
Arms are straight and extended
Arms may rotate outward
Wrists may be flexed
Legs remain extended
The easiest way to remember decorticate vs. decerebrate posturing is
to look at the position of the arms and think about where the brain injury is relative to the brainstem.
| Decorticate | Decerebrate |
Arms | Flexed toward chest | Extended and rotated outward |
Legs | Extended, often internally rotated | Extended, often internally rotated |
Classic appearance | “Flexor” posture | “Extensor” posture |
Typical lesion | Above the brainstem, often cerebral hemispheres/thalamus | Brainstem, particularly midbrain/upper pons |
General significance | Severe brain injury | Generally indicates more extensive brainstem involvement |