Anaemia
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/108

There's no tags or description
Looks like no tags are added yet.
109 Terms
Best differentiating factor between Normocytic anaemias
Reticulocyte count
What is Reticulocyte count a measure of
Measure of marrow response to anaemia
Name 2 conditions that would → normocytic anaemia with high reticulocytes

Name 3 conditions that would → normocytic anaemia with low/normal reticulocytes

Further testing done with normocytic anaemia
Blood film
Renal function
Haemolysis screen
Haematinics
Bone marrow aspirate
What leads to Haemolytic Anaemia
Red cell destruction that the bone marrow doesn’t compensate for
Reticulocyte levels in haemolysis are high/low
High
Name 3 intrinsic (inherited) causes of haemolysis
▪ Membrane Defects
▪ Haemoglobinopathies (sickle cell disease..)
▪ Enzyme Deficiencies
Name 4 extrinsic (acquired) causes of haemolysis
▪ Immune Haemolysis
▪ Microangiopathic Haemolysis
▪ Infections: Malaria
▪ Medications
Haemolysis can be intra/extravascular. Give 2 intravascular & 1 extravascular cause
Intravascular: Mechanical – Heart Valve / Paroxysmal Nocturnal Haemoglobinuria
Extravascular: Spleen
Signs we test for to show Haemolysis
Evidence of Marrow response:
• Reticulocytosis / Polychromasia
Look for breakdown products:
• Unconjugated Bilirubin ↑
• Lactate Dehydrogenase ↑
Free Haemoglobin in Plasma or Urine
• Haptoglobin ↓
• Urinary Haemosiderin/ Urobilinogen +
Abnormal Red Blood Cells:
• Blood film: Spherocytes, Sickle cells, Red Cell Fragments
Evidence for specific types of haemolysis:
• Direct Coombs = Direct Antiglobulin Test

Write in an up/down arrow

Describe how membrane defects can cause Intrinsic Haemolytic Anaemias
The normal RBC membrane has two important types of interactions:
- Vertical interactions: attach the internal protein skeleton to the lipid bilayer (outer membrane).
- Horizontal interactions: connect proteins within the internal skeleton, providing strength and stability.
Defective vertical interactions → membrane detaches and is lost → hereditary spherocytosis (HS).
Defective horizontal interactions → skeleton loses strength → hereditary elliptocytosis (HE) or, if severe, hereditary pyropoikilocytosis (HPP).

Prevalence of Hereditary Spherocytosis in Caucasians
1/1000 to 1/3000
Inheritance pattern of Hereditary Spherocytosis
AD
Mutations in Hereditary Spherocytosis
Band 3/ Spectrin/ Actin/ Ankyrin
Pathogenesis of Hereditary Spherocytosis
Mutations in Band 3/ Spectrin/ Actin/ Ankyrin → Loss of membrane support → Spherocyte shape (less deformable) → Prematurely destroyed in the spleen
Symptoms of Hereditary Spherocytosis
Asymptomatic, Anaemia, Jaundice
What 3 things would point you to suspect Hereditary Spherocytosis
Haemolysis
Spherocytes
May have family history
Test to confirm diagnosis of Hereditary Spherocytosis
Eosin-5-maleimide (EMA) binding assay
Hereditary Spherocytosis treatment
Folic acid
Management of gall stones
Monitor for Aplastic Crisis
Splenectomy if severe
Inherited/ Intrinsic Haemolytic Anaemias can also come from enzyme deficiencies. What 2 processes do they affect & explain outcome
Pyruvate Kinase (PK) Deficiency → Defects in glycolysis → Inability to meet energy needs of the cell and shortened cell lifespan
Glucose-6-phosphate
Dehydrogenase (G6PD) deficiency → Defects in the Pentose Shunt → Susceptibility to oxidative stresses & formation of Methaemoglobin

Which of the 2 enzyme deficiencies is more common
Glucose-6-phosphate dehydrogenase (G6PD) deficiency (pentose)
Outcome of Pyruvate Kinase (PK) Deficiency
Chronic Haemolysis
Treatment for Pyruvate Kinase (PK) Deficiency
Splenectomy may be needed in severe cases.
Blood film features (2) of Pyruvate Kinase (PK) Deficiency
Polychromasia
Spheroacanthocytes / ‘prickle cells
Inheritance pattern of Glucose-6-phosphate dehydrogenase (G6PD) deficiency
X-Linked Recessive
Risk factors for Glucose-6-phosphate dehydrogenase (G6PD) deficiency
Male (X-Linked Recessive inheritance)
Mediterranean & Afro-Caribbean ethnicity
Haemolysis Triggers - Infection, broad beans, medications (dapsone)
Sx of Glucose-6-phosphate dehydrogenase (G6PD) deficiency
Neonatal jaundice
Acute episodic haemolysis
How is Glucose-6-phosphate dehydrogenase (G6PD) deficiency diagnosed
Clinical
Blood Film (during episode)
Confirmatory assay for G6PD activity outside acute event
Blood film feature of G6PD Deficiency
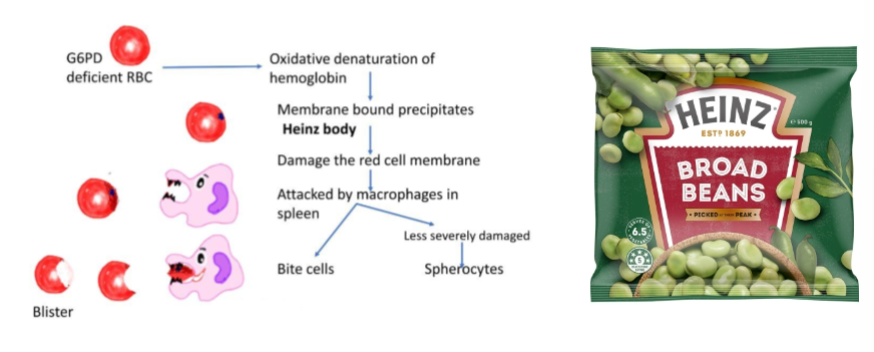
Bite cells
Spherocytes
(Heinz beans - risk factor = broad beans)

How does G6PD Deficiency → Heinz bodies, Bite cells & Spherocytes
What can lead to Antibody mediated red cell destruction
• Allo-antibodies (e.g. Transfusion reactions)
• Autoimmune Haemolytic Anaemia
How can Autoimmune Haemolytic Anaemia be classified
Primary vs Secondary (SLE, Rheumatoid Arthritis, CLL..)
Warm vs Cold (according to the temperature at which antibodies react)
Name 2 drugs that can induce Autoimmune Haemolytic Anaemia
Penicillin
Quinidine
What happens in Autoimmune Haemolytic Anaemia
Antibody coated red cells are consumed in the spleen & lose membrane to form Spherocytes
2 tests to diagnose Autoimmune Haemolytic Anaemia
Haemolysis
Positive Direct Antiglobulin (Coombs) Test
Treatment for Autoimmune Haemolytic Anaemia
Immunosuppression: Steroids, Rituximab.
Splenectomy (rare)
How is a Direct antiglobulin test (Coombs Test) done

What is Microangiopathic Haemolysis
Destruction of red cells due to abnormalities in small vessels
How does Microangiopathic Haemolysis present on a blood film
Red cell Fragmentation

3 causes of Microangiopathic Haemolysis
– Haemolytic Uraemic Syndrome (HUS)
– Thrombotic Thrombocytopenic Purpura (TTP)
– Disseminated Intravascular Coagulation
During what phase of malaria is Haemolysis seen most
Haemolysis particularly with Falciparum & High Parasite loads during erythrocytic phase of illness
How is Haemolytic Anaemias of infections/malaria similar to anaemia of chronic disease
Hepcidin
Is the connection between anaemia & kidney function strong
Yes! 90% of patients with GFR <25 are Anaemic
New unexplained Anaemia + Renal Failure points towards what
Myeloma
4 features of Renal Failure Associated with Multifactorial anaemia
• Inadequate EPO
• Uraemia – mild haemolysis
• Blood Loss (e.g. Haemodialysis)
• Secondary Hyperparathyroidism
Treatment for Renal Failure Associated Multifactorial anaemia
• Treat underlying cause
• rEPO in some cases
• Ensure iron replete (Ferritin unreliable)
Sign of Marrow Failure
Pancytopenia
If marrow failure is caused by malignancy, what will show a blood film
Blast cells
If marrow failure is caused by Fibrosis / infiltration, what will show a blood film
Teardrop cells
How is marrow failure diagnosed
Bone marrow aspirate

Name a virus that can cause anaemia
Parvovirus B19 / Erythrovirus B19
How does Parvovirus B19 / Erythrovirus B19 usually present
Slapped cheek syndrome in children
Transient arthritis or asymptomatic in adults
85% of elderly persons have serological evidence of past infection

When would Parvovirus B19 / Erythrovirus B19 cause symptomatic anaemia
In Immunosuppression or Chronic Haemolysis
7 tests to do in a Macrocytosis Work-Up
• Reticulocyte Count
• Blood Film (Megaloblastic, MDS Changes)
• Vitamin B12 and Folate levels
• TFT’s
• Liver Function Tests
• +/- Haemolysis screen
• +/- Bone Marrow Biopsy
Megaloblastic anaemia cause
Impaired DNA production
Megaloblastic Anaemias characteristic feature
Characteristic Bone Marrow Appearance
How do B12 & folate affect DNA

What happens if you consume too much B12
Body stores B12 in excess
Absorption of B12 requires what 4 conditions
Functioning:
Salivary Proteins (haptocorrin – protects B12 from stomach acid)
Stomach (Acid + Parietal cells - Intrinsic Factor)
Pancreas (Calcium Supply)
Small Intestine (Absorption of B12-IF Complexes)
Causes of Vitamin B12 Deficiency
Dietary - Vegan diet
Gastric Causes
Pernicious Anaemia
Autoimmune gastritis leads to deficiency in stomach acid + IF (IM replacement vs high dose oral replacement)
Antibodies detectable to gastric parietal cells, intrinsic factor (most specific)
Atrophic Gastritis - Loss of acid production only, may still absorb free Vitamin B12 from supplements
Gastrectomy
Medications:
Proton Pump Inhibitors / Antacids
Metformin
Nitrous oxide
Pancreatic Insufficiency
Small Bowel
Coeliac Disease
Crohn’s Disease
Sx of Vitamin B12 Deficiency
Symptoms of Anaemia
Neurological Symptoms
Peripheral Neuropathy
Subacute combined degeneration of the cord
Dementia
Glossitis
Macrocytosis / Anaemia
Pancytopenia if Severe
Raised LDH (destruction of red cells)
Causes of folic acid deficiency
Dietary Deficiency
• Alcoholism
• Elderly (“tea and toast” diet)
• Total Parenteral Nutrition
Malabsorption
• Coeliac disease
• Crohn’s disease
Increased Demand
• Pregnancy (Neural Tube Defect Risk)
• Growth spurts
• Chronic Haemolysis
• Haemodialysis
Clinical features / Sx of folic acid deficiency
• Haematologic features similar to B12 deficiency
• No neurological disturbance
• Mild jaundice (ineffective red cell production & haemolysis)
• May have features of Haemolytic anaemia if due to increased requirements
What B12 & folate levels are considered deficiencies
B12 <125
Folate <2
What is considered between 125-300 B12 & 2-4 Folate
Indeterminate
• Red Cell Folate (more specific)
• Methylmalonic Acid Levels (raised only in B12 deficiency)
• Clinical context
• Trial of Tx
• Consider other causes
Folate Deficiency treatment
• PO Folate 5mg Orally
• Consider need for B12 replacement
• Consider underlying cause
B12 Deficiency treatment
• Usually parenteral B12 (Intramuscular)
• Neurological symptoms generally resolve
• Consider underlying cause..
• Lifelong replacement required for Pernicious Anaemia
When anaemia is present with Folate & B12 deficiency and you give treatment, what is a marker of response to Tx
Treatment should lead to reticulocytosis
3 Causes of macrocytosis
Alcohol Excess (most common)
Liver disease
Hypothyroidism (rare)
3 causes of Non-Megaloblastic anaemia
– Liver disease
– Myelodysplastic Syndrome
– Alcoholism
What is Myelodysplastic Syndrome (MDS)
Spectrum of Malignant Bone Marrow Disorders that → Ineffective / Abnormal blood cell production
Blood features of Myelodysplastic Syndrome (MDS)
Low blood counts:
• RBC: fatigue
• WBC: infection
• Plt: bleeding
Risk associated with Myelodysplastic Syndrome (MDS)
Risk of transformation / Progression to Acute Leukaemia (AML)
Differentiate between Thalassaemia vs Haemoglobinopathy

Where in the world are thalassaemia / sickle cell anaemia seen

What is wrong in Thalassaemias
Impairment of production of one globin chain leads to
• Reduced Haemoglobin (microcytosis)
• Imbalance, precipitates of excess globin chains, red cell damage + Haemolysis
How would anaemia develop from Thalassaemias
In milder forms of thalassaemias, increased RBC production can compensate, but in more severe forms anaemia develops
What is Beta Thalassaemia trait
Heterozygosity for Beta Thalassaemia gene
Presentation of Beta Thalassaemia trait
Microcytosis without Anaemia
How is Beta Thalassaemia trait diagnosed
Haemoglobin analysis - Increased Hb A2 (2α + 2δ)
What is Beta Thalassaemia Major
Homozygosity for βo or β+
Clinical severity of Beta Thalassemia Major
Severe
What actually happens in Beta Thalassemia Major
Failure of HbA to take over

Beta Thalassemia Major leads to
Expanded, ineffective haematopoiesis → Transfusion dependent anaemia
Describe Beta Thalassemia Major blood film

Treatment for Beta Thalassaemia Major
Transfusion Support
Management of Iron Overload
Bone Marrow Transplant
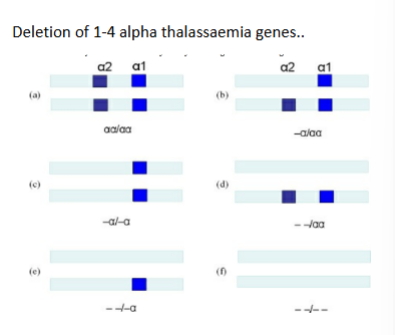
Outcome of Alpha Thalassaemia with 1-2 gene deletion
• Microcytosis
• Asymptomatic
Outcome of Alpha Thalassaemia with 3 gene deletions
• ‘Haemoglobin H Disease’
• Microcytic anaemia
• Haemolysis and Splenomegaly
Outcome of Alpha Thalassaemia with 4 gene deletions
• Homozygous for α0
• Haemoglobin Barts / Hydrops Fetalis
• Non-functional Hb Barts (4γ chains)
• Fatal in utero or in neonatal period
Name Haemoglobinopathies associated with Africa & SE Asia (separateley)
Haemoglobin S & C (African ancestry)
Haemoglobin E (SE Asia)
Most severe Haemoglobinopathy
Haemoglobin S
Haemoglobin S Haemoglobinopathy →
Sickle Cell Disease
S Haemoglobinopathy mutation
Glu -> Val
When is Haemoglobin S insoluble
Insoluble at concentrations >60% when low partial pressures of O2
What happens RBCs in S Haemoglobinopathy
Crystallisation → Sickle shaped red cells
What is Sickle Cell Trait
Heterozygosity for HbS
What % of HbS is Sickle Cell Trait
45%
Significance of Sickle Cell Trait
It is of genetic, but rarely of clinical significance