Kidney (COMPLETE)
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/414

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
415 Terms
What is anuria?
No urine output
What is oliguria?
Less than 1 L per day of urine
What should be the normal levels of urine?
1-2 L per day
What is polyuria?
>2 L per day of urine
What is azotemia?
Biochemical elevation of:
BUN
Creatinine
In response to a decreased GFR
Why do BUN and creatinine levels increase in azotemia?
The increased levels reflect a decreased GFR
What causes prerenal azotemia?
Hypoperfusion
Hemorrhage
Shock
Volume depletion
CHF
What causes postrenal azotemia?
Obstruction of urine flow distal to the kidney
Ex. Kidney stones
What is uremia?
Azotemia + systemic metabolic/endocrine effects
GI
Heart
Peripheral nerves
How does uremia affect other organs/structures?
GI — Uremic gastroenteritis
Peripheral nerves — Peripheral neuropathy
Heart — Uremic fibrinous pericarditis
What is the normal excretion amount in proteinuria?
40-150 mg/day
What amount is usually asymptomatic in proteinuria?
1-3 g/day
What contributes to asymptomatic proteinuria?
Reflects increased glomerular permeability
Impaired tubular reabsorption contributes to low-level proteinuria
What is nephrotic-range proteinuria?
≥3.5 g protein/day
Massive proteinuria
What are the 4 classic features of nephrotic syndrome?
Massive proteinuria
Hypoalbuminemia — plasma albumin <3 g/dL
Generalized edema
Hyperlipidemia and lipiduria
What are major complications of nephrotic syndrome?
Increased susceptibility to:
Infection (staphylococcus and pneumococcus)
Thrombotic and thromboembolic complications
What classifies hematuria?
>5 RBC/HPF
Glomerular bleeding often shows dysmorphic RBCs and RBC cast
What characterizes nephritic syndrome?
Hematuria with RBC casts
Mild-to-moderate proteinuria (usually <1 g/day)
Elevated creatinine
Oliguria
Hypertension
Mild-to-moderate edema → Periorbital edema
What do dysmorphic RBCs indicate?
Glomerular hematuria
What are key features of rapidly progressive GN (RPGN)?
Rapid decrease in renal function (≥50% in 3 months)
Crescents on bx
What are key features of isolated hematuria/proteinuria?
Asymptomatic
No other renal findings
What are key features of chronic renal failure?
Prolonged azotemia/uremia
Uremic symptoms
What is Tamm-Horsefall protein?
A renal glycoprotein secreted in the tubules that forms the essential gel matrix (backbone) that traps red blood cells to create RBC casts
A key sign of glomerular bleeding
What are the macroscopic tests on urinalysis?
Color
Red/brown urine:
Hematuria vs hemoglobinuria/myogloinuria vs. drugs/foods
What is the purpose of a dipstick in urinalysis?
Tests for:
pH
Protein
Blood
Leukocyte esterase
Nitrates
Glucose
Ketones
in the urine
What are the microscopic tests on urinalysis?
Tests for:
Cells
Casts
Crystals
Some are normal; Certain ones are NOT
in the urine
What type of tests are used for renal and urinary tract disease?
Major noninvasive diagnostic tools
What do fatty urinary casts indicate?
Nephrotic syndrome (lipiduria)
What do hylaine urinary casts indicate?
Nonspecific
Concentrated urine
Exercise
What do RBC urinary casts indicate?
Glomerulonephritis — Specific for glomerular bleeding
What do WBC urinary casts indicate?
Polynephritis
Interstitial nephritis
What do granular urinary casts indicate?
Nonspecific tubular injury
What do waxy urinary casts indicate?
Chronic renal failure
Urinary stasis
What crystal types are normally seen in urinary analysis?
Uric acid
Calcium oxalate
Triple phosphate
(Usually no pathologic significance)
What are some drug-induced crystal types seen in urinary analysis?
Sulfonamides
Indinavir
(Usually benign)
What are some pathologic crystal types seen in urinary analysis?
Cystine (cystinuria)
Calcium oxalate (ethylene glycol toxicity)
What crystals are these pictures microscopically showing?
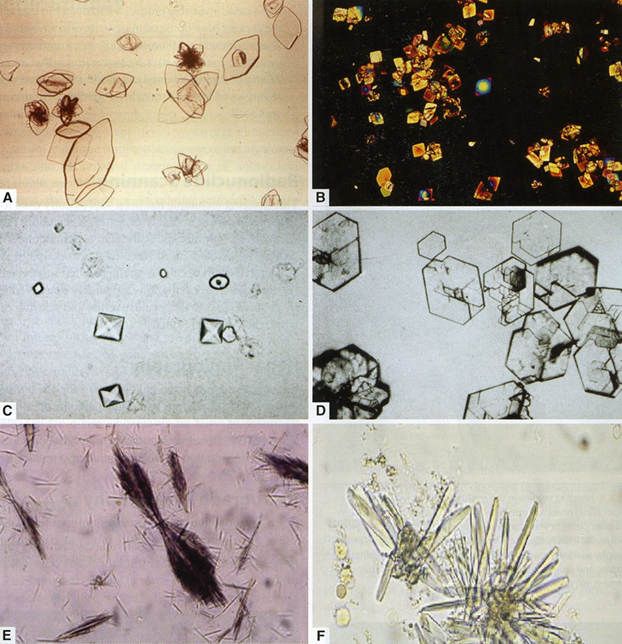
A. Uric acid
B. Uric acid stone disease
C. Calcium oxalate
D. Cystine crystals
E. Wheat-like
F. Calcium phosphate
What causes nephrotic syndrome?
Excessive glomerular permeability to plasma proteins
What is the most common cause of nephrotic syndrome in children?
Minimal change disease
What is the typical age for minimal change disease?
Children
Peak incidences — Ages 2–6
What does minimal change disease look like on LM?
Glomeruli appear normal
What does minimal change disease show on EM?
Diffuse podocyte foot-process effacement
No immune deposits
How does minimal change disease respond to steroids?
Excellent response → Excellent prognosis
[Selective proteinuria (albumin only)]
What can minimal change disease sometimes follow?
Respiratory infection
Routine prophylactic immunization
What does FSGS mean?
Focal segmental glomerulosclerosis
Focal = Some glomeruli affected
Segmental = Only subset of glomeruli is affected by sclerosis
Not global/diffuse
What is the most common cause of nephrotic syndrome in adults?
Focal segmental glomerulosclerosis (FSGS)
10-35%
Membranous nephropathy
What are primary cases of FSGS?
Idiopathic
Podocyte injury
What are secondary cases of focal segmental glomerulosclerosis (FSGS)?
HIV
Heroin use
Obesity
Reflux nephropathy
What is the LM finding in FSGS?
Segmental sclerosis
Hyalinosis
What is the EM finding in FSGS?
Foot process effacement
What FSGS variant is associated with HIV?
Collapsing glomerulopathy
(An aggressive variant)
How does FSGS respond to steroids?
Less responsive than minimal change disease → Progress to chronic kidney disease
What are the primary causes of membranous nephropathy?
85% idiopathic
Anti-PLA2R antibodies
What are the secondary causes of membranous nephropathy?
15% secondary
SLE
Hepatitis B/C
Drugs
Malignancy
What is the LM finding in membranous nephropathy?
Diffuse thickening of glomerular capillary walls

What are IF findings in membranous nephropathy?
Granular IgG and C3 deposits
Where are the granular IgG and C3 deposits locally seen on EM for membranous nephropathy?
Subepithelial deposits
“Spikes” on silver stain

What is the overall prognosis for membranous nephropathy?
Variable course
NOT steroid-responsive
What causes membranoproliferative glomerulonephritis (MPGN)?
Combination of:
Nephrotic features
Nephritic features
A pattern of immune-mediated injury rather than a specific disease
What is the classic LM finding in MPGN?
Hypercellularity
Thickened GBM w/ tram-track/double-contour appearance

What causes Type I MPGN?
Immune-complex-mediated injury with subendothelial deposits
What is Type II MPGN called?
Dense deposit disease
What causes Type II MPGN?
Dysregulation of the alternative complement pathway
Where are the deposits in Type II membranoproliferative glomeurlonephritis (MPGN)?
Intramembranous dense deposits
What demographic typically presents MPGN?
Adolescence and young adults
How is MPGN treated?
Steroid treatments typically NOT helpful
With 10 years → 50% of pts develop chronic kidney failure
Disease follows a slow progressive but unremitting course
What is diabetic nephropathy role in the US?
Leading cause of:
Nephrotic syndrome
End-stage renal disease
What are the major renal lesions in diabetic nephropathy?
Diffuse and nodular (Kimmelstgiel-Wilson) glomerulosclerosis
What is Kimmelstiel-Wilson disease?
Nodular glomerulosclerosis caused by diabetic nephropathy
Shows up on PAS+ stain
What happens to the renal arterioles in diabetic nephropathy?
Hyaline arteriolosclerosis affects both afferent and efferent arterioles
What happens microscopically in diabetic nephropathy?
Thickened GBM
Mesangial matrix expansion
What can diabetic nephropathy led to?
Increases susceptibility to pyelonephritis
What is acute proliferative (poststreptococcal) GN?
Immune complex-mediated
Occurs 1–4 weeks AFTER streptococcal pharyngitis or impetigo
What is the classic urine appearance in acute proliferative (poststreptococcal) GN?
Cola-colored/Brown urine
What demographic is most commonly susceptible to acute proliferative (poststreptococcal) GN?
Child 6-10 y/o
What are common symptoms of acute proliferative (poststreptococcal) GN?
Periorbital edema
Oligura
What is the LM findings of acute proliferative (poststreptococcal) GN?
Enlarged, hypercellular glomeruli with neutrophils
What are the IF findings of acute proliferative (poststreptococcal) GN?
Granular IgG, IgM, and C3
What are the EM findings of acute proliferative (poststreptococcal) GN?
Subepithelial humps
What is the prognosis of acute proliferative (poststreptococcal) GN?
>95% of children recover fully
What conditions can cause acute proliferative (poststreptococcal) GN?
Nonstreptococcal causes include:
Endocarditis
Hepatitis B/C
Malaria
What defines rapidly progressive (crescentic) GN (RPGN)?
Severe glomerular injury
Rapid decline in renal function (≥50% within 3 months)
With crescents in >50% of glomeruli
What is a histological hallmark of RPGN?
Crescents in >50% of glomeruli
What forms the crescents in RPGN?
Parietal epithelial cells + Macrophages/monocytes + Fibrin in Bowman space (compressed the space)
What are the 3 mechanical types of RPGN?
Anti-GBM
Immune-complex
Pauci-immune
What is the IF pattern in anti-GBM disease?
Linear IgG and C3 along the GBM
What is Goodpasture syndrome?
Anti-GBM disease involving both kidneys and lungs
Causes pulmonary hemorrhage
What is the target antigen in Goodpasture syndrome?
α3 chain of type IV collagen (NC1 domain)
How is anti-GBM disease treated?
Plasmapheresis + immunosuppression
What is the IF pattern in type II: immune-complex RPGN?
Granular/"lumpy-bumpy" deposits
What diseases can cause type II: immune-complex RPGN?
Poststreptococcal GN
Lupus nephritis
IgA nephropathy
Henoch-Schönlein purpura
What characterizes type III: pauci-immune RPGN?
Little or no immune deposition
Commonly ANCA-associated
What diseases are associated with type III: pauci-immune RPGN?
Wegener granulomatosis with polyangiitis
Microscopic polyangiitis
What can cause type III: pauci-immune RPGN?
Many cases are idiopathic
What is IgA nephropathy also called?
Berger disease
What are two types of hematuria groups?
IgA nephropathy (Berger disease)
Alport syndrome and thin basement membrane disease
What is the most common GN worldwide?
IgA nephropathy
When does hematuria occur in IgA nephropathy?
Shortly AFTER a mucosal respiratory or GI infection
Infection → increased IgA circulation
What is a symptom of IgA nephropathy?
Recurrent gross or microscopic hematuria
Where are the immune deposits in IgA nephropathy?
Mesangium