L11-12: N/V p1 and p2
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/64

There's no tags or description
Looks like no tags are added yet.
65 Terms
What is nausea?
subjective feeling of impenidng vomitting or need to vomit
Retching
spasmodic contractions of diaphragm and intercostal muscles
Vomiting (emesis)
forceful oral expulsion of gastric contents
GI retroperistalisis
often associated with pallor, tachycardia, diaphoresis
What are the afferent impulses (stimuli) ? (4)
chemical signals
visceral signals
vestibular input
cortical input
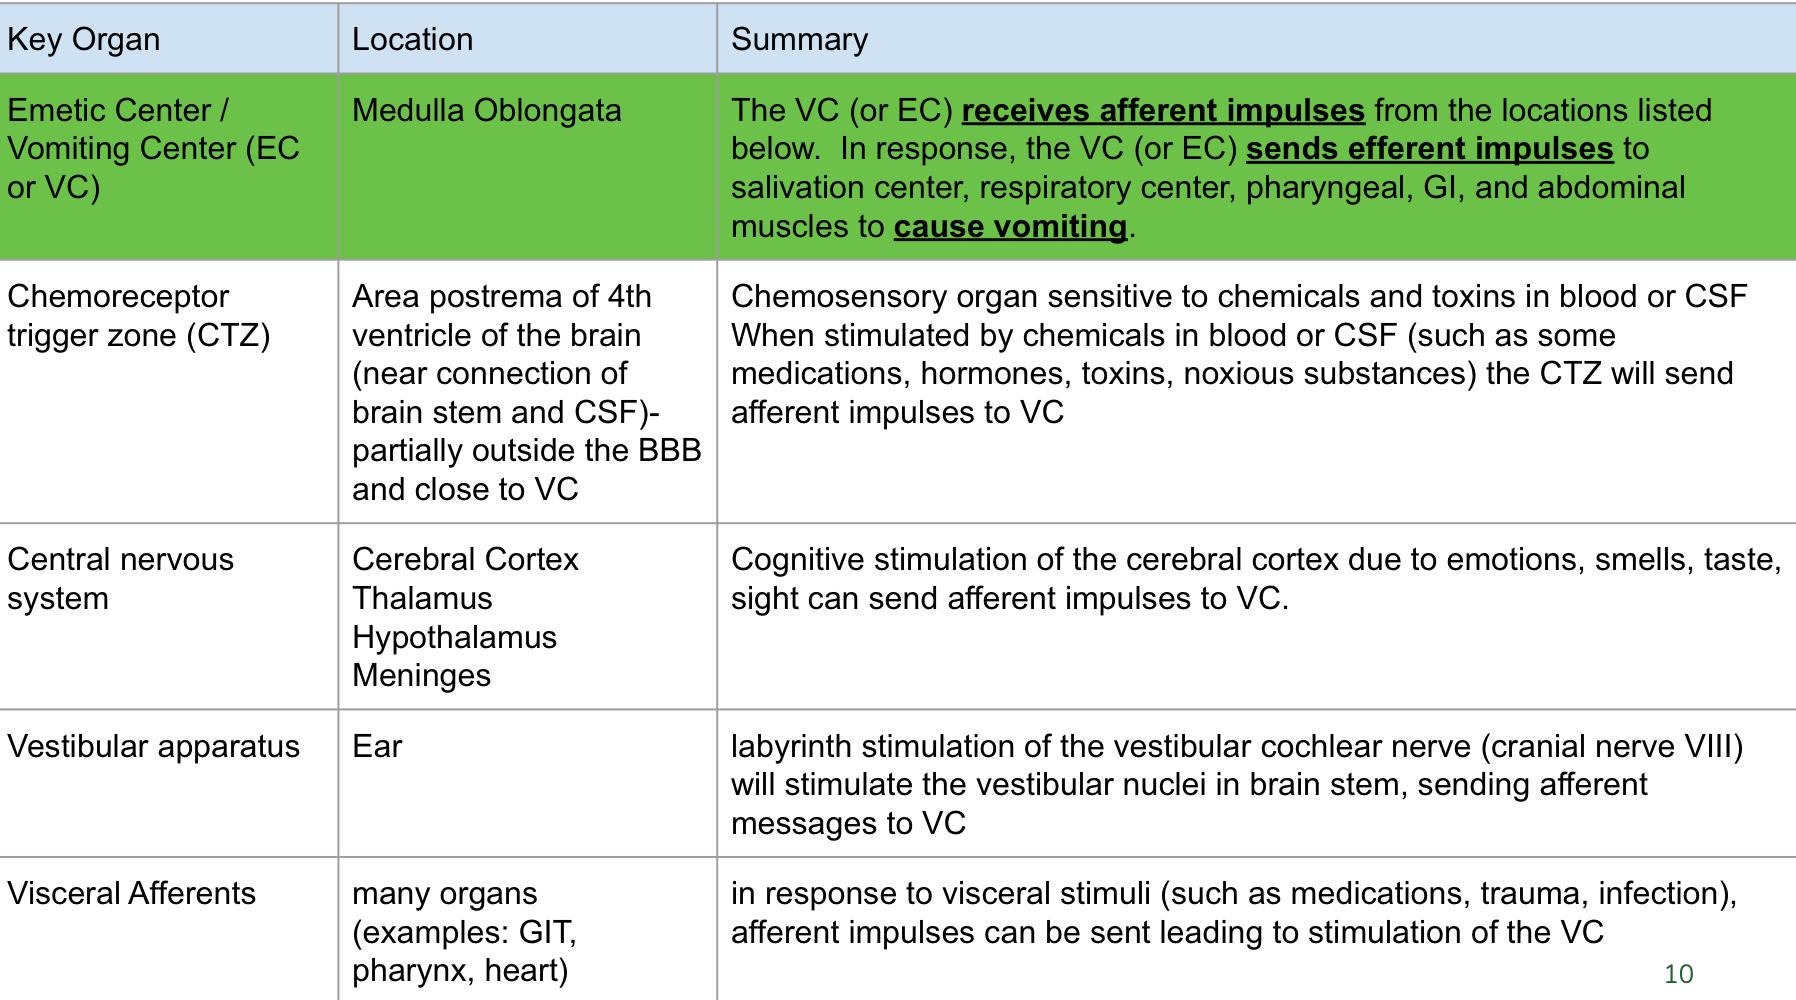
How are these organs involved in vomiting?
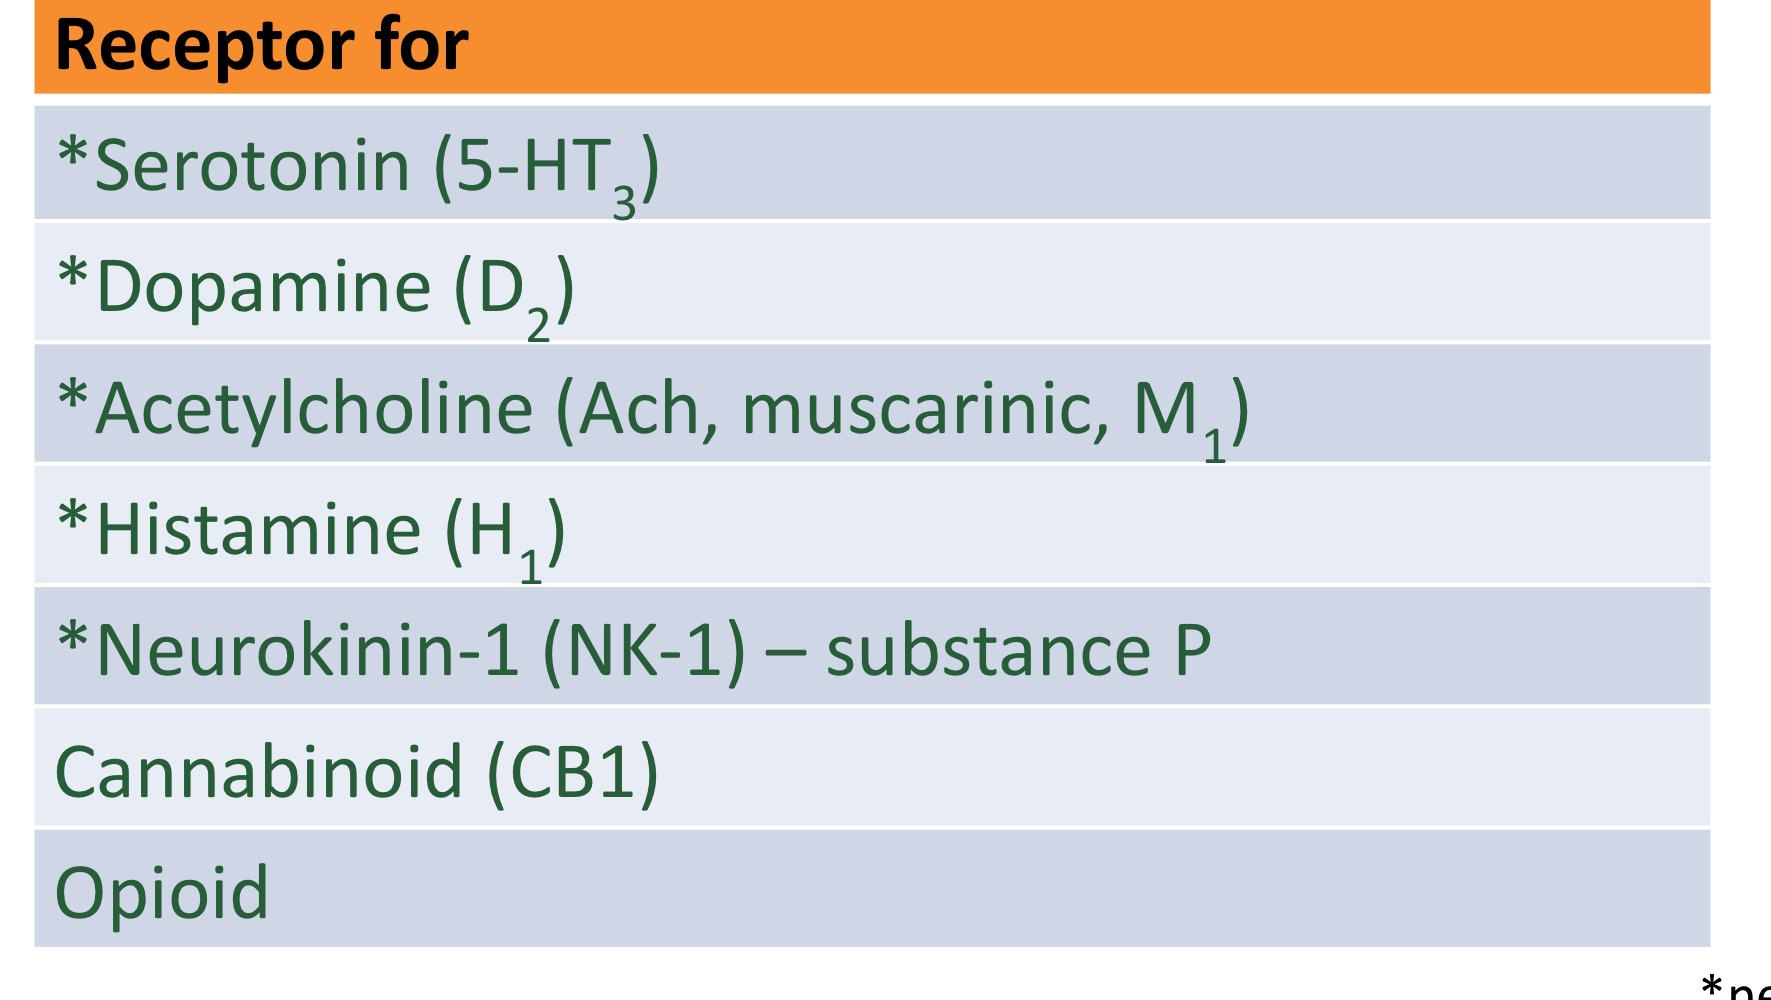
Which receptors are involved in the emetic reflex
What are the causes of N/V? (5)
motion sickness
NV of pregnancy
post op n/v (PONV)
medcaitions → antineoplastic induced n/v or chemotherapy
radiation therapy
diseases → infections, cardiac, GI, metabolic/endocrine, CNS, psychiatric
What are the complications of vomitting? (3)
fluid, electrolyte and metabolic alterations
aspiration penumonia
prolonged vomiting
What are the conseuqneces of fluid, electrolyte and metabolic alterations? (7)
dehydration
hypotenison
hemoconcentration
oliguria
muscle weakness
electrolyte abnormalities
cardiac arrythmias
What are the consquences of prolonged vomiting? (5)
Nutritional deficiencies - malnutrition
Esophagitis (inflammation of esophagus)
Lacerations at the gastroesophageal junction*
Multiple purpuric lesions
Dental caries/erosions
What is the 3 step approach for N/v?
Recognize and correct any consequences of the vomiting e.g. dehydration, electrolyte abnormalities
Identify underlying cause for NV.
Treat/manage underlying cause. If no etiology can be determined use empiric therapy to treat symptoms.
What are the goals of therapy? (4)
Prevent/halt nausea and/or vomiting
Prevent complications such as dehydration
Improve quality of life
Additional goals depending on etiology (eg AINV goal – maintain anticancer therapy schedule)
What should be included in assessing for NV?
Assess signs and symptoms:
SCHOLAR
Gather additional patient information (recent events and long-standing issues)
Medical history (acute and chronic)
Medication history (new and ongoing) prescription, non-prescription, herbal
Social history (including recent experiences)
Allergies (food and drug)
Physical Exam?
Rule out Red Flags (or refer if present)
refer if complications present (signs/symptoms of significant dehydration)
refer if etiology (cause) requires medical attention
Give examples of SCHOLARE as part of ax

What types of physical ax is done? (4)
signs of dehydration
abdominal examination
neurological examination
signs of psychiatric cause
What are signs of dehydration? (4)
dry mucous membranes
increased thirst
reduced urination
weak/dizzy/lightheaded
What are signs of dehydration in children? (4)
few or no tears when crying,
less wet diapers,
sunken eyes,
skin tugor
What are the red flags? (7)
Symptoms of moderate-severe dehydration
may need aggressive rehydration with IV fluids
Persistent vomiting
may be a worrisome infectious cause and high risk of complications
Blood or “coffee-grounds” in vomitus
ulcer or other bleeding?
Blood in stools (black or tarry)
GI bleed? cancer?
Severe pain
abdominal - appendicitis? pancreatitis? cholecystitis? serious infection?
chest - myocardial infarction?
pelvis - pelvic inflammatory disease?
Altered mental status, neurologic symptoms, disorientation
intracranial disorder, stroke, or complication of dehydration?
Recent head trauma
concussion? brain injury?
What are other factors to consider?
difficulty swallowing (dysphagia)
age > 55 → not a sole factor, if can assess and determine cause then don’t necessarily need to refer
weight loss, unintended
s/s of prolonged vomiting
What should be considered when approaching treatment options? (4)
what is the cause
how severe are the symptoms
if pharmcotherapy is indicated, can they swallow oral formulations?
what has already been tried with what success?
What non pharm therapy is appropriate? (5)
adequate hydration
avoid noxious odors/foods that cause nausea
eat frequent small meals
decrease physical activity
gear approach to cause/etiology
if labyrinth changes produced by motion then…
assume stable position
Should patients maintain fluid intake? (3)
Depends on amount of vomiting
Normal amounts - adults need 1-3 L of total water intake
Amount required will depend on amount lost with vomiting (and/or diarrhea)
Moderate or severe vomiting may require electrolyte replacement:
E.g. oral rehydration solution (ORS) - as discussed in diarrhea lecture
What is the role of acupressure in n/v?
Sixth point along the pericardial meridian (P6)
Nei Guan (“inner guard”)
approximately three finger breadths below the wrist on the inner forearm between the two tendons
3 - 5 minutes of pressure every 4 hours
NVP, motion sickness, AINV, PONV
role of acupuncture?
?
Can patients use the acupressure wristbands?
Yes, however it has not been shown to be effective in motion sickness
less effective than manual pressure
What rx agents are available for NV? (6)
H1RA
D2RA
5HT3RA
NK1RA
GCs
Cannabinoids
What are examples of H1 receptor antagonists? (3)
dimehydrinate (gravol)
diphenhydramine (Benadryl)
hydroxyzine (prescription)
What is the role of H1RAs? (3)
management of motion sickness, vertigo and mild gastroenteritis
What are the primary side effects of H1R antagonists? (6)
also has antichol. effects
drowsiness
confusion
dry mouth, blurred vision
urinary retention
constipation
What is the concern with elderly and H1RAs?
They are at increased risk of anticholinergic side effects
What are examples of D2RAs used? (3)
class and drugs
Antipsychotics
phenothiazines: chlorpromazine, promethazine, prochlorperazine
butyrophenones: haloperidol
2nd gen: olanzipine
What is the role of D2RAs in NV?
Severe n/v, NVP, PONV, AINV
What are side effects of D2RAs? (7)
has anticholinergic and antihistamine effects therefore…
drowsiness
EPS:dystonic rxns, tardive dyskinesia
olanzapine may have less of this
postural hypotension
dry mouth and other anticholinergic
hyperprolactinemia
QT prolongation (more so wiht haloperidol)
elderly more prone to anticholinergic
What are the side effects of metoclopromide and domperidone?
drowsiness
EPS
prolongation of QT interval, arrythmias - only domperidone
increase prolactin release (breast tenderness, galactorrhe
Why is domperidone only used short term?
Due to QT prolongation
Which 5HT3RAs are used? (3)
ondansetron
granisetron
palonosteron
What are the indications for
ondansetron
granisetron
palonosetron
AINV, PONV
AINV
AINV
What are the side effects of 5HT3RAs? (5)
Constipation
Headache
lack of energy/weakness
risk of serotonin syndrome (rare; in combination with other serotonergic and/or neuroleptic drugs)
dose-dependent QT interval prolongation (rare)
What NK1RAs are used? (3)
PO = aprepitant (emend)
IV = fosaprepitant (prodrug)
combo PO = netupitant + palonosetron
What is the role of NK1RA ? (2)
used in combo w/ 5HT3RAs and dexamethasone for AINV
can also be used in PONV
What DIs does aprepitant have? (2)
inducer AND inhibitor of CYP3A4
inducer of CYP2C9
How is GC used in n/v?
MOA
EXAMPLE
INDICATION
SIDE EFFECTS SHORT TERM
SIDE EFFECTS LONG TERM
MOA - not well understood
example - dexamethasone (most common)
indication: PONV, AINV, radiation induced NV
Side effects: short term but fluid electrolyte disturbances, hyperglycaemia, infections, psychosis
long term: osteoporosis
How are cannabinoids used?
examples
indication
side effects
synthetic cannabinoids → nabilone
role in AINV
use when refractory to other antiemitics
eupohria, sedation, dysphora, hallucinations/paranoia
Role of medical cannabis?
AINV
What NHP options are available? (6)
ginger
vitamin b6
peppermint oil
green tea
lemon balm
What are AEs of ginger? (4)
heartburn, diarrhea
mouth irritation - reduced if EC product
dermatitis if used topically
thought to inhibit thromboxane synthase and decrease platelet aggregation
What drug interactions does ginger have? (2)
anticoags,
antiplatelets
risk of bleeding therefore need to monitor INR
What forms of ginger can be used? (7)
fresh root
dried root
tabs
caps
tincture
tea
food
What triggers vomiting?
Afferent impulses to the vomiting centre (emetic centre)
How does vomiting occur?
Contraction of diaphragm + abdominal muscle.
Relaxation of lower esophageal sphincter.
Peristalsis reverses direction:
pushes stomach contents out of mouth
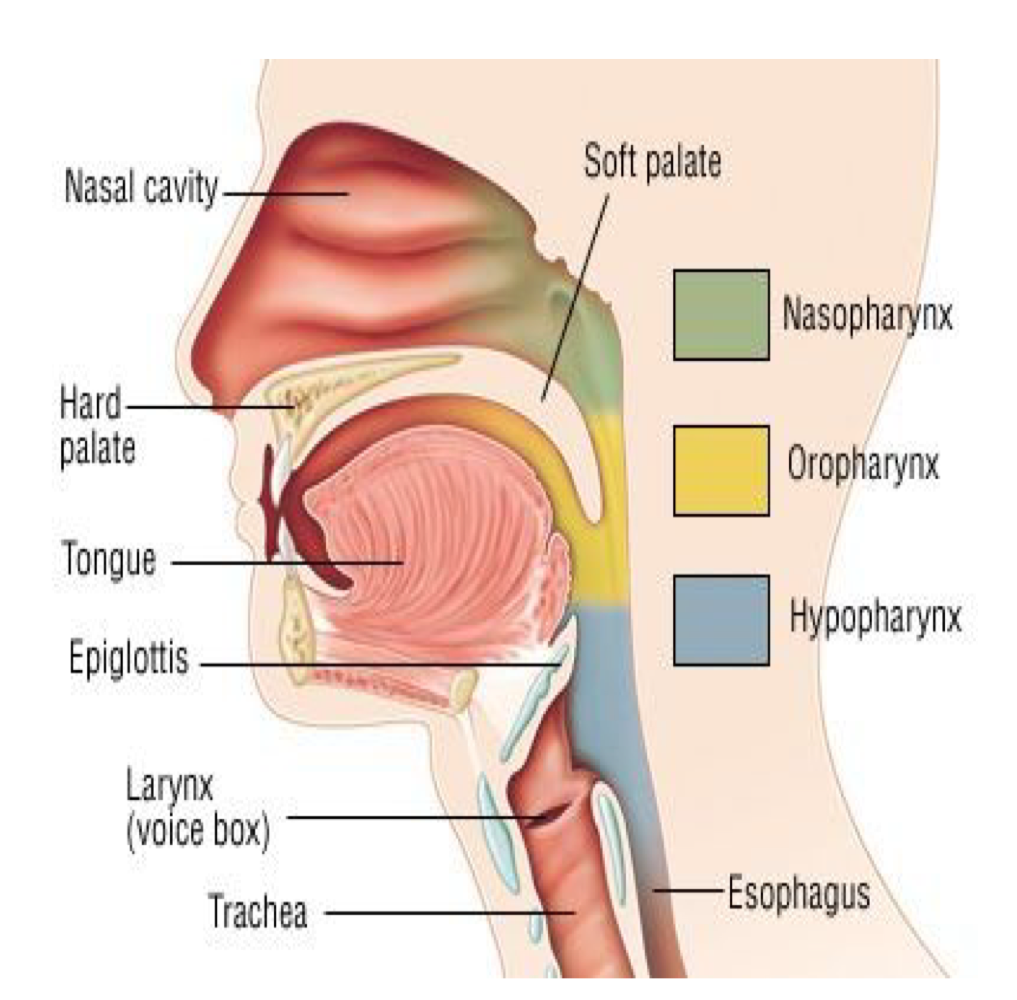
Soft palate is raised to prevent GI contents going into nasopharynx.
Epiglottis closed to prevent pulmonary aspiration.
Which NTs are involved in motion sickness?
ach and histamine
What nonpharm measures are recommended for motion sickness? (7)
stable visual point → clear forward view, minimal head movements
audi visual/non visual stimuli that exacerbate (reading, odors, smoking)
acupressure points (although not effective, maybe for mild)
diet: avoid eating within 3 hours of travel, avoid dairy products or high protein/calories or sodium
increase ventilation
on a boat → sit in central area
avoid visual stimuli that can be triggers → 3d movies, intense video game graphics
What are pharmacological options for motion sickness?
Short duration expected
dimenhydrinate
diphenhydramine or
hydroxyzine
Long duration
scopolamine patch, but not available anymore
What is hyperemesis gravidarum?
extreme, persistent NV during pregnancy
requires hospitalization
dehydration, electrolyte disturbances can occur
nutritional/malnutrition
When does N/V of pregnancy usually occur?
1st trimester
onset around 4 weeks, peaks at 9, disappears by week 20
What causes NVP?
unknown
potentially high estrogen levels but not confirmed
also correlates with hCG but not definitive cause
What are the mainstay nonpharm considered for NVP?
diet - small bland meals
Eat at times of the day when nausea is less
Eat cold foods (hot foods may bother and have stronger scents)
Drink fluids
What other nonpharm can be used for NVP?
acupressure
ginger for mild NVP
What pharmacological options are available for mild NVP?
diclectin = pyridoxine (B6) 10mg + doxylamine 10mg delayed release
pyridoxine alone 25mg
What are the side effects of diclectrin? (3)
drowsiness
disorientation
diarrhea
What are the pharmacological options for moderate to severe NVP? (4)
1st to 3rd line agents
4-5th line
dimenhydrinate – 3rd or 4th line (after pyridoxine, diclectin, ginger).
Also diphenhydramine or promethazine can be an option
If ineffective (4th or 5th line), consider….
phenothiazines – chlorpromazine, prochlorperazine
Metoclopramide
How can gravidarum be managed?
nonpharm
pharm (4)
IV fluids/electrolyte replacement
May consider any of the following:
• Phenothiazines
• Metoclopramide
• Ondansetron
• Corticosteroids for refractory – methylprednisolone
Can ondansetron be used in pregnancy?
potentially for severe/persistent NV or hyperemesis gravidum
caution use in 1st trimester
