Surgery of the stomach, SI, LI, rectum and anus
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/33

There's no tags or description
Looks like no tags are added yet.
34 Terms
What is a hiatal hernia?
Herniation of cardia of stomach through oesophageal hiatus
May present as gastrooesophageal intussusception
How are hiatal hernia graded?
1-4 based on location/ extent
How are hiatal hernia treated?
Surgically if persistent
Suture reduction of hiatus
Oesophagopexy
Left fundic gastropexy
When is a gastrotomy usually performed?
Usually for FB removal but can be exploratory
Outline how a gastrotomy is performed?
Ventral midline coeliotomy.
Pack off stomach and stabilise the avascular area between the greater and lesser curvatures with 3-4 stay sutures.
Incise stomach in this area (mucosa is quite tough) and explore
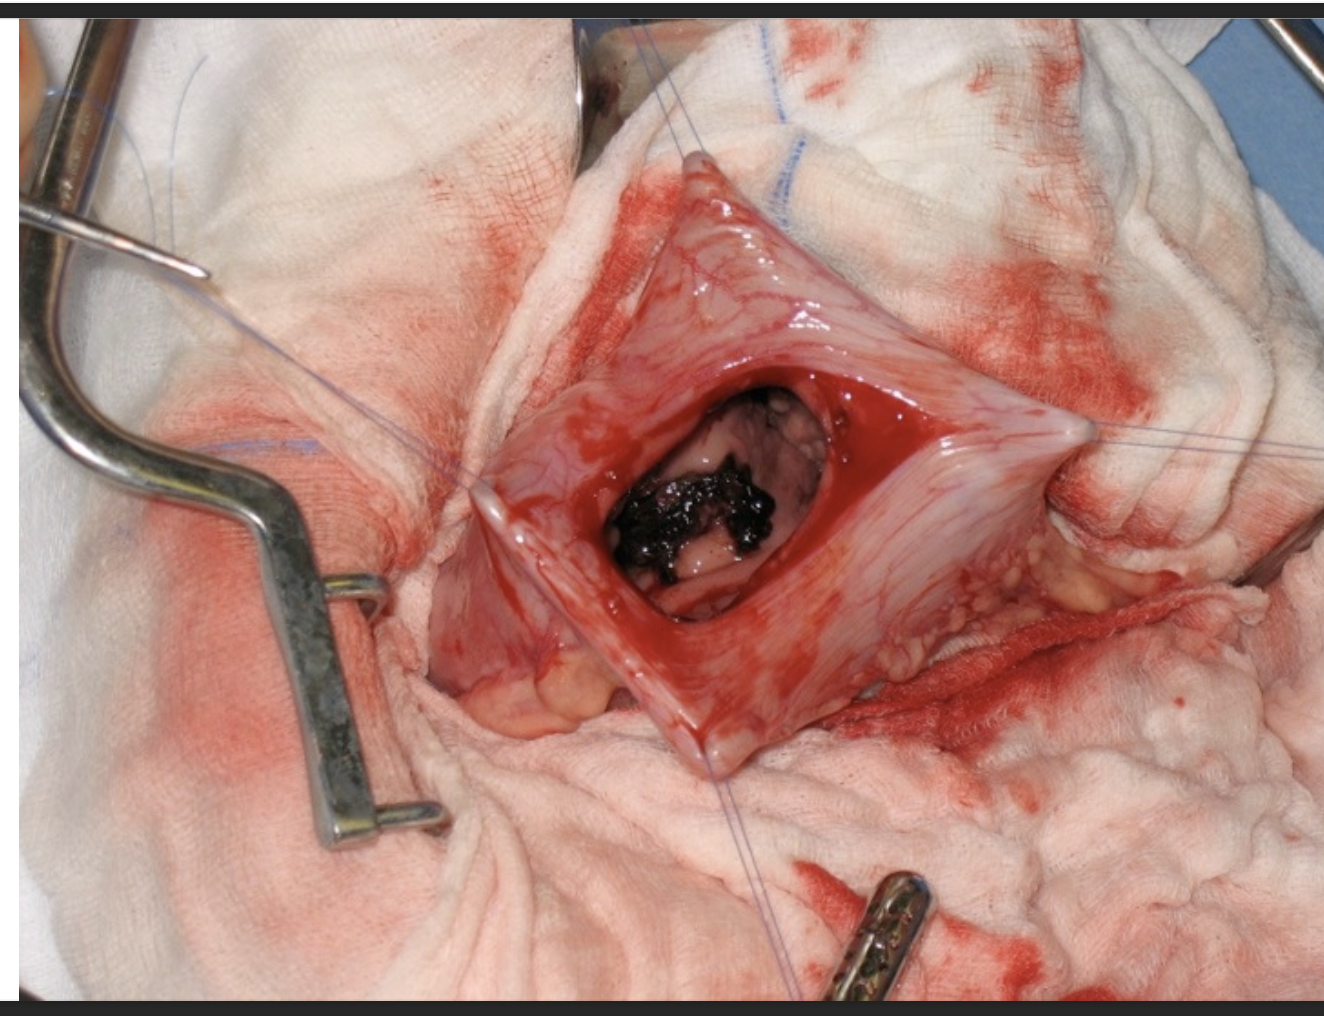
How is a gastrotomy closed?
1 or 2 layer closure
First layer in mucosa or submucosa (contiunous or interrupted / Cushing or lembert)
Second layer in serosa/ muscularis/ submucosa (Cushing or lembert)
When would you perform a partial gastrectomy?
Necrosis (e.g.- in GDV)
Neoplasia
ulceration
What are the different techniques for partial gastrectomy?
Invagination of tissues
Serosa apposed, necrotic tissue allowed to slough
Sharp excision
Surgical staplers
What dogs are predisposed to GDV?
Purebred large / giant dogs
Gordon setter, standard poodle, Weimeraner, Irish setter, great Dane and St. Bernard at greatest risk
Particularly with inc thoracic depth:width ratio
First degree relative with GDV
Fearful/ aggressive temperament
Feeding few meals, eating rapidly
What happens in a GDV
Rotation of stomach (more common clockwise)
180° most common but anywhere from 90-360°
Pylorus moves to left and fundus to right (rotation along long axis)
Oesophagus twists where enters stomach
Stretching and thinning of pylorus occluding outflow as well, causing dilation and other physiological effects
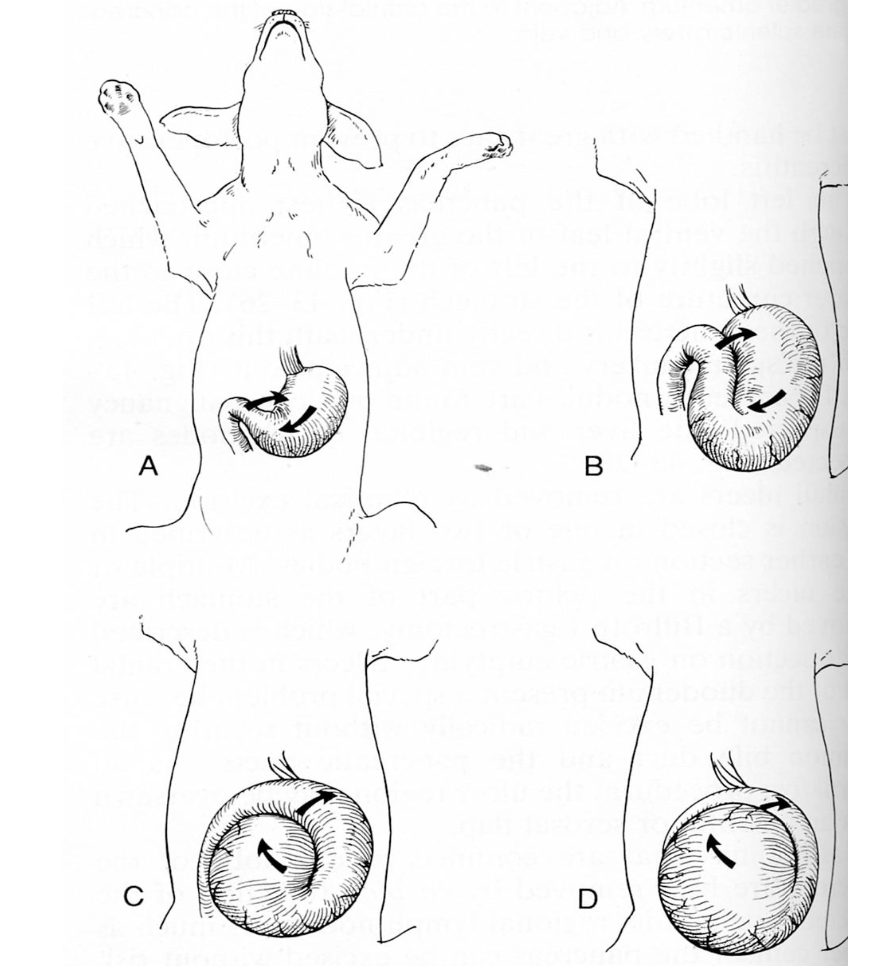
Explain the physiological effects of GDV
Haemodynamic effects
Red abdo blood flow and venous return-> cardiogenic shock-> splenic congestion
Resp dysfunction
Inc pressure limits diaphragmatic movement
Cardiac dysfucntion
Red perfusion
Myocardial depressant factor released causing myocardial ischaemia
Necrosis and arrythmias
Gastric wall necrosis
Vessels compressed reduced perfusion
Bacterial translocation
Sepsis, toxic shock
Reperfusion injury when corrected
What is this radiograph showing?
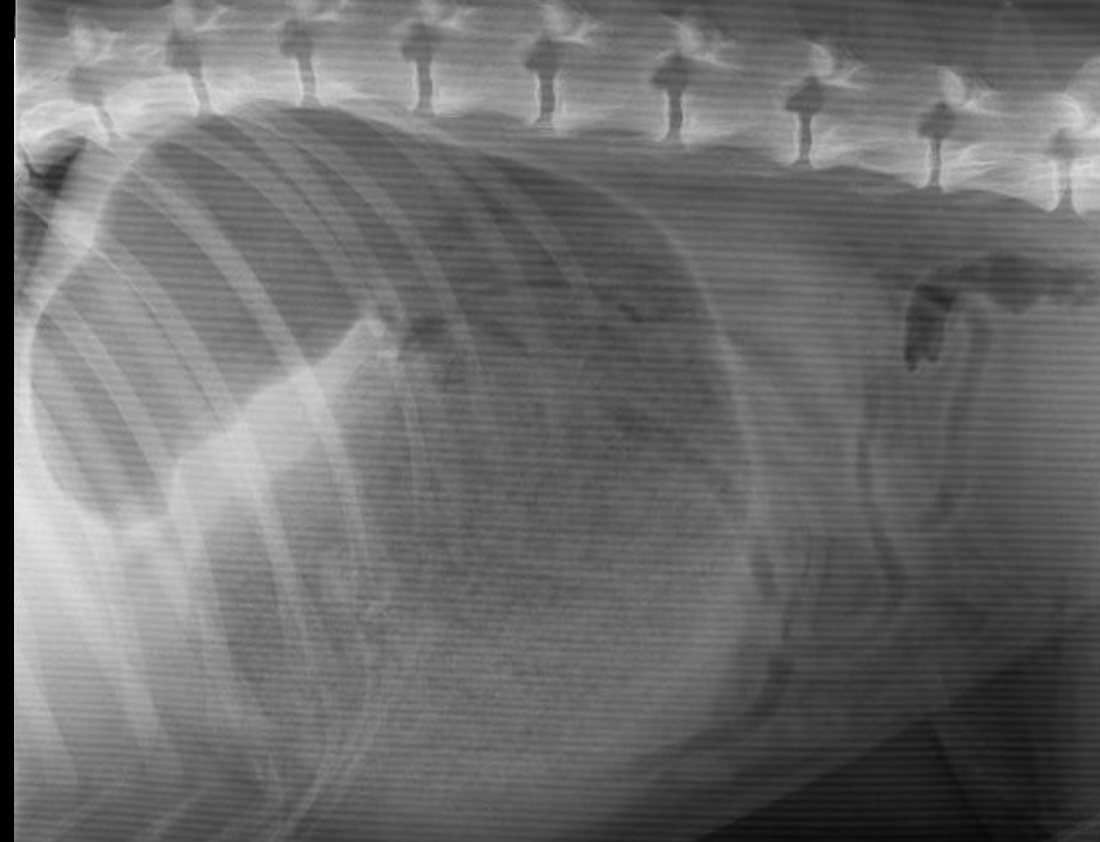
GDV
Typical reverse C shape
What would you see on lab tests with GDV?
Haematology: haemoconcentration, stress leucogram, thrombocytopaenia.
Biochem: inc ALT and bilirubin, increased BUN and creatinine due to hypotension and various electrolyte abnormalities.
Plasma lactate may be helpful inpredicting prognosis and the presence of gastric necrosis
What are your two immediate priorities with a GDV treatment?
Fluid therapy
Decompression of stomach
What do all GDV cases require to prevent reoccurence?
Gastropexy
NB- won't prevent tmpany/dilation
How would you admin fluids for GDV?
Shock therapy
Short wide cannulae, 2 if required (never in HL bc caudal to venous return)
How is decompression of the stomach performed?
Stomach tube
Done conscious
Pass with aid of lub and mouth gag
Turn to aid passage
Cover end on removal to stop fluid spillage and aspiration
Needle paracentesis
14-16g needle via flank
ID gas filled fundus by percussion
Temporary gastrotomy
How is a temporary gastrotomy performed for a GDV?
LA via flank
5cm incision caudal and parallel to costal arch
Dissect through abdo wall to stomach
Stay suture and decompress with needle then stab incision
Suture gastric and seroa to subcut
Suture mucosa to skin
How are stay sutures used to manipulate tissue?
Assistant hold them and manipulate
Hold one with your non dominant hand
Clip to drapes/ wind them around a retractor if don't have assistant
How does a gastropexy work?
Fixes pylorus to right abdo wall
Reposition stomach by gentle traction on pylorus first
Explain two techniques of gastropexy
Incisional gastropexy
Longitudinal incision in pyloric antrum
Transverse incision just caudal to last rib
Stay suture at each end of first incision, tie suture and then appose the margins of wound (see notes)
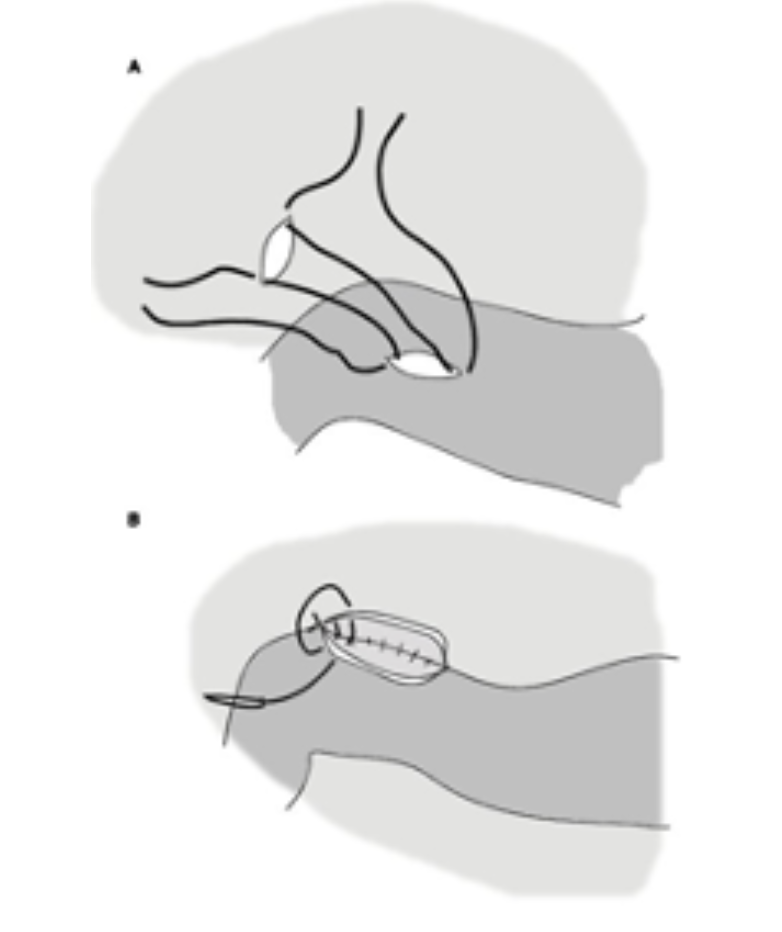
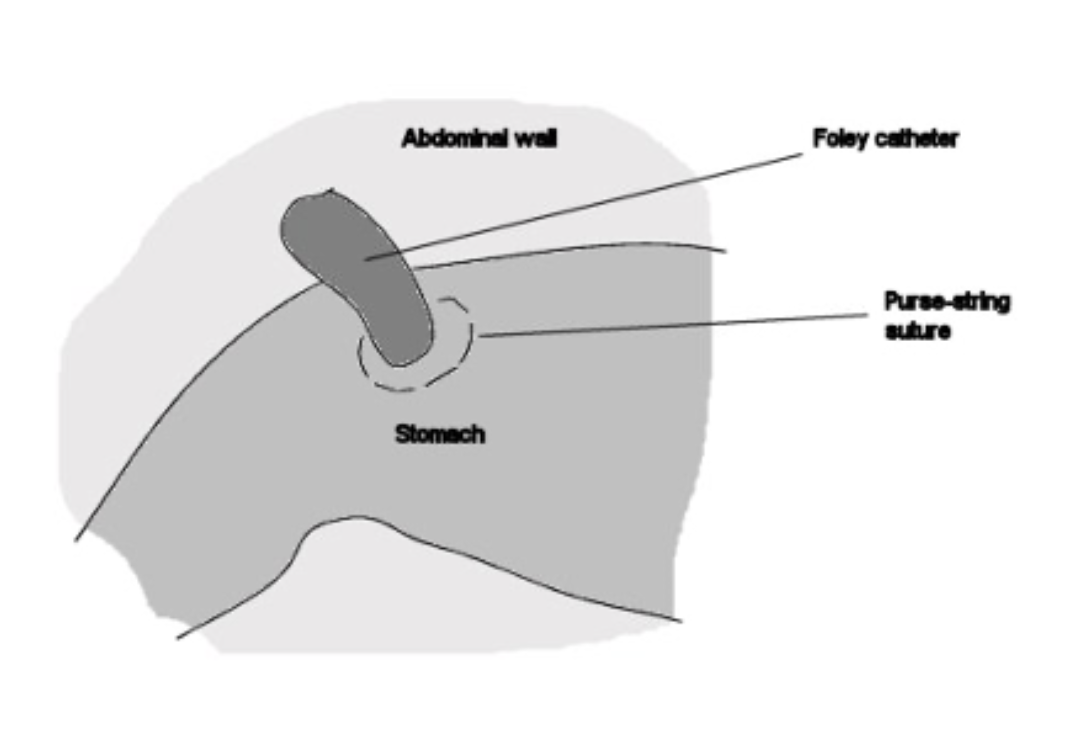
Tube gastropexy
Foley catheter through stab incision
Purse string suture in pyloric antrum (see notes)
Should splenectomy be performed with a GDV surgery?
If not thrombi and no splenic torsion not indicated
Congestion generally resolves when stomach repositioned
Don't remove unless have to bc inc surgical time
When do you have to perform a partial gastrectomy in a GDV surgery?
Presence of gastric necrosis
Assess stomach wall viability
Colour
Bleeding
Pulses
Thinning= necrosis
What are the post op considerations to make for GDV?
Fluids
Monitor ECG (VPCs common)
Monitor electrolyes
Nil by mouth 24-48hrs then water and small amounts of food
Gastric mucosal protectants
Sucralfate, Antacids
Metoclopramide if vomiting (delay feeding)
Small freq meals and avoid exercise after meals
What are the possible causes of gastric outflow obstruction
Neoplasia
Pyloric stenosis
Hypertrophic gastritis
Pyloric muscular hypertrophy/dysfunction
How are gastric outflow obstructions treated?
Surgically
Several pyloroplasty procedures (widens diameter of pylorus)
What are Billroth I (gastroduodenostomy) and Billroth II (gastrojejunostomy) procedures?
Allow resection of large amount of distal stomach and pylorus (e.g.- in neoplasia)
Choice based on amount of tissue to be resected and resulting tension
What are they doing here?
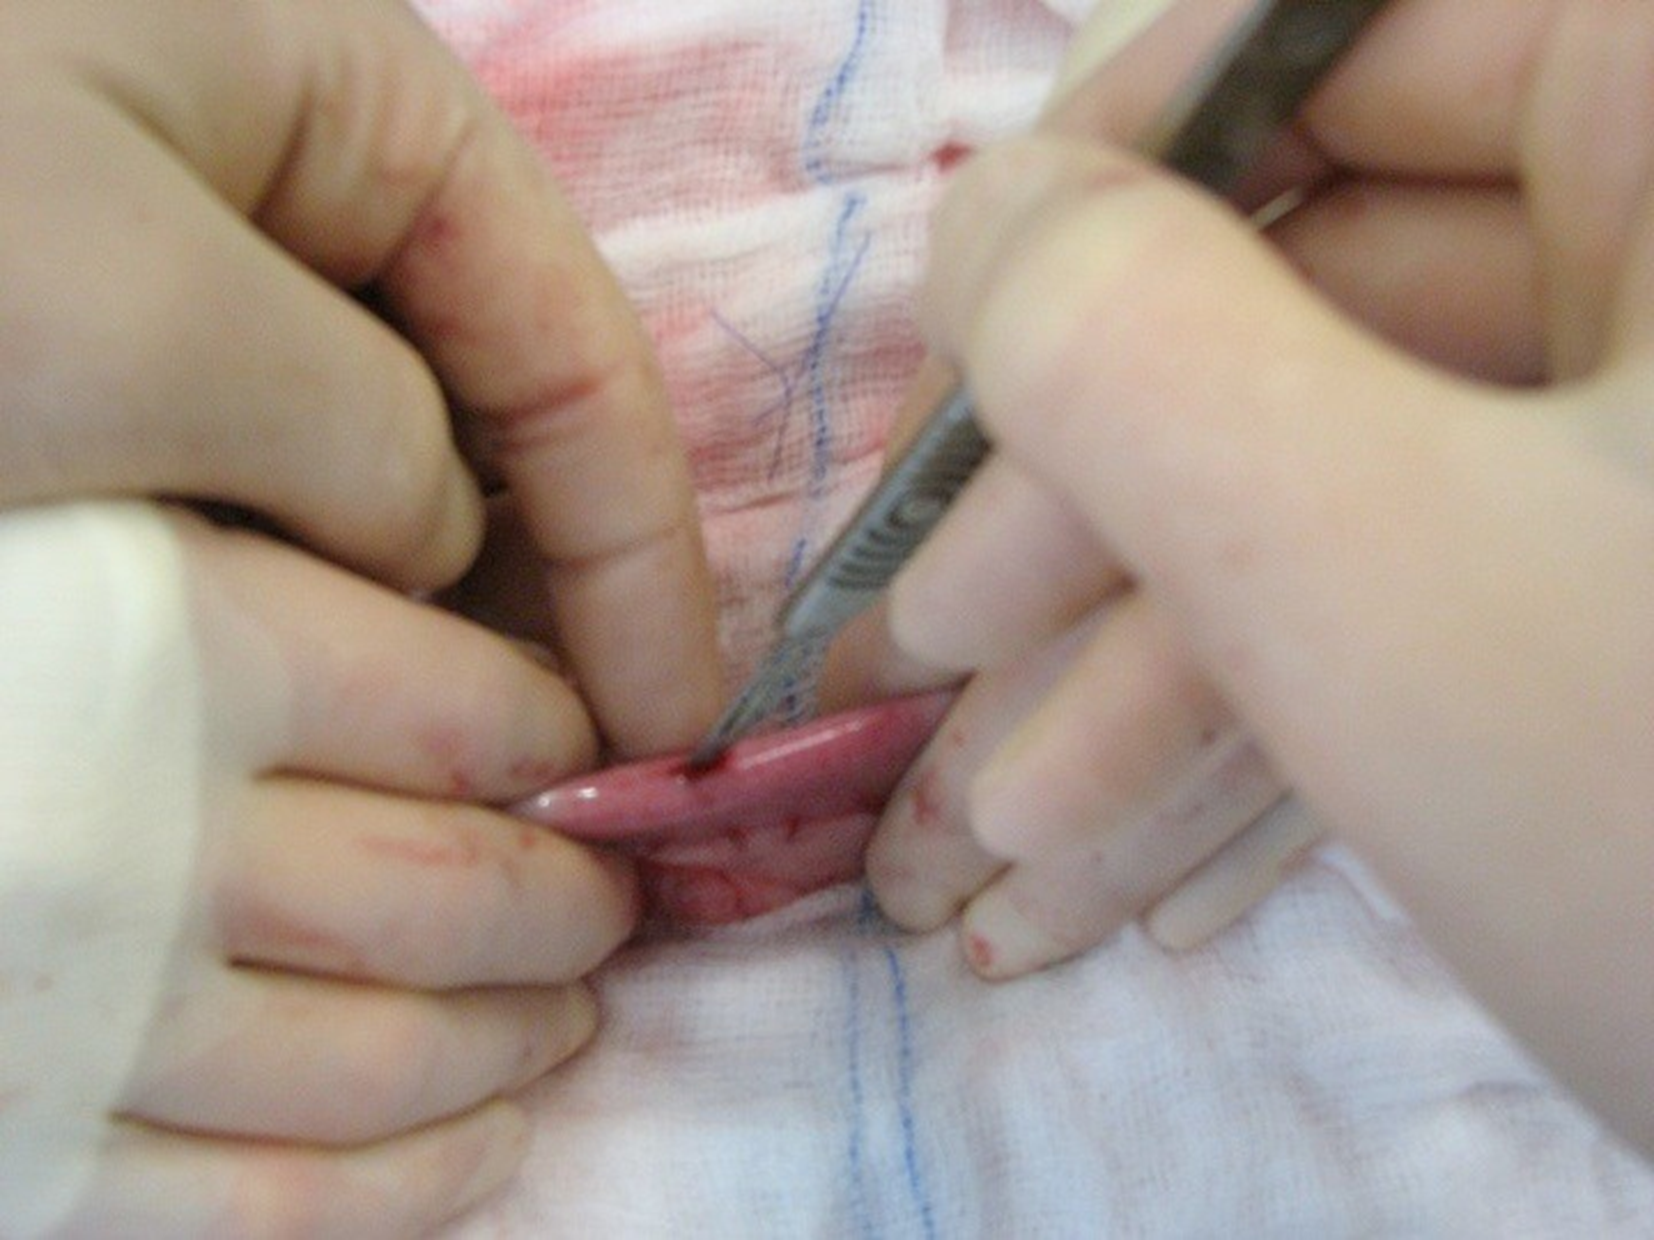
Occluding the lumen before incision to prevent leakage of the GI contents
Longitudinal incision - least vascular and least likely to cause stricture
How do you deal with joining these intestines?
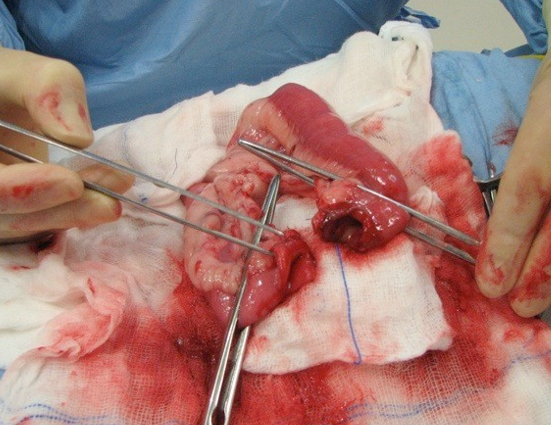
Left smaller diameter - cut on the antemesenteric border to increase the diameter
Right everting slightly - can trim this
When you’re clamping off the intestinal lumen to do an enterectomy, which set of clamps (crushing or non-crushing) should you put on first?
Crushing clamps first then non curshing
Sets boundaries for resection
Ensure where you are cutting is in viable tissue
Minimises time that intestine you're not resecting is clamped for
What are the features of linear foreign bodies
More common in cats
Problem when fixed proximally
Concertina of intestines
How do you treat a linear foreign body?
Conservative- cut it
If FB under tongue, no evidence of peritonitis then FB will often past ok in 3d
Surgery if FB not fixed at tongue or signs of peritonitis
Mutliple incisions starting at distal end
What is intussception usually secondary to?
Something causing hypermotility (e.g.- diarrhoea, high parasite burden)
Can happen at ileocolic junction may progress and protrude through anus
How can you treat intussusception?
Sometimes can be done manually
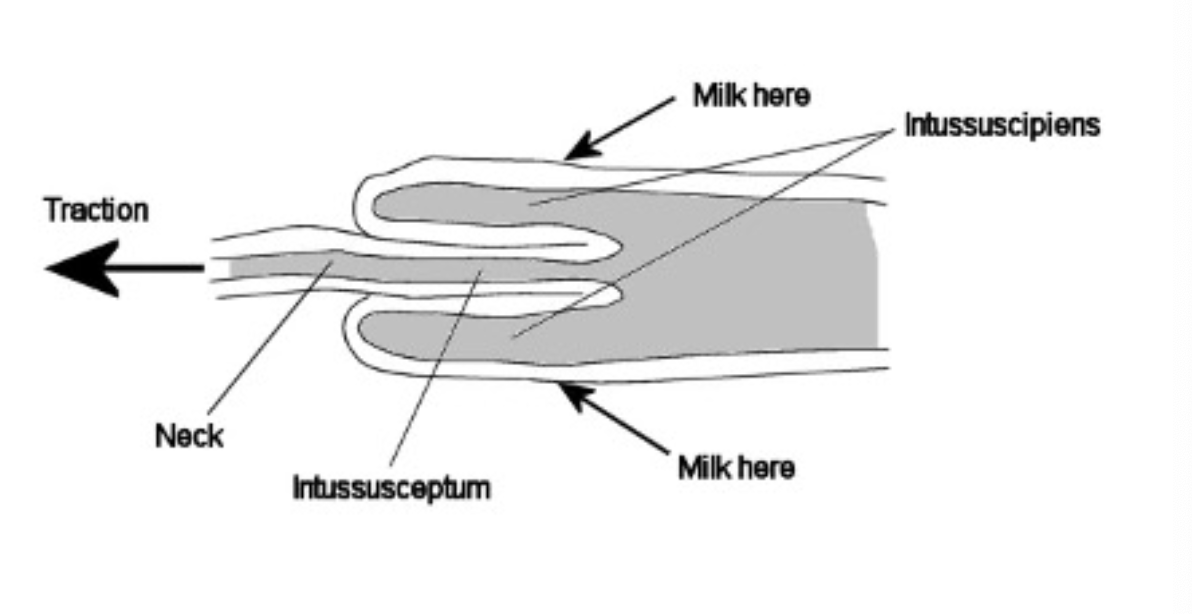
If not have to perform enterectomy