Chemistry 1 Solo 2 Lecture 2 Hyperglycemia and Hypoglycemia
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/41

Earn XP
Description and Tags
42 Terms
High blood glucose
The most frequently encountered disorder of carbohydrate metabolism is high blood glucose concentration due to diabetes mellitus (DM)
DM is a group of metabolic disorders of carbohydrate metabolism in which glucose is underused, producing hyperglycemia
Low blood glucose
Hypoglycemia is an abnormally diminished concentration of glucose in the blood
Diabetes mellitus causes microvascular complications
Diabetic retinopathy (causing blindness)
Diabetic nephropathy (causing renal failure)
Neuropathy (nerve damage)
Diabetes mellitus causes macrovascular complications
Atherosclerosis: hardening of the arteries
cardiac (myocardial infarction)
cerebral (stroke)
peripheral large vessels (limb amputation)
Diabetes mellitus symptoms
Urinating often
Feeling very thirsty
Feeling very hungry even when eating
Extreme fatigue
Blurry vision
Cuts/bruises slow to heal
Weight loss even when eating more (type 1)
Tingling, pain, or numbness in the hands/feet (type 2)
Diabetes mellitus - ketone bodies
When the body doesn’t have enough carbohydrates for cells to burn for energy, it burns fat instead
As part of this process, it makes three acidic, intermediate products known as ketones
Acetone
Beta-hydroxybutyrate
Acetoacetic acid
The primary substrates for the formation of ketone bodies are free fatty acids from fat tissue
Normally, long chain fatty acids are
Taken up by the liver
Re-esterified to triglycerides
Stored in the liver or incorporated in very low density lipoproteins (VLDL), and then
Returned to plasma
In uncontrolled diabetes, low insulin concentrations result in increased lipolysis and decreased re-esterification of these fatty acids to triglycerides
Increased counter-regulatory hormones also increase lipolysis and ketogenesis in adipose tissue and liver; free fatty acids are the precursors for ketone bodies
Excessive formation of ketone bodies results in
Increased blood concentrations of ketones
Increased excretion of ketones in the urine
Diabetes mellitus and alcohol consumption are the common causes of ketoacidosis
May form due to low availability of carbohydrates
Starvation
Frequent vomiting
May form due to low use of carbohydrates
Diabetes mellitus
Glycogen storage disease
Alkalosis
Diabetic ketoacidosis
Complication of type 1 diabetes mellitus
Without enough insulin, the body can’t use sugar properly for energy
This prompts the release of hormones that break down fat as fuel, which produces acidic ketones
Excess ketones build up in the blood and eventually “spill over” into the urine to be measured
Hyperosmolar nonketotic coma
Characterized by severe hyperglycemia, extreme dehydration, hyperosmolar plasma, and altered consciousness; complications include coma, seizures, and death
Metabolic complication of diabetes mellitus, most often type 2 in the setting of physiologic stress (acute illness, infection, myocardial infarction, or stroke)
Response to stress increases hormones that favor elevated glucose levels
Hyperglycemia → fluid shift from cells to blood → increased urine output (osmotic diuresis) → dehydration
Serum ketones are not present because the amount of insulin present in most patients with type 2 diabetes mellitus is adequate to suppress ketogenesis
Diagnosed by severe hyperglycemia and plasma hyperosmolality and absence of significant ketosis
Symptoms of Diabetes mellitus include all of the following except
Polychromasia
The development of ketosis in uncontrolled diabetes is a result of
Increased lipolysis of fatty acids from adipose stores and decreased re
Table 9.3 Classification of Diabetes Mellitus
The terms juvenile-onset and adult-onset diabetes were abolished in 1979 by the National Diabetes Data Group (NDDG)
The terms insulin-dependent diabetes mellitus (IDDM) and non-insulin dependent diabetes mellitus (NIDDM) were eliminated in 1997 by the American Diabetes Association (ADA)

Type 1 Diabetes Mellitus Overview
5-10% of DM cases
Peak incidence in childhood and adolescence
Acute onset: Symptoms occur abruptly
Polyuria: Increased urine output
Polydipsia: Increased thirst
Rapid weight loss
Patients have deficiency of insulin caused by loss/destruction of pancreatic islet beta cells
Patients are dependent on insulin to sustain life and prevent ketosis
Most patients have antibodies that identify an autoimmune process
Type 1 diabetes mellitus etiology
Type 1A
Caused by cell mediated autoimmune destruction of Beta cells of the pancreas
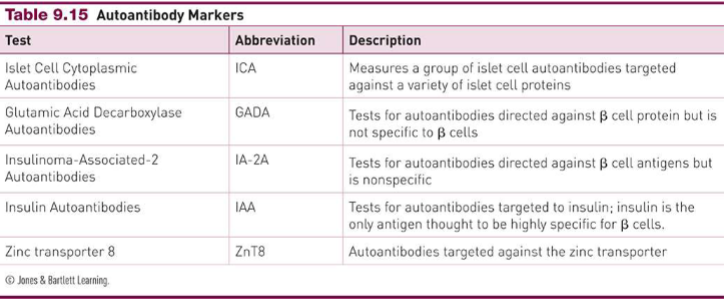
Autoantibodies may be detected in circulation, including islet cell cytoplasmic antibodies and insulin autoantibodies
Type 1B
Called idiopathic T1DM
Patients experience Beta cell destruction, but it is due to a chromosomal abnormality or an unknown cause rather than an autoimmune process
Genetic predisposition
Complex, undefined mode of inheritance
Associated with HLA-DR3 or HLA-DR4; screening by determining HLA type is not currently warranted except in research studies
Routine measurement of genetic markers is not of value at this time
Environmental factors contribute to onset of disease
Viruses such as rubella, mumps, or coxsackie virus B have been implicated
Autoimmunity to beta cells may be initiated by a viral protein that shares an amino acid sequence with a beta cell protein
Table 9.15 Autoantibody Markers
Type 2 Diabetes mellitus overview
90% of all cases of diabetes mellitus
Most acquire disease after age 40
Minimal symptoms, not prone to ketosis, not dependent on insulin to prevent ketonuria
Insulin concentrations may vary among patients, but most have impaired insulin action
Obesity is commonly associated; weight loss typically improves condition
To control hyperglycemia, these patients may require change in diet, hypoglycemia oral medications, or insulin
Glycemic Index
A relative ranking of carbohydrate in foods according to how they affect blood glucose levels
Carbohydrates with a low value (55 or less) are more slowly digested, absorbed, and metabolized
Type 2 diabetes mellitus - Two pathological Defects are present
Insulin resistance: Decreased ability of insulin to act on tissues
Loss of beta cell function: There is an inability of the pancreas to produce sufficient insulin to compensate for the insulin resistance
Type 2 diabetes mellitus etiology
Environment
Lack of diet and exercise; 60-80% of T2DM patients are obese; distribution of fat and duration of obesity play a role
Diabetogenes
Genes that contributes to the development of diabetes
>30 genetic loci have been identified that contribute to the T2DM
Genetics account for only 5% of patients with T2DM
Multiple genetic factors interact with environmental influences to produce the phenotype
Diabetes mellitus Treatment
Type 1
Control carbohydrate intake
Insulin with or without and immunosuppressive drug
Type 2
Control carbohydrate intake
May require insulin or oral hypoglycemic agent
Weight reduction
Hyperglycemia and Underlying Disorders
Formerly called secondary diabetes, hyperglycemia may be due to specific underlying disorders
Genetic defects of beta cell function
Genetic defects of insulin action
Disease of exocrine pancreas
Endocrinopathies such as Cushing disease (excess cortisol), acromegaly (excess growth hormone), glucagonoma (excess glucagon)
Hormones or drugs known to induce beta cell dysfunction or to impair insulin action
Infections
Uncommon immune mediated diabetes
Other genetic syndromes: Down syndrome, Klinefelter syndrome, porphyria
Gestational diabetes mellitus Overview
Occurs in 6-8% of all pregnancies in the US
Carbohydrate intolerance of variable severity with onset or first recognition during pregnancy
Carbohydrate intolerance often reverts to normal after delivery
Potential Risks for mother
Usually asymptomatic and not life-threatening to mother
High rate of C-sections
Hypertension
Women with GDM are more likely to develop DM later in life
Potential risks for baby
Associated with increased morbidity and mortality in neonate that can be reduced if recognized early
Macrosomia: maternal hyperglycemia causes the fetus to secrete more insulin, resulting in fetal growth and hypoglycemia
Gestational Diabetes Mellitus
Normal pregnancy is associated with increased insulin resistance, especially in the late second and third trimesters
Euglycemia is maintained by increased insulin secretion; Gestational diabetes mellitus develops in women who fail to increase insulin sufficiently
Risk factors
family history of diabetes in first degree realtive
Obesity
Advanced maternal age
Glycosuria
Selected adverse outcomes in a previous pregnancy (miscarriages, stillbirths, macrosomia)
Treatment for GDM
Treatment strategies include daily blood sugar monitoring, a healthy diet, exercise, and monitoring the baby
If blood sugar is too high, medication is needed. Anti-diabetic medications control the amount of sugar (glucose) in the blood. Common drugs include metformin
Impaired fasting glucose
Diagnosed in people with intermediate fasting glucose levels
Fasting glucose values are 100-125 mg/dL
Increased prevalence of cardiovascular disease
Metabolic syndrome
Also known as insulin resistance syndrome, Syndrome X, Reaven’s syndrome, obesity dyslipidemia syndrome
Metabolic syndrome is a cluster of conditions that occur together, increasing risk of heart disease, stroke and diabetes

Type 2 diabetes
Is associated with resistance to the action of insulin
Gestational diabetes mellitus refers to
Women that develop DM during pregnancy
Hypoglycemia
Low blood glucose concentration
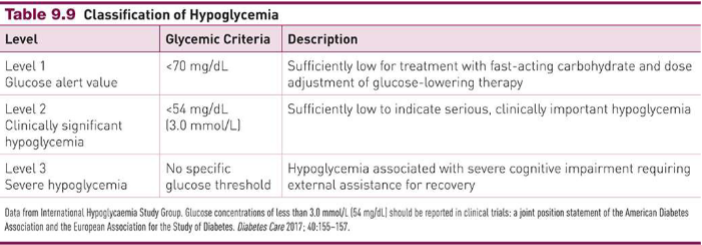
The most widely used cutoff is 70 mg/dL
May occur without symptoms or evidence of underlying disease
Symptoms of hypoglycemia are common, but actual hypoglycemic disorders are very rare
Epinephrine produces the classic signs and symptoms of hypoglycemia
Table 9.9 Classification of Hypoglycemia
Hypoglycemia brain effects
The brain needs glucose for energy production
One third of glucose use in resting adults occurs in the central nervous system (CNS)
Impairment of cerebral function begins when glucose <50 mg/dL
Very low blood glucose (<20-30mg/dL) may cause severe damage to the CNS, leading to symptoms referred to as neuroglycopenia
Hypoglycemia in neonates and infants
Neonates have lower glucose concentrations than adults
Glucose levels decline after birth due to depletion of liver glycogen stores
Causes of hypoglycemia in neonates
Prematurity
Maternal diabetes
Preeclampsia (maternal toxemia)
Inborn error of metabolism
Hypoglycemia in adults
More than 100 specific causes
Results form a low rate of glucose production in the liver OR an increased rate of glucose use

Postprandial hypoglycemia
Postprandial: 1 hour period immediately after a meal
Symptoms occur 1 to 3 hours after ingestion of food and last for 30 to 35 minutes
Whipple’s Triad
Hypoglycemia may be the cause of otherwise unexplained symptoms
A diagnosis of hypoglycemia should not be made unless a patient meets the criteria of Whipple’s triad
Symptoms are known or likely to be caused by hypoglycemia
Low glucose is measured when symptoms occur
Relief of symptoms occurs when glucose is increased to normal
Hypoglycemia with diabetes mellitus
Occurs frequently in both type 1 and type 2 diabetes
Causes include
Defective glucose counter-regulation, which involves the ability to increase glucose, counter to the effect of insulin
- Early type 1 diabetes: the secretion of glucagon in response to hypoglycemia is impaired
- Later in type 1 diabetes: The secretory response of epinephrine to hypoglycemia becomes deficient
Unawareness of hypoglycemia, due to lack of symptoms, in long-standing type 1 diabetes
Glycogen storage disease
Inherited disorders of defective glycogen storage
Glycogen is not being converted to glucose due to enzyme deficiency involved in glycogen metabolism
Liver and skeletal muscles are most affected
Hepatomegaly may be present due to increased liver glycogen stores
Hypoglycemia may be present due to inability to convert glycogen to glucose
The most widley used cutoff for hypoglycemia is a glucose value in mg/dL of less than
75
Which statement is incorrect concerning carbohydrates?
The brain functions normally with a low concentration of plasma glucose (<20 to 30 mg/dL)
Deficiency of a specific enzyme involved in glycogen metabolism will produce some type of
Glycogen storage disease
The typical cause of an inborn error of carbohydrate metabolism is
The absence of an enzyme involved in carbohydrate metabolism