Adult Health Exam 3
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/44

There's no tags or description
Looks like no tags are added yet.
45 Terms
12-lead ECG
Provides info about the contraction and relaxation of atria and ventricles
Only 10 electrodes!
Depolarization on ECG
Contraction
Repolarization on ECG
Relaxation
Placing electrodes
30-40 degrees to find intercostal
Clean skin
Remove excessive hair
Connect wires prior to sticking
Ambulatory electrocardiography
Outpatient
Holter, implantable loop recorder, mobile cardiac telemetry
P wave
Atrial depolarization
PR interval
From start of P to start of QRS
Represents conduction from SA node to AV node
0.12-0.20
Abnormal PR interval
May indicate heart block
QRS complex
Ventricular depolarization and atrial repolarization
<0.10
J point
Where the QRS ends and the ST segment begins
If it’s above the isoelectric line indicated ischemia
ST segment
Shows signs of ischemia
Represents early ventricular repolarization
T wave
Ventricular repolarization (relaxation)
Abnormal T wave
Ischemia or abnormal K+
Peaked T wave
High K+
Inverted T wave
Ischemia/hypokalemia → prevent ventricle from repolarizing properly
U wave
Repolarization of the Purkinje fibers
Hypokalemia, HTN, heart disease
QT interval
Total time for ventricle depolarization and repolarization
<0.48
Prolongued QT
Increases risk for torsade the pointes
PP interval
Used to determine atrial rate and rhythm
RR interval
Used to determine ventricular rate and rhythm
ST segment depression
Evidence of ischemia
ST segment elevation
Acute MI
Q waves
Necrosis and evidence of a previous infarction
Normal QRS duration
<0.10 sec
Artifact
Interference not related to heart
Poor electrode contact, client moves, malfunctions

Sinus arrythmias
SA node creates impulse at irregular rhythm
Often related to respiration and not clinically significant
Younger peeps
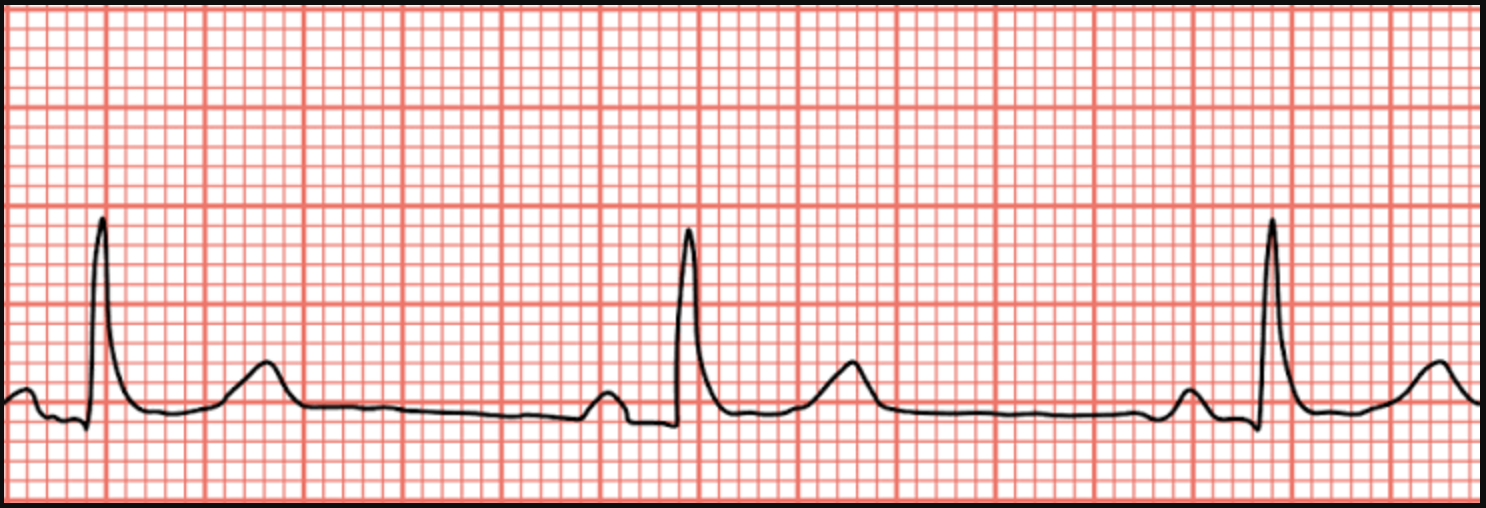
Sinus bradycardia
SA node <60bpm
Otherwise normal and regular rhythm
Causes for sinus bradycardia
Lower metabolic needs
Vagal stimulation
Medications (CCB, amiodarone, BB)
ICP
Rare: Inferior MI
Sinus bradycardia tx
Only if symptomatic!
Transcutaneous pacing
Atropine
Dopamine/epi → if ineffective pacing
Withhold meds that cause brady
IV fluids
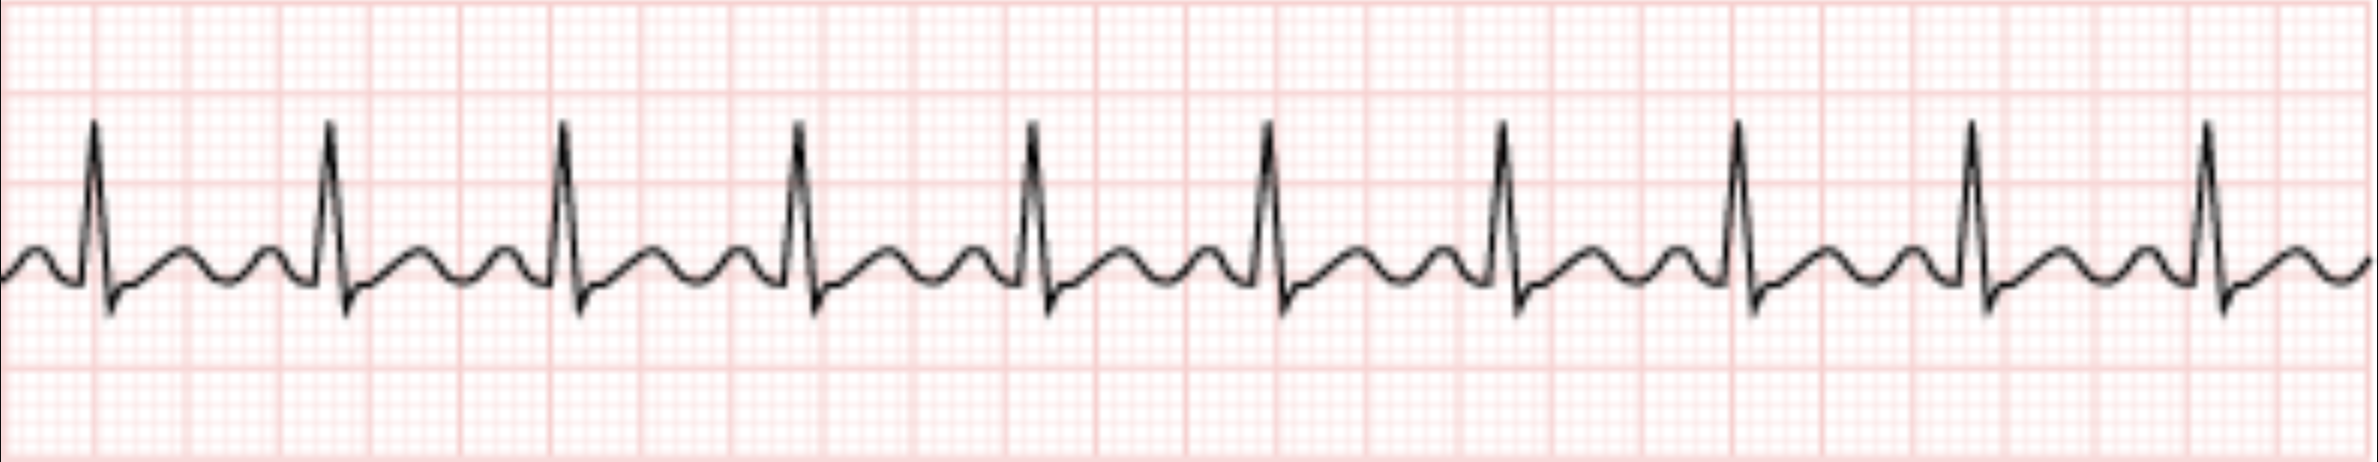
Sinus tachycardia
SA generates rate >100bpm
Otherwise normal
Sinus tachycardia causes
Physical/psychological stress → pain, PE, shock, fever, anxiety
Medications → stimulate sympathetic response
Stimulants/illicit drugs
Pathway of electrical activity in the heart
SA node
AV node
Bundle of His
Bundle branches
Purkinje fibers
Golden rule of contraction
Mechanical contraction ALWAYS comes after electrical conduction

Premature atrial contractions (PACS)
Benign early firing of heartbeat from irritated atrial nodes
No tx needed
Causes of PACS
Unknown
MI, HF, HTN
Medications
Common in 20s-30s
Randomly happen and go away

Supraventricular tachycardia (SVT)
Complex tachycardia caused by overexitability of atria
“Super excited to tell the ventricles”
Causes of SVT
Stress/substance use
PMH: Heart/lung disease
Wolff-Parkinson-White Syndrome
Pregnancy
s/s of SVT
HR >110
Hypotension
SOB
Palpitations/discomfort
Dizziness
SVT tx (in order)
Valsalva maneuvers → blowing into straw
Adenosine
IV Metoprolol/diltiazem
Syncronized cardioversion
Ablation

Characteristic of SVT ECG
No discernible P wave
Adenosine MOA
Decrease electrical conduction through AV node and decrease automaticity in SA node → reset the rhythm
Adenosine classification
Other antidysrhythmic
Adenosine adverse effects
Asystole!
Sinus bradycardia
Hypotension
Dyspnea
Facial flushing
Adenoside contraindications
AV block
Atrial flutter
Afib
Caution: Asthma and older adults
Adenosine nursing implications
Admin as quick as possible
Begin w 6mg → 20mL flush → 12mg → flush
Use port closest to heart
12-lead continuous monitoring
Crash cart in the room