Lecture 35: Lower Respiratory Tract Disorders
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/48

There's no tags or description
Looks like no tags are added yet.
49 Terms
cough
protective reflex to forcefully expel air and material from airways
characteristics of cough
productive vs non-productive
intensity → loud, harsh, paroxysmal, soft
temporal associations → time of day, activity
productive cough
moist sound heard during cough
delivers mucus, exudate, edema fluid, or blood from airways into oral cavity
most commonly caused by inflammation, infectious disease, or heart failure
non-productive cough
dry cough
mostly associated with airway disease such as collapsing trachea
exercise intolerance
begins with hypoxia from a variety of disease processes
mild tachypnea and subtly decreased activity → exercise intolerance and dyspnea at rest
often present in overt distress
evaluating respiratory distress
resting respiratory rate → upper limit 20-30 breaths per minute
mucus membrane color → pallor (acute hypoxemia), cyanosis (severe hypoxemia)
breathing pattern → rate, depth, inspiratory and expiratory efforts, audible sounds
inspiratory respiratory distress
extrathoracic disease
pulmonary disease
expiratory respiratory distress
intrathoracic airways
initial evaluation for respiratory distress includes
PE → complete systematic physical, thoracic auscultation
radiographs
bloodwork → CBC
bronchial lung sounds
most prominent in central area of lungs; tubular sounds over large airways
vesicular lung sounds
most prominent in peripheral lung fields → breeze blowing through leaves
auscultation of abnormal lung sounds
decreased lung sounds (pleural effusion, pneumothorax, mass lesions)
increased or harsh lung sounds, crackles, wheezes
what is the most helpful diagnostic tool for intrathoracic disease?
radiographs
radiographs for intrathoracic disease
minimum 2 views → right lateral and ventrodorsal
right and left laterals increase sensitivity
dorsoventral views are taken to highlight dorsal pulmonary arteries
horizontal views to evaluate pleural effusion or cavitary lesions
what phase of respiration is the best for taking thoracic radiographs?
peak inspiration

what is this showing?
inspiratory view
what are the 4 main pulmonary patterns for radiographs?
vascular pattern
bronchial pattern
alveolar pattern
interstitial pattern

what is blue?
pulmonary artery

what is red?
pulmonary vein

what view is this?
DV
vascular pattern
characterized by an increase or decrease in size of the pulmonary arteries and/or veins

what pattern is this?
vascular

what pattern is this?
bronchial
bronchial pattern
characterized by prominent bronchial walls resulting in thickened end-on and longitudinal bronchi → donuts and tram lines
alveolar pattern
characterized by air bronchogram, lobar signs, and silhouette effect
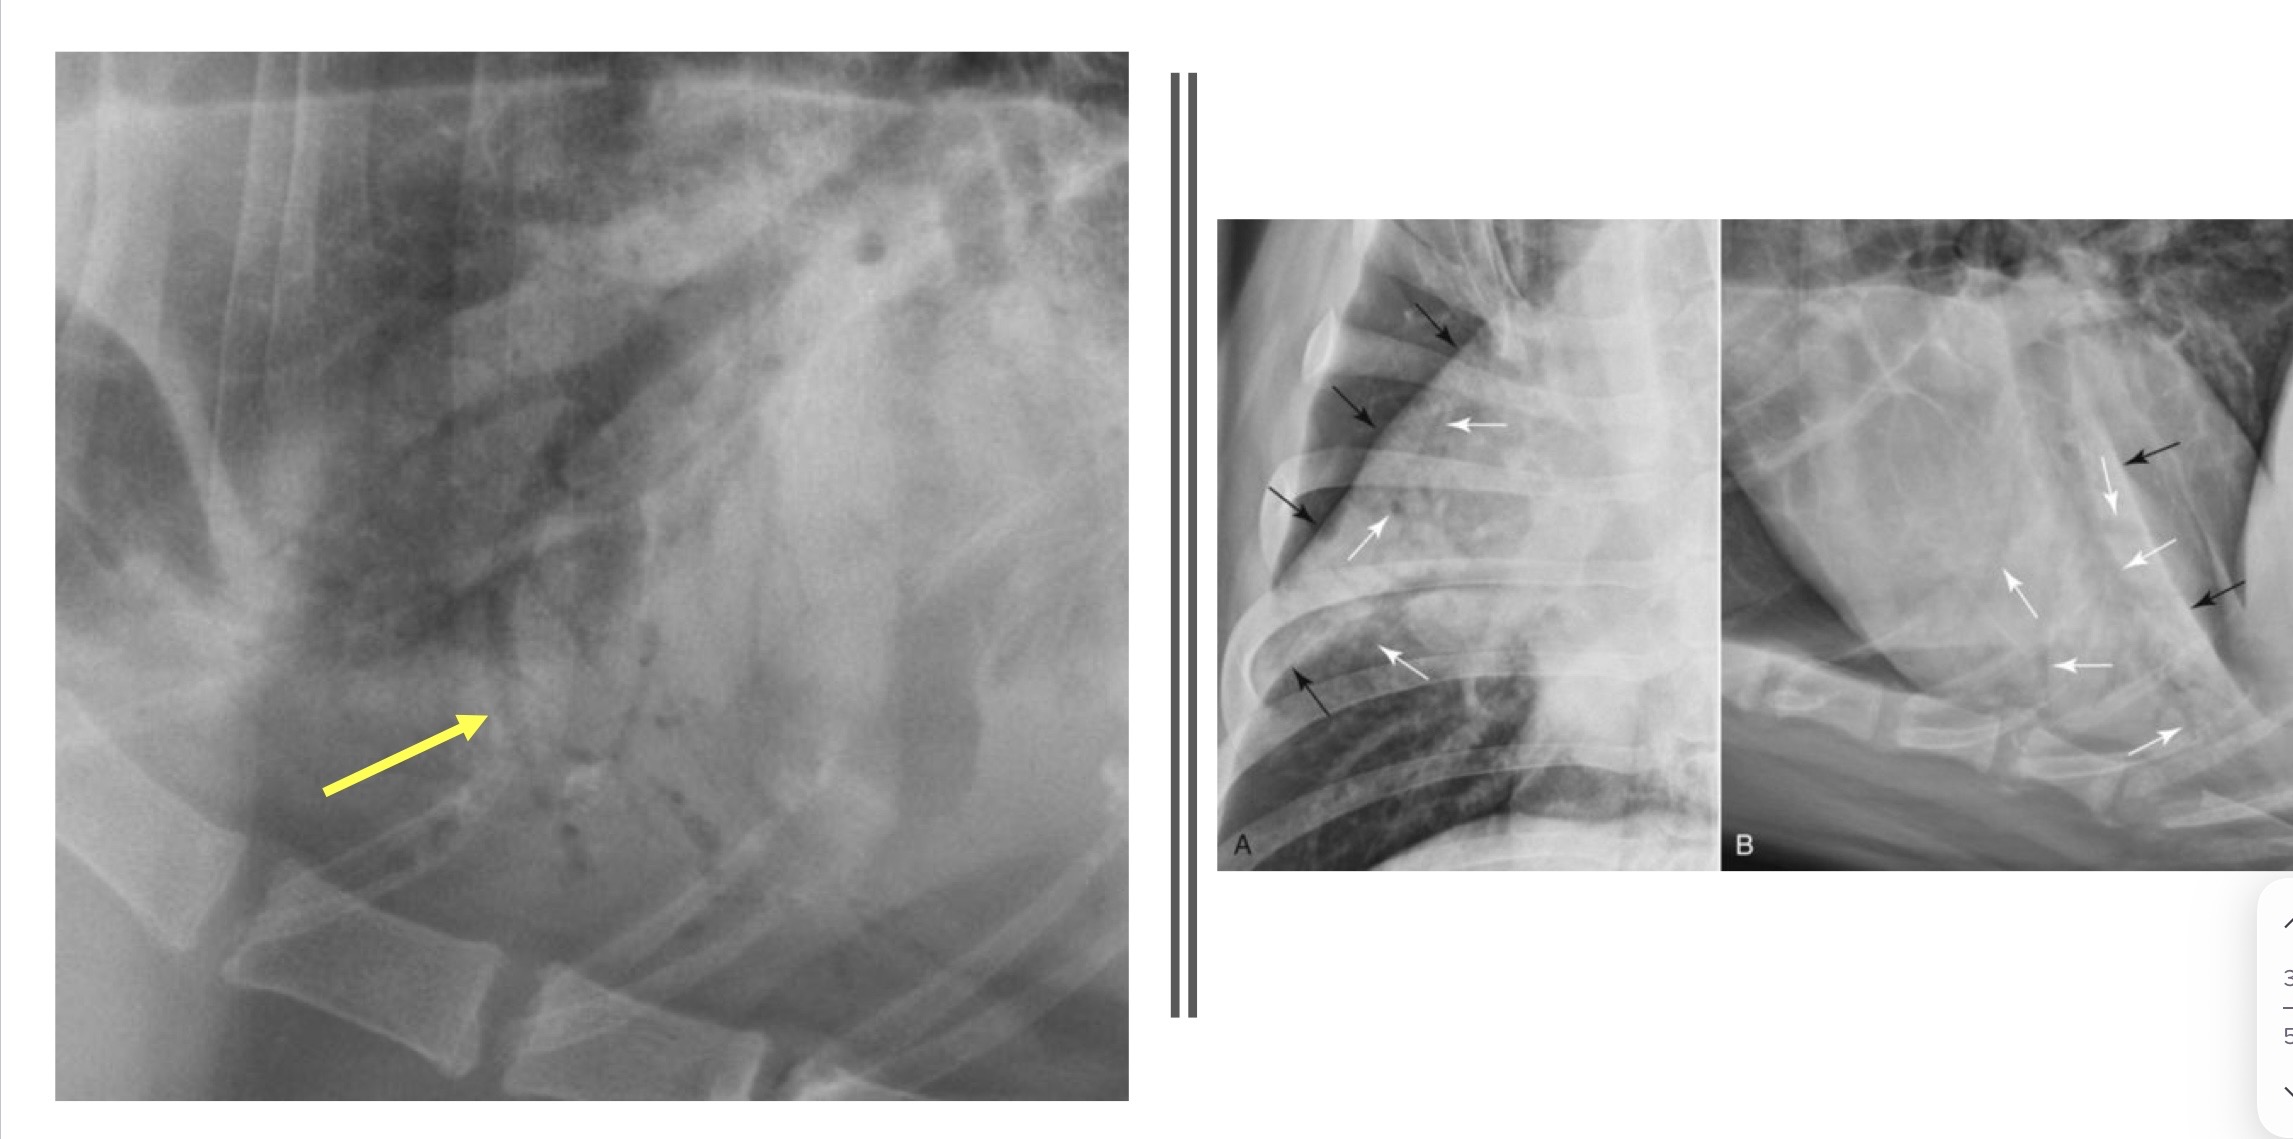
what pattern is this?
alveolar pattern
interstitial pattern
structured (nodular), unstructured (diffuse) or a combination resulting in an increase in lung opacity

what pattern is this?
interstitial
pleural effusion
characterized by retraction/rounding of lung lobes due to pleural fluid accumulation, dorsal displacement of the trachea

what is this showing?
pleural effusion

what are these showing?
pneumothorax
lung lobe consolidation
entire lobe is soft tissue opacity
atelectasis
collapsed lung lobe due to airway obstruction; lobe is also soft tissue opacity but smaller sized
cavitary lesions
abnormal air accumulation in lung
angiography
used to confirm pulmonary thromboembolism
ultrasonography
used to evaluate pulmonary mass lesions, guide collection of FNA samples, assess pleura, lungs
CT/MRI
advanced imaging to evaluate masses, metastatic disease, PTE, pneumonias, etc
nuclear imaging
used to diagnose ciliary dyskinesia, pulmonary perfusion, and ventilation
parasitology
direct observation via scoping
blood tests
cytological analysis of fluid or respiratory samples
fecal floatation
serology
fungal pulmonary disease → histoplasmosis, blastomycoses, coccidioidomycoses
toxoplasmosis
cryptococcus
heartworm disease
tracheal wash
transtracheal wash technique
transoral (endotracheal) technique
bronchoalveolar lavage
bronchoscopic
nonbronchoscopic
what should cats be pre-treated with for a transoral wash?
terbutaline and lidocaine on arytenoids
transthoracic lung aspiration
ultrasound guided FNA of pulmonary parenchyma
potential complications include pneumothorax, hemothorax, and pulmonary hemorrhage
can be utilized for masses near body wall and diffuse interstitial lung disease
bronchoscopy
evaluation of major airways
broncho-alveolar lavage performed routinely
technique of choice for airway foreign body removal

what is this?
blastomycosis

what are these?
macrophages
thoracotomy/thoracostomy
allows surgical exploration, tissue biopsy and definitive treatment of pulmonary lesions
which clinical sign is most commonly seen in patients with lower respiratory tract disease?
cough