Oral immunology
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/63

There's no tags or description
Looks like no tags are added yet.
64 Terms
primary oral disease are caused by:
infectious oral microorganisms
oral microorganisms (3)
Bacterial, viral, and fungal etiology
autoimmune diseases with oral manifestations
Sjorgren’s syndrome and pemphigus
recurrent oral mucosal ulcers
Bacterial etiology
Dental caries
periodontitis
Viral etiology
herpes simplex type I
HPV
Epstein bar virus
Fungal etiology
Oral candidiasis
caused by acquired immunodeficiency, poor OH, prolonged antibiotic use
immune mechanisms of oral cavity derive from: (2)
secretory system (secretions of major/minor salivary glands)
systemic immune system (gingival reticular fluid)
oral cavity immune barriers: (4)
saliva and mucins
oral mucosal lining
periodontium (including gingival crevice)
lymphoid tissue (tonsils) (major site of oral cavity manifesting bacterial infections)
Fluid barrier defense
Saliva
mechanical barrier defense
epithelium and connective tissue
chemotactic defense
neutrophils, lymphocytes, cytokines

innate vs adaptive immune responses
Oral adaptive immunity:
lymphocytes, T and B cells
in underlying connective tissue
B cell products can transudate to gingival crevice
Oral innate immunity:
secreted by salivary glands, epithelial cells and leukocytes
they kill, and inhibit growth of microorganisms
have broad spread antibacterial, antifungal, and antiviral properties
periodontal disease involves:
dysbiosis of microbiome
activate complement system and vasodilation
chemotactic recruitment of inflammatory exudate (mostly neutrophils)
adaptive immunity brings in T and B cells (for antibodies and cytokines)
Acquired Ig factors
secretory IgA, IgG, IgM
Non-Ig, innate factors
lysozyme, lactoferrin, peroxidase, agglutinins, phagocytic cells
Saliva
key role in innate host defense
lysozyme=cleaves bacterial cell walls
antimicrobial peptides(histatins) inhibit growth of caries causing bacteria
Salivary IgA (S-IgA)
aggregates oral bacteria like S. mutans to prevent plaque formation
Ab of IgA control microbial adherence to musical surfaces
Most important humoral mediator of specific oral mucosal immunity
secretory IgA
S-IgA Antibodies
bind to specific microbial targets and control microbial adherence to mucosal surfaces or neutralize toxins
Secretory IgA
major Ab in saliva, inhibits adherence and agglutinates bacteria
lactoferrin
bacteriostatic-iron binding
lysozyme
destroys the outer membrane of bacteria (against S. mutans)
Agglutinins
glycoproteins, histatins, PLPs
Oral mucosal immune system components (3)
Phagocytes, antigen-presenting cells, lymphocytes
pharyngeal Waldeyer’s ring
a central mucosal inductive site there Ag are processed by APCs
Antigens stimulate:
Naive musocal B and T cells
Tonsils
site of systemic (pharyngeal) bacterial infection, because of clefts that can collect debris (tonsilitis)
Waldeyer’s ring components (4)
galantine tonsils (sides of back of mouth, we can see)
lingual tonsils (at base of tongue)
tubal tonsils (near opening of auditory tubes)
pharyngeal tonsils (adenoids, in upper throat behind nose)
How tonsils support immunity
tonsils and adenoids are inductive sites where immune response begins
they activate B cells that develop into plasma cells to make Ab
leads to IgA production (in saliva to protect mucosal surfaces)
connective tissue of periodontium
are highly vascular=facilitate vascular leukocyte emigration in response to infection
Gingival crevicular fluid (GCF)
bathes the gingival sulcus
carries complement components and Ab, neutrophils, and plasma cells (to prevent tissue invasion)
Periodontium
supports and surrounds the teeth, is susceptible to acute and chronic inflammation from plaque bacteria in gingival sulcus
Subgingival biofilm
present in the gingival crevice
elicits host response to control bacteria
neutrophils are recruited, TLRs on gingival epithelium, then produce antimicrobial peptides
immunocompromised patient
acquired condition from: HIV/AIDS, cancer chemo therapies, or prolonged use of corticosteroids
HIC immunodeficiency
low levels of CD4+ T cells (higher susceptibility to candida albicans)
common oral manifestations
xerostomia, aphthous ulcers, recurrent fungal and viral infections
oral apthous ulcers
etiology is unclear
risk factors: stress, UV light, malnutrition, genetics
appear in buccal and lingual mucosa, very painful
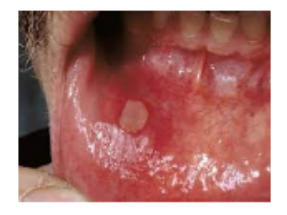
an oral apthous ulcer
autoimmune disease affecting the oral cavity
can be inflammatory disease with oral manifestations
etiology can be multifactorial
can have auto Ab with unknown causes
autoimmune disease examples
Sjogrens disease
rheumatoid arthritis
systemic lupus
pemphigus vulgaris
autoimmune disease oral manifestations
apthous ulcers
mucosal ulceration
desquamative gingivitis
xerostomia
increased caries risk
MOST COMMOM= MUCOSAL ULCERATIONS
mucosal ulceration cause
autoantibodies attack keratinocytes, cell junctions, and desmosomes
pharmacologic agents to treat autoimmune diseases
immunosuppressants
glucocorticoids
nonsteroidal anti-inflammatory medications (NSAIDs)

oral manifestations of diseases affecting oral region
TNF alpha inhibition
a target for autoimmune disease treatment
increases liability to infections
immunosuppressive drug uses:
reduce immune response against transplanted organs
treat autoimmune diseases (like pemphigus, lupus, or allergies)
Glucocorticoids
large doses over prolonged periods of time—>poor wound healing response and decreased resistance to infection
mainly given as topical for ulcers
NSAIDs
used for pain because of its analgesic, antipyretic, and anti-inflammatory effects
block prostaglandin by inhibits COX1 and COX2
adverse effects: increased bleeding risk and renal toxicity
Salicylates
like aspirin
irreversibly inhibits COX2
has antiplatelet effects to inhibit Thromboxane A2 production, and inhibit NF-kappa B (inflammation TF)
adverse effects: GI bleeding
most common oral cancer
oral squamous cell carcinoma (OSCC)
OSCC risk factors
smoking and chronic alcohol consumption
OSCC common locations
lateral borders of tongue and floor of mouth
important to do thorough oral cancer screening on all patients
Salivary biomarkers
elevated salivary and serum levels of Copper, zinc, and iron=oral malignancy likely
salivary albumin, salivary lactate dehydrogenase, and oxidative stress are other markers
Pro-inflammatory cytokines
like IL-6 and IL-8
significantly increased in serum and saliva of patients with leukoplakia and OSCC
Activation of classic complement pathway
CD4 containing split fragments
a propose biomarker for OSCC
apoptotic cells
another potential marker for oral cancer
significantly fewer apoptotic epithelial cells in oral cancer
Immunostimulators are prescribed:
to enhance the immune response against infectious diseases, tumors, and immunodeficiency disorders
Dental caries vaccines
conventionally available vaccines taken before disease development4immunization follows eruption of baby teeth
early immunization can have benefits for adult teeth as well
local passive immunization is better (because there are various antibodies against S. mutans Ag)
tooth decay is:
multifactorial
dental vaccine adverse effect:
human heart reactivity
vaccination trials conducted in 3 phases:
infants
preschool children
preadolescent children