Exam 1 - 508: Transgender Pharmacotherapy in Adults
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/48

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
49 Terms
Learning Objectives
Identify appropriate terminology used when providing care for transgender individuals
Recommend specific therapies used to help MTF and FTM transition
Recognize the expected and desired effects of hormonal therapy
Identify and manage adverse events of hormonal therapy
Differentiate sex assigned at birth, gender identity, and gender expression:
Sex Assigned at Birth → Based on assessment of external genitalia, as well as chromosomes and gonads
Gender Identity → A person’s internal sense of self and how they fit in the world, from the perspective of gender
Gender Expression → The outward manner in which an individual expresses or displays their gender. May include choices in clothing, hairstyle, speech and mannerisms
Define cisgender and nonbinary
Cisgender = individuals who identify with their sex assigned at birth
Nonbinary = Gender identity or expression not exclusively male or female
Define transfeminine and transmasculine
Transgender = gender identity and/or expression differs from cultural expectations based on the sex that was assigned at birth
Transfeminine (Transgender female/AMAB) = a person with female gender identity who was assigned male sex at birth
Transmasculine (Transgender male/AFAB) = a person with male gender identity who was assigned female sex at birth
AMAB = assigned male at birth; AFAB = assigned female at birth
What gender affirming hormone therapy (GAHT)?
Medications used to assist with the transition; Includes sex hormones and hormone blockers used to align physical characteristics with gender identity
Must be individualized
Patient’s goals
Presence of other medical conditions
Consideration of economic issues – insurance cost vs. cash cost
What are goals of transfeminine therapies? What agents are used?
GOALS
Promote the development of female secondary sex characteristics
Reduce endogenous effects of testosterone
Approaches to therapy
17 β-estradiol
Anti-androgens (spironolactone, finasteride, dutasteride)
GnRH agonists (leuprolide)
Progesterone
What labs do you have to monitor for feminizing hormone therapy?
Renal function & Potassium
At baseline and Q3 months until 1 year, then yearly afterwards + PRN
Estradiol
Every 3 months up until 1 year + PRN
Total testosterone
Every 3 months up until 1 year + PRN
CBC
As needed
What are the different types of estrogen given for transfeminine therapy?
17-beta-estradiol valerate (oral estradiol)
Estradiol cypionate (IM)
Estradiol valerate (IM)
Vivelle-dot (Transdermal estradiol patch)
Which estrogen is used in gender affirming hormone therapy?
17-beta estradiol valerate (oral)
>2 mg recommended BID dosing due to adverse effects
Can measure estrogen levels at any time
What are side effects seen with 17-beta estradiol valerate?
Mood changes (both good and bad), migraines, hot flashes, weight gain, nausea, thromboembolic events (low risk)
What are AEs and clinical pearls of estradiol cypionate (IM)?
Fluctuations in AEs
Less thromboembolic risk than oral
Measure levels at midpoint of treatment (IM injections given weekly)
Full effects last 11 days
Brand only
What are AEs and clinical pearls of estradiol valerate (IM)?
Fluctuations in AEs
Less thromboembolic risk than oral
Measure level at midpoint (IM injection given weekly)
Full effects last 11 days
Generic only
What are AEs and clinical pearls of transdermal estradiol (Vivelle-dot)?
Skin reactions observed
Least likely risk of thromboembolic events compared to IM and PO therapies
Slower onset
Can measure estrogen levels at anytime
What are counseling points of the transdermal estradiol patch?
Do not cut the patch
Adhesive does not work well sweaty, prolonged time in water
Change patch 2x/week
What other AEs are observed with estrogen therapy?
Decreased insulin sensitivity/DM
Increased risk of DVT/PE
Breast cancer risk is same as for cisgender women
Bone mineral density preserved while on estrogen and antiandrogens
Prostate cancer - not enough data
What are equivalencies of estrogen formulations?

What are our androgen lowering agents?
Spironolactone - most common
Finasteride/Dutasteride
Leuprolide
What is the MOA of Spironolactone?
Binds to androgen receptor and directly inhibits testosterone production (antiandrogen)
What AEs are seen with Spironolactone? Which is one desired in GAHT?
Hyperkalemia
Gynecomastia → Desired effect in GAHT
Hypotension
What is the MOA of Finasteride/Dutasteride?
5-alpha reductase inhibitors: Block conversion of testosterone to dihydrotestosterone (DHT)
It is an antiandrogen
What effects are seen with Finasteride/Dutasteride?
Decrease male pattern baldness
Used for benign prostatic hyperplasia
What is the MOA of leuprolide?
It is a GnRH agonist, binds to GnRH receptors in the anterior pituitary → Allows for sustained receptor stimulation, leading to paradoxical down regulation and desensitization of pituitary GnRH receptors
What AEs are seen with leuprolide?
Injection site pain
Headaches
Hot flashes
Increased prolactin
Why are androgen lowering therapies and estrogen therapies sometimes used together?
Blocking testosterone allows the use of a lower estradiol dose
What forms of progesterone are used?
Medroxyprogesterone (Provera)
Micronized progesterone (Prometrium & Endometrin)
Depo-Provera
How long is progesterone therapy used for? Why?
Only used for 3-6 months due to increased risk of CV events
Which progesterone agent is contraindicated in patients with peanut allergy?
Micronized progesterone (Prometrium & Endometrin) → It is dissolved in peanut oil
What AEs are seen with progesterone products?
Possible increased risk of VTE
Dizziness/somnolence
Weight gain
What permanent effect does estrogen and anti-androgen therapies have?
Increase in breast tissue/size, seen anywhere between 3-6 months and 2-5 years
List of Estrogen and Anti-androgen effects
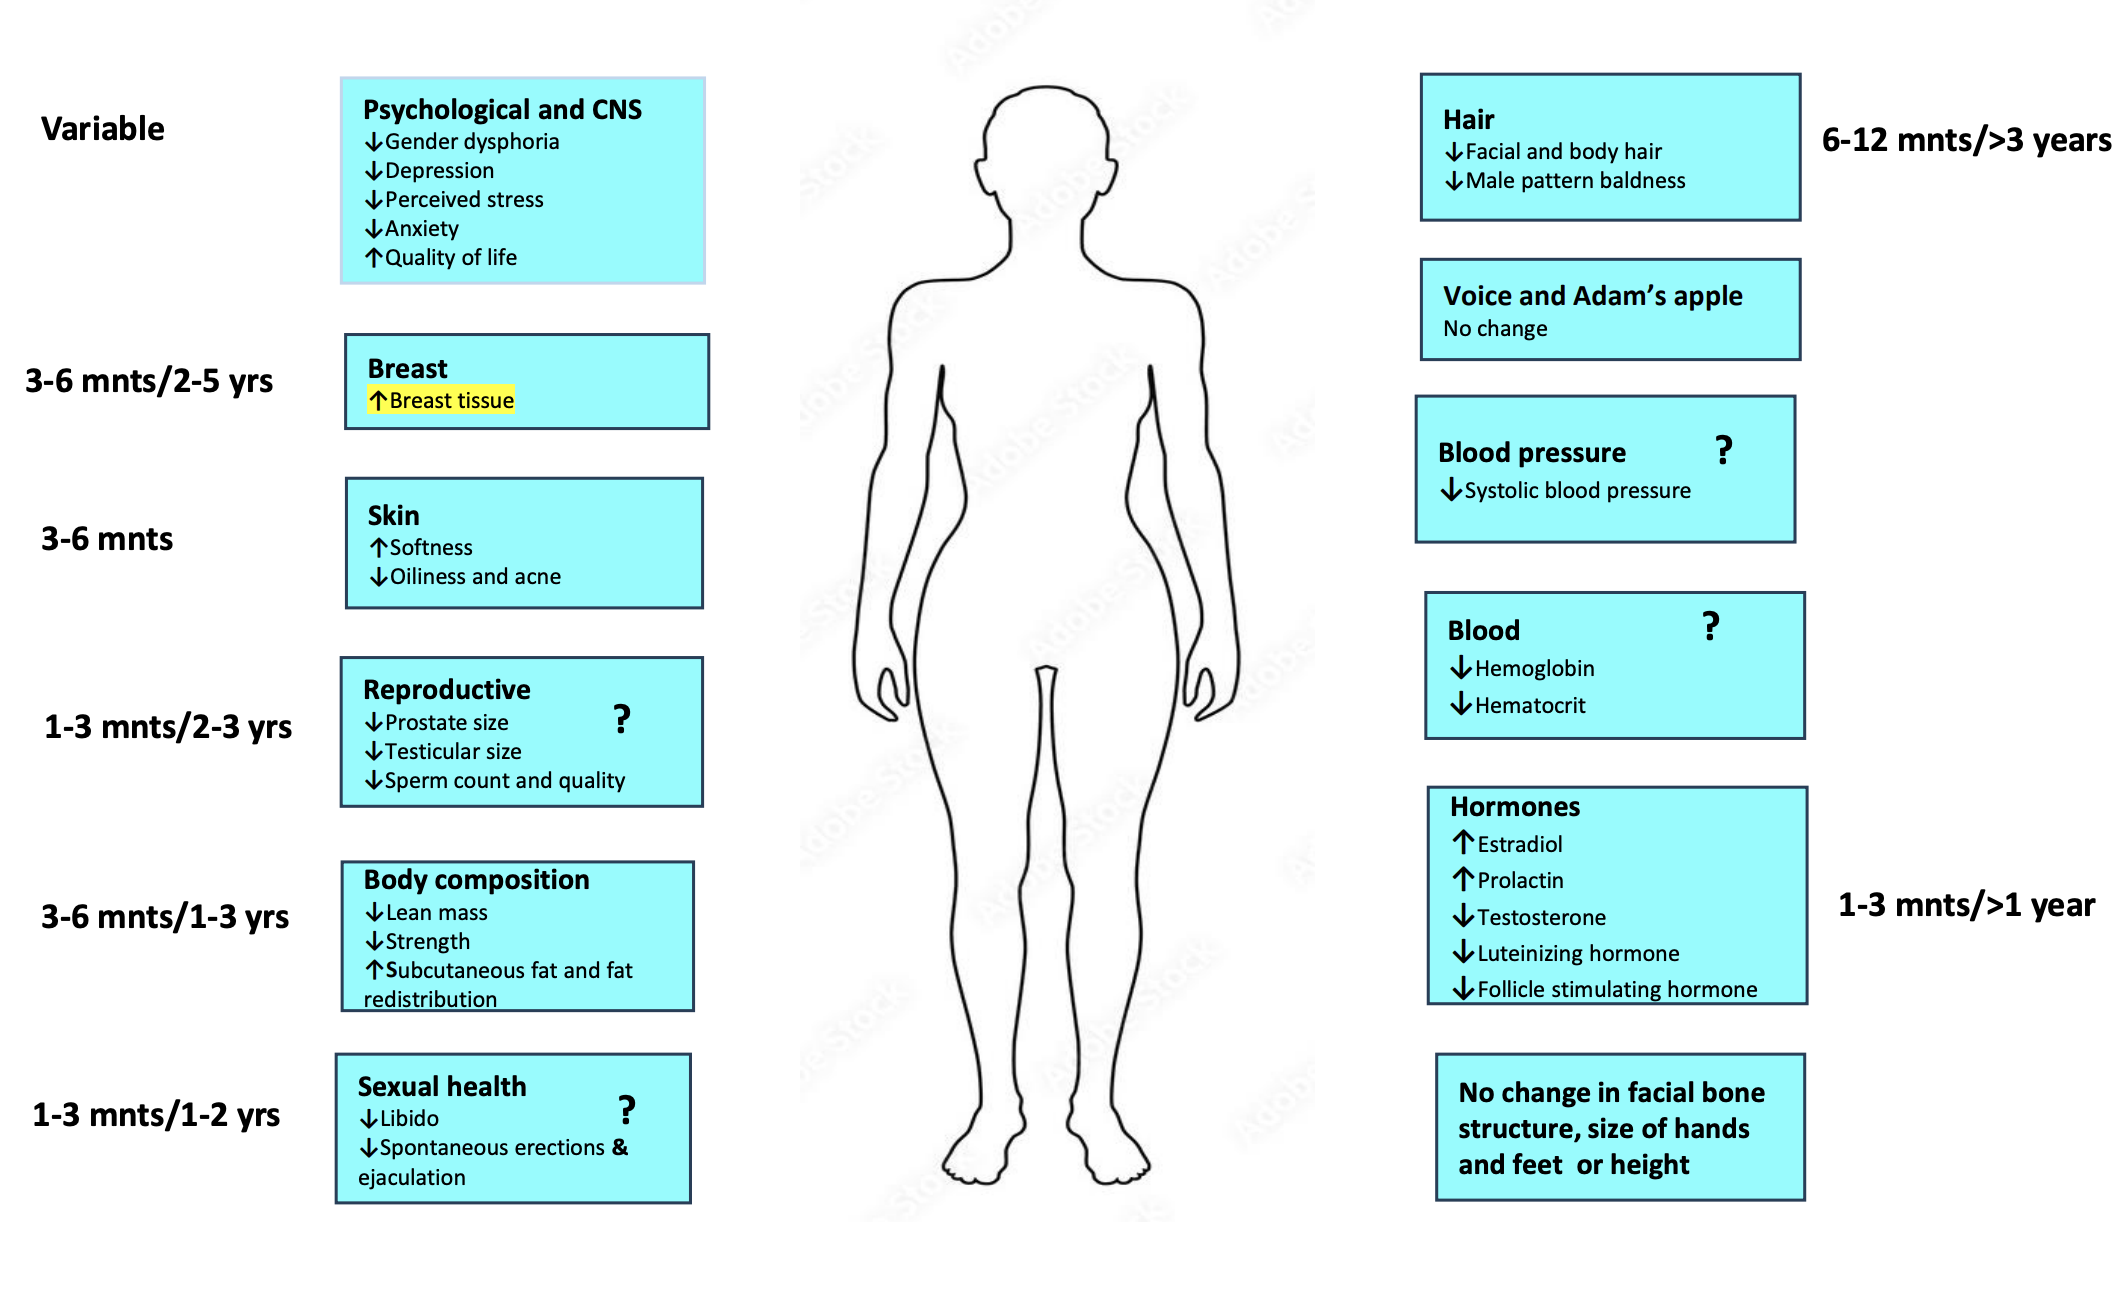
What are treatment recommendations for transwomen >40 years old?
Consider adding aspirin
Transdermal estradiol patch is preferred due to less VTE
Smoking cessations interventions
Adding statins
Can you use GAHT with antiretroviral therapy?
Yes, potential interactions should not prohibit use of ART
INSTIs
Least potential to affect GAHT
No adjustments necessary
Protease Inhibitors (PIs)
Limited data, impact unclear (may increase or decrease GAHT concentrations)
Monitor for AEs; titrate GAHT dose based on desired clinical effects and hormone concentration
What drug interactions does Estrogen have?
Partially metabolized through CYP3A4
Watch out for inducers and inhibitors
Truvada (TDF/FTC) used for HIV PrEP
TDF decreased slightly (12-27%) but still provided protection
No change in estrogen tho
What are the goals of transmasculine therapies? Which agents do we use?
Goals
Promote the development of male secondary sex characteristics
Decrease secondary female sex characteristics
Approaches to therapy
Testosterone
Vaginal Estrogen cream
Progesterone → to help stop menses
Hair loss prevention
Birth control
Which labs we do monitor in transmasculine therapy?
Total testosterone
q3 months, up until 1 year + PRN
Complete metabolic panel (LFTs/Glu/Alb)
q3 months, up until 1 year + PRN
CBC (Hb/Hct)
q3 months up until 1 year, then yearly afterwards
What agents do we use for masculinization?
Testosterone enanthate (sesame oil)
Testosterone cypionate (cottonseed, olive, or grapeseed oil)
Testosterone undecanoate (castor oil)
Topical gel (Androgel)
Which testosterone formulations are injectable?
Testosterone enanthate (sesame oil)
Testosterone cypionate (cottonseed, olive, or grapeseed oil)
What AEs do testosterone enanthate/cypionate have?
Acne
Polycythemia
Sleep apnea
Dyslipidemia
Injection site reactions
Pelvic pain
Genital atrophy
Hot flashes
Emotional changes
For which testosterone formulation do we have to monitor 30 mins after for?
Testosterone undecanoate (castor oil)
Rare cases of pulmonary oil micro embolism (POME) and anaphylaxis
Observe for 30 min after injection
What AE is seen with androgel?
Potential for secondary exposure
Hypersensitivity
Musky odor
How should androgel be applied?
Apply to upper arms, shoulders
Keep area dry for ≥2 hours after (no swimming, showering, sweating)
Can check T levels at anytime
Less variation in levels than IM/SQ
Testosterone Formulation Equivalency

What are ways we can supplement transmasculine therapy?
Estrogen cream to decrease vaginal atrophy - if desired
Start applying ~ 2 weeks prior to cervical cancer screening to ↓ pain
Topical Minoxidil or oral Finasteride for androgenic alopecia
Use of Progesterone
May help in the cessation of menses
Depo medroxyprogesterone 150 mg every 3 months or 5-10 mg PO HS
Discontinue after 3-6 months on testosterone if menses stop
Birth control interventions
Testosterone does not always eliminate ovulation
Also, Testosterone will be converted into estrogen
Which effects/consequences of testosterone are permanent?
Decreased fertility
Increased clitoral size
Increased facial and body hair
Increased androgenic alopecia
Voice deepening

What drug interactions does testosterone have?
It is a CYP3A4 substrate
CYP3A4 inducers and inhibitors will affect testosterone levels
P-gp substrate and inhibitor
Increases the anticoagulant effects of Warfarin → Monitor INR
Decreases blood glucose → May need to decrease the dose of diabetes medications
What is the goal testosterone level in transmasculine therapy?
300-1000 ng/dL
How often can we check testosterone levels during treatment?
Check hormone levels at any time when using topical testosterone
Check levels at the midpoint of the dosing interval when using injectable testosterone
What is the goal testosterone level in transfeminine therapy?
< 50ng/dL
What is the goal estradiol level in transfeminine therapy?
100-200 pg/mL