25 Dystocia, Fetotomy, and Postpartum Disorders
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/41

There's no tags or description
Looks like no tags are added yet.
42 Terms
b. uterine dorsoretroflexion
d. rupture of prepubic tendon
e. uterine torsion or inertia
f. twinning
Select the MARE causes of dystocia:
a. posture, presentation, position
b. uterine dorsoretroflexion
c. fetal monster
d. rupture of prepubic tendon
e. uterine torsion or inertia
f. twinning
a. posture, presentation, position
c. fetal monster
f. fetal oversize
Select the FOAL causes of dystocia:
a. posture, presentation, position
b. uterine dorsoretroflexion
c. fetal monster
d. rupture of prepubic tendon
e. uterine torsion or inertia
f. fetal oversize
Mare
What determines the size of the fetus, mare or sire?
a. anterior
Majority of baby horses are born in what presentation?
a. anterior
b. posterior
c. transverse
Drafts
What general breed is predisposed to transverse presentation?
Because vaginal/cervical mucous membrane disruption causes adhesions in mares VERY COMMON
Why should you limit arm movement in and out of a mare with dystocias?
1. tail wrap
2. clean perineal area/buttocks
3. wear sterile sleeves and disposable gloves when washing
What things do you need to do to prepare a mare for an exam for a dystocia?
Foals
Which are more time sensitive for dystocia intervention, calves or foals
INVERSE: only 13.6 minutes on average separates foals that survive and don't survive
What is the relationship like between length of dystocia in mares and fetal survival?
1. Assisted vaginal delivery
2. controlled vaginal delivery
3. fetotomy
4. c-section
Name the methods of correction/delivery for mare dystocias
It means that dystocia has the ability to negatively impact the mare's future fertility
What does it mean that overall post-dystocia foaling rates are 67% versus 84% for the normal population?
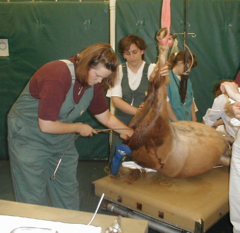
Controlled vaginal delivery (we make more room in the pelvis and push things around)
What is happening here?
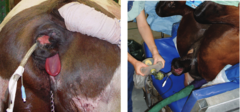
EX-utero, intra-partum treatment = intubate the foal and actively ventilate it while in the birth canal + check CO2 to allow for more time to correct dystocias
What is "E.X.I.T." and why do we care about it in mare dystocias?
E.X.I.T. = EX-utero, intra-partum treatment
What is this?
FALSE
TRUE OR FALSE: the longer it takes you to correct a dystocia, the better the outcome of the mare will be
Lots of lube and room to manipulate the fetus aka elevation (make mare stand up)
What is the key to quick dystocia corrections?
Lidocaine, xylazine, or a combo
What are your epidural dosing options in horse dystocias?
Lidocaine
Overall, which is shorter lasting and quicker acting? Lidocaine or xylazine?
b. onset 5 minutes
c. lasts 1.5 hours
Select the characteristics of a lidocaine epidural:
a. onset 20-30 mins
b. onset 5 minutes
c. lasts 1.5 hours
d. lasts 2.5 hours
e. lasts up to 5 hours
a. onset 20-30 mins
d. lasts 2.5 hours
Select the characteristics of a xylazine epidural:
a. onset 20-30 mins
b. onset 5 minutes
c. lasts 1.5 hours
d. lasts 2.5 hours
e. lasts up to 5 hours
e. lasts up to 5 hours
note: onset is quick, faster than the 20-30 mins of xylazine, but slightly longer than lidocaines 5 minutes = basically mixing them lengthens an epidural
Select the characteristics of a xylazine AND lidocaine epidural:
a. onset 20-30 mins
b. onset 5 minutes
c. lasts 1.5 hours
d. lasts 2.5 hours
e. lasts up to 5 hours
Traction synchronized with mare's contractions
When should you provide traction when helping a mare deliver a dystocia?
OXYTOCIN (do not give more than every 6-8 hours, use a lower dose at foaling)
Lavage, antibiotics
NSAIDs
Consider tetanus status
What medications should be given in the aftercare of a mare with dystocia?
2 people pulling max
How many people MAX should be pulling to help a mare with a dystocia?
Pull DOWN, NOT straight out
Which direction should you pull the baby out of the birth canal in mare dystocias to cause the least amount of trauma?
"Foal feathers" = eponychium
What is this?

If the foal still has feathers, this means it has not stood up, which means you know it has not had colostrum
Why do we care if we go to a farm and see a foal still has eponychium after several hours?
Oversew the edge of the uterine incision (whip stitch)
How can you limit hemorrhage when doing a c-section in horses?
C-section
Transverse presentations typically warrant what kind of intervention in mares?
Furacin ointment (Nitrofurazone) on mucosa with sterile sleeved hand (because adhesions are basically like treating proud flesh)
May add 40 mg dexamethazone
Post-dystocia vaginal irritation may lead to vaginal adhesions in mares. What can you use to treat this?
LESS
In mares, it is better to do more or less cuts when doing a fetotomy
FALSE: DO NOT DO A FETOTOMY if the birth canal is already traumatized from unsuccessful delivery
TRUE OR FALSE: you should elect to do a fetotomy if the birth canal is traumatized from unsuccessful delivery attempts by the owner because you don't want to have the mare push more and cause further trauma
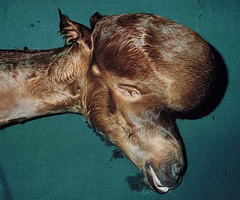
Hydrocephalus
What is this condition that may warrant a fetotomy?
Retention beyond 3 hours is abnormal
What is considered abnormal retention of fetal membranes in horses?
Incidence of retained fetal membranes is lower in horses
Is incidence of retained fetal membranes higher in cattle or horses?
Toxic metritis --> septicemia --> laminitis
What consequences make retained fetal membranes more severe that are actually the cause of death in horses?
Retained fetal membranes (tie this up so the mare doesn't step on it)
What is happening in this mare if the owner has been seeing this for 4 hours?

1. Burn's technique
2. infuse umbilical vessels
3. manual assistance (don't do this tho)
4. treatment with abx, NSAIDs, tetanus prophylactics, lavage
What are some treatment options for retained fetal membranes in horses?
Burn's technique
This technique for retained fetal membrane treatment in horses is when you distend the chorioallantoic cavity with 3-4 gallons of warm saline thru the cervical star
Infuse umbilical vessels
This technique for retained fetal membrane treatment in horses is when you cannulate vessels with a foal nasogastric tube and infuse with a garden hose for 5 minutes
This is the rectogenital pouch. Tears in the cranial vagina communicate with the abdomen and the guts can come out of the vulva.
Tears in the caudal vagina are not nearly as significant because they don't communicate with this pouch and can simply be rectified with nitrofurazone
What am I pointing to on this diagram and why should you care about it?

Cranial
Is this the consequence of a cranial or caudal vaginal tear?
