Neuro Week 7
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/151

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
152 Terms
What drives behaviour selection
Internal needs
What does optimal behaviour performance require
Coordinated physiological response
What is an example of internal needs driving behaviour
Low calories or nutrients →
"I'm hungry" →
get food = cognitive task to plan meal, gross and fine motor control of limbs, internal digestive processes
What is an example of physiological response to internal needs
Thermoeceptors sense dropping core body temp → warmth seeking behaviours (clothes, shelter) and physiological responses (shivering)
What was the adaptive need and evolutionary pressure for the nervous system
To develop mechanisms and systems to coordinate internal and external states
what does Brain–body communication is bidirectional mean
the brain regulates the same physiological state it senses
What is interoception
The nervous system's continuous sampling of the internal physiological environment
What does interoception interact with
Exteroception, cognition and action to maintain and ensure the integrity of an organism
What does interoception involve
Sensing and integrating internal physiological state from sensors → pathways → networks
is introception coscious
Often unconscious and regulatory, not just consciously perceived sensation
what does introception include
neural afferents, hormones, immune mediators and metabolites
what does introception support
autonomic, endocrine and behavioural responses
what are neural bodily signals
vagal and spinal afferents
what are endocrine bodily signals
steroid, peptide and metabolic hormones
what are immune bodily signals
cytokines, chemokines, immune-cell signalling
what are metabolic/chemical bodily signals
glucose, oxygen, CO₂, ammonia, osmolarity, electrolytes
What are the three levels of brain-body communication (hierarchial loops)
1. Central regulation and immunoception;
2. Reflexive control;
3. Local modulation


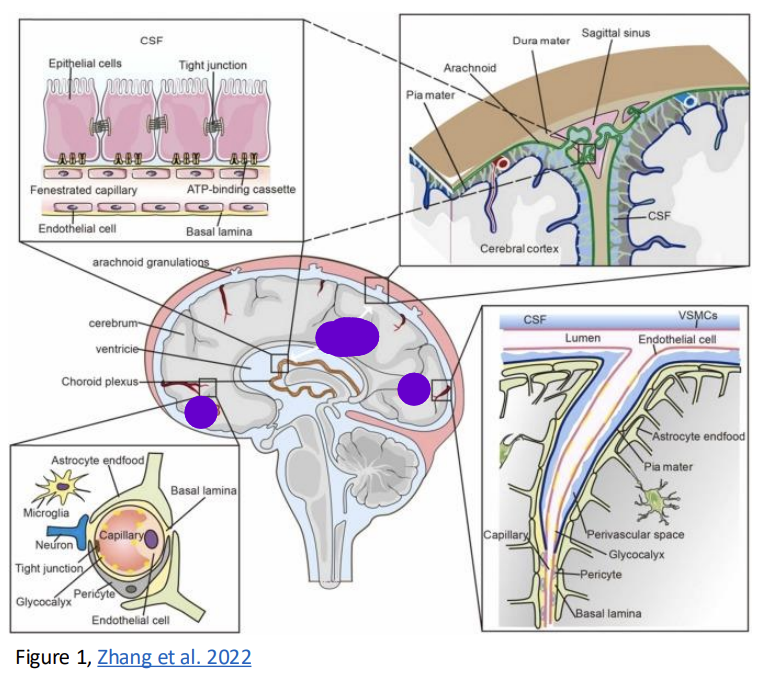
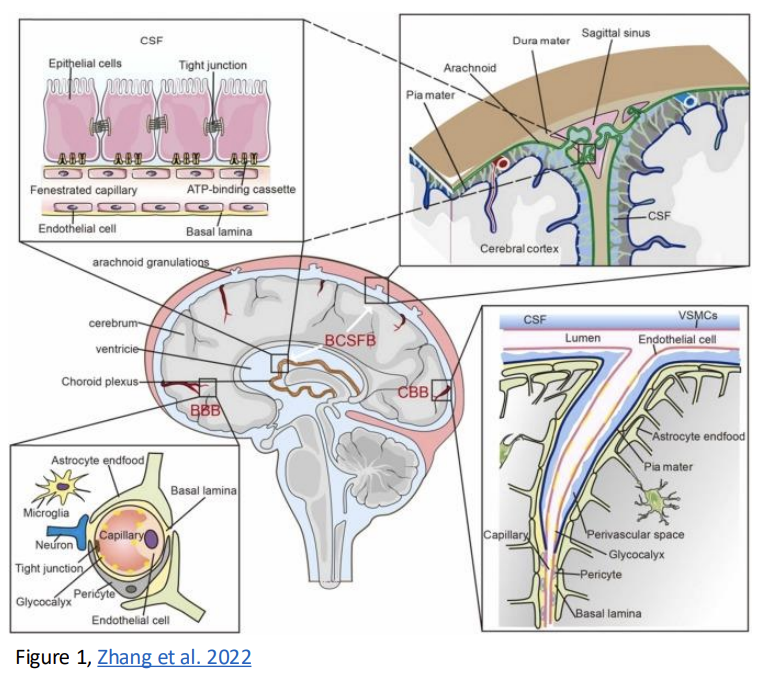
What are the three main barriers protecting the brain
Blood-brain barrier (BBB)
blood-cerebrospinal fluid barrier (BCSFB)
cerebrospinal fluid-brain barrier (CBB)
What is the blood-brain barrier (BBB) composed of
Basement membrane, pericyte, astrocyte endfeet
Where is the blood-cerebrospinal fluid barrier (BCSFB) located
In arachnoid granulations protruding into veins and choroid plexus
What is the cerebrospinal fluid-brain barrier (CBB) composed of
Pia mater and astrocytes
What are circumventricular organs
Specialized blood-brain interfaces that sense circulating hormones, metabolites and immune signals
Why are some brain regions deliberately more exposed
So the brain can access information about the internal state not captured by peripheral neural pathways
is The blood–brain barrier a wall that makes the brain biologically independent
no
What should the brain respond to
Changing physiological state, to maintain survival and homeostasis
When can the same response be adaptive vs dysfunctional
Adaptive in the short term; dysfunctional if persistent, excessive, mistimed or poorly resolved
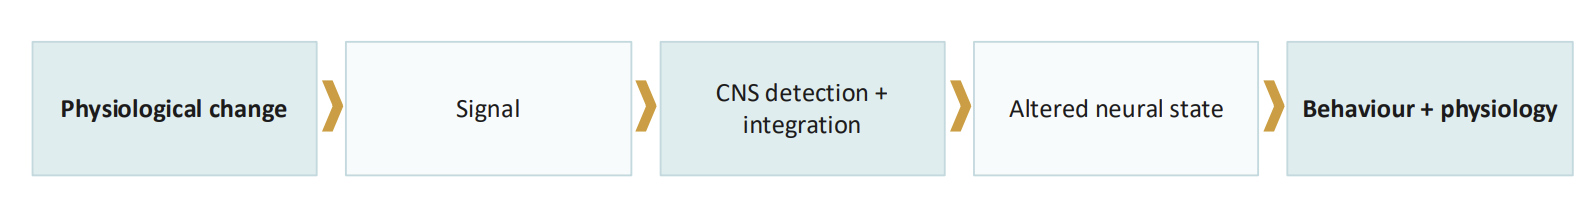
what is the basic pathway of a physiological response
What was the historical "standard" research subject
male as default
How was the female body studied historically
The female body was studied as a reproductive body (only) or a variation (at worst, a malformation) of the male body
What did the 1977 FDA guidance do
Excluded women of childbearing potential from early drug trials
When was the FDA exclusion reversed
1993 – but female research lagged
What was the ratio of male-only to female-only animal studies in 2009 neuroscience
Male-only animal studies outnumbered female-only by ~5.5:1
How was female hormonal cycling often treated
As inconvenient biological noise that would mask effects and statistical significance
why does Sex as a Biological Variable policy matter
Sex and hormonal state can alter disease phenotype, pharmacokinetics and treatment response. Due to the lag in research, there is still a lot we don't know about female physiology
What is the key takeaway about hormonal variation
Hormonal variation is not noise, especially if it systematically changes the biology we are trying to understand
What hormones vary over predictable timescales in the menstrual cycle
Oestradiol and progesterone
Where are receptors for these hormones expressed
Across hippocampus, amygdala, hypothalamus, striatum and cortex
How do these hormones act
Through genomic and rapid signalling mechanisms
What systems are affected
Dopamine, serotonin, glutamate and GABAergic networks
What does the menstrual cycle change
The neurochemical environment in which brain circuits operate → contributes to the dynamic nature of the nervous system & neuroplasticity
What are the phases of the menstrual cycle
Follicular, Ovulatory, Luteal
What hormones peak during the follicular phase
Oestrogen rises
What hormones peak during the ovulatory phase
LH and FSH surge; oestrogen peaks
What hormones peak during the luteal phase
Progesterone rises
what do Age x estradiol and progesterone levels influence
brain connectivity
What networks were influenced by estradiol and progesterone
Whole-brain, DMN, limbic, dorsal attention, somatomotor, and subcortical networks
What is the most likely function of ovarian hormone effects
Coordinated whole-body adaptation to align neural function with reproductive and energetic context
What are the five adaptive functions of ovarian hormones
1. Motivation & reward;
2. Social & emotional processing;
3. Learning & plasticity;
4. Homeostasis;
5. Reproductive behaviour
How do ovarian hormones affect motivation & reward
Alter salience, approach behaviour and reinforcement when reproductive opportunity changes
How do ovarian hormones affect social & emotional processing
Tune sensitivity to social cues, threat and affiliation
How do ovarian hormones affect learning & plasticity
Adjust synaptic strength and network responsivity to current physiological demands
How do ovarian hormones affect homeostasis
Coordinate appetite, energy use, thermoregulation, sleep, stress responses and autonomic function with reproductive state
How do ovarian hormones affect reproductive behaviour
Integrate sexual motivation and behaviour with ovulation and fertility
Are all effects of ovarian hormones beneficial adaptations
no
what are some negative adaptations of reproductive hormones
There are pleiotropic consequences of hormones acting on widely distributed receptors
costs of repeated neural recalibration as hormone levels rise and fall
amplified in susceptible individuals when normal adaptive mechanisms become dysregulated, or due to inherent biological variability
What is the key takeaway about ovarian hormones
Ovarian hormones help the brain optimise behaviour and physiology for the body's current reproductive state; the same plasticity can also generate unintended or maladaptive effects
How does oestradiol change synaptic excitability and plasticity
Both slow (genomic) and fast (phosphorylation cascades) receptor pathways.
Enhance NMDA receptor-mediated glutamatergic signalling.
Alter AMPA/NMDA receptor trafficking and synaptic efficacy.
Increase dendritic spine and synapse formation.
Alter BDNF and other neurotrophic factors
What did Woolley & McEwen 1992 find in rats (estradiol study)
CA1 hippocampal synapse density decreased about 32% over 24h from high-estradiol → estrus
what did human studies on estradiol find
Estradiol-related changes across emotion, reward, memory and resting-state networks
when do estrogen levels rise and drop
rise towards ovulation
drop towards menstruations
What do estradiol and progesterone alter?
Dopaminergic signalling
what happens to dopamine during follicular → just after ovulation
Dopamine levels increase. Dopamine transporter and receptor expression increases
What is the dorsal striatum involved in
Action selection, learning, habits and movement
What is the ventral striatum involved in
Value, motivation, reward prediction, salience
What happens in the dorsal striatum during high estrogen (proestrus/estrus)
GABA release from SPNs decreases, and DA release increases
What happens in the ventral striatum during high estrogen (proestrus/estrus)
DA release increases by increasing VMAT activity, decreasing DAT activity, decreasing DA autoreceptor activity, and decreasing local GABA release
when were ADHD symptoms most severe in female participants (zaritski et al)
in menstruation phase
what is a proposed treatment for ADHD symptoms in menstruation
increase dose few days before, and during menstruation
What is progesterone metabolised to
Allopregnanolone (ALLO) by corpus luteum, circulating levels reflected in brain
What is ALLO
A positive allosteric modulator of GABA receptors
What is GABA
The main inhibitory neurotransmitter of the CNS
What are GABA receptors
fast-acting, ligand-gated ion channels → hyperpolarization → inhibition of neuronal firing
What is an allosteric modulator
Binds to a non-active site on a receptor or enzyme to modify the normal response (volume dial)
What is a positive allosteric modulator
Boosts the normal receptor signal
What happens to progesterone in the follicular phase
Progesterone is low
What happens to progesterone after ovulation
Progesterone rises
What happens to progesterone before menstruation
Falls rapidly
What is the sequence of progesterone effects
Progesterone ↑ and peaks mid-luteal phase →
allopregnanolone ↑ →
"Boosted" GABAA receptor activity →
Increased effectiveness of GABA-mediated firing →
Altered neuronal inhibition, stress responsivity and network excitability
Are GABAA receptors plastic
yes
what is dynamic regulation
GABAA receptor subunits composition and sensitivity changes in response to sustained progesterone exposure
What do changes to progesterone/ALLO cause
Homeostatic recalibration of the inhibitory system
What happens in the follicular phase
Low progesterone / low ALLO → baseline GABAA configuration
What happens in the early luteal phase
↑ progesterone → ↑ ALLO → stronger neurosteroid modulation → adaptive changes in GABAA receptor expression/subunit composition
What happens in the late luteal phase
Rapid ↓ progesterone / ↓ ALLO → (neurosteroid withdrawal) → GABAA receptors must recalibrate again → transient change in inhibitory tone / Excitatory : Inhibitory balance
What is Premenstrual Dysphoric Disorder (PMDD)
Affects 3-8% of women in reproductive years. Cyclic recurrence of debilitating mood symptoms in the luteal phase
What are potential causes of PMDD
Abnormal ovarian hormones? Altered dopamine dynamics? Atypical ALLO sensitivity?
what did Timby et als study on PMDD patients do
Administered IV allopregnanolone to 10 PMDD and 10 control participants.
Functional GABAA receptor activity measured by saccadic eye velocity (SEV) at baseline and after IV injection
what is saccadic eye velocity
Peak speed of rapid eye movements used to shift gaze.
Serves as a reliable, non-invasive neurophysiological marker for GABAA receptor sensitivity in the central nervous system
What were the results of Timby et al. 2016
Controls and PMDD showed opposite sensitivities to allopregnanolone depending on phase (follicular/luteal).
PMDD women were more sensitive to allopregnanolone in the luteal compared to the follicular phase, *p < 0.05
what is the evidence for the claim Ovarian hormones modulate CNS function, including dopaminergic and GABAergic signalling
Many preclinical and human neuroendocrine studies show estradiol alters dopaminergic signalling and corticostriatal responsivity, while progesterone-derived allopregnanolone dynamically modulates GABAA receptors and inhibitory tone.
what is the evidence for the claim ADHD symptoms can vary across menstrual-cycle phases in some women
Zaritsky et al., 2026: 30 women with ADHD treated with amphetamine salts completed 35 days of daily ratings; symptoms were most severe during menstruation and milder in the mid-follicular phase
what is the evidence for the claim Women with ADHD should alter medication by cycle phase
de Jong et al., 2023: case series of 9 women reporting premenstrual symptom worsening and reduced stimulant effect; temporary premenstrual dose increases improved attention, mood and energy in all 9, but the study was uncontrolled.
what is the evidence for the claim PMDD reflects altered neural sensitivity to normal hormonal fluctuations rather than abnormal hormone levels
Ovarian-suppression/add-back experiments show symptoms remit when cycling is suppressed and re-emerge when estradiol/progesterone change; reviews converge on altered sensitivity to normal neurosteroid fluctuations rather than abnormal circulating hormone levels
what is the evidence for the claim Altered allopregnanolone–GABAA signalling is implicated in PMDD
Timby et al., 2016: women with PMDD showed a different phase-dependent physiological response to IV allopregnanolone than controls, consistent with altered GABAA receptor sensitivity across the cycle.
what is the endocrine state in the menstrual cycle
endocrine context varies over days to weeks
what is the endocrine state in pregnancy/postpartum
rapid and profound hormonal transitions
what is the endocrine state in Perimenopause
fluctuating ovarian hormones, sleep and thermoregulatory disruption