Human Processes 1 Exam Revision
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/98

99 Terms
When and how are erythrocytes produced?
When low oxygen levels are detected, the kidneys release erythropoietin which is responsible for synthesising erythrocytes. Iron (from stored ferritin or dietary intake) is transported in the blood by transferrin and released to cells in the bone marrow. In addition to iron, folic acid and vitamin B12 are required for erythropoiesis. Approximately 200 billion erythrocytes are produced daily.
What happens as erythrocytes age? How are they broken down?
They last around 120 days. As they age, they lose structural integrity. Old cells undergo phagocytosis by macrophages in the spleen and liver. As they are broken down, haemoglobin is released and metabolised to bilirubin. The bilirubin enters the blood stream and travels to the liver where it’s further metabolised and the by-products are secreted in bile and the small intestine to be eliminated in the faeces.
What is haemostasis and its 3 phases?
The process of blood clotting in response to damaged blood vessels. Vascular (spasm), platelet (plug) and coagulation phases.
what is meant by a “committed cell” ?
path of specialisation is determined and cannot regress to its precursor (stem cell)
why might those with kidney disease suffer from anaemia?
when the kidney cells fail, they do not produce enough erythropoietin to sustain erythropoiesis in bone marrow
Explain the process of haemostasis (3 phases)
Vascular phase: trauma to the blood vessel stimulates nociceptors which trigger the smooth muscle to contract, causing vasoconstriction of the injured blood vessel. Endothelial cells become sticky. This allows time for clotting to occur, lasting 30 seconds.
Platelet phase: due to injury, collagen fibres are exposed. Platelets arrive at the site and attach to the sticky basal lamina and collagen fibres. Platelets release chemicals that make them sticky to other platelets (platelet aggregation), forming a plug.
Coagulation phase: blood becomes a gel. prothrombin is converted to thrombin which converts soluble fibrinogen to insoluble fibrin to form a mesh that traps erythrocytes and platelets to form a clot. Takes 30 seconds. Clot retraction is when platelets contract within fibrin mesh, reducing size of clot (30-60 min).
List the functions of blood
distribution (O2, waste, hormones)
regulation (pH, temperature, fluid/water)
protection (clotting, immunity)
Describe the composition and physical characteristics of whole blood
plasma (55%) and formed elements (1% Buffy coat of leukocytes and platelets; 45% erythrocytes)
Discuss the composition and functions of plasma
- Plasma proteins; Albumin, Globulins - α, β transport proteins; γ antibodies; Clotting proteins - Fibrinogen; Prothrombin
• Non-proteins - Urea, Lactic Acid, Creatinine
• Nutrients - Carbs, amino acids, fatty acids, Glycerol, Vitamins
• Electrolytes - Na+, K+, Ca2+, Mg2+, Cl-, HCO3-
• Gases - Respiratory O2 and CO2
• Other - Enzymes; Antigens; Antibodies; Hormones
Describe the structure and function of erythrocytes. What’s the benefit of its shape?
biconcave, anucleate, flattened, rich in haemoglobin. To transport gases (O2 and CO2).
→ Increased surface to volume ratio
→ All areas of cytoplasm close to membrane
→ Ability to squeeze through small vessels
Describe the composition of haemoglobin
Made up of 4 polypeptide chains (2 alpha 2 beta) and 4 heme groups containing iron. Can carry up to 4 oxygen molecules
List the classes, structural characteristics, and functions of leukocytes
(3) granulocyte (-phil), (2) agranulocyte (-cyte).
Defence against disease
Granulocytes (Bound granules)
• Neutrophils - Phagocytise bacteria, multilobed nucleus
• Eosinophils - Kill parasitic worms, bilobed nucleus, red granules
• Basophils - Mediators of inflammation (heparin, histamine), bilobed nucleus
Agranulocytes (Lack granules)
• Lymphocytes - Immune response via attack or antibodies
• Monocytes - Migratory phagocyte, kidney shaped nucleus
How are leukocytes are produced
Occurring in the bone marrow, they begin as haemocytoblast stem cells which divide and turn into myeloid or lymphoid stem cells. Then they divide and turn into one of 3 committed cells: myeloblast, monoblast or lymphoblast then follow their developmental pathway and mature in the bone marrow, with the exception of T cells that mature in the thymus (lymphocytes)
Describe the structure and function of platelets (thrombocytes)
2-4 um in animated, rough discs.
mature platelets are:
bound by plasma membrane
anucleate
age rapidly (degenerate after 10 days)
rich in serotonin granules to aid clotting process
Describe how platelets are produced
Haemeocytoblast → megakaryoblast → promegakaryoblast → megakarycyte → platelets
What is the body’s natural anticoagulant?
heparin (produced in the granules of mast cells and basophils)
Discuss the difference between monocytes and lymphocytes in their differentiation
They both start from a haemocytoblasts but the haemocytoblast differentiates into either a myeloid stem cell or lymphoid stem cell.
myeloid = monocyte (much larger)
lymphoid = lymphocyte (travel between blood and lymphatic organs)
Oxygen and carbon dioxide are poorly soluble in plasma so they require erythrocytes for their transport in blood. Describe how erythrocytes transport these gases.
Erythrocytes contain two proteins necessary for the transport of oxygen and carbon dioxide: hemoglobin and carbonic anhydrase.
Hemoglobin is a protein that contains four subunits, each of which has a heme group that can bind oxygen reversibly. Thus, hemoglobin can transport up to four oxygen molecules. Hemoglobin can also transport carbon dioxide, but the carbon dioxide binds reversibly to amino acids within the polypeptide chains, not to the heme group.
Carbonic anhydrase is an enzyme that catalyzes the reversible reaction converting carbon dioxide and water to carbonic acid. The carbonic acid can then dissociate into a hydrogen ion and bicarbonate ion. Most of the carbon dioxide transported in blood is transported as bicarbonate ion.
Describe the general format/prefix/suffix for cell differentiation
-blast (initial stem cell) → -blast (committed cell; first half of stem cell + -blast) → pro-(previous cell name)-cyte (drop -blast) → drop pro- → full cell name
e.g. haemocytoblast → myeloid stem cell → myeloblast → promyelocyte → myelocyte → neutrophil/eosinophil/basophil
e.g. hemocytoblast → myeloid stem cells → monoblast → promonocyte → monocyte
List the functions of haemoglobin
→ Hb loads O2 in the lungs and transports it to
the tissues where it is offloaded for cellular use
→ Hb loads CO2 (waste) and transports it
to the lungs where it is offloaded and exhaled to the
atmosphere (maintains acid-base homeostasis)
→ Hb has a role in vasodilation through its release
of small amounts of nitric oxide
Explain how blood clots are removed from the body
Plasminogen is converted to plasmin, which is fibrinolytic (dissolves clots)
Describe the functions of the skeleton and of bone tissue
support (hard framework to support soft organs)
protect (casing for soft organs against external forces)
movement (for muscles to use as anchors and levers)
mineral storage (deposit and withdrawal of Ca2+ and K+)
blood cell formation (synthesis occurring in marrow)
Name the major regions of the skeleton and describe their relative functions
Axial Skeleton (skull, vertebral column, thoracic cage) - 80 bones
protection, support, carrying
Appendicular Skeleton (limbs, shoulders, hips) - 126 bones
locomotion, environmental manipulation
Compare and contrast the four bone classes and provide examples of each class
Long Bones
• Consists of an elongated long shaft and two ends
• e.g: Finger bones, Femur
Short Bones
• Generally cube-shaped, and stubby
• e.g: Wrist, Ankles, Patella (Sesamoid)
Flat Bones
• Thin, flattened, and slightly curved
• e.g: Skull, Ribs, Sternum, Shoulder blades
Irregular Bones
• Complicated shapes not fitting any classes
• e.g: Vertebrae, Pelvis
Indicate the locations and functions of red and yellow marrow
Red:
in flat bones (sternum, skull, ribs, spongy ends of long bones)
produces RBCs, WBCs and platelets
gets colour from haemoglobin in developing RBCs
Yellow:
found in medullary cavities of long bones
stores lipids
gets colour from carotenoids in fat cells
Indicate the locations and functions of articular cartilage
A form of hyaline cartilage (collagen)
ribs, joint surfaces, diaphyses of long bones
resists outward expansion due to water component
support, flexibility, resilience
Distinguish between the epiphyseal disc and epiphyseal line
The epiphyseal disc is hyaline cartilage and the site of linear growth. When the cartilage is replaced by bone, a line of fusion remains
Indicate the locations and functions of periosteum and endosteum
Periosteum
dual-layer covering external bone surface
outer layer (thick collagen fibres/fibrous) - anchor tendons, muscles and contains most blood vessels and nerves
inner layer (contains osteo stem cells)
innervated, highly vascular and lymphatic
cell repair, bone growth, anchor point for tendons and ligaments
Endosteum
found internally, surrounding the trabeculae and medullary cavity
single layer membrane
internal bone remodelling (breakdown and growth) and reabsorption of internal bone tissue
Describe the histology of compact and spongy bone
Compact Bone (Hard)
• Osteon (Haversian System) - Mineralised, structural unit
• Haversian Canal - Contains capillary and nerve supply
• Volkmann’s Canal - Link blood and nerves to periosteum
Spongy Bone (Cancellous)
• Trabeculae - Align along stress lines
• Lamellae - Deposited by osteocytes in rings
• Canaliculi - Canals joining lamellae and osteocytes
• Endosteum - Surrounds trabeculae providing nutrition
Discuss the chemical composition of bone and the advantages conferred by its organic and inorganic components
• Osteoid - Organic; Collagen; Flexibility
• Mineral Salts - Inorganic; Ca, (PO4)2; Durability
Compare and contrast intramembranous ossification and endochondral ossification
Describe how epiphyseal plates allow long bones to grow
Compare the locations and remodeling functions of the osetoblasts, osteocytes, and osteoclasts
• Osteocytes - Mature bone cells; Former osteoblasts (lacunae, canaliculi)
• Osteoblasts - Bone ‘forming’ cells; Add matrix (endosteum, periosteum)
• Osteoclasts - Bone ‘degrading’ cells; Remove matrix (on hard bone matrix at sites of breakdown/repair); stem from WBCs
Explain how hormones and physical stress regulate bone remodeling
Parathyroid Hormone (PTH)
Blood Ca2+ levels ↓; Bone matrix degraded; Ca2+ released
Calcitonin
Blood Ca2+ levels ↑; Ca2+ deposited in bones; Ca2+ absorbed
Describe the steps of fracture repair
1. Haematoma Formation
Torn vessels, clotting, phagocytes clear debris
2. Fibrocartilaginous Callus
Collagen secreted, broken ends joined, spongy bone
3. Bony Callus
Trabeculae appear in callus, compact bone forms
4. Bone Remodelling
Excess materials removed, shaft walls reconstructed
Classify joints by structure and by function
Structurally:
• Fibrous - Immoveable or slightly moveable
e.g: Skull sutures; Periodontal ligaments
• Cartilaginous - Immoveable and immobile
e.g: Rib and sternum joints; Intervertebral discs
• Synovial - Highly moveable with fluid
e.g: Majority of joints; Patella; Shoulder
Functionally:
• Syntharthroses - Immovable
• Amphiarthroses - Slightly moveable
• Diarthroses - Freely moveable
Describe the structural characteristics of synovial joints
→ Freely moveable joints
→ They have two articulating surfaces covered in hyaline cartilage
→ Surrounded by a fluid-filled joint capsule (synovial fluid)
→ Comprised of fibrous connective tissue
→ Joint capsule is lined with a synovial membrane
Name and provide examples of the six types of synovial joints based on the movement(s) allowed
→ Saddle (first carpometacarpal/thumb base)
→ Hinge (elbow, interphalangeal, ankle)
→ Plane (inter carpal joints)
→ Condyloid (wrist, knuckles)
→ Ball-and-socket (shoulder, hip)
→ Pivot (proximal radioulnar joints)
What is osteoporosis?
→ Bone density regulated by sex hormones
→ ↓ oestrogen = ↑ osteoclast activity
→ Bone matrix is degraded, bone density ↓
→ Increased risk of fractures (porous bones)
What is rickets?
→ Poorly mineralised bones occurring in children
→ Causes bow legs and bone deformities
→ Decreased calcium or Vitamin D in diet
→ Vitamin D promoted intestinal calcium absorption
Compare and contrast the three basic types of muscle tissue
skeletal
striated, bundles, multiple nuclei in cells, attached to skeleton and skin, voluntary
cardiac
striated, sheets, one nucleus, blunt-ended, joined by intercalated discs, found in heart walls, involuntary
smooth
non-striated, sheets, once central nucleus, spindle shaped, walls of hollow organs, involuntary
List four important functions of muscle tissue
thermoregulation (heat generation, piloerection)
movement (locomotion, fine motor, digestion)
posture & stability
circulation and respiration
Describe the gross structure of a skeletal muscle
Connective tissue coverings
Epimysium
• Outer layer surrounding whole muscle
Perimysium
Middle layer surrounding muscle fibre bundles
Endomysium
Inner layer surrounding each muscle fibre
Continuous with tendons
Attach muscles to bones → bone is moved
Fascicles are formed by bundled muscle fibres, composed of myofibrils
Muscle fibres (often called cells)
Myofibrils multinucleate contractile cells
Composed of myofilaments (molecular structure)
Defined by sarcomeres (contractile units)
Nerve Supply
Muscle fibres supplied with motor units for contractibility
Blood Supply
Waste removal, ATP delivery, O2 delivery
Describe the microscopic structure and functional roles of the myofibrils
myofibrils are made of myofilaments
Molecular structure of muscles
composed of sarcomeres
Thick filaments (myosin)
Two polypeptide chains, two globular heads, forming a myosin molecule
Heads contain ATP binding sites
contain 200 myosin molecules
Thin filaments (actin)
Globular proteins linked into chains
These form actin molecule
Strengthened by tropomyosin protein strands
Contains myosin bindings sites (troponin)
Describe the functional roles of the sarcoplasmic reticulum
specialised endoplasmic reticulum
is the network surrounding each myofilament
store, release and reabsorb Ca2+ (into cytosol) for muscle contraction and relaxation
Terminal cisternae
Longitudinal cross channels
T-tubules
Elongated tubes entering cell depths
Discuss the role of ionic calcium in muscle contraction
Actin filaments contain binding sites composed of troponin and tropomyosin (troponin complex)
When Ca2+ levels are low → Tropomyosin ‘blocks’ actin binding sites
When Ca2+ levels increase → Ca2+ binds to troponin causing shape change
Tropomyosin moves away from site → Binding sites free for myosin
Describe the sliding filament model of muscle contraction
Thick Filaments: globular heads
Thin Filaments: binding sites
Ca2+ ‘unlocks’ Actin binding sites causing:
1. Cross-Bridge Attachment
Actin and Myosin bind
2. ‘Power’ Stroke
Myosin pivots and pulls on Actin filament
3. Cross-Bridge Detachment
Actin and Myosin detach
4. ‘Cocking’ of Myosin
Myosin head resumes initial position
Filaments overlap causing contraction
What are the 4 fibre arrangements?
Parallel (Fusiform)
Long, parallel, strap-like; Cover long distances
Convergent
Fan-shaped; Converge at insertion
Pennate (Pinnate)
Short; Many fibres per unit area
Circular
Circular fibre bands; Surround body openings
What is the function of cholinesterase and the advantage of having it at the neuromuscular junction?
To degrade acetylcholine in the synapse
To prevent multiple impulse transmission
Describe the structural and functional relationships between the hypothalamus and the pituitary gland
→ Hypothalamus is connected to pituitary gland by infundibulum
→ Infundibulum contains neural tracts that carry hormones from the hypothalamus to the posterior pituitary (neural tissue)
→ Hypothalamus connects to anterior pituitary via hypophyseal portal system (glandular tissue)
→ Capillaries in the hypothalamus are connected to capillaries in the anterior pituitary via the infundibulum
Describe how hormones are classified chemically
lipid-soluble/steroid and water-soluble/protein/non-steroid
Describe the two major mechanisms by which hormones bring about their effects on their target tissues
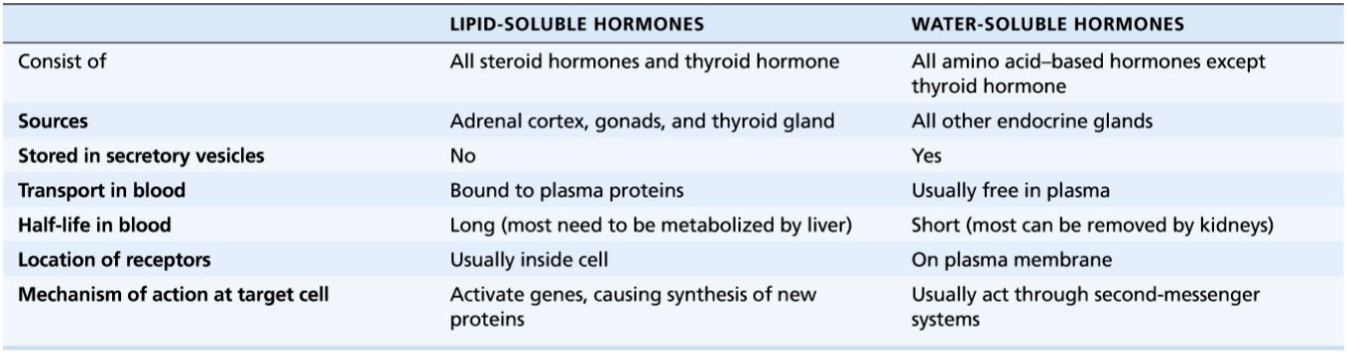
Discuss the structure of the posterior pituitary and describe the effects of the two hormones it releases
List and describe the chief effects of anterior pituitary hormones
Identify the key differences between the posterior and anterior pituitary gland
Describe the effects of the two groups of hormones produced by the thyroid gland
Explain the process of thyroxine formation and release
Describe the hormonal functions of parathyroid hormone and calcitonin on bone homeostasis (feedback loops when too high/low)
Describe the function and regulation of the thyroid hormones T3 and T4
Thyroid hormones influence protein, carbohydrate, and lipid and vitamin metabolism, as well as heat production and cardiac function. Thyroid stimulating hormone, which is made and stored in the anterior pituitary, acts on the thyroid gland, stimulating the secretion of T3 and T4 as needed. Protein-bound T3 and T4 are circulated in the plasma and released as needed for metabolic processes. This process is regulated by a negative feedback loop involving thyroid releasing hormone, the anterior pituitary and the hypothalamus.
Describe the physiological processes involved in antidiuretic hormone (ADH) secretion
The secretion of ADH is primarily accomplished by osmoreceptors in the hypothalamus but also by baroreceptors in the left atrium, the carotids and the aortic arches. The posterior pituitary releases ADH. Mediators are cholinergic and adrenergic neurotransmitters. ADH secretion is increased by changes in intravascular volume and decreased plasma osmolality (increased solute concentration). Stress, trauma, pain, exercise, nausea, nicotine, exposure to heat and drugs can also increase secretion. Decreased plasma osmolality, increased intravascular volume, hypertension and alcohol ingestion decreases the ADH secretion.
List hormones produced by the adrenal gland, and cite their physiological effects
aldosterone - Na+ control via kidneys
cortisol - Immune response and alertness (ie waking)
adrogens - Gonad development
adrenaline - fight or flight (sympathetic NS stimulation)
Compare and contrast the two effects of the two major pancreatic hormones
Identify factors that influence activation of a target cell by a hormone
Which hormones are secreted by the posterior pituitary gland?
oxytocin and antidiuretic hormone
Differentiate between a nucleus, a ganglion, a nerve, and a tract
Explain the importance of the myelin sheath and describe how it is formed in the central and peripheral nervous systems
Explain the structural and functional divisions of the nervous system
List the types of neuroglia and cite their locations
Classify neurons by structure and by function
Define resting membrane potential and describe its electrochemical basis
Explain how action potentials are generated and propagated along neurons
Define absolute and relative refractory periods
Distinguish between electrical and chemical synapses by structure and by the way they transmit information
Define neurotransmitter and classify neurotransmitters by chemical structure
Explain lateralisation of cortical function
Describe the location of the diencephalon, and name its subdivisions and functions
List the major lobes, fissures, and functional areas of the cerebral cortex
Name and locate the ventricles of the brain
Lateral (2) in either hemisphere
Third (in diancephalon)
Fourth (between brain stem and cerebellum)
Identify the three major regions of the brain stem, and note the functions of each area
Describe how meninges, cerebrospinal fluid, and the blood brain barrier protect the CNS
Meninges (physical and structural support)
dura, arachnoid, pia mater (connective tissue)
Together, these layers act as a tight physical sheet and shock absorber that restrains the brain, keeping it from slamming against hard bone during sudden physical impact
Cerebrospinal Fluid (CSF): Mechanical Cushioning & Waste Removal
flows through brains ventricles into subarachnoid space
buoyant suspension, shock absorption, supplies nutrients, clear metabolic waste and lymphatic drainage
BBB: biochemical defence (internal environment protection from threats in the bloodstream)
selective permeability
presence of tight endothelial junctions to prevent large molecules and blood borne pathogens to enter
last line of defence against erratic nerve impulses or stray toxins and neurotransmitters (break down via enzymes)
Explain how cerebrospinal fluid is formed and describe its circulatory pathway
formed by choroid plexus in all ventricles
Describe the gross and microscopic structure of the spinal cord
List the sensory receptors, their functions and locations
Describe sensory perception and adaptation
Name the 12 pairs of cranial nerves; indicate the body region and structures innervated by each

Name the major plexuses and describe the function of the peripheral nerves arising from each plexus
Cervical
Brachial
Lumbar
Sacral
Name the components of a reflex arc and distinguish between autonomic and somatic reflexes
1. Receptor: Site of stimulus action
2. Sensory Neuron: Afferent pathway toward CNS
3. Integrator: Synaptic interchange within CNS
4. Motor Neuron: Efferent pathway away from CNS
5. Effector: Muscle or gland response
Autonomic:
smooth muscle, cardiac muscle and glands
inhibitory OR excitatory/stimulatory
ACh (nerves) OR norepinephrine (blood)
Somatic:
skeletal muscle
stimulatory only
ACh only
single neuron from CNS to effectors
Define cholinergic and adrenergic receptors (ANS)
cholinergic:
binds to ACh
2 types:
nicotinic (always stimulatory)
muscarinic (inhibitory or stimulatory)
adrenergic:
binds to adrenaline (dumped directly into blood as hormone) and noradrenaline (neurotransmitter)
can be inhibitory or stimulatory
2 types:
alpha
beta
Compare and contrast the functions of the parasympathetic and sympathetic divisions
both part of autonomic nervous system
Sympathetic: emergency situations
• ‘Fight or flight’ (positive feedback)
Parasympathetic: energy conserving
• ‘Rest and digest’ (negative feedback)

Define autonomic nervous system and explain its relationship to the peripheral nervous system
The myelination of central and peripheral axons occurs rapidly through the first few years of life. How can this developmental process explain the improved motor abilities of infants and toddlers?
Without full myelination, information about limb movement and body position moves slowly to the CNS, and motor commands move slowly and erratically to the muscles. By the time the brain is aware of movement or position and can issue a motor command, the limb has already moved. When the motor command reaches the skeletal muscle, the response is no longer appropriate. As the neurons become fully myelinated, information processing speeds up, so we observe improved balance, coordination, and movement.
Mary, age 15, is watching a scary movie late at night. She notices that her heart is racing and she is beginning to feel cold and clammy. From what you have read in this chapter, what is causing her to feel this way?
Mary is experiencing stimulation of her sympathetic nervous system. Neurotransmitters such as adrenaline and noradrenaline are being released to prepare her for a ‘fight or flight’ response. This is the same response that Mary would experience if she were in a true life-threatening situation.
What 3 elements make up the neuromuscular junction?
presynaptic membrane
synaptic cleft
postsynaptic membrane
What occurs BEFORE the muscle contracts? (Hint: calcium)
Calcium comes in and binds to TROPONIN → TROPOMYOSIN can roll off → expose myosin binding sites and actin
Explain step-by-step how muscle contraction occurs
Action potential arrives at neuromuscular junction via motor neuron.
neurotransmitter acetylcholine (ACh) is released into synaptic cleft/synapse
ACh binds to post synaptic membrane (the sodium channels on the motor end-plate of sarcolemma), creating an end-plate potential.
Depolarisation of sarcolemma allows action potential to be propagated across the sarcolemma
Ca2+ is released into the sarcoplasm.
at rest, tropinin and tropomysoin wrap around actin, blocking the myosin binding sites
the Ca2+ ions bind to the troponin, allowing the tropomysoin to roll away and expose the myosin binding sites on the actin strands
myosin head attaches to the actin myofilament, forming a cross bridge
inorganic phosphate generated from previous contraction cycle is released, initiating the power stroke. Myosin head pivots and bends as it pulls on actin filament sliding towards the m line. ADP is released
As new ATP attaches to myosin head, the myosin-actin link weakens → cross-bridge detaches
ATP splits into ADP and inorganic phosphate (ATP hydrolysis), the myosin head is energised, ready for cycle to occur again.
What is the cross-bridge formation?
Calcium ions bind to troponin, moving tropomyosin away and exposing the binding sites on actin. The energised myosin head (holding ADP and inorganic phosphate) attaches to actin;
With the actin-binding site unblocked and the myosin head primed with ADP and inorganic phosphate still attached, the myosin head reaches out and binds firmly to the actin filament, forming a physical cross-bridge.
What is the power stroke? What happens?
When the myosin head releases the inorganic phosphate, the myosin head pivots and pulls the actin filament toward the centre of the sarcomere (the M-line). ADP is released during or after this pivoting motion.
The release of inorganic phosphate from the myosin head triggers the power stroke
Why does rigor mortis occur?
Loss of ATP: When a person dies and breathing stops, cells are deprived of oxygen and can no longer produce ATP, the energy molecule required for muscle relaxation.
Actin and Myosin Locking: Without ATP to detach them, the actin and myosin bind together and lock in place.
Calcium Leaks: As cell membranes break down postmortem, calcium floods the muscle fibers, intensifying the contraction and rigidity
compare the endocrine and nervous systems
