Insulin Therapy
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/114

There's no tags or description
Looks like no tags are added yet.
115 Terms
insulin
hormone secreted by the beta cells of the pancreatic islets of Langerhans
- key for cellular glucose uptake
- Most effective in lowering blood glucose levels
- No ceiling effect/maximum dose (unless hypoglycemia)
advantages of insulin
- cost
- weight gain ~ 2-4 kg (rarely edema)
- hypoglycemia
- injection Site Reaction: Pain, Swelling, Lipodystrophy
- requires technique & frequent monitoring of blood glucose levels
disadvantages of insulin
true
T/F: Always initiate insulin first in T1DM.
false, initiate if other therapies have failed, if hyperglycemia is very uncontrolled, or in an inpatient setting
T/F: Always initiate insulin first in T2DM.
1. T1DM
2. Elderly
3. Highly physically activity
4. Erratic meal schedules or less appetite from illness/surgery/stress
caution for hypoglycemia in which patients receiving insulin therapy?
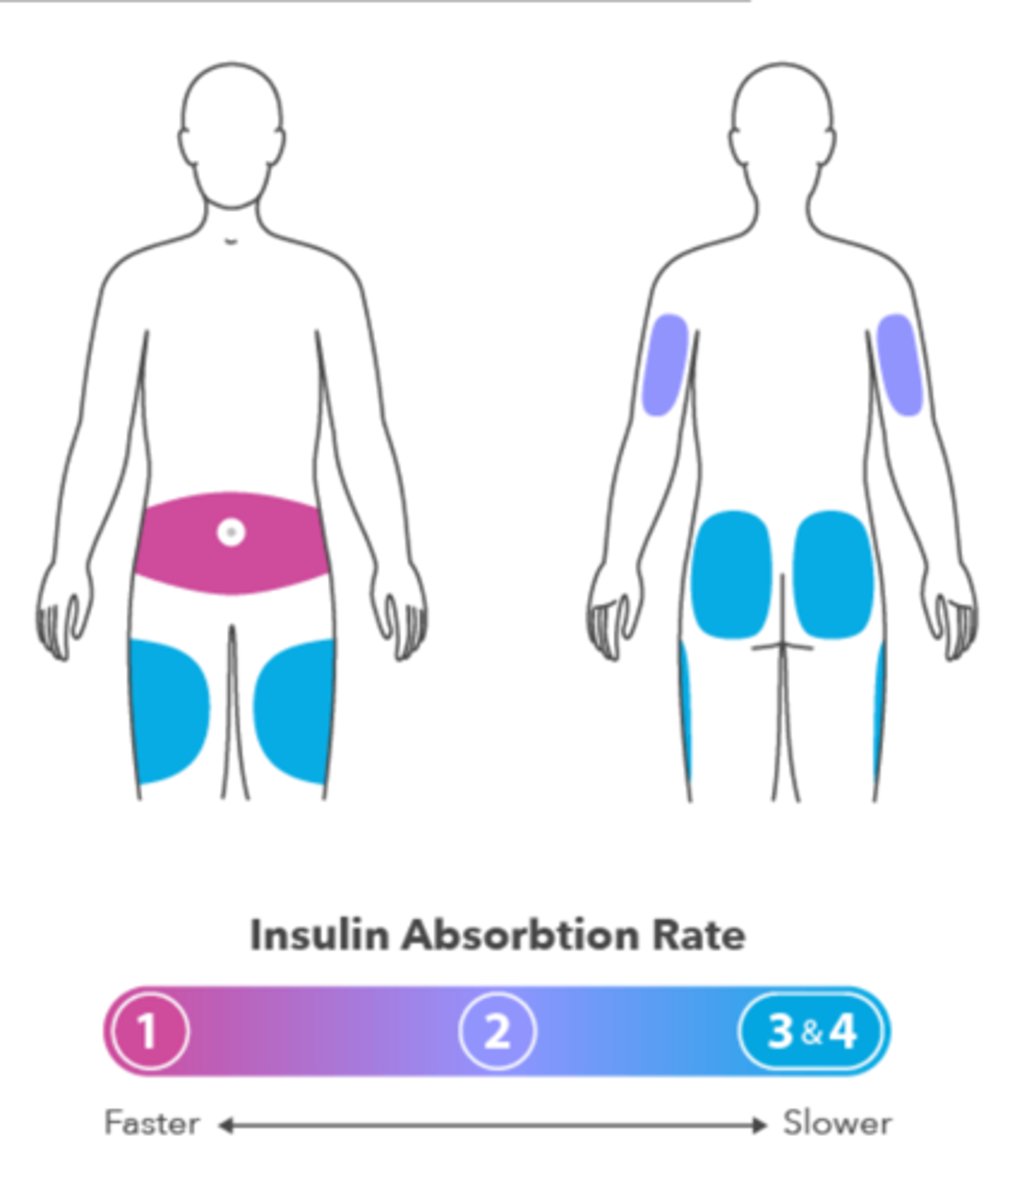
1. SQ injection + Rotate among abdomen, arms, thighs, or buttocks
- inject at least 2 inches away from the belly button
- for multiple injections throughout the day, rotate clockwise around the belly button
2. Unopened vials, store in fridge vs. Opened vials, store at room temp
3. Roll (don’t shake) cloudy insulins
4. Increasing daily injections = higher risk for dosing error
5. Reduce the dose/discontinue agents
- sulfonylurea, meglitinide: hypoglycemia
- TZD: weight gain/edema
clinical pearls for insulin
50% basal
steady insulin between meals/overnight
50% bolus/prandial
peaks of insulin for meals
4-6 hours
how long does aspart/lispro last?
- rapid acting
5-6 hours
how long does Glulisine last?
- rapid acting
2.5-3 hours
how long does inhaled rapid-acting insulin last?
- rapid-acting
6-8 h
how long does regular insulin last?
- short-acting
14-18 h
how long does intermediate [NPH] insulin last?
24-30 h
how long does glargine last?
- long-acting
36-42 h
how long does degludec last?
- long-acting
Humulin N
Novolin N
- human insulins
list the intermediate [NPH] acting insulins used for basal?
Insulin Glargine
Insulin Degludec (ultra long-acting agent)
**Detemir (Levemir) discontinued
- insulin analogues
list the long-acting insulins used for basal?
Humulin R
Novolin R
Myxredlin** IV infusion
- human insulins
list the short-acting insulins used for bolus/prandial
Insulin Lispro
Insulin Aspart
Insulin Glulisine
Insulin Human: HUMAN not analog
- insulin analogues
list the rapid-acting insulins used for bolus/prandial
Humulin 70/30
Novolin 70/30
- human insulins
Humalog Mix
Novolog Mix
- insulin analogues
list the pre-mix insulins
Humalog U-100, U-200
Admelog
Lyumjev*
*ultra-rapid acting
Lispro brands
Novolog
Fiasp*
*ultra-rapid acting
Aspart brand
Apidra
Glulisine brand
Afrezza
*ultra-rapid acting
*not an analog; human insulin
inhaled insulin brand
10-30 min
onset of action of rapid-acting insulins
- Lispro (Humalog U-100, U-200, Admelog, Lyumjev*)
- Aspart (Novolog, Fiasp*)
- Glulisine (Apidra)
- Human inhaled insulin (Afrezza*)
* ultra-rapid acting
0.5-1.5 h
peak effect of rapid-acting insulins
- Lispro (Humalog U-100, U-200, Admelog, Lyumjev*)
- Aspart (Novolog, Fiasp*)
- Glulisine (Apidra)
- Human inhaled insulin (Afrezza*)
* ultra-rapid acting
3-5 h
duration of rapid-acting insulins
- Lispro (Humalog U-100, U-200, Admelog, Lyumjev*)
- Aspart (Novolog, Fiasp*)
- Glulisine (Apidra)
- Human inhaled insulin (Afrezza*)
* ultra-rapid acting
Administration: within 15 minutes before meals or immediately after
- except Afrezza, Fiasp, Lyumjev
Composition: clear and colorless
Stability and Storage: 28 days at room temp
- except Afrezza
key points for rapid-acting insulins
- Lispro (Humalog U-100, U-200, Admelog, Lyumjev*)
- Aspart (Novolog, Fiasp*)
- Glulisine (Apidra)
- Human inhaled insulin (Afrezza*)
* ultra-rapid acting
15 min BEFORE meals or immediately after
**except: Lyumjev and Fiasp: usually administered at the start of the meal or within 20 minutes of starting a meal
**except: Afrezza (inhaled): inhale at the beginning of a meal
When to administer rapid-acting insulins?
- Lispro (Humalog U-100, U-200, Admelog, Lyumjev*)
- Aspart (Novolog, Fiasp*)
- Glulisine (Apidra)
- Human inhaled insulin (Afrezza*)
* ultra-rapid acting
at the start of the meal or within 20 minutes of starting a meal
When to administer the ultra-rapid acting insulins Lyumjev (lispro) and Fiasp (aspart)?
inhale at the beginning of a meal
When to administer the ultra-rapid acting inhaled insulin Afrezza?
28 days at room temperature
**except Afrezza: replace inhaler every 15 days; comes in blister packs; blister packs good for 10 days unopened and 3 days for opened packs.
How long are rapid acting insulins good for?
- Lispro (Humalog U-100, U-200, Admelog, Lyumjev*)
- Aspart (Novolog, Fiasp*)
- Glulisine (Apidra)
* ultra-rapid acting
replace inhaler every 15 days; comes in blister packs; blister packs good for 10 days unopened and 3 days for opened packs.
How long is the ultra-rapid acting inhaled insulin Afrezza good for?
- inhale at beginning of meal
- blister packs good for 10 days unopened; only 3 for opened
- inhaler only good for 15 days
- do not use in patients with asthma, COPD, or who smoke
Afrezza administration pearls
15-30 min
onset of action of the short-acting human insulins
- Humulin R U-100, U-200
- Novolin R
2-4 hours
peak effect of the short-acting human insulins
- Humulin R U-100, U-200
- Novolin R
4-8 hours
**13-24 hours for Humulin R U-500
duration of the short-acting human insulins
- Humulin R U-100, U-200
- Novolin R
Administration: 30 min before meals
Concentrated Insulin: Recommended in patients that require > 200 units/day
Composition: clear and colorless
Availability: OTC [100 unit/ml only]
key points for the short-acting human insulins
- Humulin R U-100, U-200
- Novolin R
in patients that require > 200 units/day
when is U-500 short-acting insulin preferred?
30 minutes BEFORE meals
when is short-acting insulin administered?
31 days
storage/stability of Humulin R vial U-100
40 days
storage/stability of Humulin R vial U-500
28 days
storage/stability of Humulin R pen U-500
2-4 h
onset of action of intermediate-acting [human] insulin
- Humulin N, Novolin N
- basal
42 days
storage/stability of Novolin R vial
28 days
storage/stability of Novolin R pen
4-12 h
peak effect of intermediate-acting [human] insulin
- Humulin N, Novolin N
- basal
14-18 h
duration of intermediate-acting [human] insulin
- Humulin N, Novolin N
- basal
- Administration: usually given once or twice daily [BASAL]
- If mixing insulins, pull up clear before cloudy
- Composition: cloudy due to protamine in NPH; roll the medication to mix it; don't shake
- Availability: OTC [100 unit/mL]
key points for intermediate-acting [human] insulin
- Humulin N, Novolin N
- basal
31 days
storage and stability for Humulin N vial U-100
14 days
storage and stability for Humulin N pen U-500
42 days
storage and stability for Novolin N vial
28 days
storage and stability for Novolin N pen
0.5-1 h
onset of action for human insulin intermediate + short-acting
- Humulin 70/30 (70% NPH + 30% regular)
- Novolin 70/30 (70% NPH + 30% regular)
2-10 h
peak effect for human insulin intermediate + short-acting
- Humulin 70/30 (70% NPH + 30% regular)
- Novolin 70/30 (70% NPH + 30% regular)
10-18 h
duration for human insulin intermediate + short-acting
- Humulin 70/30 (70% NPH + 30% regular)
- Novolin 70/30 (70% NPH + 30% regular)
10-15 min
onset of action for analogue insulin protamine + rapid-acting
- Humalog Mix 75/25 (75% lispro protamine + 25% lispro)
- Humalog Mix 50/50 (50% lispro protamine + 50% lispro)
- Novolog Mix (70% aspart protamine + 30% aspart)
10-16 h
duration for analogue insulin protamine + rapid-acting
- Humalog Mix 75/25 (75% lispro protamine + 25% lispro)
- Humalog Mix 50/50 (50% lispro protamine + 50% lispro)
- Novolog Mix (70% aspart protamine + 30% aspart)
1-7 hours
peak effect for analogue insulin protamine + rapid-acting, Humalog Mix 75/25 (75% lispro protamine + 25% lispro)
1-5 hours
peak effect for analogue insulin protamine + rapid-acting, Humalog Mix 50/50 (50% lispro protamine + 50% lispro)
1-4 hours
for analogue insulin protamine + rapid-acting, Novolog Mix (70% aspart protamine + 30% aspart)
Lantus U-100
Basaglar U-100
Semglee U-100
Rezvoglar U-100
Toujeo U-300
formulations for long-acting glargine
1:1
Detemir (Levemir) was discontinued by the manufacturer in December 2024. Many patients have been switched to Glargine (Lantus). What is the conversion ratio from Levemir to Lantus?
Glargine/Lixisenatide
what is in the long-acting insulin Soliqua 100/33
Tresiba U-100, U-200
Degludec brand
- ultra-long acting
Degludec/Liraglutide
what is in the long-acting insulin Xultophy 100/3.6
2-3 hours
onset of action for long-acting glargine
1 hour
onset of action for long-acting degludec
Administration: given as once daily (except Levemir once or twice daily)
Composition: clear and colorless
Stability and Storage: 28 days at room temp (except Levemir: 42 days and Toujeo: 56 days)
key points for long-acting insulins
GLP-1 agonist
preferred to insulin after failed PO therapy for T2DM.
>3 months; basal [glargine, degludec, NPH]
if A1c is uncontrolled after _____ months of triple therapy, initiate ______ insulin
1. A1c > 10%
2. blood glucose ≥ 300 mg/dL
3. ongoing catabolism (weight loss)
4. significant symptoms of hyperglycemia are present
when would you introduce insulin therapy in type 2 diabetics?
0.1-0.2 units/kg/day OR 10 units/day
for initiating insulin therapy in T2DM, add a basal such as a long-acting insulin analog or bedtime NPH insulin (intermediate-acting), starting at what dose?
2 units
For titration of basal insulin in T2DM, increase by _____ every 3 days to reach FPG target without hypoglycemia
10-20%
For titration of basal insulin in T2DM, decrease by _____ for hypoglycemia without clear reason.
Basal > 0.5 units/kg/day (or)
Elevated bedtime-morning differential (or)
Elevated post pre-prandial differential (or)
Hypoglycemia
what are some things to assess for overbasalization and an A1c above target?
4 units/day or 10% of basal dose
If a patient's basal insulin is > 0.5 units/kg/day, add a prandial (bolus) insulin to the largest meal of the day or add additional NPH. For prandial insulin, what is the starting dose? how is it titrated?
increase 1-2 units or 10-15% twice a week
If a patient's basal insulin is > 0.5 units/kg/day, add a prandial (bolus) insulin to the largest meal of the day or add additional NPH. For prandial insulin, the starting dose is 4 units/day or 10% of basal dose. how is it titrated up?
decrease by 10-20% for hypoglycemia without a clear reason
If a patient's basal insulin is > 0.5 units/kg/day, add a prandial (bolus) insulin to the largest meal of the day or add additional NPH. For prandial insulin, the starting dose is 4 units/day or 10% of basal dose. how is it titrated down?
80% of current bedtime NPH dose
If a patient's basal insulin is > 0.5 units/kg/day, add a prandial (bolus) insulin to the largest meal of the day or add additional NPH. For additional NPH, what is the dose?
dose #1: 2/3 in AM
dose #2: 1/3 at HS
If a patient's basal insulin is > 0.5 units/kg/day, add a prandial (bolus) insulin to the largest meal of the day or add additional NPH. For additional NPH, use 80% of current bedtime NPH dose. For NPH dose #1 use _____ in AM, and for dose #2, use ____ at night.
A. Stepwise addition of Prandial Insulin (e.g., 2 injections, then 3 injections)
B. Add 4 units of Short/Rapid-acting insulin or 10% of NPH dose to each NPH injection
C. Convert to twice daily premix regimen (Same TDD of insulin)
After adding prandial insulin or additional NPH to a type 2 diabetics regimen and they are still above target A1c, what do you do?
B. 17 units
TL has been experiencing hypoglycemia while on basal insulin 20 units daily without a clear cause. What basal insulin dose should you recommend?
A. 19 units
B. 17 units
C. 15 units
D. 12 units
E. 10 units
C. 16 units in the morning, and 8 units at bedtime
WE with type 2 diabetes is on oral agents and NPH insulin 30 units at bedtime, but her blood sugars are still uncontrolled. When converting to a twice-daily NPH regimen, what directions should you recommend?
A. 12 units in the morning, and 12 units at bedtime
B. 15 units in the morning, and 15 units at bedtime
C. 16 units in the morning, and 8 units at bedtime
D. 20 units in the morning, and 10 units at bedtime
0.4 - 1.0 units/kg/day (usually 0.5 units/kg/day: standard of care)
For initiating initial total daily dose (TDD) of insulin in T1DM, what is the starting dose normally?
0.7 - 1.2 units/kg/day
For initiating initial total daily dose (TDD) of insulin in T1DM, what is the starting dose in pregnant patients?
1.5 units/kg/day
For initiating initial total daily dose (TDD) of insulin in T1DM, what is the starting dose for patients in puberty?
1.5 - 2 units/kg/day
For initiating initial total daily dose (TDD) of insulin in T1DM, what is the starting dose in patients who are obese?
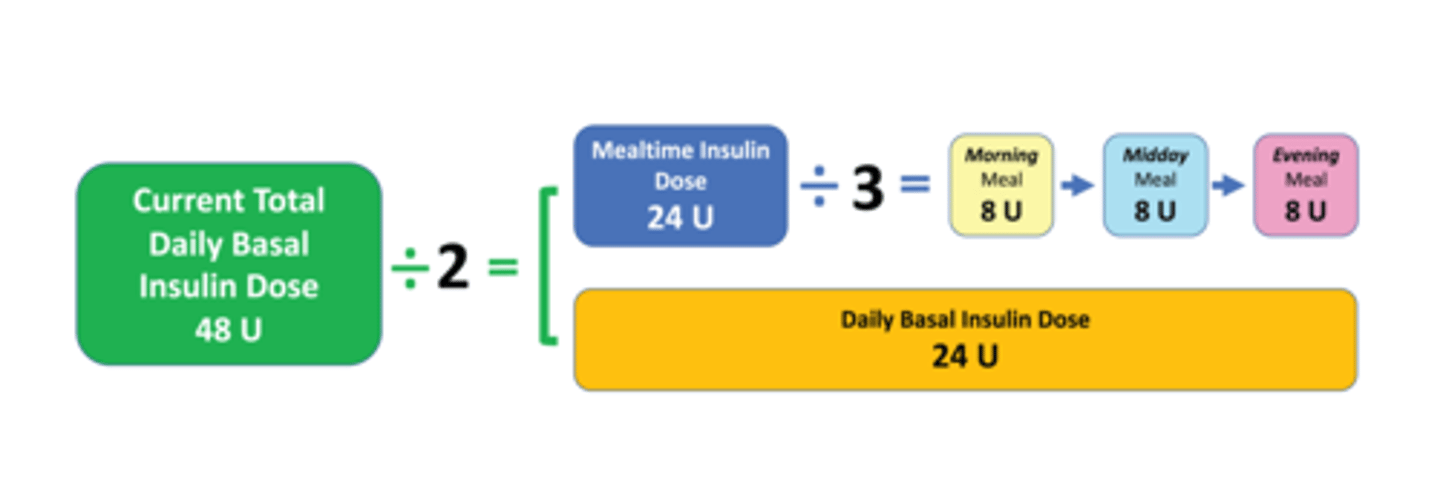
start with 50% basal, 50% bolus divided by meals
- Bolus will be strongly dependent on Carbohydrates and Elevated BSG!
how is insulin therapy divided for patients with T1DM?
Pramlintide (Symlin)
what may be used as adjunct therapy in patients with T1DM?
B. 13 units/day
AB is a newly diagnosed type 1 diabetic adult who is normal BMI (50 kg) and has no other comorbidities. What is a recommended daily basal insulin dose for patient to administer?
A. 5 units/day
B. 13 units/day
C. 26 units/day
D. 50 units/day
B. 4 units TID
AB is a newly diagnosed type 1 diabetic adult who is normal BMI (50 kg) and has no other comorbidities. What is a recommended bolus insulin dose for patient to administer at each meal?
A. 2 units TID
B. 4 units TID
C. 10 units TID
D. 25 units TID
Basal: 50% at Bedtime
Bolus: 20% pre-breakfast, 10% pre-lunch, 10% pre-dinner
Less Flexible Insulin Regimen for T1DM: Intermediate-Acting NPH + Rapid Acting/Short-Acting Insulin. What % of TDD should be basal and bolus (in what increments)?
Pre-Breakfast: 40% NPH + 15% Rapid/Short Acting
Pre-Dinner: 15% Rapid/Short Acting
Bedtime: 30% NPH
To reduce daily injections for T1DM, there are fewer injections regimens. Three Injections Daily: Intermediate-Acting NPH + Rapid Acting/Short-Acting Insulin. What % of TDD should be injected prebreakfast, predinner, and at bedtime?
Pre-Breakfast: 40% NPH + 15% Rapid/Short Acting
Pre-Dinner: 30% NPH + 15% Rapid/Short Acting
To reduce daily injections for T1DM, there are fewer injections regimens. Two Injections Daily: Intermediate-Acting NPH + Rapid Acting/Short-Acting Insulin. What % of TDD should be injected prebreakfast and predinner?
Pre-Breakfast: 40% NPH + 15% Rapid/Short Acting
Pre-Dinner: 30% NPH + 15% Rapid/Short Acting
Calculate TDD = 42 units
Basal for pre-breakfast: 0.4 (42 units) = 16.8 = 17 units
Basal for pre-dinner: 0.3 (42 units) = 12.6 = 13 units
Lispro: 0.15 (42 units) = 6.3 = 6 units prebreakfast and predinner
TD is a type 1 diabetic patient who is currently on 21 units of Insulin glargine once daily in the morning, and 7 units of Insulin lispro three times a day before meals. It is very difficult for him to injection insulin so frequently while being in school. How will you adjust his insulin regimen to two injections per day?
Rule of 450: carbs (g) Covered by Insulin (1 unit) = 450 / TDD Insulin
For T1DM, we prefer to start with 50% Basal +50% Bolus. With monitoring, we want to adjust the Bolus Dose for EACH MEAL and snack based on the insulin-to-carbohydrate ratio (ICR) to cover meals. What is the rule for short-acting insulin?
Rule of 500: carbs (g) covered by insulin (1 unit) = 500/TDD insulin
For T1DM, we prefer to start with 50% Basal +50% Bolus. With monitoring, we want to adjust the Bolus Dose for EACH MEAL and snack based on the insulin-to-carbohydrate ratio (ICR) to cover meals. What is the rule for rapid-acting insulin?
Rapid-acting: Rule of 1800: BSG (mg/dL) Covered by Insulin (1 unit) = 1800 / TDD Insulin
For T1DM, we prefer to start with 50% Basal +50% Bolus. With monitoring, want to adjust Bolus Dose for EACH MEAL and SNACKS based on the insulin sensitive factor to cover elevated BSG between meal. For rapid-acting insulin, what is the rule for BSG covered by 1 unit of insulin?