Lecture 12: Bacterial and Other Causes of Neurologic Disease
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/39

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
40 Terms
brain abscess prognosis
very poor without surgical drainage and long term antibiotics
brain abscess clinical signs
vital signs normal, slow onset, asymmetric
CSF/CBC: inflammatory to normal
antimicrobial therapy and surgical drainage for success
adults to young adults
dehorning/sinusitis/inner ear infections, nasal foreign bodies are risk factors
trueperella pyogenes
signs due to compression rather than due to inflammation
pituitary abscess
defined as a relatively rare abscess of the pituitary often caused by trueperella pyogenes in ruminants
pituitary abscess clinical signs
acute and progress rapidly over a 7-10 day period
general signs include ataxia, head and neck extension, inappetence, depression, and bradycardia
neurologic signs include a base-wide stance, ataxia, head-pressing, asymmetric CN deficits with dysphagia, blindness, anisocoria, lack of pupillary light reflexes, mydriasis, lack of tongue tone, nystagmus, facial paralysis, ventrolateral strabismus, and head tilt
eventually recumbency, coma, and death
pituitary abscess EEP
pyogenic infection of the head may predispose → vegetative foreign material
agent reaches pituitary via hematogenous spread
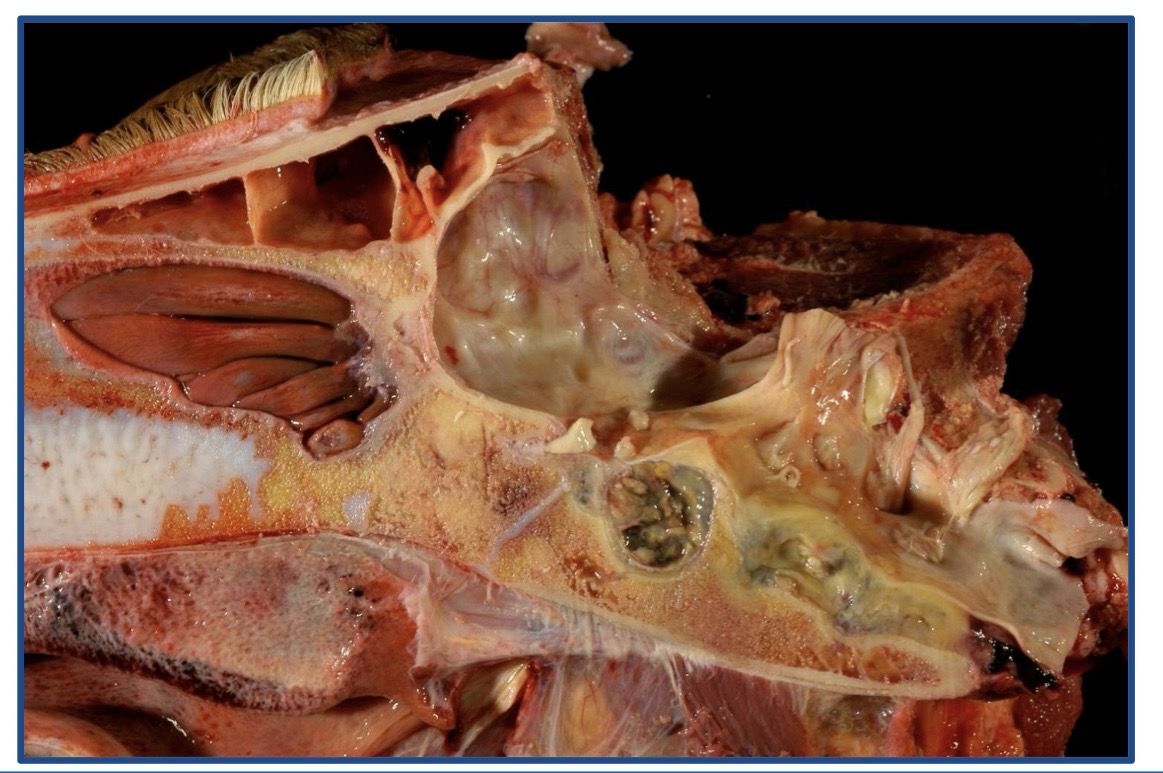
what is this?
pituitary abscess
plant foreign bodies
remnants of 5-inch thorny stick was removed from the right nasal passage and along with the heat, was determined to be the cause of the open mouth breathing → allergic rhinitis, rete mirabilia
also consider fox tails and plant awns
tetanus
progressive muscular rigidity due to a clostridium tetani neurotoxin → gram + rod
tetanus clinical signs
initially stiff, airplane ears, sawhorse stance, hypertonia, retracted lips, trismus (lockjaw)
lateral recumbency and muscular rigidity that becomes worse with auditory, ocular, or tactile stimuli → eventual respiratory paralysis and death
tetanus diagnosis
limbs and head resistant to passive flexion
history → castration, parturition, tail docking
no reliable clinicopathological tests
no characteristic lesions on necropsy
culture suspected at site of entry
tetanus treatment
eliminate toxin → remove existing and future toxin
tetanus antitoxin → binds free tetanus toxin only → 50,000 to 100,000 once
tetanus toxoid
antibiotics
muscular relaxation
TLC
consider rumenostomy
cannulation for rumen fluid collection and enteral feeding
sources → cannulated cow, animal at slaughter, oral collection
use → ASAP, can be started short term
tetanus EEP
soil and feces
sporadic but epidemics reported
incubation period is 2 weeks and 1 month
entry via the uterus → common in dairy cattle
tetanospasmin
toxin responsible for clinical signs
binds to nerves and transported to CNS
at spinal cord, crosses synaptic cleft to presynaptic inhibitory interneurons
inhibits release of glycine and GABA from renshaw cell
results indisinhibition of gamma motor neurons
results in hypertonia and muscular spasms
tetanolysin
promotes spread of tetanus by increasing local tissue necrosis
tetanus vaccine
not routine in cattle (should be routine in sheep and goats)
tetanus mortality is
up to 80%
botulism
progressive muscular hypotonia → rear to front, no effect on peripheral sensory nerves and CNS
clostridium botulinum
ID toxin in serum, GI, or food
antitoxin is effective early, TLC
botulism incubation period is
1-7 days
botulism performed toxin
animal carcasses (type C)
spoiled silage (type B)
pica (type D)
botulism snare protein
SNAp REceptor → aids in fusion of vesicles of neurotransmitters
botulinum toxin → cleaves snare proteins and prevents fusion of vesicle
botulism treatment
EQ → antitoxin and toxoids
healing is based on the decay of bound botulism toxin at the nerve
supportive care
otitis media
commonly due to infections by mycoplasma bovis
can see concurrent infections with respiratory disease and arthritis
source is thought to be contaminated milk/colostrum
otitis media radiographs
may show opacification of the tympanic bulla (normally air filled)

what is this?
otitis media with opacification of tympanic bulla
otitis media therapy
appropriate antimicrobial
± myringotomy
± TBO
full recovery 60%
lead poisoning
a diffuse cerebral disease
aggression, convulsions, central blindness, wandering, head pressing, opisthotonos, odontoprisis, bellowing, and eventual death
CBC → basophilic stippling and nucleated RBCs

what is this?
lead poisoning histology
lead poisoning therapy
urinary lead extraction following Ca EDTA, D-penicillamine or succine treatment
treat with thiamine as well
magnesium sulfate laxatives help form insoluble lead sulfides
sources of lead poisoning
lead paint, linoleum, caulking compounds, batteries (auto), old machinery oil or grease, etc
lead poisoning control
minimize contact
other mineral deficiencies can enhance lead absorption
lead poisoning prognosis
fair with aggressive and early treatment
locoweed
species of oxytropis and astragalus
toxin is swainsonine
at altitudes it can lead to heart failure
swainsonine
leads to a storage disease similar to mannosides
inhibits alpha-mannosidase
quick removal of the toxin can be reversible
chronic exposure is irreversible
organophosphate
OP vary considerably in potency → inhibit the recycling of inhibitory acetylcholinesterase
differential for rear end weakness and flaccid paralysis
treatment often unsuccessful → atropine, cholinesterase reactivators, emetics, cathartics, etc
salt poisoning
overload of salt or lack of water intake
aggressiveness then recumbency to coma
diagnostic history → distance to water or frozen water or lack of water
serum and CSF Na markedly elevated
histopath → brain edema and cortical lesions
salt poisoning treatment
slowly decrease sodium levels
quick/fast administration of significantly less osmolar substances will lead to water intake into nervous tissue and cell bursts
infrequent PO offering of water
calculating and IV administration of slightly less osmolar fluids
vitamin A deficiency
characterized by central blindness due to vitamin A deficiency
occurs primarily when stock does not have access to succulent plants
abnormal bone development constricts optic nerve
calves born with normal levels may require supplementation
prominent blindness not reversible

what is this?
calf born with micropthalmia from vitamin A deficiency
clinical signs of vitamin A deficiency
reduced feed intake and growth
rough hair coat
blindness
night blindness
edema
diarrhea
seizures
decreased repro growth and growth performances