AE 1.2 - Echo Protocol
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/22

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
23 Terms
parasternal long axis
- left sternal border, @ 3rd intercostal space
- index marker to the patient’s right shoulder
can see:
- RV, IVS, LV, LVOT, AV, LA
- start high
- have the patient exhale
- move down a rib space
Tips
- LV should be perpendicular to the beam
- should NOT see apex - if you do you are too lateral or too low

- left sternal border, @ 2nd intercostal space
- index marker to the patient’s right shoulder
can see:
- ascending aorta (runs NE to SW)
- right pulmonary artery (circle below)
Tips
- aorta should be open
- should try to see short axis of right PA

- left sternal border, @ 3rd intercostal space
- index marker to the patient’s right shoulder
- tilt transducer anteriorly towards the patient’s left shoulder
can see:
- RVOT, PV, PA
Tips
- may need to move up a rib space
- may need a slight clockwise rotation

- left sternal border, @ 3rd intercostal space
- index marker to the patient’s right shoulder
- tilt transducer inferiorly towards the patient’s right hip
can see:
- RV, TV, RA
Tips
- may need a slight rotation counterclockwise
- may need to move down a rib space to make image more vertical
- should not see the LV (tilt more if you do)

parasternal short axis
- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- RA, LA, PA, PV, AV, TV
- tilt transducer inferiorly
Tips
- should see all 3 AV cusps
- should see all 3 valves
-- TV, AV, PV

- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- tilt transducer inferiorly
- should see all 3 AV cusps
-- RCC (top), LCC (right), NCC (left)
Tips
- sometimes can see:
-- left main coronary artery origin at around 3-5:00
-- right coronary artery origin around 11:00

- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- tilt transducer superiorly
- RA, RVOT, PV, PA, LPA, RPA, Aorta
Tips
- rock to center right side, and bring in PA (RVOT)
- may need to move up a rib space
- look for “legs” or bifurcation of PA

- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- tilt transducer inferiorly
- RV, TV, RA
Tips
- rock to other side (RVIT)
- move sector to focus on tricuspid valve

- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- continue to tilt transducer inferiorly
- tilt down or slide down
- RV, IVS, LV, AMVL, PMVL
Tips
- need to see both leaflets
-- AMVL (top)
-- PMVL (bottom)
- LV should be circular, not oblong shape
-- if not a circle, need to slightly rotate counter or clockwise or move up a rib space
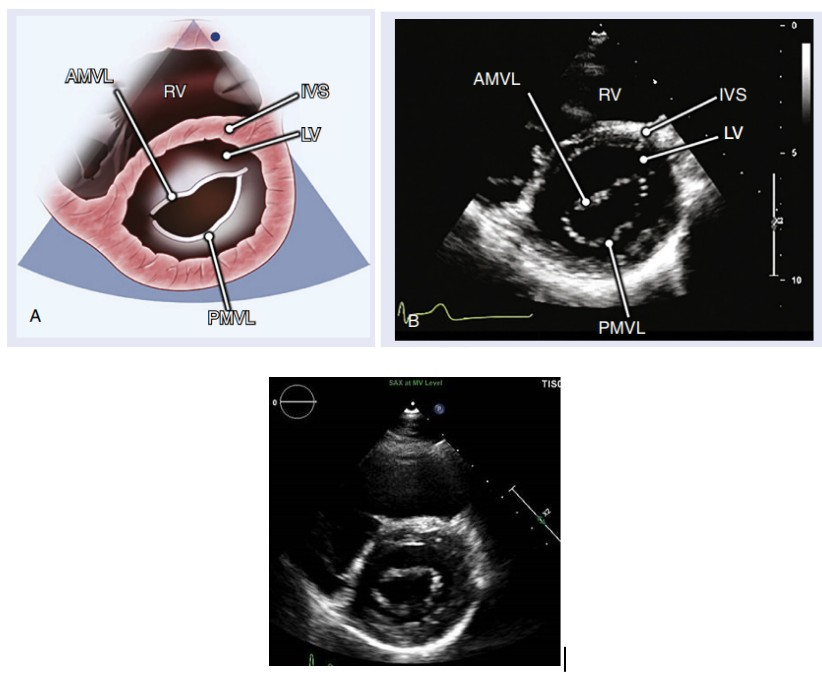
- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- continue to tilt transducer inferiorly
- RV, LV, ALPap, PMPap
Tips
- need to see both pap muscles
-- ALPap (anterolateral)
-- PMPap (posteriomedial)
- LV should be circular, not oblong shape
-- if not a circle, need to slightly rotate counter or clockwise or move up a rib space

- left sternal border, @ 3rd intercostal space
- rotate marker 90° clockwise from PLAX view
- continue to tilt transducer inferiorly
- LV apex
Tips
- may need to slide down a rib space
- should not see papillary muscles in this view or it is not the apex!

apical 4 chamber
- mid-axillary line, start @ 5th intercostal space (PMI)
- index marker down towards the bed
- IVS, LV, RV, MV, TV, LA, RA, IAS
Tips
- use patient positioning and breathing to optimize
- start low and move up a rib space as needed
- if the ventricle is foreshortened, the apex will appear more rounded
- typically long axis of heart should be 2/3rd LV, 1/3rd RV

- mid-axillary line, start @ 5th intercostal space
- index marker down towards the bed
- zoom to LV & LA separately
- LV, MV
- LA, RA, TV, Pulmonary veins

- mid-axillary line, start @ 5th intercostal space
- index marker down towards the bed
- slide laterally
- transducer is then rotated slightly counterclockwise
- angle the transducer medially
- LV, LA, RV, TV, RA
Tips
- view all of RV free including the apex
- center RV
- view for right-sided measurements

apical 5 chamber
- mid-axillary line, start @ 5th intercostal space
- index marker down towards the bed
- tilt anteriorly until the LVOT, AV, and prox Asc Ao come into view
- IVS, LV, RV, LVOT, LA, Aorta
Tips
- may need to move up a rib space to open aorta
- must see proximal aorta

apical 2 chamber
- mid-axillary line, start @ 5th intercostal space
- rotate transducer 60° counterclockwise (toward left shoulder) from A4C
- LV, MV, LA, LAA, anterior wall, inferior wall
Tips
- may need to slide to look for view
- should not include RV

- mid-axillary line, start @ 5th intercostal space
- rotate transducer 60° counterclockwise
- zoom LV
- zoom LA
- LV, LA

apical 3 chamber
- mid-axillary line, start @ 5th intercostal space
- rotate transducer another 60° counterclockwise (toward right shoulder) from the A2C view
- LV, MV, LA, LVOT, AV, Ao
- anteroseptal wall (IVS), inferolateral wall
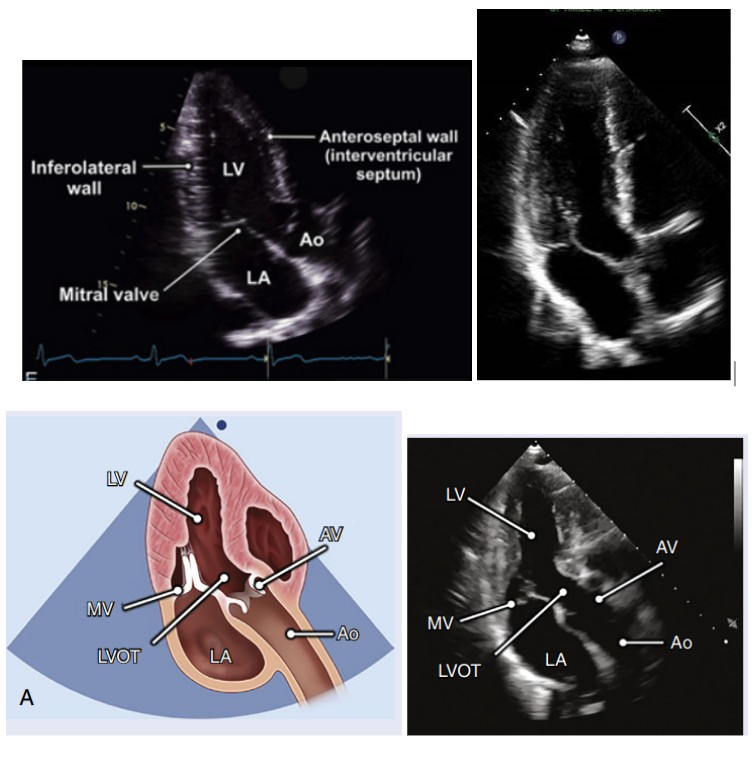
- mid-axillary line, start @ 5th intercostal space
- rotate transducer another 60° counterclockwise from the A2C view
- LV

- patient supine
- index marker pointed to the patient’s left, at about a 3:00 position
- transducer pointed towards patient’s left shoulder
- RV, TV, RA, IAS, IVS, LA, MV, LV
Tips
- have patient bend his/her knees to relax stomach
- have patient take breath in and hold if you can’t find image
- watch the RV, make sure it is open and not collapsed

- Patient supine
- index marker pointed to the patient’s left, at about a 3:00 position
- counterclockwise rotation of the transducer approximately 90°
- angle towards the liver
- liver, IVC, RA

- patient supine
- index marker pointed to the patient’s left, at about a 3:00 position
- counterclockwise rotation of the transducer approximately 90°
- angle towards the liver
- Hvn, IVC
Tips
- try tilting anteriorly to get hepatic veins

- patient lying supine
- the patient’s neck should be relaxed with a slight upward tilt of the chin
- remove the pillow from behind the patient’s head (can always place the pillow under the shoulders)
- transducer marker ~1:00
- slight inferior angle towards the left hip
