NURO ANATOMY
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/4

Earn XP
Description and Tags
FULL
5 Terms

BRAINSTEM
: What are the major parts of the brainstem, and which structures identify its main cross-sectional levels?
What is the corticospinal tract, where does it cross, and what happens when it is damaged?
What do the medial lemniscus, spinal lemniscus, and spinocerebellar tracts carry?
Which trigeminal nuclei carry facial sensation, and what deficits follow their damage?
What are the important medullary nuclei, and what clinical findings result when they are damaged?
: How do lateral medullary (Wallenberg) syndrome and medial medullary syndrome differ?
What are the major pontine pathways, nuclei, and clinical associations?
What are the major midbrain structures at the inferior and superior colliculus levels?
How do Weber and Benedikt syndromes arise, and how do you distinguish them clinically?
How can you rapidly localize a brainstem lesion using the most important tract, nucleus, and syndrome associations?
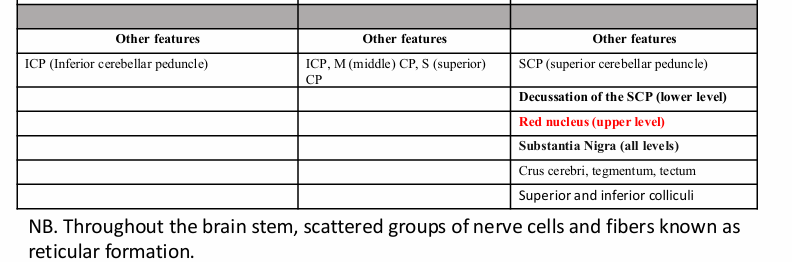
Function: Inferior Olivary Nucleus • Med. Long. Fasciculus (The main pathway connects the cochlear and vestibular nuclei with the nuclei of the extraocular muscles : oculomotor, trochlear, and abducent) • Olivocerebellar tract (Associated with voluntary movements
Solitarius nucleus (taste nucleus,7th , 9th , 10th cranial Ns). • Ambiguous nucleus (motor nucleus for 9th , 10th , and 11th cranial Ns)
Inferior cerebellar peduncle damage -→cerebellar ataxia
Spinal lemniscus -----→CONTRALATERAL loss of pain and temperature.
A:
The brainstem consists of the medulla oblongata, pons, and midbrain. It contains ascending sensory tracts, descending motor tracts, cranial nerve nuclei, cerebellar connections, and the reticular formation.(Cranial nerve nuclei = little clusters ("islands")Tracts = bundles of wires ("highways")Reticular formation = the mesh/net filling the spaces in between)
Lower medulla: Pyramidal decussation — crossing of most corticospinal fibers.
Middle medulla: Gracile and cuneate nuclei and sensory decussation — formation of the medial lemniscus.
Upper medulla: Olivary nuclei; hypoglossal, dorsal motor vagal, nucleus ambiguus, and other cranial nerve nuclei.
Lower pons: Facial colliculus level — abducens nucleus and facial nerve fibers.
Upper pons: Trigeminal motor nucleus and main sensory nucleus of CN V.
Lower midbrain: Inferior colliculus and trochlear nucleus (CN IV).
Upper midbrain: Superior colliculus, oculomotor nucleus (CN III), Edinger–Westphal nucleus, and red nucleus.
Exam trap: Identify the level first, then identify the nuclei and tracts present.
A:
The corticospinal tract carries voluntary motor commands from the cerebral cortex.
It descends through the cerebral peduncles, pons, and medullary pyramids.
Approximately 75–90% of fibers cross at the pyramidal decussation in the lower medulla to form the lateral corticospinal tract. The lecture emphasizes approximately 75%.
Most remaining fibers descend in the anterior corticospinal tract and may cross near their spinal termination.
A lesion above the pyramidal decussation usually causes contralateral weakness.
A lesion below the decussation affecting the lateral corticospinal tract causes ipsilateral weakness.
Clinical association: Medial medullary lesions can damage the pyramid and cause contralateral hemiparesis.
Exam trap: Pyramidal decussation = lower medulla; it is a motor crossing.
A:
1. Dorsal column–medial lemniscus pathway
Carries:
Fine/discriminative touch.
Vibration.
Conscious proprioception.
Pathway: Gracile/cuneate fasciculi → gracile/cuneate nuclei in the medulla → internal arcuate fibers cross at the sensory decussation → medial lemniscus ascends through the brainstem.
A lesion above the sensory decussation causes contralateral sensory loss.
2. Spinal lemniscus
Contains ascending pathways described in the lecture:
Lateral spinothalamic tract → pain and temperature.
Anterior spinothalamic tract → crude touch and pressure.
Spinotectal tract → orienting responses to sensory stimuli.
A brainstem lesion typically causes contralateral body pain-temperature loss.
3. Spinocerebellar pathways
Carry unconscious proprioceptive information to the cerebellum for coordination. The posterior spinocerebellar tract enters through the inferior cerebellar peduncle.
Exam trap: Medial lemniscus = fine touch, vibration, conscious proprioception; spinal lemniscus = body pain and temperature; spinocerebellar pathways = unconscious proprioception.
A:
Spinal trigeminal nucleus and tract: Pain and temperature from the face; extend through the medulla and lower pons.
Main sensory nucleus of CN V: Touch and pressure from the face; located in the pons.
Mesencephalic nucleus of CN V: Proprioceptive information, particularly from the muscles of mastication.
Trigeminal sensory pathways cross and ascend toward the thalamus in the trigeminal lemniscus.
Clinical application: In a lateral medullary lesion, damage to the spinal trigeminal nucleus/tract causes ipsilateral facial pain-temperature loss. Damage to the spinal lemniscus causes contralateral body pain-temperature loss.
This creates the classic crossed sensory deficit: ipsilateral face, contralateral body.
Exam trap: Spinal trigeminal = facial pain and temperature; main sensory nucleus = facial touch; mesencephalic nucleus = proprioception.Face ↓ Trigeminal nerve ↓ Trigeminal nucleus ↓ CROSS ↓ Road (trigeminal lemniscus) ↓ Brain
A:
Hypoglossal nucleus (CN XII): Tongue motor control. Damage produces ipsilateral tongue weakness.
Dorsal motor nucleus of vagus (CN X): Parasympathetic output to thoracic and abdominal viscera.
Nucleus solitarius: Visceral sensory information and taste; receives input associated with CN VII, IX, and X.
Nucleus ambiguus: Motor control of pharyngeal and laryngeal muscles through CN IX and X; damage causes dysphagia and hoarseness.
Vestibular nuclei (CN VIII): Balance; lesions can cause vertigo and nystagmus.
Cochlear nuclei (CN VIII): Auditory processing.
Inferior olivary nucleus: Connections with the cerebellum important for motor coordination and learning.
Medial longitudinal fasciculus (MLF): Coordinates conjugate eye movements by connecting vestibular and ocular motor nuclei.
Exam trap: Nucleus ambiguus → swallowing and voice; hypoglossal nucleus → tongue; vestibular nuclei → vertigo and nystagmus.
A:
Feature
Lateral medullary (Wallenberg)
Medial medullary
Typical artery
PICA
Vertebral artery branches
Main structures
Nucleus ambiguus, spinal trigeminal nucleus, spinal lemniscus, inferior cerebellar peduncle, vestibular nuclei
Pyramid, medial lemniscus, hypoglossal fibers
Motor deficit
Usually no prominent hemiparesis
Contralateral hemiparesis
Sensory deficit
Ipsilateral facial and contralateral body pain-temperature loss
Contralateral loss of fine touch, vibration, and conscious proprioception
Other clues
Dysphagia, hoarseness, vertigo, nystagmus, ipsilateral ataxia
Ipsilateral tongue weakness
Wallenberg mnemonic: PICA — pain-temperature crossing, ipsilateral ataxia, cranial nerve symptoms, and vestibular symptoms.
Exam trap: Hoarseness and dysphagia strongly suggest lateral medullary involvement of the nucleus ambiguus.
A:
Important pathways:
Corticospinal and corticonuclear fibers: Descend through the pons in longitudinal bundles.
Pontine nuclei: Receive input from the cerebral cortex.
Corticopontocerebellar pathway: Cortex → pontine nuclei → crossing transverse pontine fibers → middle cerebellar peduncle → cerebellum.
Medial lemniscus: Fine touch, vibration, and conscious proprioception.
Spinal lemniscus: Body pain-temperature and related sensory information.
Trapezoid body and lateral lemniscus: Auditory pathway toward the inferior colliculus.
Important cranial nerve nuclei:
CN VI — abducens nucleus: Abducts the ipsilateral eye through the lateral rectus.
CN VII — facial motor nucleus: Controls facial expression.
CN V — trigeminal motor nucleus: Controls muscles of mastication.
Main sensory nucleus of CN V: Facial touch and pressure.
CN VIII vestibular nuclei: Balance; extend across the pontomedullary region.
Clinical associations:
CN VI lesion → impaired abduction of the ipsilateral eye.
CN VII motor lesion → ipsilateral facial weakness.
CN V motor lesion → weakness of mastication.
Exam trap: Facial colliculus = abducens nucleus plus the internal genu of the facial nerve passing around it.
A:
Inferior colliculus level (lower midbrain):
Inferior colliculus: Auditory processing.
Trochlear nucleus (CN IV): Supplies the superior oblique muscle.
CN IV fibers decussate and emerge from the dorsal surface of the brainstem.
Superior colliculus level (upper midbrain):
Oculomotor nucleus (CN III): Supplies most extraocular muscles, excluding lateral rectus (CN VI) and superior oblique (CN IV).
Edinger–Westphal nucleus: Parasympathetic component of CN III; pupillary constriction and accommodation.
Superior colliculus: Visual orienting reflexes.
Red nucleus: Motor coordination.
Substantia nigra: Movement regulation and basal ganglia circuitry.
Other major structures:
Crus cerebri: Descending cortical motor and pontine fibers.
Superior cerebellar peduncle: Major cerebellar output pathway; decussates in the midbrain.
Medial and spinal lemnisci: Ascending body sensory pathways.
Exam trap: CN III = upper midbrain; CN IV = lower midbrain. A CN III lesion can cause ptosis, a dilated pupil, and a “down-and-out” eye.
Both are associated with lesions of the midbrain and can involve ipsilateral CN III palsy.
Weber syndrome:
CN III fascicle damage → ipsilateral oculomotor palsy.
Corticospinal fibers in the crus cerebri → contralateral hemiparesis/hemiplegia.
Classic pattern: ipsilateral CN III palsy + contralateral weakness.
Benedikt syndrome:
CN III fascicle damage → ipsilateral oculomotor palsy.
Red nucleus and nearby structures → contralateral involuntary movements or movement abnormalities.
Medial lemniscus involvement → contralateral impairment of discriminative touch, vibration, and proprioception.
Weakness may occur if descending motor fibers are also involved.
Exam trap:
Weber = eye palsy + weakness.
Benedikt = eye palsy + abnormal movements, often with sensory deficits.
A:
Clue
Localization
Pyramidal decussation
Lower medulla
Sensory decussation / medial lemniscus formation
Middle medulla
PICA + dysphagia + hoarseness + crossed pain-temperature loss
Lateral medulla (Wallenberg)
Contralateral weakness + contralateral dorsal-column sensory loss + ipsilateral tongue weakness
Medial medulla
Facial colliculus
Lower pons
Pontine nuclei and middle cerebellar peduncle
Pons
Trigeminal motor and main sensory nuclei
Upper pons
Inferior colliculus + CN IV nucleus
Lower midbrain
Superior colliculus + CN III and Edinger–Westphal nuclei
Upper midbrain
Ipsilateral CN III palsy + contralateral hemiparesis
Weber syndrome
Ipsilateral CN III palsy + contralateral abnormal movements ± sensory deficits
Benedikt syndrome
Rapid revision ❤
Alar plate = sensory; basal plate = motor (developmental link).
Medial lemniscus: Fine touch, vibration, conscious proprioception.
Spinal lemniscus: Body pain and temperature.
Spinal trigeminal nucleus: Facial pain and temperature.
Nucleus ambiguus: Swallowing and voice.
PICA: Wallenberg syndrome.
Pons → middle cerebellar peduncle.
CN III: Upper midbrain.
CN IV: Lower midbrain and exits dorsally.
Weber: CN III palsy + contralateral weakness.
Benedikt: CN III palsy + contralateral movement abnormalities, often sensory findings.
DIENCEPHALON
What are the parts of the diencephalon, and what are the main anatomical features of the thalamus?
How is the thalamus divided internally, and what are its main white-matter coverings?
What are the connections and functions of the anterior and medial thalamic nuclear groups?
What are the nuclei, connections and functions of the lateral thalamic group?
: What are the subdivisions of the ventral posterior nucleus, and how do the geniculate bodies function?
: Where are the intralaminar and reticular nuclei located, and what are their connections and functions?
Where is the hypothalamus located, and how are its nuclei organized?
What are the main afferent and efferent connections of the hypothalamus?
What are the major functions of the hypothalamus, and which nuclei are responsible?
What are the functions of the subthalamus and epithalamus, and what are the highest-yield diencephalon associations?
A:
A:
Diencephalon: Caudal part of the forebrain; consists of the thalamus, hypothalamus, epithalamus and subthalamus.
Thalamus: Largest part of the diencephalon; paired, oval masses of gray matter on either side of the third ventricle.
Main function: Relays almost all sensory information to the cerebral cortex, except olfaction.
Anterior end: Lies just behind the interventricular foramen.
Posterior end: Called the pulvinar, situated above the superior colliculus.
Lateral surface: Related to the posterior limb of the internal capsule.
Medial surface: Forms part of the lateral wall of the third ventricle; may connect to the opposite thalamus through the interthalamic adhesion (massa intermedia).
Superior surface: Related to the lateral ventricle and fornix.
Inferior surface: Continuous with the midbrain tegmentum; related to the hypothalamus anteriorly and subthalamus posteriorly.
A:
The thalamus consists mainly of gray matter and is organized by white-matter laminae:
Stratum zonale: Covers the superior surface.
External medullary lamina: Covers the lateral surface.
Internal medullary lamina: Y-shaped sheet of white matter that divides the thalamus into three main groups:
Anterior group
Medial group
Lateral group
The lateral group is subdivided into dorsal and ventral tiers.
Exam tip: The Y-shaped internal medullary lamina is the key landmark for understanding the thalamic nuclear groups.
A:
1. Anterior thalamic nuclei
Connections: Mammillary bodies via the mammillothalamic tract and the cingulate gyrus.
Functions: Emotional tone and recent memory; closely associated with the limbic system.
2. Medial thalamic group
Largest nucleus: dorsomedial nucleus.
Connections: Prefrontal cortex, hypothalamus and other thalamic nuclei.
Functions: Integrates sensory information and relates it to emotional feelings and subjective experiences.
High-yield association: Anterior thalamus = limbic system and memory; dorsomedial nucleus = emotion and integration.
A:
A. Dorsal tier
Nuclei: Lateral dorsal, lateral posterior and pulvinar.
Connections: Other thalamic nuclei, parietal, temporal and occipital lobes, and cingulate gyrus.
Function: Integration of sensory information between the thalamus and cerebral cortex.
B. Ventral tier
Nucleus
Main connections
Main function
Ventral anterior (VA)
Motor cortex, basal ganglia, substantia nigra and reticular formation
Motor control
Ventral lateral (VL)
Similar to VA, with additional input from cerebellum and red nucleus; projects to motor cortex
Influences motor activity
Ventral posterior (VP)
Sensory pathways, including medial and spinal lemnisci and trigeminal pathways
Sensory relay to the cortex
Memory aid: VA and VL are primarily motor; VP is primarily sensory
A:
Ventral posterior (VP) nucleus
VPL — ventral posterolateral: Receives body sensory information through the medial and spinal lemnisci.
VPM — ventral posteromedial: Receives trigeminal sensory information from the face and taste pathways.
Both project to sensory areas of the cerebral cortex.
Geniculate bodies — traditionally called the metathalamus:
- Medial geniculate body (MGB):
Input: Inferior colliculus.
Output: Auditory cortex.
Function: Hearing.
- Lateral geniculate body (LGB):
Input: Optic tract carrying retinal information.
Output: Visual cortex.
Function: Vision.
Exam traps: VPL = body sensation; VPM = face and taste; medial geniculate = hearing; lateral geniculate = vision
A:
Intralaminar nuclei
Location: Within the internal medullary lamina.
Inputs: Reticular formation, trigeminothalamic and spinothalamic tracts.
Outputs: Cerebral cortex and basal ganglia.
Function: Influence consciousness and alertness.
Reticular nucleus
Location: Between the external medullary lamina and internal capsule.
Inputs: Cerebral cortex and reticular formation.
Outputs: Other thalamic nuclei.
Function: Regulates thalamic activity under cortical influence.
Quick recall: Intralaminar nuclei = alertness; reticular nucleus = regulation of other thalamic nuclei.
A:
Extends from the optic chiasma to the mammillary bodies.
Forms the floor and part of the lateral wall of the third ventricle.
Fuses caudally with the tegmentum of the midbrain.
Its inferior surface includes the optic chiasma, tuber cinereum, infundibulum and mammillary bodies.
OMIM"
Optic chiasma → front
Mammillary bodies → back
Infundibulum → bottom
Midbrain tegmentum → behind
The fornix and mammillothalamic tract divide the hypothalamus into medial and lateral zones.
Medial zone nuclei AS- DVP
Part of the preoptic nucleus.
Anterior nucleus, suprachiasmatic nucleus and paraventricular nucleus.
Dorsomedial, ventromedial and infundibular (arcuate) nuclei.
Posterior nucleus. A Smart Doctor Visits Patients"
A = Anterior nuclei
D = Dorsomedial
V = Ventromedial
P = Posterior
Lateral zone nuclei "LST"
Part of the preoptic nucleus.
Supraoptic nucleus.
Lateral nucleus.
Tuberomammillary nucleus.
Lateral tubular nuclei.
Lateral side = "LST"
L
Lateral nucleus
S
Supraoptic
T
Tuberomammillary + Tuberal nuclei
LST = Lateral Side Team
Mammillary nuclei
A:
Afferent connections (inputs)
Somatic, gustatory and visceral afferents through collateral branches of the lemnisci and tractus solitarius.
Visual afferents.
Auditory afferents.
Olfactory information through the medial forebrain bundle.
Corticohypothalamic fibers from the frontal cortex.
Tegmental fibers from the midbrain.
Thalamo hypothalamic fibers from the dorsomedial thalamic nuclei.
Hippocampo hypothalamic fibers through the fornix. (Fornix For Memory)
Amygdalo hypothalamic fibers through the stria terminalis.(Amy is emotional)
Efferent connections (outputs)
Descending fibers to the brainstem and spinal cord, influencing autonomic neurons through pathways including the reticulospinal tract.
Mammillothalamic tract: MATC Mammillary body → anterior thalamic nucleus → cingulate gyrus.
Mammillotegmental tract: Mammillary body → reticular formation of the midbrain tegmentum.
Multiple pathways to the limbic system.
Exam tip: Fornix connects the hippocampus to the hypothalamus; stria terminalis connects the amygdala to the hypothalamus
A:
Function
Nucleus/region and role
Autonomic control
Anterior/preoptic regions influence parasympathetic responses; posterior/lateral regions influence sympathetic responses.
Circadian rhythms
Suprachiasmatic nucleus receives retinal input and regulates sleep–wake rhythms.
Temperature regulation
Anterior hypothalamus promotes heat-loss responses; posterior hypothalamus promotes responses to cold.
Anterior pituitary control
Hypothalamic releasing and release-inhibiting factors regulate anterior pituitary hormone secretion.
Posterior pituitary hormones
Supraoptic and paraventricular nuclei produce vasopressin and oxytocin, respectively, according to the lecture.
Hunger and thirst
Lateral hypothalamic region: hunger/thirst; bilateral destruction can cause anorexia and weight loss.
Satiety
Ventromedial nucleus: satiety; bilateral destruction can cause excessive eating and obesity.
Emotion and behavior
Lateral hypothalamic stimulation may cause rage; ventromedial stimulation may cause passivity. The hypothalamus works with the limbic system and prefrontal cortex.
Important clarification: Both the supraoptic and paraventricular nuclei contribute to vasopressin and oxytocin production; the lecture's one-to-one assignment is a simplified association.
A:
Subthalamus
- Subthalamic nucleus: Functionally associated with the basal nuclei and regulation of motor activity.
Epithalamus
Pineal gland: Secretes melatonin, involved in circadian rhythms.
Habenular nucleus: Part of the limbic system.
Posterior commissure: A commissural structure in the epithalamic region.
Rapid revision — memorize these associations
Largest diencephalic part → Thalamus.
Y-shaped white-matter sheet → Internal medullary lamina.
Anterior thalamic nuclei → Limbic system and memory.
VA/VL → Motor relay.
VPL → Body sensation.
VPM → Face sensation and taste.
Medial geniculate → Hearing.
Lateral geniculate → Vision.
Intralaminar nuclei → Consciousness and alertness.
Suprachiasmatic nucleus → Circadian rhythms.
Lateral hypothalamus → Hunger/thirst.
Ventromedial nucleus → Satiety.
Pineal gland → Melatonin.
Subthalamic nucleus → Motor regulation.
STRUCTURAL ORGANZITION OF NERVOUSSYSTEM
What are the major divisions of the nervous system, and what structures belong to each?
What is a neuron, and how are neurons classified by shape, axon length and function?
What are the main neuroglial cells, and how do gray matter, white matter, nuclei, ganglia and tracts differ?
What are the main anatomical features and internal organization of the spinal cord?
How is the brain divided, and what are the key features of the brainstem, cerebellum and ventricles?
What are the parts and main functions of the diencephalon and cerebrum?
How are spinal nerves organized, and what are the functions of their roots and rami?
How are cranial nerves classified, and what are the major sensory and autonomic ganglia?
: How is the autonomic nervous system organized, and how do its sympathetic and parasympathetic divisions differ?
: What are the afferent pathways of the ANS, and what are the most important exam distinctions from this lecture?
A:
Central nervous system (CNS): Brain and spinal cord.
Peripheral nervous system (PNS): Cranial nerves, spinal nerves and their ganglia.
Autonomic nervous system (ANS): Controls involuntary structures such as the heart, smooth muscle and glands; it is distributed throughout the CNS and PNS.
Sympathetic: Fight or flight; prepares the body for emergencies.
Parasympathetic: Rest and digest; conserves and restores energy.
Protection of the CNS: The brain and spinal cord are covered by three meninges — dura mater, arachnoid mater and pia mater — and surrounded by CSF in the subarachnoid space. The skull and vertebral column provide additional protection.
A:
A neuron is an excitable nerve cell consisting of a cell body and processes called neurites.
Dendrites: Receive information.
Axon: Conducts impulses away from the cell body; also called a nerve fiber.
Neurons communicate at synapses, using neurotransmitters.
By shape
Pseudounipolar: Posterior root ganglia.
Bipolar: Retinal bipolar cells.
Multipolar: Most neurons in the brain and spinal cord; includes stellate, pyramidal, fusiform and Purkinje cells.
By axon length
Golgi type I: Long axon, potentially 1 m or more.
Golgi type II: Short axon; often inhibitory and more numerous according to the lecture.
By function
Sensory (afferent): Carries information toward the CNS.
Motor (efferent): Carries impulses away from the CNS.
Interneurons: Located entirely within the CNS.
A:
Neuroglia
Astrocytes: Support neurons and nerve fibers; help form the blood–brain barrier.
Oligodendrocytes: Form myelin in the CNS.
Microglia: Immune effector cells of the brain.
Ependymal cells: Line the ventricles and are associated with CSF production.
Schwann cells: Form myelin in the PNS.
Nervous tissue organization
Term
Definition
Gray matter
Mainly neuronal cell bodies embedded in neuroglia
White matter
Mainly axons/nerve fibers embedded in neuroglia
Nucleus
Mass of neuronal cell bodies within the CNS
Ganglion
Collection of neuronal cell bodies outside the CNS
Tract
Bundle of axons within the CNS connecting gray-matter regions
Fasciculus / lemniscus
Larger collections of axons within the CNS
Peripheral nerve
Bundle of axons in the PNS
Exam trap: Oligodendrocyte = CNS myelin; Schwann cell = PNS myelin.
A:
General anatomy
Approximately 45 cm long, cylindrical and located in the vertebral canal.
Begins at the foramen magnum, continuous with the medulla oblongata.
Terminates around the lower border of L1, forming the conus medullaris.
The filum terminale is a prolongation of pia mater extending toward the coccyx.
Covered by the three meninges and surrounded by CSF.
31 spinal cord segments
8 cervical
12 thoracic
5 lumbar
5 sacral
1 coccygeal
Internal structure
Central, H-shaped gray matter, surrounded by white matter.
Gray matter contains two anterior (ventral) horns and two posterior (dorsal) horns, joined by a gray commissure containing the central canal.
Lateral horns contain sympathetic nuclei in thoracic and upper lumbar segments.
White matter is divided into anterior, lateral and posterior columns
A:
Major brain divisions
Forebrain: Cerebrum and diencephalon.
Midbrain: Connects forebrain and hindbrain.
Hindbrain: Pons, medulla oblongata and cerebellum.
Brainstem: Consists of the midbrain, pons and medulla oblongata.
Medulla oblongata: Connects the pons to the spinal cord; contains nuclei and ascending/descending tracts.
Pons: Lies anterior to the cerebellum, inferior to the midbrain and superior to the medulla; contains nuclei and ascending/descending tracts.
Midbrain: Contains nuclei and ascending/descending tracts; its cerebral aqueduct connects the third and fourth ventricles.
Cerebellum: Posterior to the pons and medulla; has an outer gray-matter cortex arranged in folia and inner white matter containing deep nuclei, including the dentate nucleus.
Ventricles
The medulla, pons and cerebellum surround the fourth ventricle.
The cerebral aqueduct connects the third and fourth ventricles.
A:
Diencephalon
Thalamus: Paired, egg-shaped gray-matter masses on either side of the third ventricle; relays and integrates most sensory information, except olfaction, to the cerebral cortex and other subcortical regions.
Hypothalamus: Forms the floor and lower part of the lateral wall of the third ventricle; integrates autonomic and endocrine functions, body temperature, body fluids, hunger and thirst.
Subthalamus: Inferior to the thalamus, between the thalamus and midbrain tegmentum.
Epithalamus: Includes the habenular nuclei and pineal gland.
Cerebrum
Two cerebral hemispheres connected by the corpus callosum and separated by the longitudinal fissure.
Four lobes: frontal, parietal, temporal and occipital.
Gyri are raised folds; sulci are grooves between them.
Contains outer cortical gray matter and central white matter.
Basal nuclei include the caudate nucleus, lentiform nucleus, amygdaloid nucleus and claustrum, as listed in the lecture.
Corona radiata fibers converge into the internal capsule.
Caudate nucleus lies medial to the internal capsule; lentiform nucleus lies lateral to it.
Each hemisphere contains a lateral ventricle.
A:
There are 31 pairs of spinal nerves: 8 cervical, 12 thoracic, 5 lumbar, 5 sacral and 1 coccygeal.
Anterior (ventral) root: Motor/efferent fibers carry impulses away from the CNS.
Posterior (dorsal) root: Sensory/afferent fibers carry impulses toward the CNS.
Posterior root ganglion: Contains the cell bodies of sensory neurons.
The two roots unite at the intervertebral foramen to form a mixed spinal nerve, containing sensory and motor fibers.
After emerging, the spinal nerve divides into:
Posterior ramus: Supplies muscles and skin of the back.
Anterior ramus: Supplies the anterolateral body wall and limbs; anterior rami form nerve plexuses near the roots of the limbs.
Cauda equina: The vertebral column grows more rapidly than the spinal cord during development, leaving lumbar and sacral nerve roots descending below the end of the cord.
Exam traps
8 cervical nerves but only 7 cervical vertebrae.
Anterior root = motor; posterior root = sensory.
Both anterior and posterior rami contain mixed motor and sensory fibers.
A:
There are 12 pairs of cranial nerves.
Predominantly sensory
CN I — Olfactory
CN II — Optic
CN VIII — Vestibulocochlear
Predominantly motor
CN III — Oculomotor
CN IV — Trochlear
CN VI — Abducens
CN XI — Accessory
CN XII — Hypoglossal
Mixed
CN V — Trigeminal
CN VII — Facial
CN IX — Glossopharyngeal
CN X — Vagus
Sensory ganglia listed in the lecture
Posterior root ganglia.
Trigeminal ganglion — CN V.
Geniculate ganglion — CN VII.
Spiral and vestibular ganglia — CN VIII.
Superior and inferior ganglia of CN IX and CN X.
Autonomic ganglia
Paravertebral sympathetic trunks.
Prevertebral ganglia, such as celiac and renal ganglia.
Ganglia close to or embedded within visceral walls.
Autonomic ganglia associated with CN III, VII, IX and X.
A:
The ANS innervates involuntary structures, including the heart, smooth muscle and glands. Its efferent pathway generally consists of two neurons:
Preganglionic neuron.
Postganglionic neuron, with synapses between them in an autonomic ganglion.
Sympathetic division — thoracolumbar outflow
Preganglionic cell bodies: Lateral gray columns of T1–L2.
Postganglionic neurons: Sympathetic trunks, prevertebral ganglia or suprarenal medulla.
Chromaffin cells of the suprarenal medulla are modified postganglionic neurons.
Function: Fight or flight.
Parasympathetic division — craniosacral outflow
Preganglionic cell bodies: Brainstem nuclei associated with CN III, VII, IX and X, and spinal cord segments S2–S4.
Postganglionic neurons: Ganglia close to or within the walls of the target viscera, or ganglia associated with the relevant cranial nerves.
Postganglionic fibers are characteristically relatively short.
Function: Rest and digest.
A:
Autonomic afferent pathways
Visceral sensory fibers travel from the organs toward the CNS.
Sympathetic visceral afferent cell bodies are located in the posterior root ganglia of the corresponding spinal nerves.
Parasympathetic visceral afferents travel with cranial nerves or pelvic splanchnic nerves; their cell bodies lie in sensory ganglia of cranial nerves or posterior root ganglia of the relevant spinal nerves.
The lecture notes that the afferent component of the autonomic system is part of the general afferent component of the nervous system.
High-yield exam revision
CNS = brain and spinal cord; PNS = nerves and ganglia.
Astrocytes = support and blood–brain barrier.
Oligodendrocytes = CNS myelin; Schwann cells = PNS myelin.
Nucleus = CNS cell-body collection; ganglion = PNS cell-body collection.
Gray matter = mainly neuronal cell bodies; white matter = mainly axons.
Anterior root = motor; posterior root = sensory.
Posterior ramus = back; anterior ramus = anterolateral trunk and limbs.
Brainstem = midbrain + pons + medulla.
Cerebral aqueduct = third to fourth ventricle.
Sympathetic = T1–L2; parasympathetic = CN III, VII, IX, X and S2–S4.
Sympathetic = fight or flight; parasympathetic = rest and digest.
SPINAL TRACTS
What are spinal tracts, and how are ascending sensory pathways organized?
What sensations does the spinothalamic tract carry, and what is its pathway?
: What sensations travel through the dorsal column pathway, and where does the pathway cross?
: What is the function of the spinocerebellar pathways, and how do the anterior and posterior tracts differ?
What are the functions of the spinotectal, spinoreticular, spino-olivary and visceral sensory pathways?
: What is the organization of descending motor pathways, and how does the corticospinal tract descend and cross?
What are the origins and functions of the reticulospinal, tectospinal, rubrospinal and vestibulospinal tracts?
How are sensory fibers arranged within the spinothalamic and dorsal column pathways, and why is this clinically important?
What are the spinal cord lesions in tabes dorsalis and poliomyelitis?
What are the characteristic findings of a complete spinal cord hemisection (Brown-Séquard syndrome)?
A:
Spinal tracts are bundles of nerve fibers within the CNS that carry information between different regions.
Sensory information
Exteroceptive: Pain, temperature and touch originating from outside the body.
Proprioceptive: Information from muscles and joints about body position and movement.
Three-neuron chain of ascending pathways
First-order neuron: Cell body in the dorsal root ganglion or cranial sensory ganglion; carries sensory information into the CNS.
Second-order neuron: Cell body in the spinal cord or brainstem; commonly crosses to the opposite side and projects toward the thalamus or another target.
Third-order neuron: Usually in the thalamus; projects to the cerebral sensory cortex.
Three major ascending pathways
Spinothalamic pathway.
Dorsal column–medial lemniscal pathway.
Spinocerebellar pathway.
A:
The spinothalamic tract forms part of the anterolateral system.
Lateral spinothalamic tract: Pain and temperature.
Anterior/ventral spinothalamic tract: Crude touch and pressure.
Pathway
First-order neuron: Cell body in the dorsal root ganglion. Its axon enters the spinal cord and may ascend or descend 1–2 segments in Lissauer's tract.
It synapses in the dorsal horn, including the substantia gelatinosa or nucleus proprius.
Second-order axons cross obliquely through the spinal cord and ascend contralaterally toward the thalamus.
Third-order neurons in the ventral posterolateral (VPL) nucleus project through the posterior limb of the internal capsule and corona radiata to the sensory cortex.
Exam tip: A spinal cord lesion affecting the spinothalamic tract causes contralateral pain and temperature loss below the lesion, often beginning a little below the lesion because of the initial segmental course
A:
Modalities
Fine/discriminative touch.
Vibration.
Conscious proprioception.
Pathway
First-order neurons: Cell bodies in dorsal root ganglia; axons ascend ipsilaterally in the posterior white column.
Fasciculus gracilis: Mainly lower-limb and lower-trunk information; lies medially.
Fasciculus cuneatus: Mainly upper-limb and upper-trunk information; lies laterally.
Second-order neurons: Gracile and cuneate nuclei in the caudal medulla.
Their axons form the internal arcuate fibers, cross in the medulla and form the medial lemniscus.
The medial lemniscus ascends to the VPL thalamus.
Third-order neurons project through the posterior limb of the internal capsule and corona radiata to the sensory cortex.
Critical distinction: This pathway crosses in the medulla, whereas the spinothalamic pathway crosses in the spinal cord.
A:
Main function: Carry unconscious proprioceptive information from muscles, tendons and joints to the cerebellum for coordination of limb movement and maintenance of posture.
Posterior spinocerebellar tract
First-order neurons: Dorsal root ganglia.
Synapse on second-order neurons in Clarke's column (nucleus dorsalis).
Ascends mainly ipsilaterally to the medulla.
Enters the cerebellum through the inferior cerebellar peduncle.
Terminates in the cerebellar cortex.
Anterior spinocerebellar tract
Second-order neurons are associated with Clarke's column in the lecture.
Most fibers cross in the spinal cord and ascend through the medulla and pons.
Enters the cerebellum through the superior cerebellar peduncle.
Fibers that crossed in the spinal cord are believed to cross back within the cerebellum.
Cuneocerebellar tract
Equivalent pathway for the upper limb.
Originates from the accessory/external cuneate region described in the lecture as the nucleus cuneatus.
Enters the cerebellum through the inferior cerebellar peduncle on the same side.
A:
Spinotectal tract: Crossed; provides sensory input for spinovisual reflexes, helping direct the eyes and head toward a stimulus.
Spinoreticular tract: Crossed or uncrossed; influences levels of consciousness and arousal.
Spino-olivary-cerebellar tract: Crossed; carries cutaneous and proprioceptive information toward the cerebellum.
Visceral sensory tracts: Carry visceral sensory information and join the spinothalamic pathways, according to the lecture.
Quick recall
Orienting eyes/head toward a stimulus → Spinotectal.
Influencing consciousness → Spinoreticular.
Sensory information reaching the cerebellum through the olive → Spino-olivary-cerebellar.
A:
Motor neuron organization
Upper motor neuron (UMN): Cell body in a supraspinal center; axon descends in a motor pathway.
Lower motor neuron (LMN): Cell body in a motor nucleus of the brainstem or anterior horn of the spinal cord; axon ultimately innervates skeletal muscle.
The lecture describes a descending chain involving a cortical neuron, an interneuron and an anterior horn motor neuron, although some pathways allow direct cortical input to motor neurons.
Pyramidal/corticospinal tract
Originates from pyramidal cells in layer V of the cerebral cortex.
Approximately two-thirds of fibers arise from the precentral gyrus and one-third from the postcentral gyrus, according to the lecture.
Fibers converge in the corona radiata and pass through the posterior limb of the internal capsule.
Descend through the midbrain, pons and medullary pyramids.
At the lower medulla, approximately 75% cross to form the lateral corticospinal tract.
Remaining fibers descend as the anterior corticospinal tract and eventually cross near their spinal termination, mainly in cervical and upper thoracic regions.
Function: Skilled voluntary movement, especially precise movements of distal limb muscles
A:
Tract
Origin/course
Main function
Reticulospinal
Reticular formation → spinal cord
Facilitates or inhibits motor-neuron activity; contributes to descending autonomic control
Tectospinal
Superior colliculus; most fibers cross near their origin
Reflex postural movements in response to visual stimuli
Rubrospinal
Red nucleus; fibers cross at the level of the nucleus
Influences spinal motor neurons; facilitates flexors and inhibits extensors, as described in the lecture
Vestibulospinal
Lateral vestibular nucleus; descends uncrossed
Facilitates extensor activity and inhibits flexors to help maintain balance
Pyramidal versus extrapyramidal
Pyramidal: Skilled voluntary movement, especially fine distal movements.
Extrapyramidal: Basic movement patterns, posture, balance and adjustment of muscle tone.
A:
The lecture describes different medial-to-lateral arrangements:
Spinothalamic tract: Cervical to sacral fibers are arranged from medial to lateral.
Dorsal white column: Sacral to cervical fibers are arranged from medial to lateral.
Clinical significance
External pressure on the spinal cord may affect the spinothalamic fibers in an orderly pattern.
The lecture notes that pain and temperature loss may first appear in the sacral dermatomes with external compression affecting the spinothalamic tract.
Exam trap: The somatotopic arrangement differs between the spinothalamic tract and dorsal columns. Do not reverse their orders.
A:
Tabes dorsalis
Caused by syphilis.
The lecture describes selective destruction of nerve fibers where the posterior roots enter the spinal cord.
This affects sensory pathways, particularly those associated with the posterior roots and dorsal columns.
Poliomyelitis
Acute viral infection affecting neurons of the anterior gray columns of the spinal cord and motor nuclei of cranial nerves.
Damages lower motor neurons, potentially causing flaccid paralysis.
Immunization has greatly reduced its incidence.
High-yield distinction
Tabes dorsalis → sensory fibers/posterior root entry region.
Poliomyelitis → anterior horn motor neurons.
A:
After the period of spinal shock has ended, a complete hemisection produces:
Ipsilateral LMN paralysis at the level of the lesion, due to damage to segmental motor neurons or roots.
Ipsilateral spastic UMN paralysis below the lesion, due to interruption of the corticospinal tract.
Ipsilateral band of cutaneous anesthesia at the lesion level.
Ipsilateral loss of fine touch, vibration and conscious proprioception below the lesion, due to damage to the dorsal columns before they cross in the medulla.
Contralateral loss of pain, temperature and crude touch below the lesion, due to interruption of spinothalamic fibers that have crossed within the spinal cord.
LEFT side loses:
🏇 Motor knights → weakness/spastic paralysis
🎻 Vibration musicians → vibration & proprioception
🏠 Local workers at lesion level → LMN signs
RIGHT side loses:
🔥 Pain & temperature messengers
Master localization table
Finding
Likely tract/structure involved
Contralateral pain and temperature loss
Spinothalamic tract
Ipsilateral vibration and proprioception loss below spinal lesion
Dorsal columns
Ipsilateral spastic weakness below spinal lesion
Corticospinal tract
Flaccid paralysis from anterior horn damage
Lower motor neurons
Unconscious proprioception to cerebellum
Spinocerebellar pathways
Visual reflex turning of eyes/head
Spinotectal pathway
Balance and extensor tone
Vestibulospinal tract

ZAW MENINGES
Name the three meninges and describe the two layers of cranial dura mater.
: Name the four dural folds and describe their locations and the arterial supply of the dura.
What are dural venous sinuses, and what are the contents and clinical importance of the cavernous sinus?
Describe the arachnoid and pia mater, and name the major subarachnoid cisterns and their contents or clinical associations.
Differentiate the extradural, subdural and subarachnoid spaces, including the bleeding source and classic CT appearance of each hematoma.
Describe the termination of the spinal meninges, the filum terminale and ligamentum denticulatum, and distinguish lumbar puncture, epidural anesthesia and spinal anesthesia.
Name the components of the ventricular system, describe the location of each ventricle and trace their connections.
: Where is CSF produced, how does it circulate, and where is it absorbed? Include the choroid plexus structure and daily production.
What is hydrocephalus, how can ventriculostomy help, and what are the main functions of the glymphatic system?
What are the highest-yield clinical and anatomical associations from the meninges and ventricular system lecture?
Diploic veins- run between the internal and external tables of compact bone in the roof of the cranial cavity
uncal herniation: Compression of CN III near the tentorial notch may cause ipsilateral pupillary dilation and impaired eye movements.
Cistern of the great cerebral vein (quadrigeminal cistern / cisterna superior)-
contains the great cerebral vein of Galen and pineal gland.
Parinaud syndrome: Pineal region masses may compress the dorsal midbrain, causing impaired upward gaze, light-near dissociation, and convergence-retraction nystagmus.
Venous abnormalities: Contains the great cerebral vein (vein of Galen); vein of Galen aneurysmal malformations can produce severe cerebral venous and cardiovascular complications, particularly in neonates.
Neurosurgery: Important anatomical landmark for surgical approaches to pineal region tumors and deep cerebral venous structures
head trauma common in elderly fall- subdural hematoma
Surrounded by gray matter, the gray commissure- central canal
CSF enters the venous system through two routes: (1) most CSF enters the venous system by transport through the cells of the arachnoid granulations into the dural venous sinuses, and (2) some CSF moves between the cells making up the arachnoid granulation
A:
Dura mater: Tough outer layer.
Arachnoid mater: Delicate middle layer; does not follow the brain's sulci.
Pia mater: Thin inner layer, closely adherent to the brain and follows its grooves and fissures.
Cranial dura mater:
Outer periosteal layer: Attached to the skull; acts as the periosteum of the cranial cavity and contains meningeal arteries.
Inner meningeal layer: Lies close to the arachnoid and continues as spinal dura through the foramen magnum.
The two layers are fused except where they separate to enclose the dural venous sinuses.
Exam trap: Pia enters the sulci; arachnoid bridges over them.
A:
Falx cerebri: Crescent-shaped, vertical fold between the cerebral hemispheres; anteriorly attached to the crista galli and frontal crest; posteriorly blends with the tentorium cerebelli.
Tentorium cerebelli: Horizontal fold covering and separating the cerebellum from the cerebral hemispheres; attached posteriorly along the grooves for the transverse sinuses.
Falx cerebelli: Small midline fold in the posterior cranial fossa; attached to the internal occipital crest and tentorium.
Diaphragma sellae: Small horizontal shelf covering the hypophyseal fossa.
Dural arterial supply:
Anterior cranial fossa — anterior meningeal arteries from the ethmoidal arteries.
Middle cranial fossa — middle and accessory meningeal arteries from the maxillary artery.
Posterior cranial fossa — posterior and other meningeal arteries
A:
Dural venous sinuses
Endothelial-lined spaces between the periosteal and meningeal layers of cranial dura.
Venous drainage ultimately reaches the internal jugular veins.
The sigmoid sinus continues as the internal jugular vein through the jugular foramen.
Emissary veins connect extracranial veins with dural sinuses and have no valves, allowing infection to spread into the cranial cavity.
Cavernous sinus
Located on either side of the body of the sphenoid bone, beside the sella turcica.
Receives blood from cerebral veins, ophthalmic veins, the central retinal vein, emissary veins, and connected venous sinuses.
Structures passing through the sinus proper:
Internal carotid artery.
Abducent nerve (CN VI).
Structures in its lateral wall, superior to inferior:
Oculomotor nerve — CN III
Trochlear nerve — CN IV
Ophthalmic nerve — V1
Maxillary nerve — V2
Clinical importance: Infection can spread from facial/orbital regions through venous connections and cause cavernous sinus thrombosis.
Exam trap: CN VI and the internal carotid artery pass through the sinus proper; CN III, IV, V1 and V2 lie in the lateral wall.
A:
Arachnoid mater
Thin, avascular membrane that lines the inner surface of the dura but is not adherent to it.
Separated from pia by the CSF-filled subarachnoid space, which contains blood vessels and fine trabeculae.
Bridges over the sulci; widening of the subarachnoid space forms cisterns.
Pia mater
Thin, delicate membrane closely investing the brain.
Follows the brain's grooves and fissures and is closely applied to cranial nerve roots at their origins.
Four important cisterns:
Cistern
Location / contents
Clinical association
Cerebellomedullary (cisterna magna)
Between medulla and inferior cerebellum
Communicates with the fourth ventricle via the foramen of Magendie
Pontine (prepontine)
Ventral surface of pons; basilar artery
Basilar artery aneurysm or thrombosis
Interpeduncular
Between temporal lobes, at the brain base; contains the circle of Willis
Posterior communicating artery aneurysm may compress CN III
Great cerebral vein (quadrigeminal)
Near the splenium and superior cerebellum; contains vein of Galen and pineal gland
Pineal-region masses may cause Parinaud syndrome
Clinical associations to remember:
Chiari malformation can crowd the cisterna magna and obstruct CSF flow.
Dandy–Walker malformation is associated with posterior fossa cystic enlargement and fourth-ventricle abnormalities.
Parinaud syndrome may cause impaired upward gaze, light-near dissociation and convergence-retraction nystagmus.
A:
Condition
Location
Typical bleeding source
Classic clue
Epidural (extradural) hematoma
Between skull and dura
Middle meningeal artery
Biconvex/lens-shaped; typically limited by cranial sutures
Subdural hematoma
Between dura and arachnoid
Bridging veins
Crescent-shaped; can cross sutures but is limited by dural reflections
Subarachnoid hemorrhage (SAH)
Between arachnoid and pia
Ruptured intracranial aneurysm
Blood in subarachnoid spaces; sudden thunderclap headache and neck stiffness
Important anatomical distinctions:
The extradural space in the cranium is normally a potential space.
The lecture states that a true anatomical subdural space does not normally exist.
The subarachnoid space is a real space containing CSF and blood vessels.
Exam trap:
Middle meningeal artery → epidural hematoma.
Bridging veins → subdural hematoma.
Ruptured aneurysm → subarachnoid hemorrhage.A:
Spinal dura mater: Continuous with cranial dura through the foramen magnum. The dural sac ends at the lower border of S2.
Arachnoid mater: Lies against but is not adherent to the dura; also ends at S2.
Pia mater: Closely covers the spinal cord.
Ligamenta denticulata: Lateral extensions of pia that pass between nerve roots and attach to the arachnoid and dura.
Filum terminale: Extension of pia from the conus medullaris that descends toward the coccyx; its dural portion continues to the coccyx.
Procedures:
Lumbar puncture: Accesses the CSF-filled subarachnoid space, commonly at L3–L4 or L4–L5.
Spinal anesthesia: Anesthetic is injected into the subarachnoid space.
Epidural anesthesia: Anesthetic is injected into the epidural space without piercing the dura.
Exam trap: The spinal cord ends above the termination of the dural and arachnoid sacs, leaving the cauda equina within the lower subarachnoid space.
A:
The ventricular system consists of ependyma-lined, CSF-filled cavities:
Two lateral ventricles: Largest cavities; located in the cerebral hemispheres. Each has a body and anterior, posterior and inferior horns.
Interventricular foramina of Monro: Connect each lateral ventricle to the third ventricle.
Third ventricle: Slit-like cavity of the diencephalon between the two thalami.
Cerebral aqueduct of Sylvius: Passes through the midbrain and connects the third and fourth ventricles.
Fourth ventricle: Located between the pons and medulla anteriorly and the cerebellum posteriorly.
Central canal: Continues from the fourth ventricle into the medulla and spinal cord; the lecture describes expansion into a terminal ventricle.
Key fourth-ventricle communications:
Median aperture (foramen of Magendie) and lateral apertures (foramina of Luschka) → subarachnoid space.
Inferiorly → central canal.
Exam trap — memorize the sequence:
Lateral ventricles → foramina of Monro → third ventricle → cerebral aqueduct → fourth ventricle → apertures of Magendie and Luschka → subarachnoid space.
A:
Production
CSF is produced mainly by the choroid plexuses in the lateral, third and fourth ventricles.
The lecture gives a production rate of approximately 400–500 mL/day.
Choroid plexuses consist of vascular pia mater (tela choroidea) covered by modified ependymal epithelial cells.
Circulation
Lateral ventricles.
Interventricular foramina of Monro.
Third ventricle.
Cerebral aqueduct.
Fourth ventricle.
Foramina of Magendie and Luschka into the subarachnoid space.
CSF circulates around the brain and spinal cord.
Absorption
Mainly through arachnoid granulations (arachnoid villi) projecting into the superior sagittal sinus and lateral lacunae.
CSF enters the venous system by transport through and between cells of the arachnoid granulations.
Clinical connection: Abnormal accumulation of CSF within the ventricles can cause hydrocephalus. A blockage of CSF pathways, such as from an infratentorial tumor, may increase intracranial pressure.
A:
Hydrocephalus
Abnormal accumulation of CSF within the ventricles.
May result from obstruction of CSF pathways and lead to increased intracranial pressure, headaches and neurological deficits.
Ventriculostomy involves placing a catheter into a ventricle, usually a lateral ventricle, to drain excess CSF or monitor intracranial pressure.
Glymphatic system
- A brain-wide, glia-associated fluid transport system that facilitates exchange between CSF and interstitial fluid (ISF) and helps clear metabolic waste.
Main mechanisms
CSF enters along periarterial spaces.
CSF–ISF exchange is facilitated by astrocytic endfeet and aquaporin-4 (AQP4).
Solutes and waste drain through perivenous and other clearance pathways.
Functions and clinical relevance
Helps clear amyloid-β, tau and other metabolic waste.
Function is closely linked to sleep and vascular dynamics.
Dysfunction is implicated in Alzheimer's disease, cerebral small vessel disease and sleep-related disorders.
Interstitial fluid (ISF) = the fluid bathing brain cells within the brain tissue.
Periarterial space = a pathway/tunnel surrounding blood vessels that can contain and transport fluid.
Exam trap: Arachnoid granulations are the main site of CSF absorption into venous sinuses; the glymphatic system is involved in CSF–ISF exchange and metabolic waste clearance
A:
Emissary veins: Valveless connections that can allow infection to spread into the cranial cavity.
Cavernous sinus thrombosis: Important because of the sinus's connections with ophthalmic and facial venous pathways and its cranial nerve contents.
CN VI: Passes through the cavernous sinus proper alongside the internal carotid artery.
CN III compression: May cause ptosis, diplopia and pupillary dilation; associated with posterior communicating artery aneurysm or uncal herniation.
Cisterna magna: Communicates with the fourth ventricle through the foramen of Magendie.
Epidural hematoma: Middle meningeal artery; biconvex appearance.
Subdural hematoma: Bridging veins; crescent-shaped appearance.
Subarachnoid hemorrhage: Often due to a ruptured aneurysm; sudden severe headache and neck stiffness.
CSF pathway obstruction: Can produce hydrocephalus.
Lumbar puncture: Commonly performed at L3–L4 or L4–L5; spinal anesthesia enters the subarachnoid space, while epidural anesthesia does not pierce the dura.
Glymphatic system: CSF–ISF exchange and waste clearance; associated with sleep and AQP4.
Dura Partitions & Vascular Supply
📐 Falx Cerebri: Crescent-shaped dural fold between cerebral hemispheres; attaches anteriorly to the crista galli of ethmoid bone and frontal crest.
⛺ Tentorium Cerebelli: Horizontal shelf separating cerebrum from cerebellum; encloses the tentorial notch.
🩸 Middle Meningeal Artery (MMA): Enters via foramen spinosum in the middle cranial fossa; supplies the dura mater and lies directly beneath the pterion.
🩸 Head Traumas & Imaging Patterns (100% Exam Clues)
🟡 Epidural Hematoma (EDH):
Cause: Rupture of Middle Meningeal Artery due to temporal bone fracture.
Clinical: Classic lucid interval (brief recovery followed by rapid collapse).
CT Scan: Lens-shaped / Biconvex hyperdensity that does NOT cross suture lines.
🌙 Subdural Hematoma (SDH):
Cause: Tearing of bridging veins (common in elderly/alcoholics).
CT Scan: Crescent-shaped hyperdensity that CAN cross suture lines.
💥 Subarachnoid Hemorrhage (SAH):
Cause: Ruptured intracranial berry aneurysm (e.g., Circle of Willis).
Clinical: Sudden "worst headache of my life" (thunderclap) + neck stiffness.
CT Scan: High-density blood pooling inside the sylvian fissures and basal cisterns.
🐍 Cavernous Sinus Anatomic Layout
🎯 Structures Passing INSIDE (Directly through sinus):
🔴 Internal Carotid Artery (ICA)
👁 Abducent Nerve (CN VI) → Most susceptible to injury/palsy during thrombosis!
🧱 Structures in LATERAL WALL (Top to Bottom):
Oculomotor Nerve (CN III)
Trochlear Nerve (CN IV)
Ophthalmic Division of Trigeminal (CN V1)
Maxillary Division of Trigeminal (CN V2)
⚠ Danger Triangle of Face: Facial infections spread to cavernous sinus via valveless emissary veins and ophthalmic veins → Cavernous Sinus Thrombosis.
🌊 Subarachnoid Cisterns & Clinical Syndromes
📍 Cisterna Magna (Cerebellomedullary Cistern): Largest cistern between medulla & inferior cerebellum. Target for cisternal puncture.
👁 Interpeduncular Cistern: Contains Circle of Willis. Posterior communicating artery aneurysm or Uncal Herniation depresses CN III → ipsilateral dilated pupil & ptosis.
🌲 Quadrigeminal Cistern (Cistern of Great Cerebral Vein): Contains Vein of Galen and Pineal Gland. Masses here cause Parinaud Syndrome (paralysis of upward gaze, light-near dissociation).
💧 Ventricular System & CSF Flow
🔄 Flow Sequence: Lateral Ventricles → Foramen of Monro → 3rd Ventricle → Cerebral Aqueduct (Sylvius) → 4th Ventricle → Out via Foramen of Magendie (Median) & Foramina of Luschka (Lateral) → Subarachnoid Space → Absorbed by Arachnoid Granulations into Superior Sagittal Sinus.
🏭 CSF Secretion Rate: 400–500 mL/day by modified ependymal/choroidal cells.
🕳 Central Canal: Extends through spinal cord; LACKS choroid plexus.
🧹 Glymphatic System (The "New Trend" Exam Topic)
🛌 Primary Function: Brain's waste clearance pathway (clears amyloid-β and tau), active mainly during sleep.
💧 Key Transporter: Driven by astrocytic endfeet and Aquaporin-4 (AQP4) water channels.
💔 Glymphopathy Link: Dysfunction implicated in Alzheimer's disease, small vessel disease, and epilepsy.