Reproduction



Case study’
Presumptive: N/V, aversion to smells, urinary frequency, amenorrhea, breast tenderness, fatigue, quickening
Probable: Positive pregnancy test, weight gain, cervical changes, ballottement (pressive fetal movement is elicited when provider pushed on the cervix), colostrum present, Chadwick sign (blue tint to cervix), Linea nigra, Hegar sign (softening of the istrums of the uterus). Braxton hicks, fundus palpation height, blood pregnancy test, mask of pregnancy, darkining and elarging of nipples.
Positive: Fetal heartrate on an ultrasound
G2P0A1L0
Pregnant 2, none born alive, abortion one, living none
AMA: advance materinal age 35 and above
Dilation and evacuation prodcudure
Had postpartum depression after loss of first pregancy
Iron deficiey anemia which is common
Basal body temp to see when the pt is ovulating
Folic acid preven neuro two defects which occurs during the first two weeks of pregancy
25=30j lbs wieght gain
Prenatal vitamin: its for baby nutriontal need can make n/v worse
Iron
Flu, Covid, RSV good for baby bc crossess placenta to baby to rpvie aqcuired imunity
TDAP 9tentnus, diphetheria, pertusisi (whopping cough) mom gets its week 27-36 week of pregancy, and caregicers should get it as well to protect baby
Do not give live vaccines such as MMR, Vaccerlia, nasal flu, HPV
MMR (measules, murps, rubella) live want to know if they are immune, would give it to them after delivery, get a boaster if they aint immune
A immunocomprimsed/high risk would get pneumonia,
If non-immune and does not have active hep B infection - consider hep B vaccine
20 week morphology scan - looks at baby and amnitic fluid and placenta placement
Rh postive baby give rohgan after 72 hrs of birth

Coffe less than 200 mg a day, alchol, unpastruazed cheese,engergy drink, raw fish (high in mercury) /sushi listera & samollia, tuna, salmon (big fish/old fishe, deep sea fish)
Quadrplic marker screening, mood screening/postrum depression, non invasim prenatal testing, group data, blood typing,GBS for baby, non-fetal stress test, measures baby fetal Hr and movement’=, Auad screen has many false postives.
Ultrasound, fetal heart, fundal heiggt, vs,balloment, fetal monitoring, weight checks, pica, support system, cervical checks, Dropplor
Timester expectations 9baby weight,
poly
WIC- woman and children food and formula, does not cover diappers
SNAP - food stamps for low income
food drive/bank
Medicaid
walking, yoga, water arobic, kegals low impact, 150 mins per week. lay on left side
Indirect coombs test:
Expect during trimester
1: wieght gain 1-5 lbs, N/V, fatiguie, increse urination, amnehorrhea, implantation bleeding (spotting), cravings, breat tenderness/nipple changes, changes in mood
2:lessened discomfty sympoms, weight gain 1lb a week, quickining, gender reveal 20 week, vaginal discharge, glucose tolerance test, dental changes, skin changes, limia nigra, avoid sleeping on back
3:lordosis (curving of spine in the back), swelling in legs, hemrrhoids, baxtons hicks, birth plan, feeding plan, postpartum depression vs baby blues, parenting classess, nesting. Signs of impending labourl lossing mucus plug, braxton hicks(sit down and water should relive it), increase of kicking of baby
…………………………………………………………………………………………………………………………………………………………..
Aminocentesis is inbasive testing to look for fetal abnormalities or lung maturity during 3 trimester
FNST is non-invasive and uses an external monitor to assess babys HR and o2. CNS system and HR.
Danger warning signs
No fetal movement
Abd pain excessive or intense cramping
DVT( heat, pain, leg swelling)
no compression stocking on DVT leg
Signs of infection0 fever, hypereminsis,
Oluguira
Bleeding
Thoughts of harming self or other, fall on body, chest pian, stroke sympoms
Gush of fluid or contrasn leaking of fluid - color, amount
ph is alkaline for the amonic fluid
Ferning test to test if its amonic fluid vs urine
sever headache that wont go away (preecplamisa) blurry vision, URQ pain, sweeling on hands,
Magnesium sulfate drip and RR 10 stop immediately and give calicum glucanate. Magnesium sulfate is given for preeclampsia to prevent seizurez. Magnesium toxcitiy - resp suppersion, halos of light.
36 weeks
Position is baby spine to moms spine,
Leopold maneuver to feel for the baby position if baby is breached under med in hospital externally turn baby.
Effaced is how thin the cervix is.
latent phase
Cervix begins to dilate 0-6 cm, contractions begin mild and irregular, lasting 30-40 secs, Q 10:30 minutes.
Talks through contractions, excited/anxious, birthing ball, sitting backwards on the toilet, breathing excerzie.
Interventions: Ambulation, water, warm showers
pain control: Warm bath (if membranes are not ruptured)
If preterm and membranes are intact, to stop labor administer: Terbutaline
If baby gonna be born preterm adminster betamethasone to speed up development of baby lungs. Also magnesium seulfate for neuro protection for baby.
NPO/clear liquid
120-160 FHR norm
Early decela is a peack before the contraction bc baby head is trying to move
Late deceal is after the contraction, placenta
Variable decials is cord compression
For late decial and variable decels: 10-15 nonrebreather, stop oxy, L side, md
Reasurring is vairability, accelerations, early deceleration baby moving down
Mom is not dilating/thinning on own?
Cerivcal ripening agents (prostaglandins): Misoprostol a prostagladin E2
Cooks ballon
Mom contraction not progressing?
Uterine stiumaltion: Oxytocin (pitocin
IV nalbuphine (opiod) have naloxone reversal
Active phase labour
Lamaze breathing, distraction, counter pressure, involve support person,
Epidural: bupivacain/gentanyl non-system goes in epidural space
Give bolus of LR to prevent BP drop after, can they hold still, get baseline of vs, platelet level stable, foley cath, full maternal bladder increase risk of hemorrhage. D/c foley before pushing baby. Itching
Nalbuphine systempic opiod risk of low bp and suppressed RR for mom and baby
Transition phase feels like I need to push she finna push
+2 station in birth cannal +3 baby is coming out
Not push when doing cerival check when feeling imblace cord leave the hand stays there until mom goes to or for c-section, okacebta
foot,, butt, hand
Only thing ya should be feeing is the head
if stoping oxy due to late decelas then can cont oxytocin post delivery
Oil around do they wont tear
crowining you see the head
lightling: baby is moving down therefore the baby goes from diaphram to down bc preasure is off
quiz wednesday mood and afect and thruday postpartum
+Quiz only on Antepartum and intrapartum
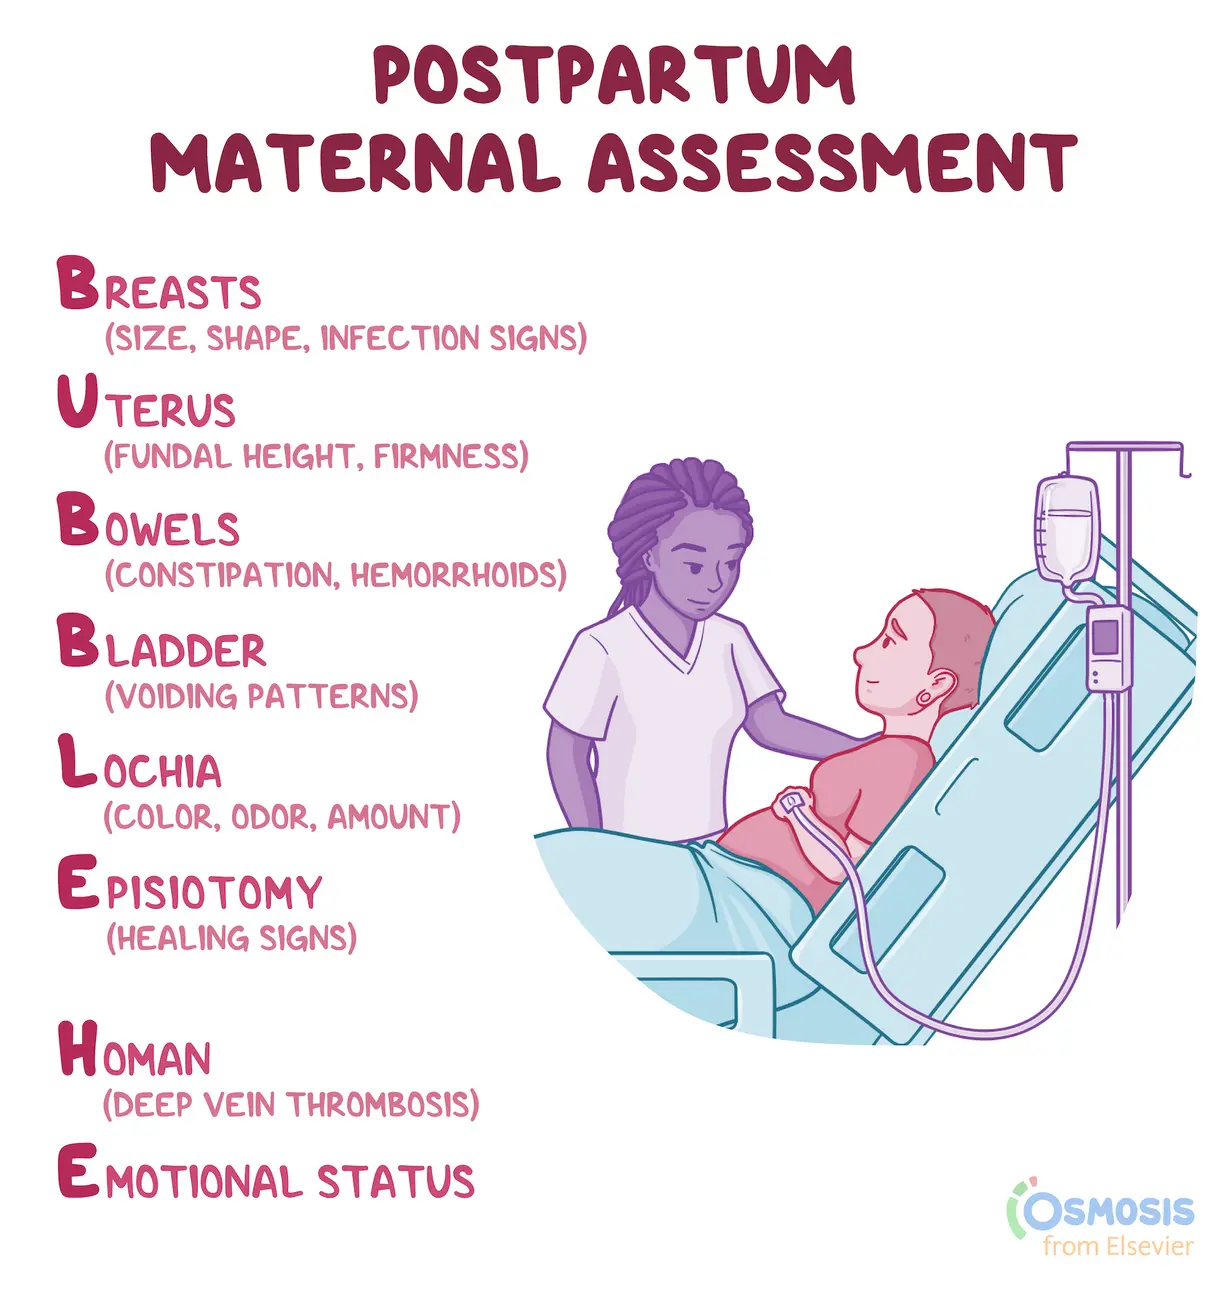
Postpartum hemorrhage is blood loss greater than 1,000 mL with c-section and 500 mL vaginal birth with s/s of hypovolemia such as hypotension and tachycardia within 24 hrs of babies birth.
Causes of postpartum hemorrhage: Uterine atony, a failure of uteretes to contract and retract. Episiotomy, uterine inversive, oxytocin, partial placenta.
A full bladder can displace uterus, encourage void.
If soft and bogggy massage the fundus.
Oxytocin/mistropol, iv fluids, massaging the fundus to help stop the bleeding.
Tocolytics used to stop uterine contracts and delay birth for up to 48 hours
IV magnesium sulfate, calcium channel blockers
Slow labor
Indications
Contraindications: Active hemorrahge, fetal distress, feltal inviability, fetal growth restrion, heart disease, intrauterine infection, fetal abnormality incompatible with life, sever preeclampsa, preterm premature rupture of membranes.
SE: Magnesium sulfate Monitor deep tendon reflexes and respiratory effort for overdose. Nifedipine: Hypotension Indomethacin: Should be given BEFORE 32 weeks, monitor for n/v and gastritis.
Antepartum: TDaP vaccine, influenza vaccine, RSV vaccin, RhoGAM, foodborne illnesses (listeria). Norm weight gain during pregnacy. 1,2,3 trimester expectation. PICA, Nagele rule. Danger warning signs fetal movement, bleeding. Fetal heart tones/sounds, doppler, ultrasound, ballottement, pap smear, amniocentesis, non-stress test. Pregnancy test, human chorionic gonadotropin, UA, basic metabolic, CBC, STI, HIV, blood type and Rh testing, glucouse tolerance tests, indirect coombs test, group beta streptococcus testing, rubella titer, hepatitis B titier.
Folic acid: Prevents neural tubes defects which occur during the first two weeks of pregnancy
Prenatal vitamin: its for baby nutritional need can make n/v worse
Food
Avoid alcohol, limit caffeine to <200 mg/day, avoid fish high in mercury (tuna?).
Betamethasone: promotes fetal lung maturity
Rhogam: At 28 weeks and within 72 hours of delivery to prevent formation of Rh antibodies. ONLY given to Rh- mom who gave birth to Rh+ baby
Intrapartum: Norm changes during labor and deliver: stages of labor, crowning, rupture of membranes, bloodyshow/mucous plug, cervical ripening, fetal position, fetal presentation, lightening, leopold maneuvers. Fetal monitoring (external and internal) interpretation. TOCO monitoring interpretation. l systemic opiods (nalbuphine).
Uterine stimulants: Oxytocin
Oxytocin
Indications: Induction of labour and postpartum hemorrhage
MOA: Uterine stimulant
SE: Painful contractions, uterine tachysytole, uterine rupture
NC: Closely moniotr contraction (every 2-3 minutes, for 60-90 seconds), maternal/fetal VS. Magnesium sulfate can be used to relax the uterus.
Uterine tocolytics: Terbutaline
Terbutaline
Indications: DELAYS preterm labor
MOA: Relaxation of the uterus
SE: Tachycardia, angina, hypokalemia, dyshythmias, restlessness, tremor
NC: used for pregancies less than 37 weeks. Short term.
Maternal and fetal disress if used more than 48-72 hours
When flying, turbuelence delays arrive time just like terbutaline delays the arrival of the baby
Prostaglandins: Misoprostol
Misoprostol
Indications: Induces labor by ripening the cervix, and treating postpartum bleeding by inducing uterine contractions
MOA: Causes uterine contractions
SE: Dysmenorrhea, GI upset, uterine hyperstimulation
NC: Assess woman of childbearing age for pregnancy before administration due to it causing miscarriage, premature birth, birth defects.
Magnesium sulfate
S/S of magnesium toxicity: Deep tendon reflexes, low RR, decreased LOC
REVERSAL AGENT: Calcium gluconate
Epidural
Adminstered in epidural space, reduces/eleiminates pain/sensation below the umbilicus. May cause maternal HYPOtension and fetal BRADYcardia
NC: Administer IV fluids and position mom on side, monitor FHR and maternal vitals continuously
Baby has judangdce give biliuruben, uv lights, and feeding